Multi-database transcriptomic screening to identify subtype-selective cell surface targets for development of SNAP-tag based immunotherapeutics

Thabo Matshoba
1,4,#

,
Viacheslav Bolotnikov
2,#
,
Marc Henry
1,4
,
Nkhasi Lekena
1,4
,
Roger Hunter
3,4
,
Stefan Barth
1,4,*
*Correspondence to:
Stefan Barth, Medical Biotechnology and Immunotherapy Research Unit, Institute of Infectious Disease and Molecular Medicine, Faculty of Health Sciences, University of Cape Town, Cape Town 7700, Western Cape, South Africa; Centre for the Development of Cancer Therapeutics for Africa (CDCTA), Faculty of Health sciences, University of Cape Town, Cape Town 7700, Western Cape, South Africa.
E-mail: stefan.barth@uct.ac.za
Comput Biomed. 2026;1:202615. 10.70401/cbm.2026.0023
Received: April 23, 2026Accepted: August 06, 2026Published: August 06, 2026
This article belongs to the Special lssue Applications of Bioinformatics in Precision Medicine and Translational Healthcare
Abstract
Aims: Cervical cancer is the second most common cancer globally in women of reproductive age. Current immunotherapies offer only moderate improvement in overall survival for metastatic or refractory disease, highlighting the need for more effective, patient-directed immunotherapies.
Methods: A unified pipelinereprocessed all The Cancer Genome Atlas (TCGA) and genotype tissue expression (GTEx) samples from raw reads using identical alignment and quantification parameters to screen a curated set of 259 high-confidence surface protein genes. This analysis provided the foundation for selecting differentially overexpressed cell surface receptors as potential antibody-drug conjugate (ADCs) targets . Recombinant single chain variable fragment (scFv)-O6-alkylguanine-DNA alkyltransferase (SNAP) fusion proteins were expressed, purified and characterised using immunoblotting. The dose-dependent and selective cytotoxicity of an auristatin F-conjugated (scFv)-SNAP fusion protein was verified in vitro.
Results: Bioinformatic screening revealed 30 potential targets overexpressed in cervical carcinoma (Cervical Squamous Cell Carcinoma and Endocervical Adenocarcinoma (CESC)) vs. healthy tissues. Tissue-of-origin analysis (endocervix vs. ectocervix) further refined priorities. These results, together with supporting evidence from the literature, justified drug production.. The (scFv)-SNAP fusion proteins exhibited strong surface binding across cervical cancer cell lines and, when conjugated to auristatin F, showed dose-dependent cytotoxicity at nanomolar concentrations, confirming the differences observed in transcriptomic analyses of endo- vs. ectocervix profiling.
Conclusion: Bioinformatics and in vitro validation synergize powerfully from initial screening through subtype refinement to iterative target confirmation, enabling a precision medicine approach for cervical cancer-specific immunotherapies. The (scFv)-SNAP-auristatin F (ADC) conjugates reproduced this refinement, showing highly promising potential.
Keywords
Cervical cancer, surfaceome screening, tissue-of-origin, SNAP-tag, immunotherapy, tumour heterogeneity, endocervix, ectocervix
1. Introduction
The World Health Organization Global Strategy for cervical cancer elimination aims to achieve improvements by 2030[1] across several target groups. These include vaccinating 90% of young women by the age of 15, having 70% of women up to 35 years of age screened using high-performance testing, and providing treatment for 90% of women with pre-cancer and 90% of women with invasive cancer. These aspirations have arisen because cervical cancer remains the fourth most commonly occurring cancer among women globally and the second most common cancer among reproductive-age women[2]. Additionally, cases of cervical cancer are expected to increase by more than 55% by 2050 if current trends in population growth and ageing continue[3].
On treatment opportunities, Bevacizumab and nimotuzumab are monoclonal antibodies targeting vascular epithelial growth factor (VEGF) and epidermal growth factor receptor (EGFR), respectively, that elicit an antitumour response by binding to the respective receptors, thereby inhibiting tumour growth pathways while tagging tumour cells for antibody-dependent cellular cytotoxicity (ADCC)[4-6].
Using either antibody in combination with cisplatin-based chemoradiation therapy (CCR) has been shown to provide a greater than 50% reduction in tumour size compared to the CCR-treated group alone over a 3-month follow-up period[7]. This highlights the importance of effective targeted cancer therapy to elicit tumour cell-specific killing using improved approaches compared to naked monoclonal antibody therapy. An emerging option in this regard is the antibody-drug conjugates (ADCs), which comprise a disease-specific monoclonal antibody, a linker, and a cytotoxic payload[8,9]. Our group has been working specifically with O6-alkylguanine-DNA alkyltransferase (SNAP)-tagged scFvs, which enable payload conjugation at a single, specific site on the antibody compared to the heterogeneous decoration when using full-size immunoglobulin Ig antibodies. This allows for an optimal 1:1 stoichiometric ratio[10-12] for generating an (scFv)-ADC, which offer great promise in reducing premature release of the cytotoxic payload[8,13,14].
A factor of paramount importance for ADC efficacy and safety is the selection of a target cell-surface receptor that is substantially overexpressed in tumour tissue relative to healthy tissues, while minimising on-target off-tumour toxicity to maximise therapeutic potency. Bioinformatic approaches offer a powerful and scalable route to this selection, and Sinkala et al. recently demonstrated, in the context of breast cancer, that machine learning and transcriptomic analyses of cell surface receptor expression profiles across tumour and healthy tissue datasets can directly predict drug response and identify receptors whose normal tissue expression is associated with adverse drug reactions[15]. This integrative framework established that the most therapeutically suitable cell surface receptors are those selectively overexpressed in tumour tissue compared to all healthy tissues, which illuminates a principle that extends beyond breast cancer and is directly applicable to the rational design of ADC targets in cervical cancer.
Moreover, cervical cancer is not a single entity since squamous cell carcinoma (SCC) and adenocarcinoma arise from distinct cells of origin in the ectocervix and endocervix, respectively, and these subtypes exhibit distinct surface receptor expression profiles that cannot be resolved through cohort-level analysis alone[16,17]. A subtype-aware transcriptomic screen, benchmarked against cervical tissue-of-origin references rather than a generic healthy composite, is therefore essential for identifying targets that are selective for each clinical context and avoiding the nomination of candidates that are substantially expressed in normal cervical epithelium. In this study, we applied this principle to an unbiased screen of 259 high-confidence surface protein genes across 304 primary the cancer genome atlas (TCGA)-cervical adenocarcinoma and squamous carcinoma (CESC) tumours, using multi-layered analysis to progress from global overexpression discovery through histological subtype refinement to molecular subpopulation stratification. The resulting candidate targets, mesothelin (MSLN), trophoblast cell surface antigen 2 (TROP-2), and zinc transporter protein (LIV-1), were then taken forward for validation using recombinant (scFv)-SNAP fusion ADCs conjugated to auristatin F. These were tested across a panel of cervical cancer cell lines representing both SCC and adenocarcinoma origins to confirm that transcriptomic subtype predictions translate directly into differential in vitro cytotoxic responses.
2. Methods
2.1 Cell culture
Cervical cancer cell lines HeLa (American Type Culture Collection (ATCC) CCL_2), SiHa (ATCC HTB_35), and ME180 (ATCC HTB_33), the immortalized human keratinocyte cell line HaCaT (CVCL_0038), and the human rhabdomyosarcoma cell line TE671 (CVCL_1756) were cultured in Dulbecco’s Modified Eagle Medium (DMEM). The human embryonic kidney cell line HEK293T (ATCC CRL_3216), the human acute promyelocytic leukemia cell line HL60 (ATCC CCL_240), and the metastatic cervical cancer cell line CaSki (ATCC CRL_1550) were cultured in Roswell Park Memorial Institute (RPMI) 1640 medium. All media were supplemented with 10% (v/v) foetal bovine serum (FBS) and 1% (v/v) penicillin-streptomycin (10,000 U/mL penicillin and 10,000 μg/mL streptomycin). Cells were maintained at 37 °C in a humidified incubator with 5% CO2.
2.2 (scFv)-SNAP fusion protein expression and purification
The (scFv)-SNAP fusion proteins were transiently expressed in HEK293T cells cultured in RPMI 1640 medium supplemented with 10% (v/v) FBS and 1% (v/v) penicillin-streptomycin. Cells were transfected with (scFv)-SNAP expression plasmids using X-tremeGENETM HP DNA Transfection Reagent (Roche, Switzerland) according to the manufacturer’s instructions. Transfection efficiency was assessed 96 h post-transfection by labelling cells with SNAP-Surface® Alexa Fluor® 405, followed by flow cytometric analysis on a BD LSRFortessaTM II flow cytometer. Transfected HEK293T cells were selected using ZeocinTM (100 mg/mL; Thermo Fisher Scientific, USA).
The anti-solute carrier family 39 member 6 (SLC39A6; αLIV-1) and anti-tumor-associated calcium signal transducer 2 (TACSTD2; αTROP-2) and anti-mesothelin (αMSLN) (scFv)-SNAP fusion proteins were purified from HEK293T cell culture supernatants by immobilized metal affinity chromatography (IMAC) using a 5 mL Ni2+ Sepharose affinity column (His-Trap Excel, GE Healthcare, USA) mounted on an ÄKTA Avant 25 system (GE Healthcare, Germany). Eluted fractions were analysed by 10% sodium dodecyl sulfate-polyacrylamide gel electrophoresis (SDS-PAGE) and visualized with AcquaStain Protein Gel Stain (Bulldog Bio, USA). SDS-PAGE images were visualized using the Gel Doc XR+ System (Bio-Rad, USA).
Protein identity was further confirmed by Western blot analysis, which detected the N-terminal 10× His-tag incorporated to facilitate purification and detection. Briefly, the proteins were transferred from an SDS-PAGE gel to a polyvinylidene fluoride (PVDF) membrane. The membrane was immediately blocked with fat-free milk (1 h) at room temperature and subsequently incubated with a mouse anti-polyhistidine-horseradish peroxidase (HRP) antibody (A7058-1VL, Sigma Aldrich, USA) (1:2,000 dilution in fat-free milk) for 2 h. Finally, the membrane was blotted with 2 mL of Pierce 1-Step Ultra 3,3′,5,5′-tetramethylbenzidine (TMB)-Blotting Solution (1-2 min) (Thermo Fisher Scientific, USA) for colorimetric detection of anti-SLC39A6 (αLIV-1), anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP fusion proteins. To verify the integrity and functionality of the C-terminal SNAP-tag, purified fusion proteins were conjugated with SNAP-Surface® Alexa Fluor® 488 as previously described[8]. Successful conjugation of the (scFv)-SNAP fusion proteins with SNAP-Surface® Alexa Fluor® 488 was confirmed by 10% SDS-PAGE, followed by fluorescence imaging using an iBrightTM FL1500 Imaging System (Thermo Fisher Scientific, USA).
2.3 Binding studies
2.3.1 Flow cytometry
Purified (scFv)-SNAP fusion proteins were conjugated to SNAP-Surface® Alexa Fluor® 647 as previously described[8]. Quantitative binding of the Alexa Fluor® 647-labelled fusion proteins to the LIV-1-, TROP-2-, and MSLN-expressing cervical cancer cell lines CaSki, HeLa, SiHa, and ME180, as well as the LIV-1-, TROP-2-, and MSLN-negative control cell lines HaCaT, TE671, and HEK293T, was assessed by flow cytometry. Briefly, 5 × 10⁵ cells were washed with 1× Phosphate-Buffered Saline (PBS) and stained with LIVE/DEADTM Fixable Violet Dead Cell Stain (1:1,000; Thermo Fisher Scientific, USA) in the dark on ice for 30 minutes. Cells were then washed with Fluorescence-Activated Cell Sorting (FACS) buffer (0.1% sodium azide, 2% FBS, and 1× PBS) and incubated with 50 µL Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins in the dark on ice for 30 minutes. The concentration of (scFv)-SNAP fusion proteins per cell line was determined using the methods described by Mungra et al.[18]. Subsequently, cells were washed twice with FACS buffer, resuspended in 200 μL PBS, and analysed on a BD LSRFortessaTM II flow cytometer (BD Biosciences, USA). Flow cytometry data were analysed using FlowJo v10.9.0 (BD Biosciences).
2.3.2 Confocal microscopy
HeLa, SiHa, ME180, CaSki, HEK293T, TE671, and HaCaT cells were seeded onto 22 × 22 mm glass coverslips in 6-well plates at a density of 1 × 10⁴ cells per coverslip and allowed to adhere overnight. Afterwards, cells were washed twice with 1× PBS and incubated with 200 μL of 10 µM Alexa Fluor® 647-conjugated (scFv)-SNAP fusion protein for 30 min at 37 °C. Thereafter, cells were washed with 1× PBS and incubated with 200 μL of a 1:5,000 dilution of Hoechst nuclear counterstain (Thermo Fisher Scientific, USA) for 5 min. Following incubation, cells were washed with 1× PBS, fixed with 4% paraformaldehyde for 20 min at room temperature, and washed again with 1× PBS. Coverslips were mounted onto glass slides using Mowiol mounting medium (Merck, USA) and left to dry overnight in the dark. Fluorescence images were acquired using a Zeiss LSM 880 Airyscan confocal laser scanning microscope equipped with 40× and 100× oil immersion objectives.
2.4 Cell viability
Purified (scFv)-SNAP fusion proteins were conjugated to BG-modified auristatin F as previously described[19]. The cytotoxicity of generated (scFv)-SNAP-auristatin F ADCs was assessed using the 2,3-bis(2-methoxy-4-nitro-5-sulfophenyl)-2H-tetrazolium-5-carboxanilide (XTT) cell proliferation assay. The LIV-1-, TROP-2-, and MSLN-expressing cervical cancer cell lines CaSki, HeLa, SiHa, and ME180, as well as the LIV-1 (TE671)-, TROP-2 (HL60)-, and MSLN (HaCaT and HEK293T) -negative control cells, were seeded in 96-well plates at a density of 5 × 10³ cells per well and allowed to adhere overnight at 37 oC, 5% CO2 atmosphere with 95% humidity. The ADCs were prepared by two-fold serial dilution. Cells were treated with ADC concentrations ranging from 31.25 to 1,000 nM to determine the half-maximal inhibitory concentration (IC50). For the αLIV-1 ADC, an extended concentration range of 0.313-10 μM was used to accurately determine the IC50. All treatments were performed in triplicate with two technical replicates. After 72 h of incubation, cell viability was determined by colorimetric monitoring of XTT reduction to formazan at 450-nm absorbance wavelength and 655-nm emission wavelength using the iMark Microplate Absorbance Reader (Bio-Rad, USA). Each experiment was carried out in triplicate (n = 3) with two technical replicates. Data were normalized with respect to the negative (100% cell viability) and positive (0% cell viability) controls, and the results were presented as percentages of cell viability against the log of drug concentration. The concentration corresponding to a 50% reduction in cell viability (IC50 value) was determined using GraphPad Prism v10.1.1 software (https://www.graphpad.com/).
2.5 Statistical analysis
Each experiment was conducted with a minimum of three biological/independent replicates performed on different days. Each repeat was subjected to duplicate analysis (n = 3). Statistical evaluation involved Student’s t-tests (relative to the negative cell line), using GraphPad Prism v10.1 for Windows (GraphPad Software, USA). A significant threshold of p < 0.05 was employed for all statistical tests. The cell viability results are expressed as means ± standard deviation of the mean. The data were normalised to be presented as a percentage relative to the untreated cells (i.e., untreated cells at 100% cell viability and dimethyl sulfoxide (DMSO)-treated cells at 0% viability). Nonlinear curve fitting was performed using a Log(concentration) vs. Normalised response (R2 ≥ 0.95).
2.6 Bioinformatics
All analyses were performed in R using the data.table and matrixStats packages. RNA-seq expression data for TCGA-CESC tumours (n = 304, primary tumours) and genotype tissue expression project (GTEx) healthy tissues (n = 7,597 samples, 52 tissue types) were obtained from the University of California, Santa Cruz (UCSC) Xena Toil recompute, a unified pipeline that reprocessed all TCGA and GTEx samples from raw reads using identical alignment and quantification parameters[20,21]. All values were stored as log2(transcripts per million (TPM) + 0.001), and as a consequence, zero-expressed genes produce negative values (log2(0.001) = -9.97), which are expected and valid. Because both tumour and normal samples derive from the same pipeline, fold-change calculations are direct subtractions in log2 space and require no additional cross-dataset normalisation. Male-specific tissues (testis, prostate) were excluded from all normal comparisons. The candidate surface-protein universe was based on the cell surface protein atlas (CSPA), an experimentally derived catalogue of human cell-surface proteins mapped by cell-surface-capture mass spectrometry (https://wlab.ethz.ch/CSPA, downloaded 25 November 2025). From this catalogue, we retained high-confidence, constitutively-surface candidates, prioritising specificity over sensitivity: because no single automated criterion cleanly separates antibody-accessible surface proteins from proteins that are only transiently at the surface, or that are annotated at the membrane but functionally intracellular or otherwise non-targetable, this selection was deliberately conservative. We acknowledge that some genuine surface targets may have been excluded as a consequence. This step retained 795 candidate surface genes. This set was then cross-referenced with human protein atlas (HPA) plasma-membrane annotation (version 25.0, downloaded 25 November 2025; ‘Subcellular location’ field, restricted to entries with experimental evidence of plasma-membrane localisation; (https://www.proteinatlas.org), and genes matching ribosomal (ribosomal protein large/ribosomal protein small (RPL/RPS)), mitochondrial (MT-) and histone (HIST) patterns were removed as known contaminants. The intersection of the retained CSPA surfaceome with HPA plasma-membrane annotation, after contaminant removal, yielded the final 259 high-confidence surface-protein genes taken forward for expression analysis. Gene identifiers were matched across resources on official HUGO Gene Nomenclature Committee (HGNC) symbol, with Ensembl gene IDs from the expression matrix mapped to symbols via the GTEx annotation. The curated 795-gene surfaceome is provided with the analysis code, which regenerates the resulting 259-gene surface universe by cross-referencing it with the HPA plasma-membrane annotation. Per-gene tumour medians were computed across all 304 TCGA-CESC samples. Per-tissue normal medians were computed across all verified GTEx samples for each of the 52 tissue categories, and the overall normal reference was taken as the median of these tissue medians. Four sequential filters were applied to identify overexpressed surface targets: tumour median TPM ≥ 5 (log2 ≥ 2.32), log2 fold-change ≥ 2 versus the pan-GTEx normal median, normal tissue median log2 < 5 (TPM < 32) to exclude ubiquitously expressed genes, and expression in ≥ 20% of tumours at TPM ≥ 1. Statistical significance was assessed by Wilcoxon rank-sum tests (one-tailed, tumour > normal) for all 259 genes with Benjamini-Hochberg correction applied across the full discovery set. Of the 259 surface genes, 30 passed all four filters. These thresholds were chosen to enforce, respectively, robust tumour expression (median TPM ≥ 5), a clear tumour-versus-normal difference (≥ 4-fold, i.e. log2 ≥ 2), absence of high constitutive expression in normal tissue (normal median TPM < 32), and expression in a substantial fraction of tumours rather than rare outliers (≥ 20% at TPM ≥ 1). For tissue-of-origin analysis, the Xena/Toil matrix contained only 6 ectocervix and 4 endocervix samples, insufficient for stable median estimates. Dedicated GTEx v10 cervix files (ectocervix n = 24, endocervix n = 23) were therefore downloaded separately and processed to match the Toil scale: raw TPM values were log2-transformed with the same pseudocount (log2(TPM + 0.001)) before fold-change calculation. Bootstrapped 95% confidence intervals (2,000 resamples) were computed on tissue-of-origin fold-change estimates to quantify uncertainty as a function of normal sample size. A tissue-wide expression heatmap was generated using the pheatmap package, displaying log2 fold-change of the top 30 genes across 29 representative GTEx tissues selected to cover vital organs, cervical subtypes, other critical tissues, and low-expression tissues.
2.6.1 Tumour histology stratification
TCGA-CESC tumours were assigned to squamous cell carcinoma (n = 243), adenocarcinoma (n = 46), adenosquamous (n = 5) or unclassified/other (n = 10) using the cBioPortal clinical-sample annotation. Each subtype was compared to its cell of origin, SCC versus normal ectocervix and adenocarcinoma versus normal endocervix, using the dedicated GTEx v10 cervix references on the identical log2 (TPM + 0.001) scale, with bootstrap 95% confidence intervals (2,000 resamples) for each fold-change. SCC and adenocarcinoma tumours were also compared directly by Wilcoxon rank-sum test, and the proportion of positive tumours (TPM ≥ 1) was recorded per subtype.
2.6.2 LIV-1 subgroup sensitivity
For LIV-1 (SLC39A6), tumours were stratified by expression z-score to identify a high-expressing subpopulation. To confirm the subgroup signal was not an artefact of a single cut-off, the analysis was repeated across a range of z-score thresholds (0.5, 1.0, 1.5, 2.0, 2.5); a primary threshold of ≥ 1.5 was used for reporting. At each threshold, a permutation test (10,000 iterations, random draws matched to the subgroup size) assessed whether the observed subgroup fold-change could arise by chance, and bootstrap 95% confidence intervals (10,000 resamples) were computed on the subgroup median fold-change (seed 42).
2.6.3 Independent bulk cohorts
Two independent bulk cervical cohorts were analysed internally (no cross-dataset merging): GSE63514 (24 normal cervix, 28 cervical cancer; Affymetrix U133 Plus 2.0, log2 robust multi-array average (RMA)) was processed with gene expression omnibus (GEO) series query, retaining the highest-expressed probe per gene and comparing cancer versus normal by one-sided Wilcoxon test with Benjamini–Hochberg correction; GSE151666 (68 pre-treatment primary tumours, bulk RNA-seq, TPM) was used to confirm target expression and prevalence.
2.6.4 Single-cell RNA-seq
Two public cervical single-cell datasets were analysed in Seurat v5: GSE208653 (4 normal, 2 high-grade squamous intraepithelial lesion (HSIL), 2 SCC, 1 adenocarcinoma) and GSE197461 (5 adenocarcinoma, 3 squamous patients), both 10× Genomics. Per-sample matrices were quality-filtered (200 < nFeature_RNA < 7,000, < 20% mitochondrial reads), normalised, dimensionally reduced (2,000 variable features, 30 principal components) and clustered (resolution 0.5); clusters were assigned to major cell types by canonical markers, and mean target expression and percent-positive cells quantified per cell type, per subtype and in malignant versus normal epithelium (seed 42).
2.6.5 Protein-level immunohistochemistry
Protein-level evidence was obtained from Human Protein Atlas immunohistochemistry (version 25.1): staining intensity in normal ectocervical squamous and endocervical glandular epithelium, and the distribution of staining intensities across cervical-cancer patients.
2.6.6 Data availability and reproducibility
The datasets analysed in this study are publicly available. TCGA-CESC tumour expression and GTEx healthy-tissue profiles were obtained from the UCSC Xena Toil recompute (https://xenabrowser.net); GTEx bulk-tissue and v10 cervix (ectocervix, endocervix) expression were obtained from the GTEx portal (https://gtexportal.org). The Cell Surface Protein Atlas is available at https://wlab.ethz.ch/CSPA/ and the Human Protein Atlas (version 25.0) at https://www.proteinatlas.org. The independent validation cohorts are available from NCBI Gene Expression Omnibus under accessions GSE63514, GSE151666, GSE208653 and GSE197461 (https://www.ncbi.nlm.nih.gov/geo). All custom R code used to process the datasets, perform the statistical analyses and generate the figures has been provided to editors and reviewers as Supplementary materials.
3. Results
3.1 Bioinformatic analysis
To identify candidate cell-surface antigens for SNAP fusion protein development, a systematic screen of the cervical cancer surfaceome was performed. Starting from a curated set of 259 high-confidence surface protein genes, we compared expression profiles across 304 primary TCGA-CESC tumours against 7,597 GTEx healthy tissue samples spanning 52 tissue types. Candidates were retained only if they were genuinely and consistently expressed in the tumour compartment, substantially overexpressed relative to normal tissue, and absent or low in healthy tissues, ensuring that shortlisted targets combined therapeutic relevance with a favourable safety profile, with a full pipeline detailed in Section 2.
3.2 Global screen: 30 overexpressed surface targets in TCGA-CESC
Applying all filters, 30 genes passed with fold-change (FC) ranging from 2.04 to 9.42 (median FC 3.40), all statistically significant after multiple testing correction (false discovery rate (FDR) < 0.0001). This list represents genes that are broadly and consistently overexpressed in cervical cancer relative to the full spectrum of normal human tissues. The top 10 candidates are shown in Table 1; the full results are provided in Table S1, together with a tissue-wide expression heatmap in Figure 1. Genes other than the targets discussed in this study are anonymised.
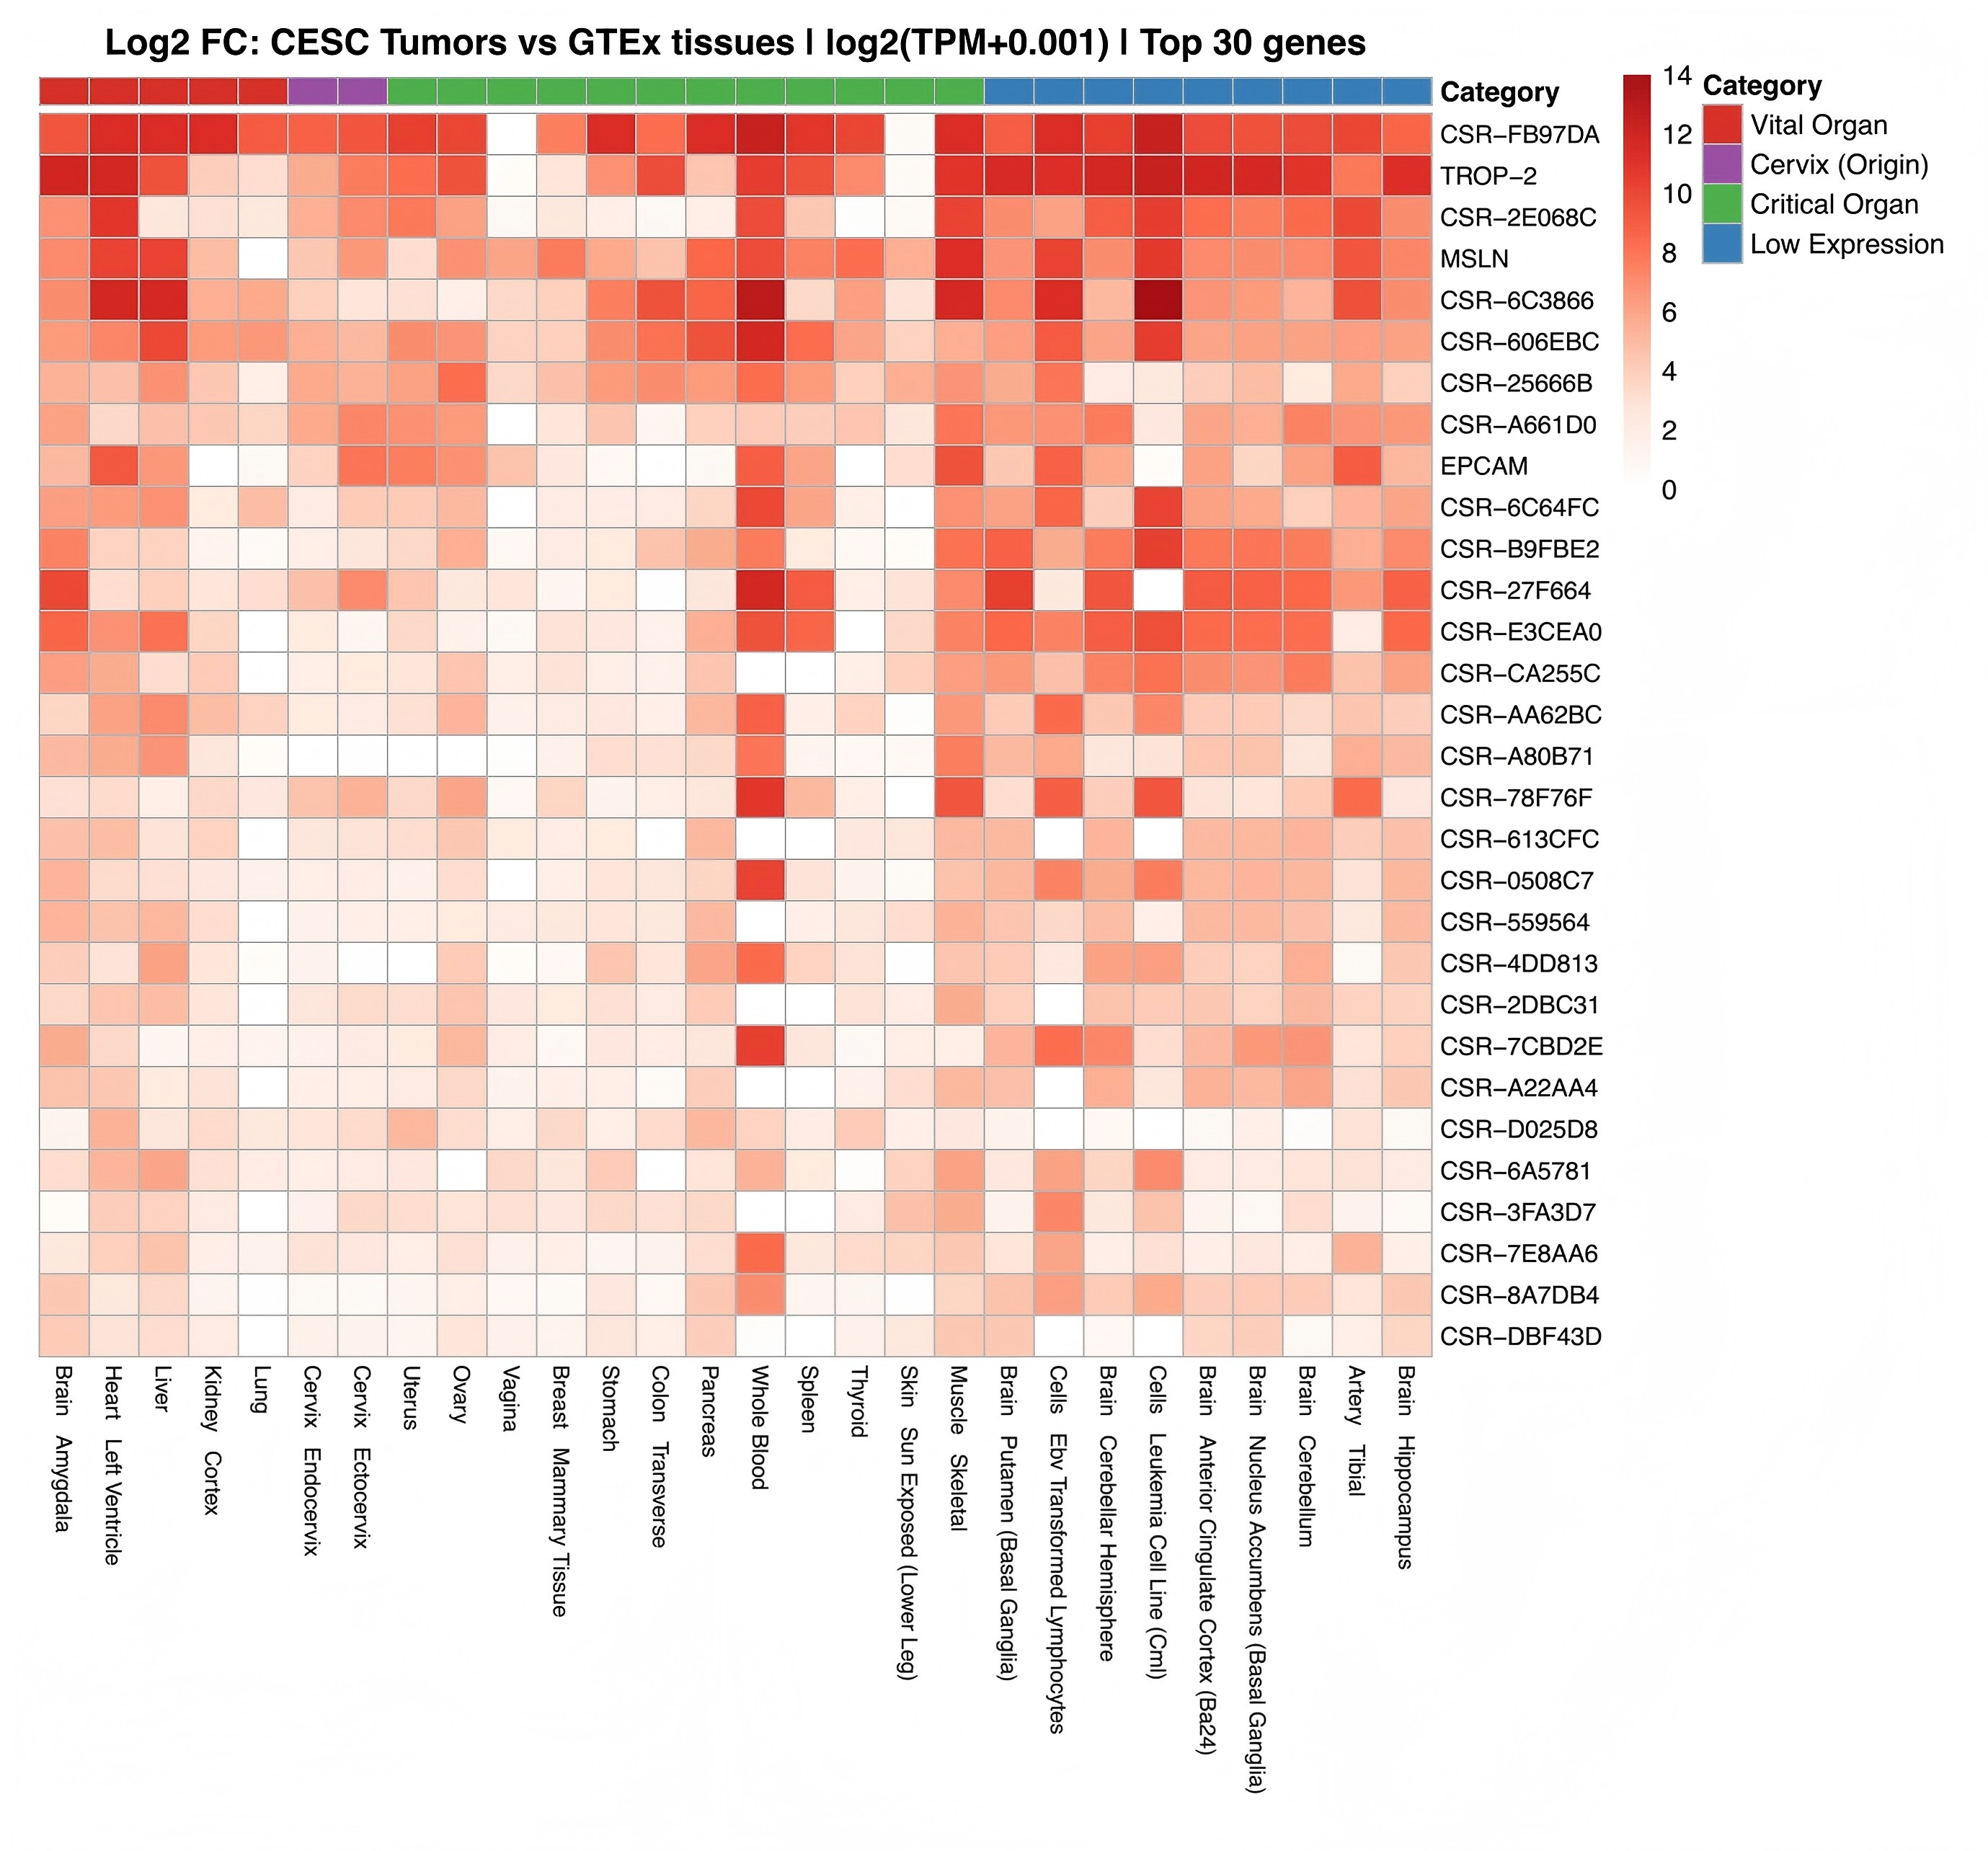
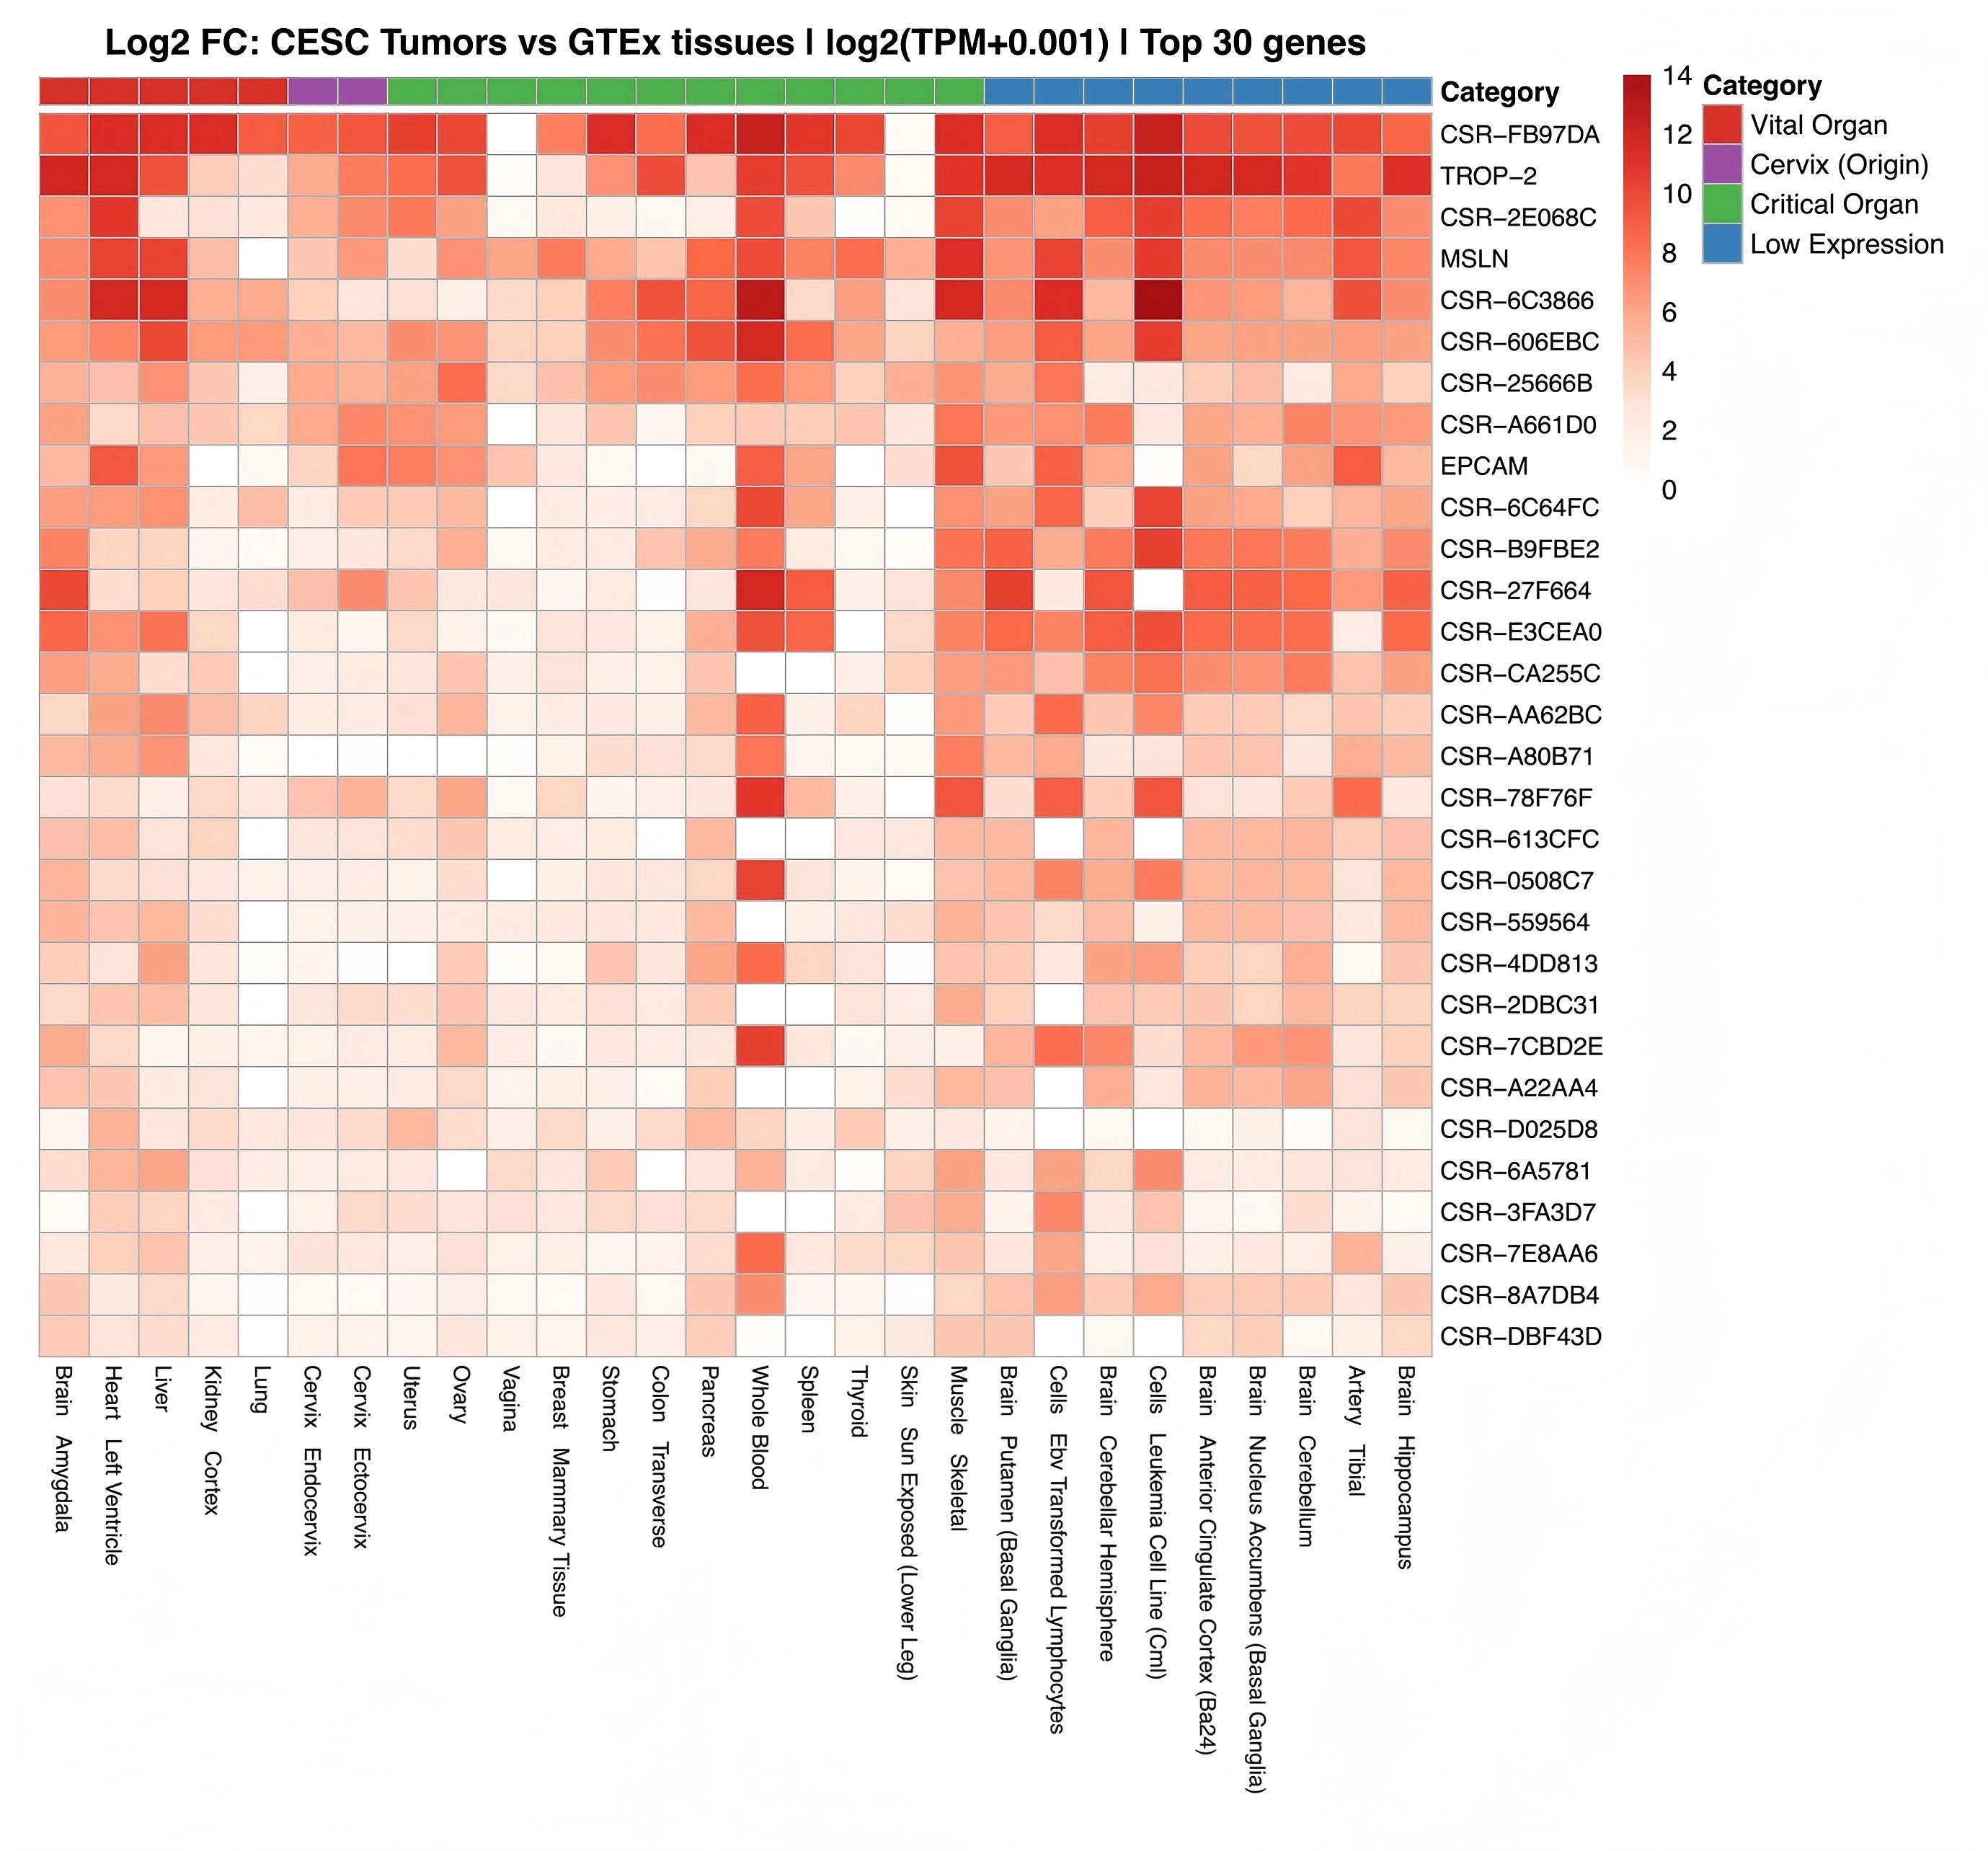
Figure 1. Tissue-wide log₂ fold-change heatmap of the top 30 overexpressed surface targets in TCGA-CESC. Each row represents one of the 30 candidate surface protein genes passing all discovery filters, ranked by descending fold-change as in Table S1. Each column represents a GTEx tissue category. Colour intensity reflects log2 FC = log2(tumour median TPM + 0.001)-log2(healthy tissue median TPM + 0.001). Column annotations indicate tissue category: vital organs (red), cervical tissue of origin (purple), other critical organs (green), and low-expression tissues (blue). TCG-CESC: the cancer genome atlas-cervical adenocarcinoma and squamous carcinoma; FC: fold-change; TPM: transcripts per million; GETx: genotype tissue expression project.
Table 1. Top 10 overexpressed surface targets in TCGA-CESC (global screen).
| Rank | Gene | Tumour TPM | FC (log2) | % Tumours |
| 1 | CSR-FB97DA | 53.7 | 9.42 | 75.3 |
| 2 | TROP-2 | 515.5 | 8.93 | 100.0 |
| 3 | CSR-2E068C | 108.2 | 6.97 | 100.0 |
| 4 | MSLN | 45.0 | 6.93 | 86.8 |
| 5 | CSR-6C3866 | 156.2 | 6.73 | 100.0 |
| 6 | CSR-606EBC | 68.7 | 6.07 | 97.7 |
| 7 | CSR-25666B | 12.2 | 5.38 | 94.1 |
| 8 | CSR-A661D0 | 35.9 | 5.24 | 99.0 |
| 9 | EpCAM | 87.3 | 5.13 | 100.0 |
| 10 | CSR-6C64FC | 65.6 | 5.09 | 99.3 |
Tumour TPM = median expression in tumour samples in TPM. FC (log2) = log2(tumour median TPM + 0.001)-log2(healthy median TPM + 0.001). % Tumours = percentage of TCGA-CESC tumours expressing the gene at TPM ≥ 1. TPM: transcripts per million; FC: fold-change; TCGA-CESC: the cancer genome atlas-cervical adenocarcinoma and squamous carcinoma; EpCAM: epithelial cell adhesion molecule; CSR: cell surfaceome resource; MSLN: mesothelin; TROP-2: trophoblast cell surface antigen 2.
3.3 Tissue-of-origin refinement: Subtype-specific prioritisation
The global screen provides a broad tumour-to-healthy comparison across 52 tissue types, but cervical cancer presents two distinct histological subtypes, namely SCC and adenocarcinoma, arising from different cells of origin in the cervix. To perform a more specific tumour-to-healthy comparison grounded in the actual tissue context of each subtype, we refined the analysis using dedicated cervical profiles as the tissue-of-origin reference, with ectocervix representing the SCC origin and endocervix representing adenocarcinoma. Because the main Xena/Toil matrix contained too few cervix-specific samples for reliable estimates, an external GTEx v10 cervix dataset processed consistently with the main pipeline was used, with bootstrapped confidence intervals confirming the reliability of the resulting fold-change estimates (see Section 2). This allowed us to move beyond a generic overexpression ranking and identify which candidates are the most relevant targets depending on the predominant cervical cancer subtype. The top-ranked candidates after this refinement are shown in Table 2; full results are in Table S2.
Table 2. Top 10 overexpressed surface targets in tissue-of-origin (GTEx v10 cervix references).
| Rank | Gene | FC vs. ectocervix | 95% CI | FC vs. endocervix | 95% CI |
| 1 | CSR-FB97DA | 0.03 | [-1.36, 7.72] | 9.72 | [9.32, 10.53] |
| 2 | CSR-A661D0 | -0.99 | [-1.80, 7.00] | 6.94 | [6.08, 7.53] |
| 3 | TROP-2 | 0.04 | [-1.26, 5.66] | 6.11 | [4.49, 6.93] |
| 4 | MSLN | 5.72 | [4.35, 6.38] | 6.04 | [2.57, 6.94] |
| 5 | CSR-2E068C | 0.79 | [-0.07, 5.13] | 5.23 | [4.46, 6.98] |
| 6 | CSR-25666B | 2.65 | [1.81, 4.54] | 5.11 | [4.44, 5.72] |
| 7 | CSR-27F664 | 3.43 | [2.87, 5.78] | 5.72 | [4.28, 6.50] |
| 8 | CSR-606EBC | 4.12 | [3.21, 5.30] | 5.35 | [4.79, 6.09] |
| 9 | EpCAM | 4.51 | [3.64, 5.47] | 4.29 | [2.77, 7.33] |
| 10 | CSR-78F76F | 0.99 | [-0.23, 3.83] | 4.11 | [2.90, 5.85] |
FC = log2(tumour median TPM + 0.001)-log2(normal subtype median TPM + 0.001). 95% Confidence Intervals (CIs) by bootstrap resampling. Ranked by median FC across both references. All expression metrics are provided in Table S2. FC: fold-change; EpCAM: epithelial cell adhesion molecule; MSLN: mesothelin; CSR: cell surfaceome resource; TROP-2: trophoblast cell surface antigen 2; GTEx: genotype tissue expression.
This refinement substantially changed the picture for several highly ranked candidates from the global screen. Cell surface receptor (CSR)-FB97DA, CSR-A661D0, CSR-2E068C, CSR-78F76F, and TROP-2 all lost SCC selectivity upon tissue-of-origin refinement, showing near-zero or negative FC against normal ectocervix with wide confidence intervals. But they retained high endocervix FC and therefore preserved their values as selective adenocarcinoma targets. MSLN stood out as the best candidate for maintaining high and consistent FC across both cervical subtypes, with tight confidence intervals on both sides, confirming it as a robust pan-CESC candidate regardless of histological subtype. Epithelial cell adhesion molecule (EpCAM) showed consistent overexpression relative to both tissue origins. Full FC values and bootstrap confidence intervals for all candidates, including estimates from both the GTEx v10 and the original Xena/Toil cervical references, are provided in Table S2.
To directly address whether these targets are subtype-selective, we additionally stratified the TCGA-CESC tumours by histological subtype (243 SCC, 46 adenocarcinoma, 5 adenosquamous, 10 unclassified; cBioPortal annotation) and compared each subtype with its own cell of origin—SCC against normal ectocervix and adenocarcinoma against normal endocervix (Table 3). This subtype-resolved analysis confirmed and sharpened the tissue-of-origin picture. MSLN was strongly overexpressed in both subtypes (log2FC 5.28 against ectocervix and 8.51 against endocervix), confirming it as a pan-CESC target. EpCAM was likewise overexpressed in both (4.21 and 6.90). TROP-2, by contrast, was adenocarcinoma-selective rather than SCC-selective: it showed no overexpression in SCC relative to normal ectocervix (log2FC 0.25, 95% CI spanning zero [-0.99, 5.12]) but clear overexpression in adenocarcinoma relative to endocervix (4.88 [3.25, 5.70]). Full subtype-stratified fold-changes for all candidates are provided in Table S3.
Table 3. Histology-stratified overexpression of the validated targets in TCGA-CESC.
| Target | Log2FC SCC vs. ectocervix | 95% CI (SCC) | Log2FC adeno vs. endocervix | 95% CI (adeno) | % SCC positive | % adeno positive |
| MSLN | 5.28 | [3.81, 5.94] | 8.51 | [4.12, 9.27] | 86 | 96 |
| TROP-2 | 0.25 | [-0.99, 5.12] | 4.88 | [3.25, 5.70] | 100 | 100 |
| EpCAM | 4.21 | [3.39, 5.41] | 6.90 | [5.37, 10.18] | 100 | 100 |
Tumours were stratified by histological subtype (cBioPortal annotation) and each subtype compared to its cell of origin (SCC vs. normal ectocervix; adenocarcinoma vs. normal endocervix; GTEx v10). FC = log2(tumour median TPM + 0.001)-log2(normal median TPM + 0.001); 95% CIs by bootstrap resampling; % positive = tumours with TPM ≥ 1. Full candidate list in Table S3. SCC: squamous cell carcinoma; GTEx: genotype tissue expression; FC: fold-change; TPM: transcripts per million; EpCAM: epithelial cell adhesion molecule; TROP-2: trophoblast cell surface antigen 2; MSLN: mesothelin.
3.4 A literature-driven target absent from the screen: LIV-1
In parallel with the computational screen, a review of the targetability literature flagged LIV-1 as a candidate of interest. Its role in tumour progression has been characterised largely in breast cancer and other tumour types[22-25], with direct cervical evidence provided by LIV-1 suppression in HeLa cells[26]. On this basis, we considered LIV-1 worth evaluating in cervical cancer. However, unexpectedly, it did not appear among the 30 global hits, and its cohort-wide median FC was only 0.97, well below the threshold. Rather than dismissing this target, we investigated whether its signal might be concentrated within a high-expressing subgroup and diluted in cohort-level analysis by the majority of tumours in which it is not elevated.
Stratifying tumours by LIV-1 expression using a z-score threshold of ≥ 1.5 identified 14 tumours (4.6% of the cohort) with consistently high expression, with a subgroup median of 122.7 TPM. Within this subgroup, the median FC across all 52 normal tissues reached 3.07 (bootstrap 95% CI [2.81, 3.29]), with overexpression in 45 of 52 tissue comparisons; a permutation test confirmed this was not due to chance (none of 10,000 random draws of 14 tumours reached FC ≥ 3.07, p < 0.001). This subgroup signal was robust across the range of z-score thresholds tested (0.5-2.5): the high-expressing fraction fell from 28.0% of the cohort at z ≥ 0.5 to 2.6% at z ≥ 2.0, while the subgroup fold-change rose monotonically from 1.92 to 3.24, with all permutation p < 0.001 (Table S4; the LIV-1 expression distribution is shown in Figure S1). LIV-1 is therefore not a pan-tumour antigen but an exploratory LIV-1-high subgroup marker, a precision-medicine candidate that would require patient stratification and one that a conventional cohort-level analysis would miss entirely. The LIV-1-high subgroup was also recovered in the independent GSE151666 cohort: pooled LIV-1 expression was modest (median 20.8 TPM), but a z-stratified high-expressing subgroup re-emerged at a prevalence comparable to TCGA (z ≥ 1.5: 6% of tumours, median 64.4 TPM, 3.1-fold the pooled median), indicating the subgroup structure is not specific to TCGA.
3.4.1 Orthogonal validation of the prioritised targets
To move beyond transcript-level fold-change, the prioritised targets were validated at the protein level, at single-cell resolution and in independent cohorts. In Human Protein Atlas immunohistochemistry, the staining patterns reinforced the transcriptomic picture: TROP-2 was present in normal squamous (ectocervical) epithelium but not detected in normal glandular (endocervical) epithelium, providing an independent protein-level line of evidence for its adenocarcinoma-selectivity, and was stained at medium/high intensity in 45% of cervical cancers; EpCAM and MSLN were positive in 36% and 25% of cancers respectively, while LIV-1 showed no medium/high protein staining, consistent with its restriction to a small subgroup (Table S5). At single-cell resolution (GSE208653, GSE197461), all four targets were predominantly epithelial, with low expression across most non-epithelial compartments (typically < 10% of cells positive); the exceptions were LIV-1, which was also detected in fibroblasts (35% of cells), and lower-level TROP-2 signal in endothelial and myeloid cells. MSLN showed a clear adenocarcinoma association: it was expressed in 66% of adenocarcinoma epithelial cells (mean 0.88) versus 23% of SCC epithelium (0.28) and 0% of non-epithelial cells, and was positive in all five adenocarcinoma patients examined individually (31-80% of epithelial cells), matching the reported ~80% MSLN positivity in cervical adenocarcinoma (Table S6,S7). In the independent bulk cohorts, GSE63514 recovered EpCAM (log2FC +1.58, FDR 0.013) and LIV-1 (+0.71, FDR 0.006) as significantly higher in cancer than normal, whereas MSLN and TROP-2 were not significantly elevated in this epithelium-microdissected dataset (Table S8); across the 68 tumours of GSE151666, all four targets were expressed in ≥ 91% of tumours, with TROP-2 the most abundant (median 980 TPM; Table S9). Together, these orthogonal analyses confirm the targets while making clear that no single line of evidence supports all four equally, a point we interpret with caution in Section 4.
On the basis of this combined transcriptomic evidence and supported by existing literature on targetability in cervical and related cancers[17,27,28], MSLN, TROP-2, EpCAM and LIV-1 were selected as the candidates for experimental validation. EpCAM in vitro validation and ADC development have been published separately by our group[19] and are therefore not repeated in the wet-lab component of this study.
3.5 SNAP fusion proteins expression and purification
The anti-SLC39A6 (αLIV-1), anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP fusion proteins were expressed in HEK293T cells and purified from the supernatant using IMAC. For confirmation of expression and purification, proteins were analysed using SDS-PAGE and Western blot. The mammalian expression plasmid contained a 10× histidine-encoding tag, allowing for purification and visualisation of the expressed proteins. SDS-PAGE and western blot analysis indicated bands for anti-SLC39A6 (αLIV-1), anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP fusion proteins at the expected size between 50 and 55 kDa (Figure 2). These three proteins were successfully conjugated to BG-Alexa Fluor 488 and specifically detected (Figure 2) at 50 and 55 kDa, demonstrating C-terminus functionality and successful self-labelling of the proteins.
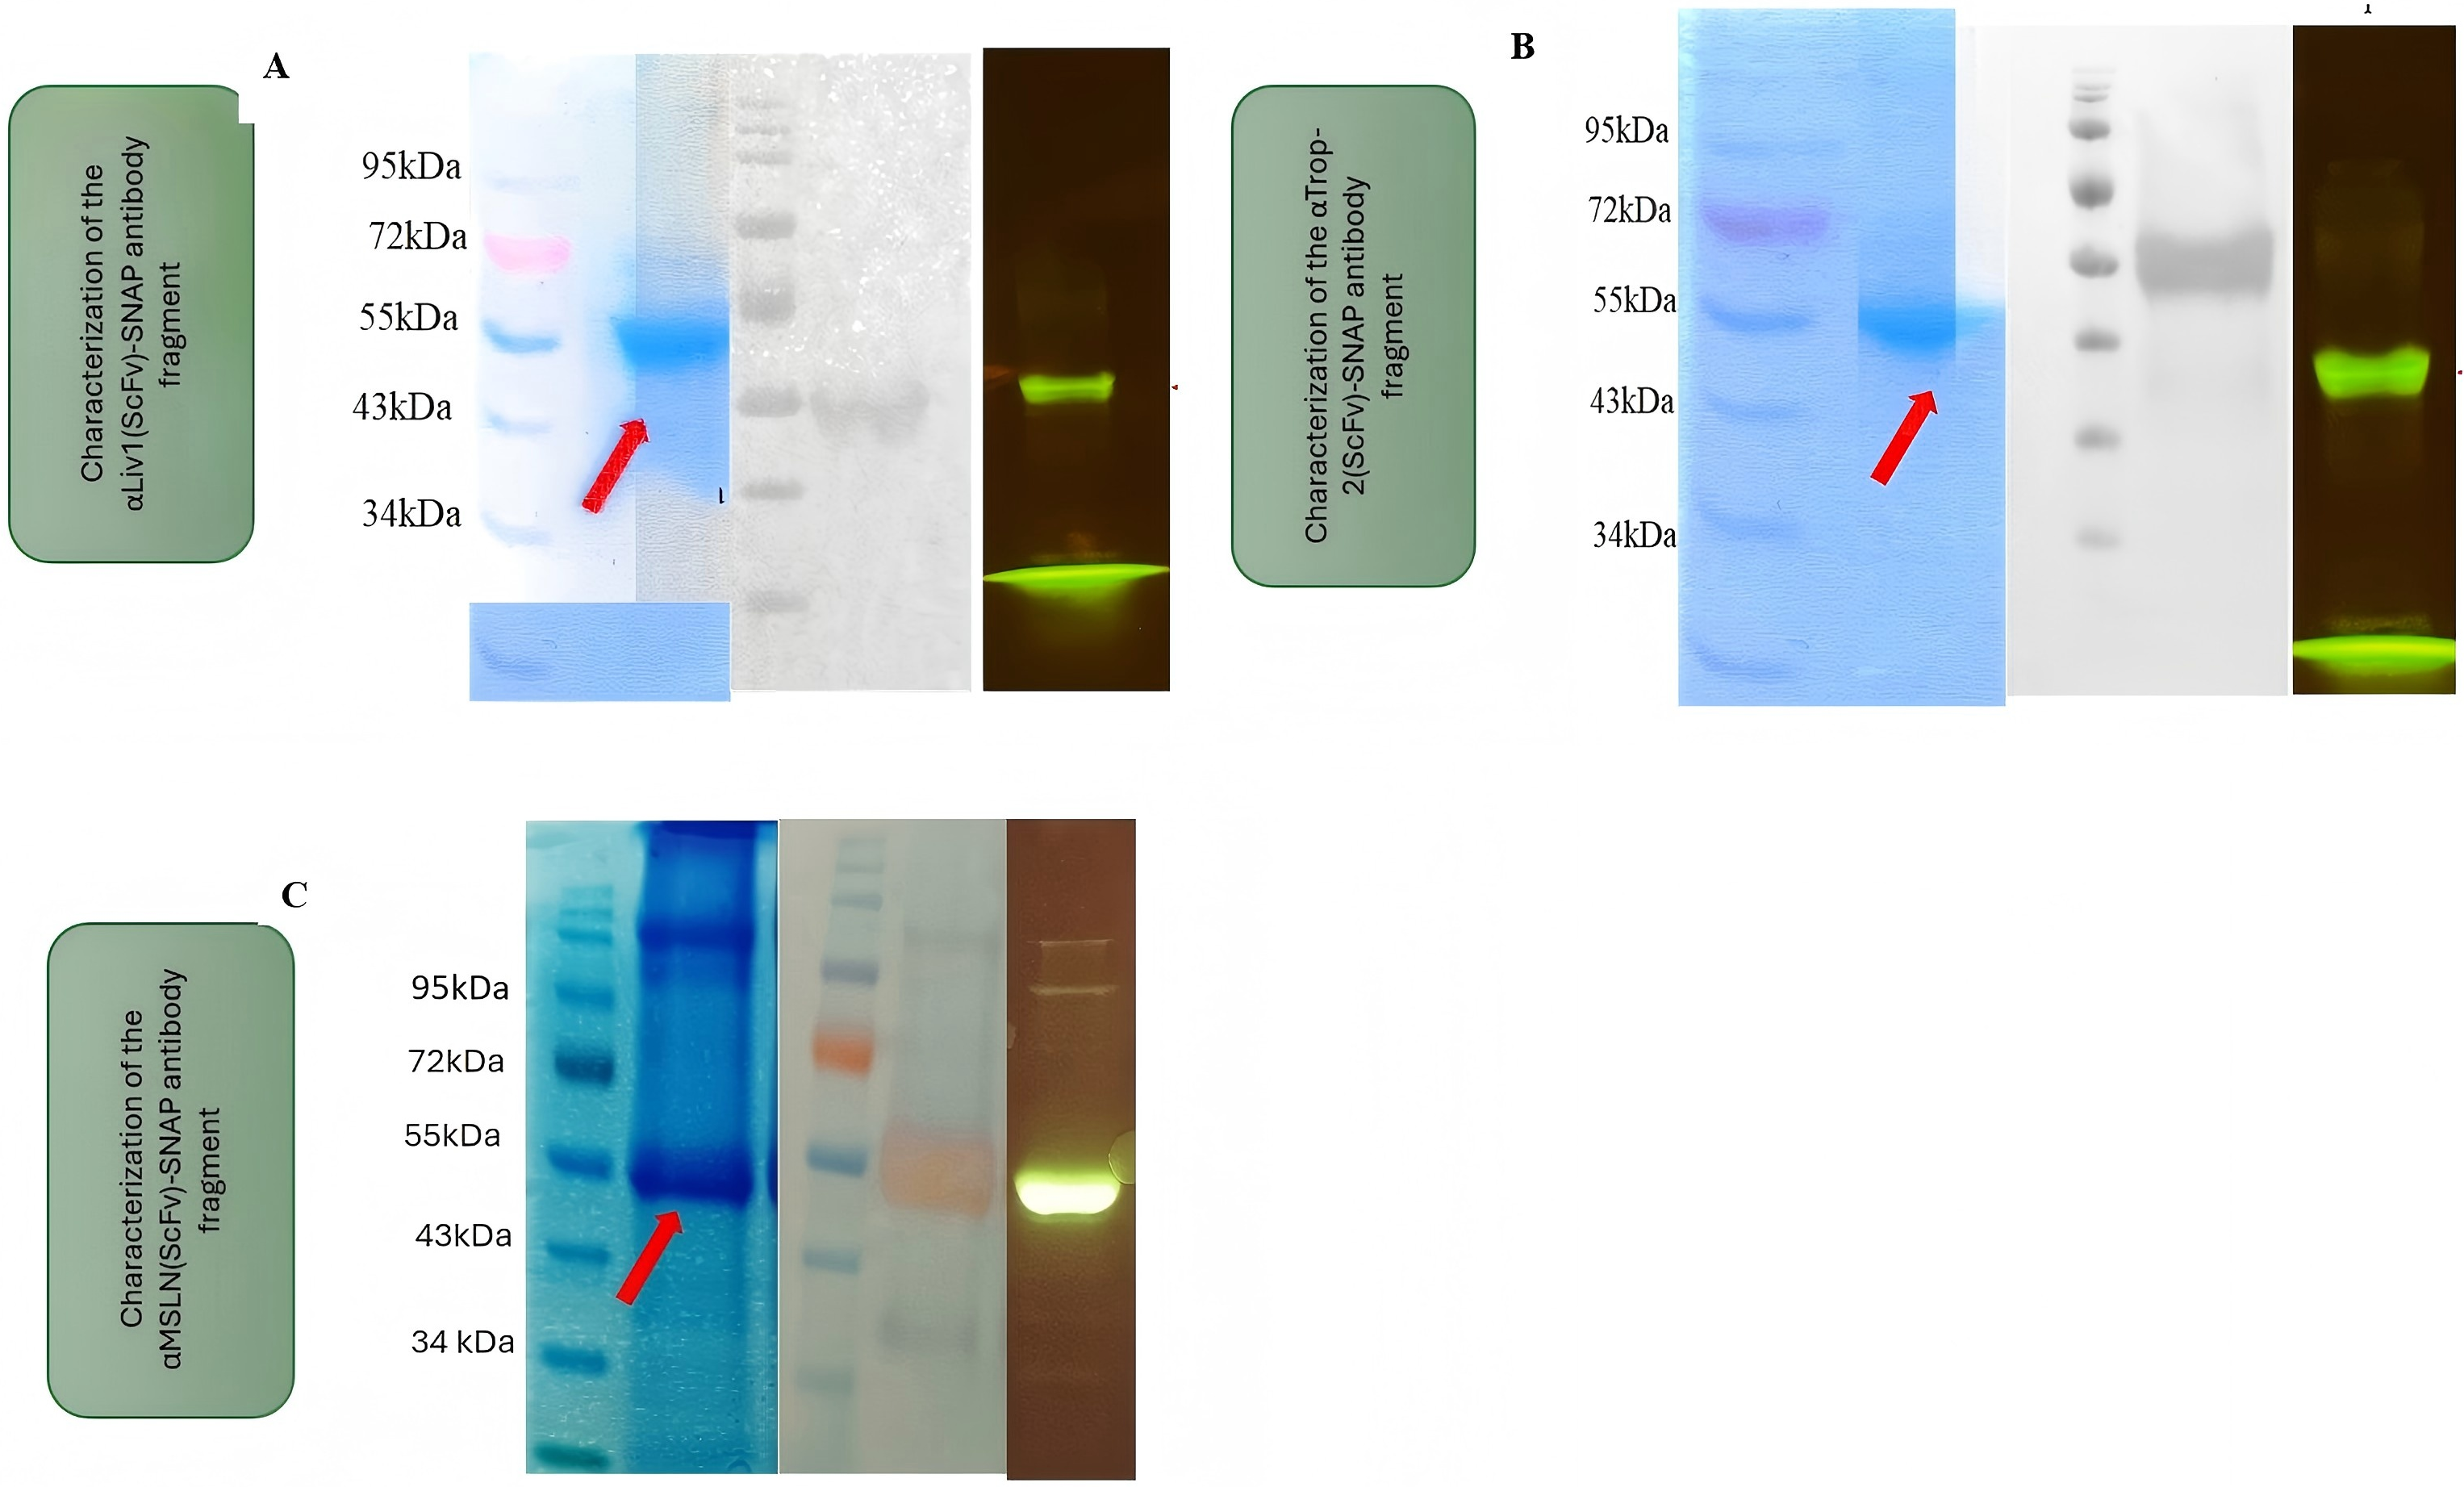
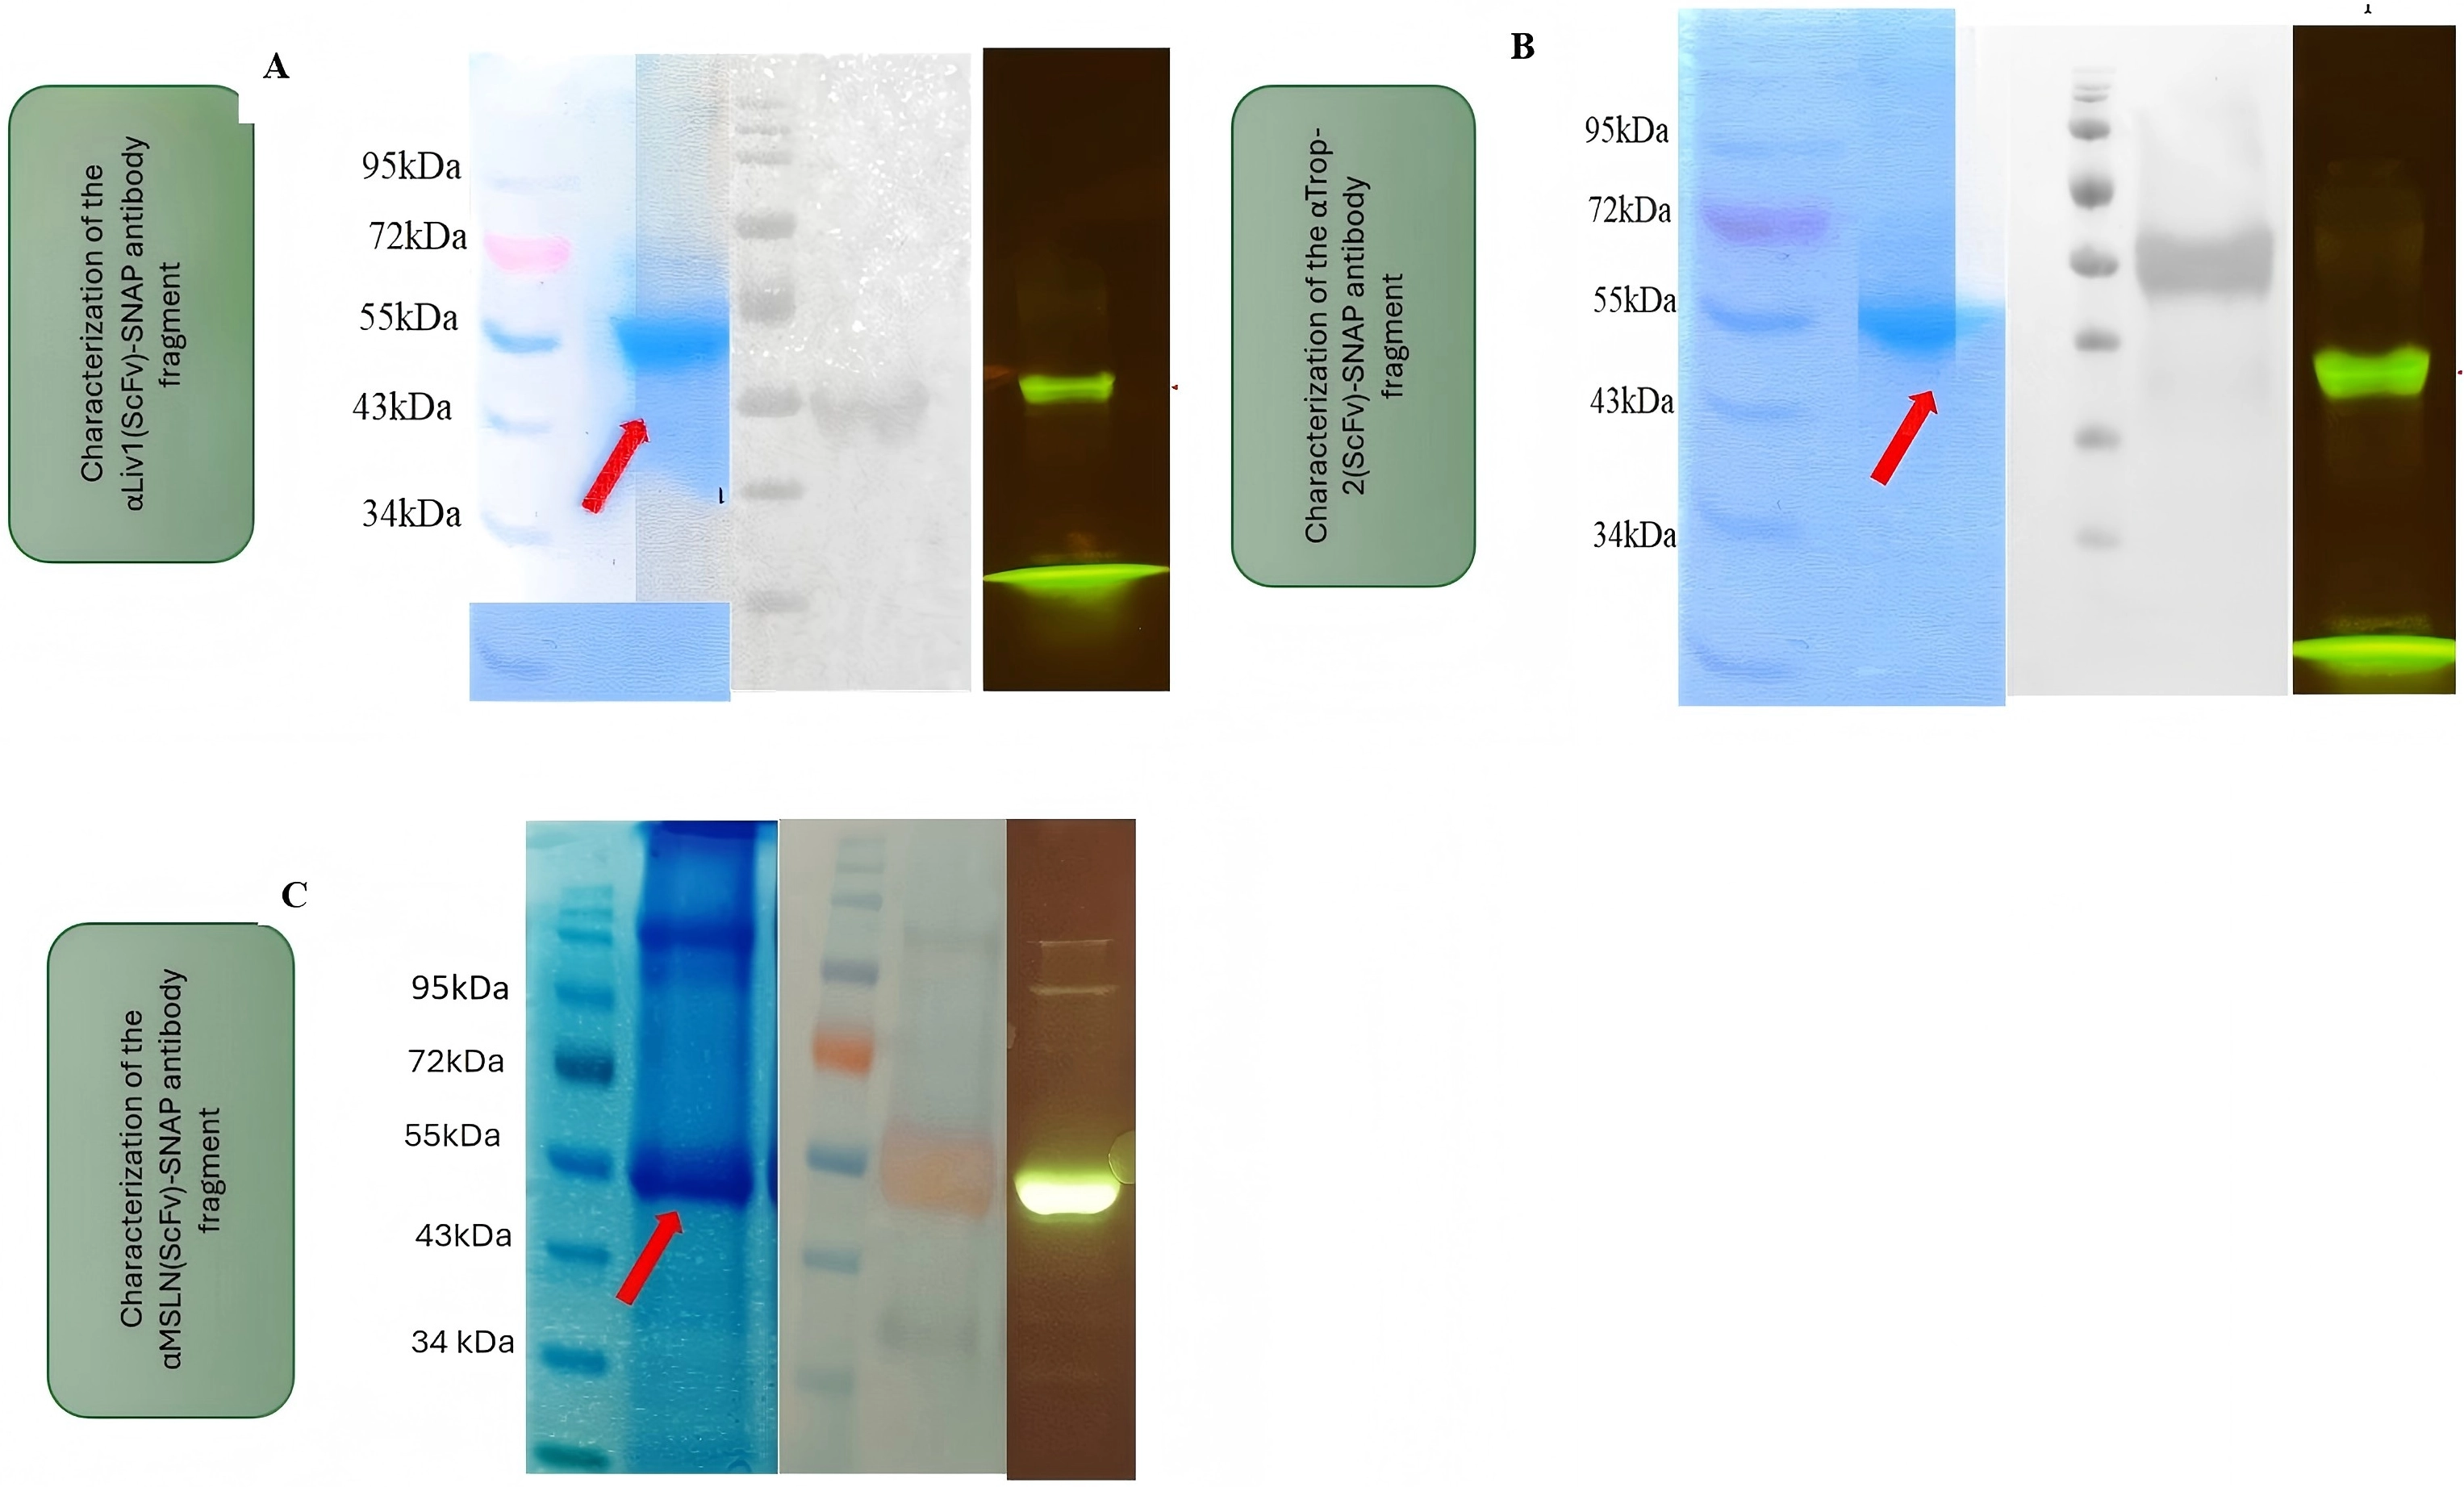
Figure 2. Expression, purification, and site-specific fluorescent labelling of recombinant (scFv)-SNAP fusion proteins. Representative analyses of the recombinant (A) anti-SLC39A6 (αLIV-1); (B) Anti-TACSTD2 (αTROP-2); (C) Anti-mesothelin (αMSLN) (scFv)-SNAP fusion proteins. For each fusion protein, the left panel shows AcquaStain solution-stained SDS-PAGE analysis following IMAC purification, the middle panel shows Western blot detection using an anti-polyhistidine antibody to confirm protein identity, and the right panel shows fluorescence imaging of SDS-PAGE gels following site-specific conjugation with a BG-modified Alexa Fluor® substrate, confirming successful SNAP-tag-mediated labelling of the full-length fusion proteins. TACSTD2: tumor-associated calcium signal transducer 2; TROP-2: trophoblast cell surface antigen 2; SDS-PAGE: sodium dodecyl sulfate-polyacrylamide gel electrophoresis; scFv: single chain antibody fragment; SNAP: O6-alkylguanine-DNA alkyltransferase; SLC39A6: solute carrier family 39 member 6; LIV-1: liver-specific protein 1; IMAC: immobilized metal affinity chromatography; MSLN: mesothelin.
3.6 Cell surface binding via Flow cytometry
Flow cytometric analysis demonstrated selective binding of all three (scFv)-SNAP fusion proteins to the cervical cancer cell line panel, as determined by the percentage of antigen-positive cells (Figure 3, Table 4). The αTROP-2(scFv)-SNAP fusion protein exhibited high binding across all cervical cancer cell lines, with 84.4-100% of cells antigen-positive. In contrast, binding to the antigen-negative HL60 control cell line was negligible (4.3%), confirming the specificity of the αTROP-2(scFv)-SNAP fusion protein. The αLIV-1(scFv)-SNAP fusion protein demonstrated strong binding to CaSki, HeLa, and SiHa cells (93.8-99.8%), whereas a lower proportion of ME180 cells were positive (55.0%). Minimal binding was detected in the antigen-negative TE671 control cell line (0.73%), indicating target-specific recognition. Similarly, the αMSLN(scFv)-SNAP fusion protein exhibited high binding to CaSki, HeLa, and ME180 cells (84.9-99.4%), while binding to SiHa cells was moderate (43.6%). Moderate binding was also observed in HaCaT cells (67.3%), whereas binding to the HEK293T control cell line was substantially lower (37.8%). To validate the flow cytometry findings, the cellular binding and internalization of the Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins were further examined by confocal microscopy (Figure 4).
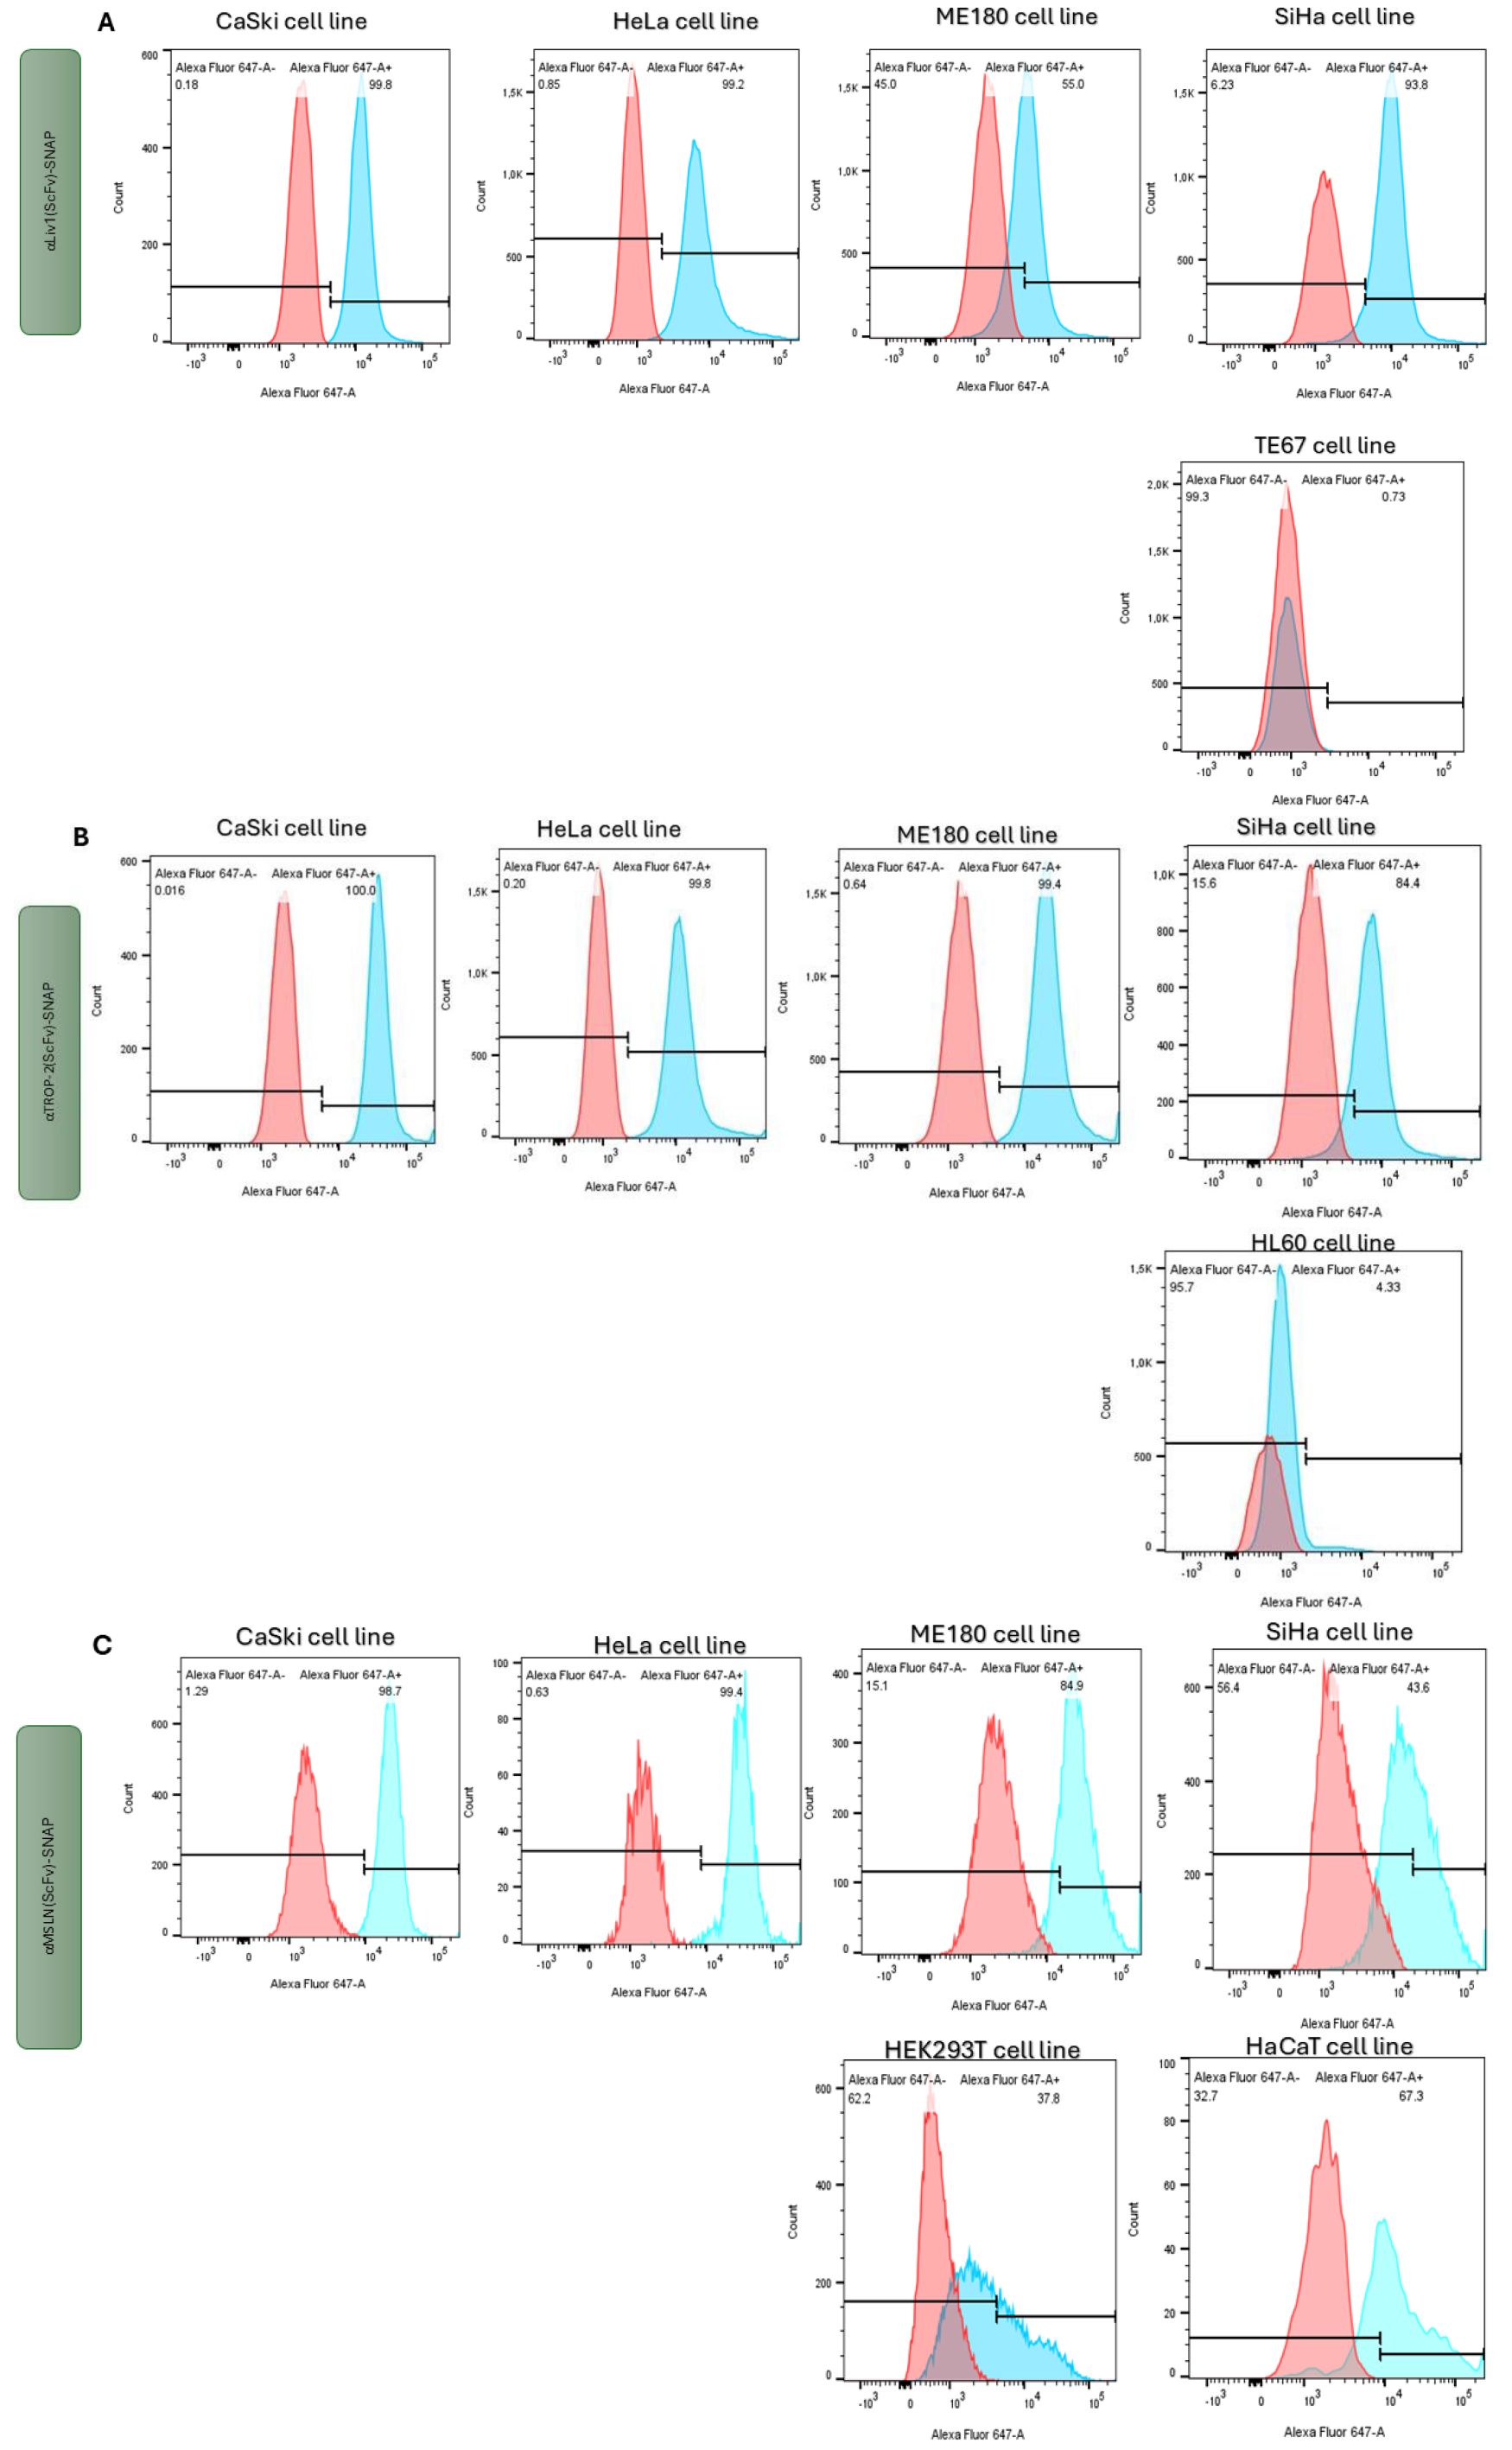
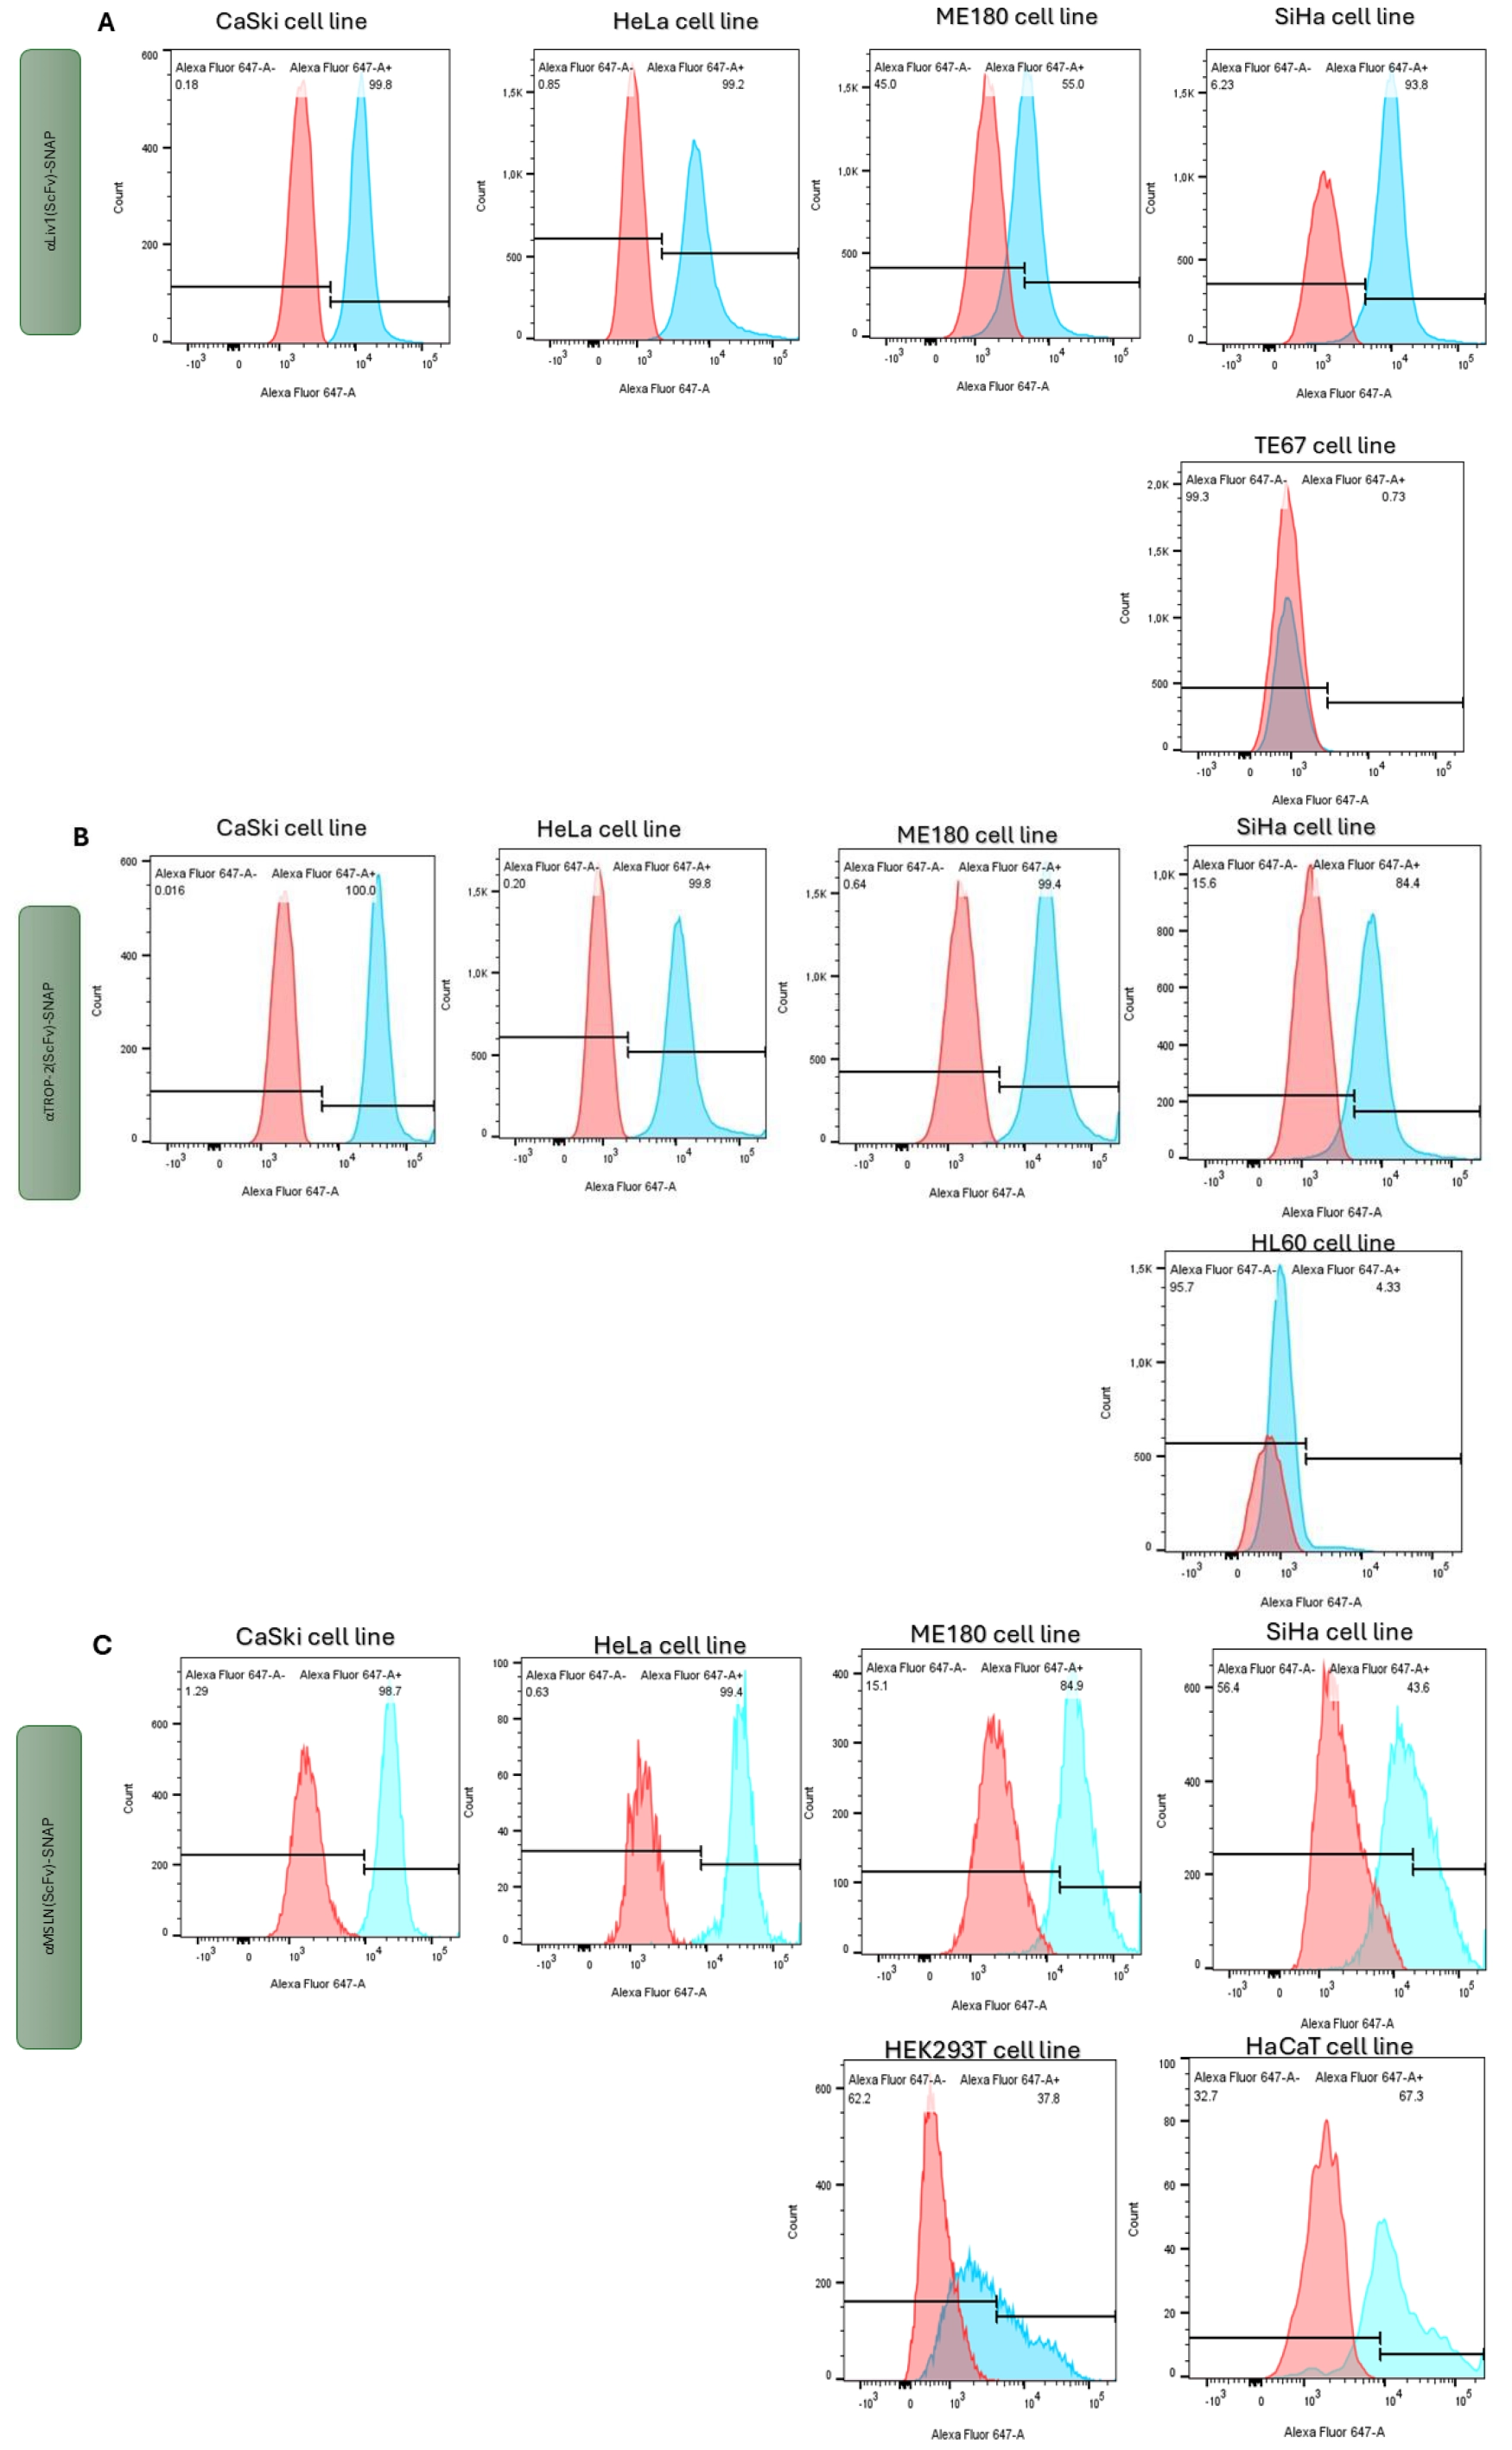
Figure 3. Cell surface binding assay by flow cytometry using fluorescently labelled (scFv)-SNAP proteins. (A) αLIV-1; (B) αTROP-2; (C) αMSLN. Cervical cancer was modelled using the human cervical cancer cell lines CaSki, HeLa, ME180, and SiHa. The human cell lines TE671, HL60, HEK293T and HaCaT were used as negative control cell lines. The red histogram represents the untreated cells; the blue histogram represents the antigen-positive cell population. The CaSki and HeLa cell lines show the clearest distinction between the antigen-positive and antigen-negative populations (represented by the untreated cells). The TE671 and HL60 cell lines have a small proportion of antigen-positive cells; this is not observed in the HEK293T and HaCaT cell lines, with more than 35% of these cell lines being MSLN-positive. MSLN: mesothelin; scFv: single chain antibody fragment; LIV-1: liver-specific protein 1; TROP-2: trophoblast cell surface antigen 2; SNAP: O6-alkylguanine-DNA alkyltransferase.
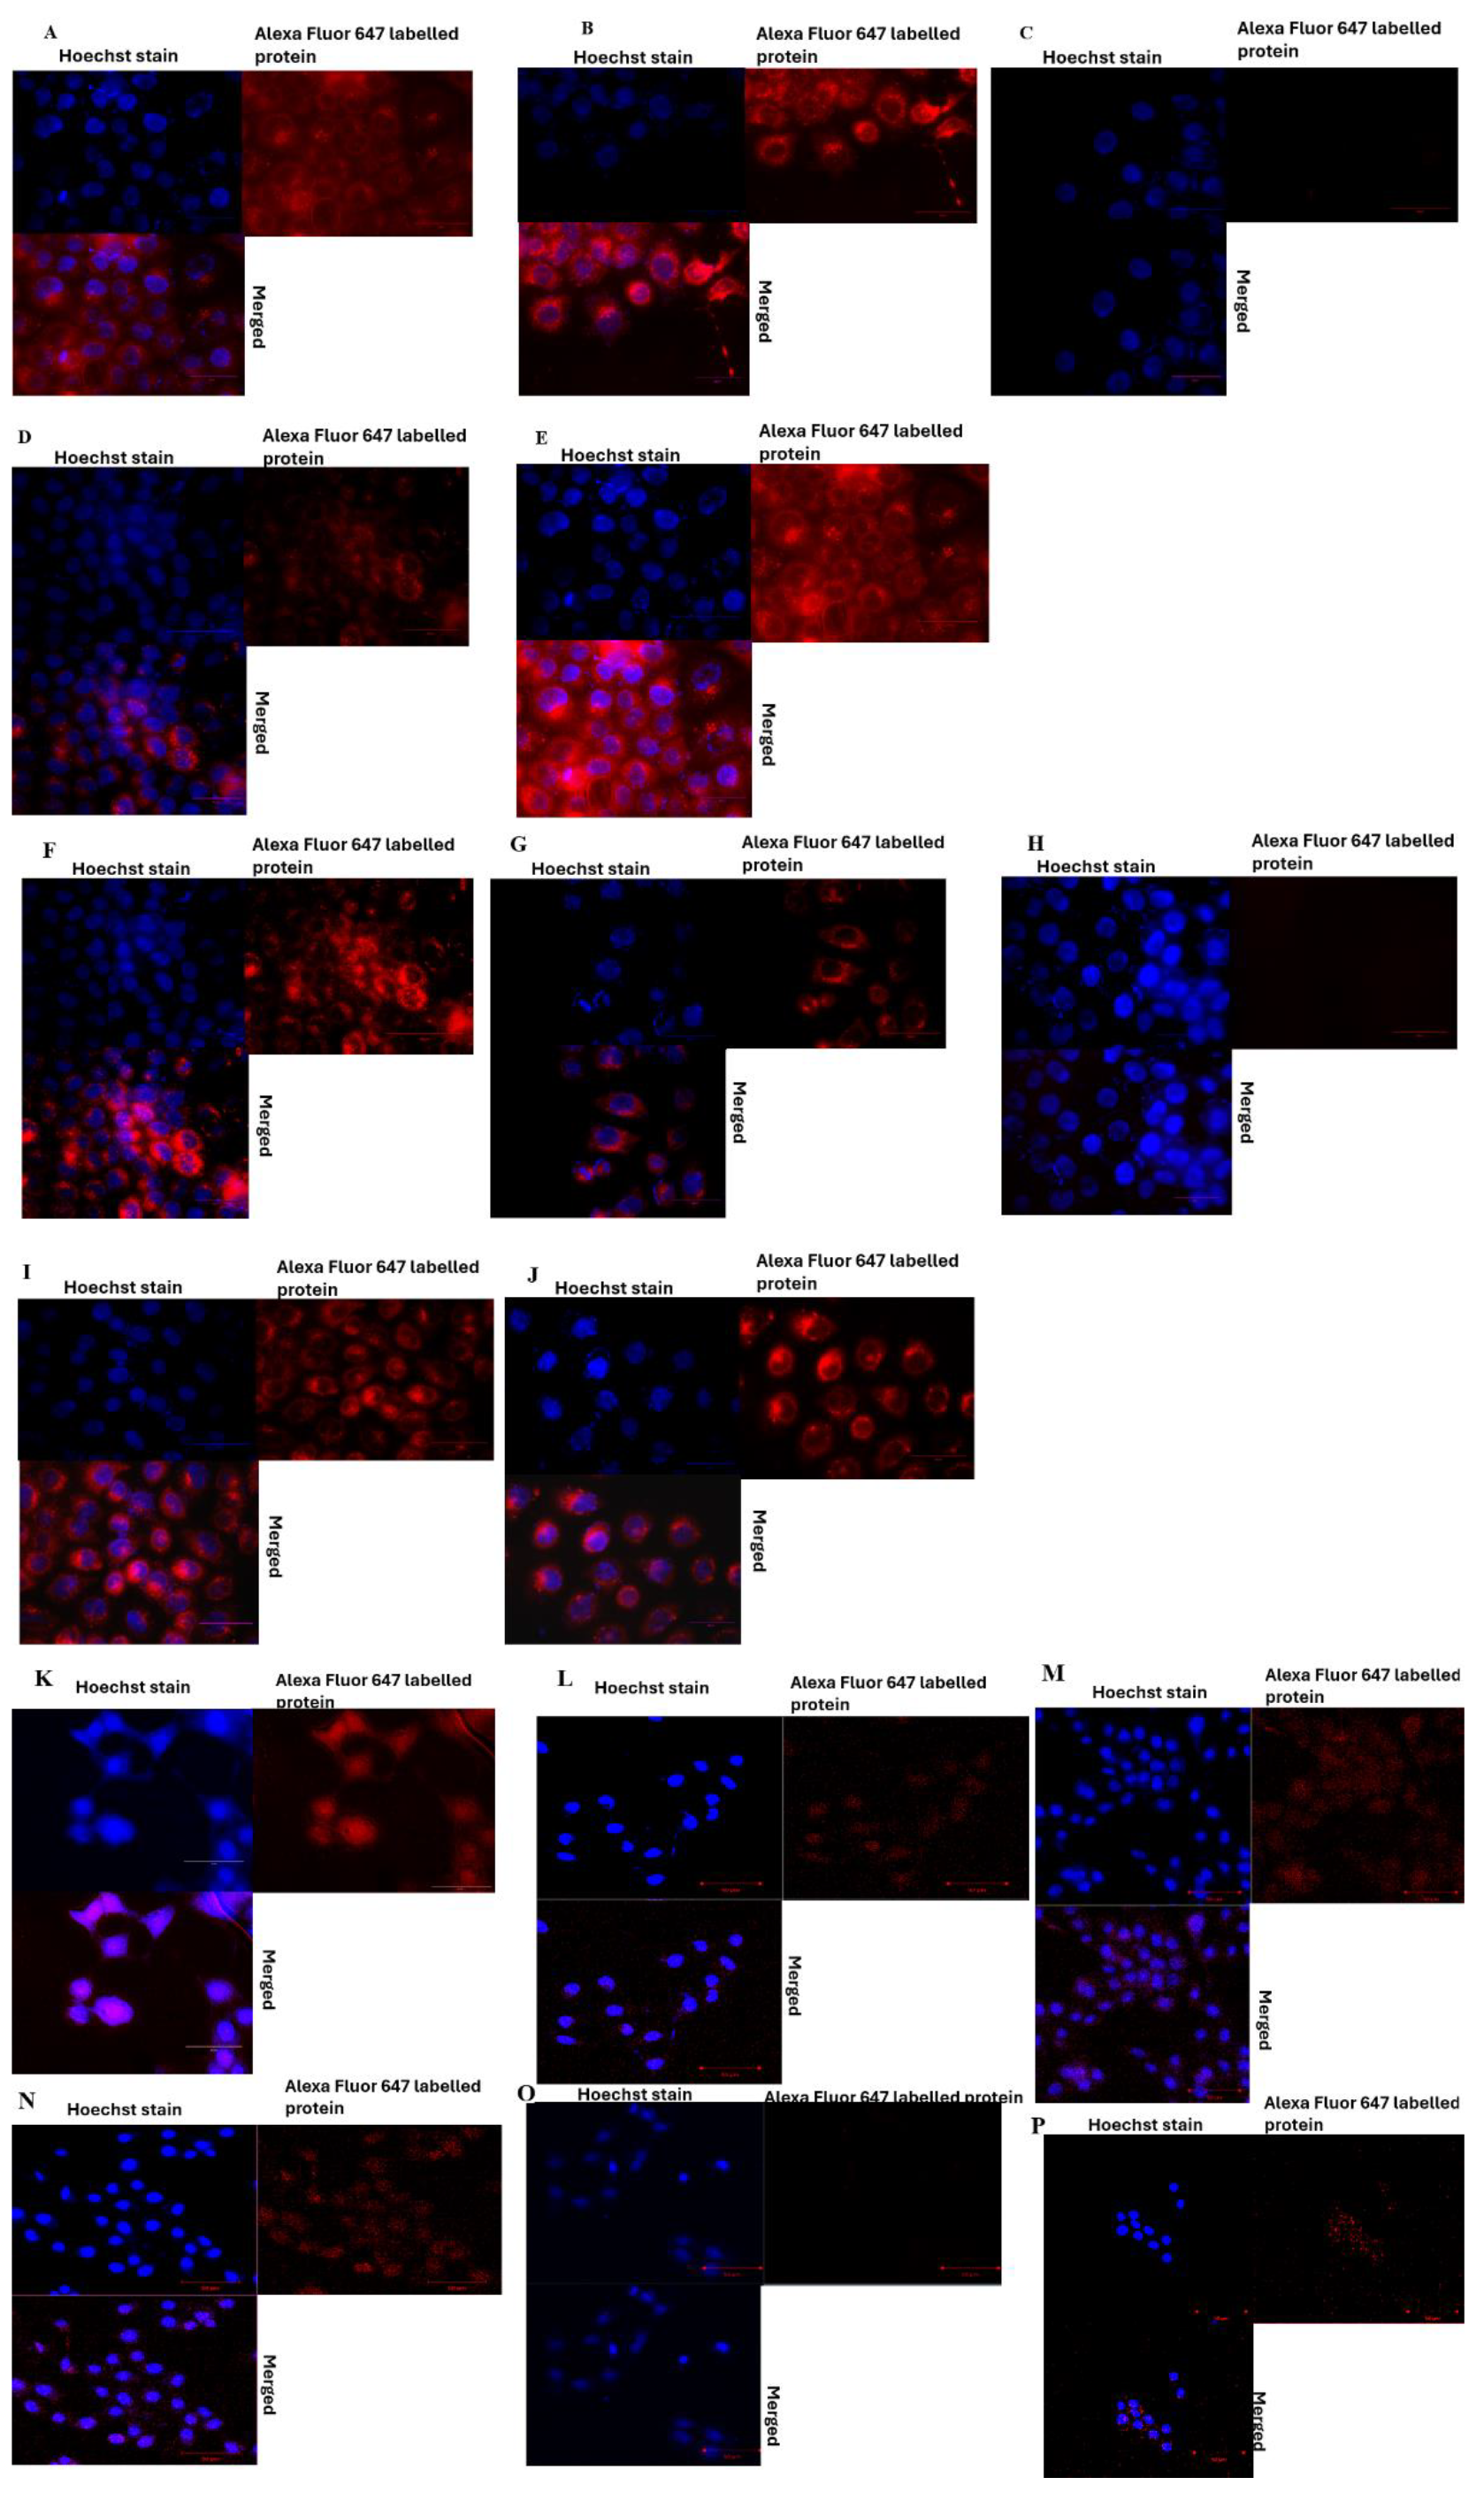
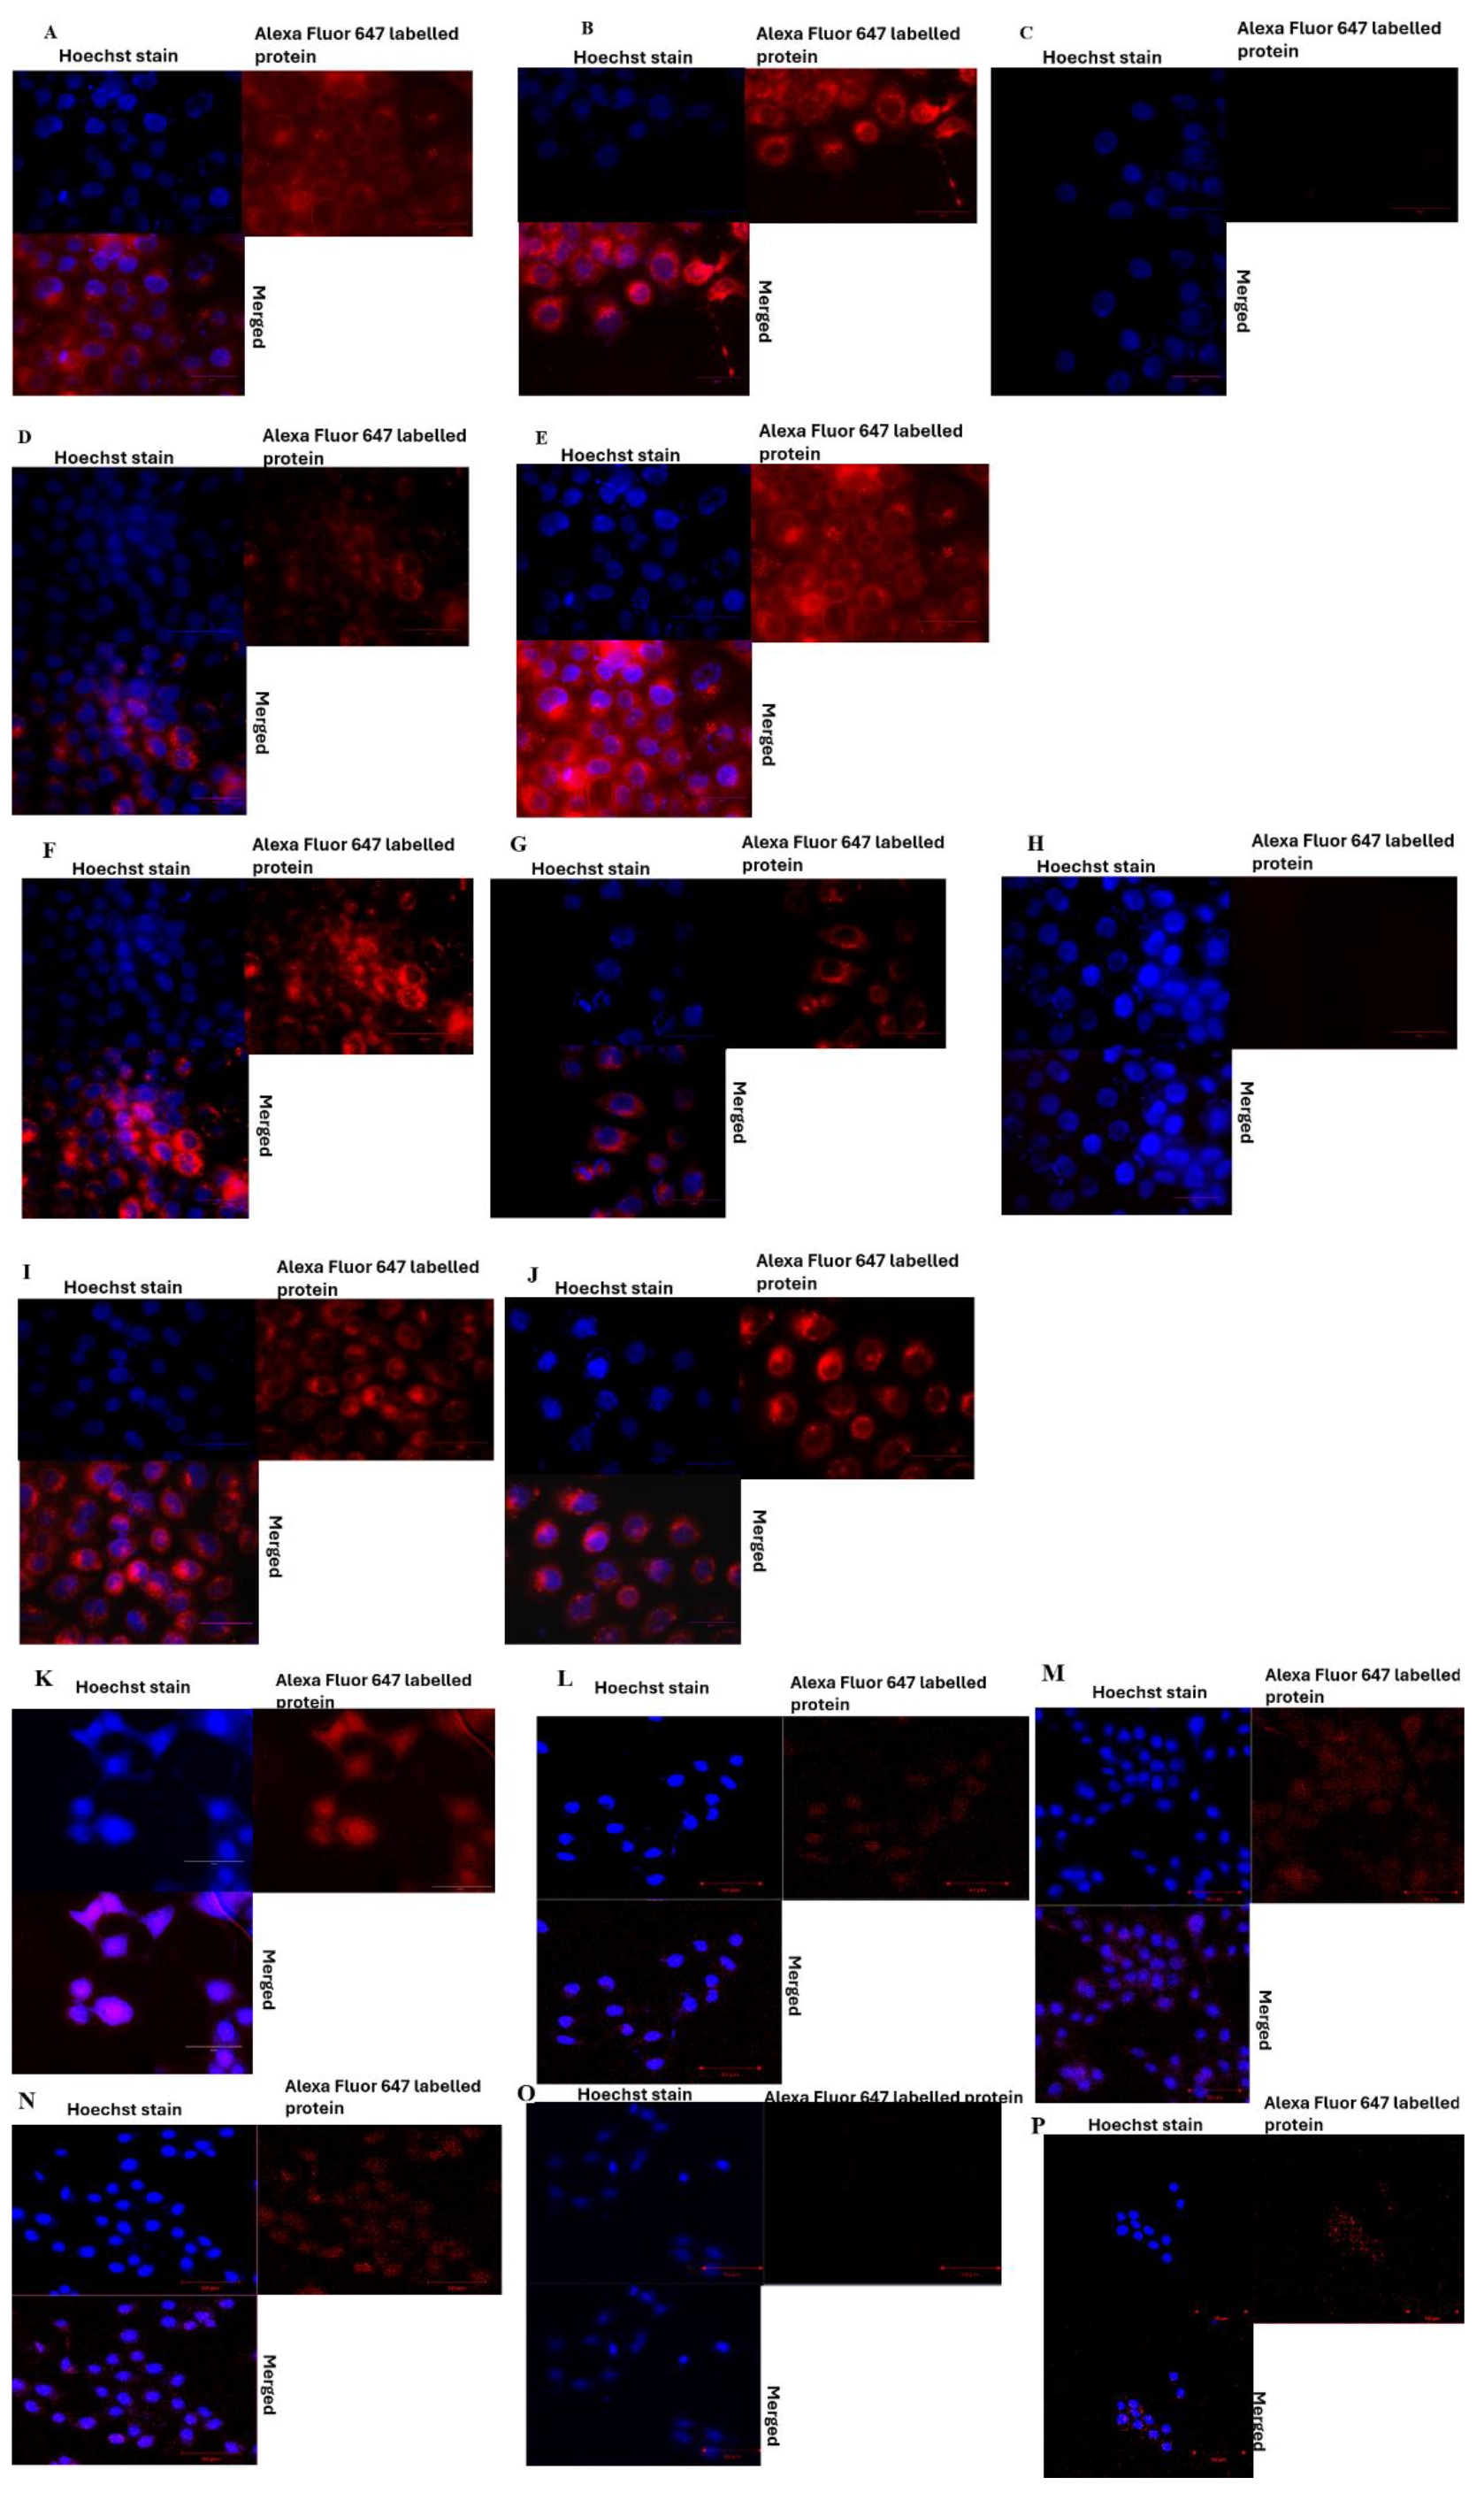
Figure 4. Confocal microscopy analysis of the binding of Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins to cervical cancer cell lines. Fixed-cell confocal microscopy was performed following 30 min incubation with Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins. (A-E) Cell-surface binding of αLIV-1(scFv)-SNAP-Alexa Fluor® 647 was observed on the LIV-1-positive cervical cancer cell lines CaSki (A), HeLa (B), ME180 (D), and SiHa (E), whereas no binding was detected on the LIV-1-negative TE671 control cell line (C); (F-J) Selective binding of αTROP-2(scFv)-SNAP-Alexa Fluor® 647 was detected on CaSki (F), HeLa (G), ME180 (I), and SiHa (J), while no binding was observed on the TROP-2-negative HL60 control cell line (H); (K-P) αMSLN(scFv)-SNAP-Alexa Fluor® 647 demonstrated preferential binding to CaSki (K), SiHa (L), ME180 (M), and HeLa (N) cells. Consistent with the flow cytometry results, binding was also observed on HaCaT cells (P), whereas little to no binding was detected on the MSLN-negative HEK293T control cell line (O). The red channel represents Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins, and the blue channel represents Hoechst-stained nuclei. Representative images of the nuclei, Alexa Fluor® 647 fluorescence, and merged channels are shown for each cell line. Images were acquired using a Zeiss LSM 880 Airyscan confocal laser scanning microscope equipped with 40× and 100× oil immersion objectives. ScFv: single chain antibody fragment; SNAP: O6-alkylguanine-DNA alkyltransferase; LIV-1: liver-specific protein 1; TROP-2: trophoblast cell surface antigen 2; MSLN: mesothelin.
Table 4. The percentage of antigen-positive cells and the origin of the cells in the cell line population treated with the fluorescently labelled (scFv)-SNAP proteins.
| Cell line | Origin | αLIV-1 (scFv)-SNAP | αTROP-2 (scFv)-SNAP | αMSLN (scFv)-SNAP |
| CaSki | Cervical carcinoma-Ectocervix | 99.8% | 100% | 96.7% |
| HeLa | Cervical carcinoma-Endocervix | 99.2% | 99.8% | 99.4% |
| ME180 | Metastatic cervical carcinoma, (Ectocervical primary tumour) | 55% | 99.4% | 84.9% |
| SiHa | Cervical carcinoma-Ectocervix | 93.8% | 84.4% | 43.6% |
| TE671 | Rhabdomyosarcoma | 0.73% | - | - |
| HL60 | Myeloid leukemia | - | 4.3% | - |
| HEK293T | Embryonic cells | - | - | 37.8% |
| HaCaT | Human skin epithelium | - | - | 67.3% |
scFv: single chain antibody fragment; SNAP: O6-alkylguanine-DNA alkyltransferase; LIV-1: liver-specific protein 1; TROP-2: trophoblast cell surface antigen 2; MSLN: mesothelin.
3.7 Binding via confocal microscopy
Fixed-cell confocal microscopy of Alexa Fluor® 647-labelled (scFv)-SNAP fusion proteins confirmed the selective cell-surface binding observed by flow cytometry (Figure 4). Following 30 min incubation, αLIV-1(scFv)-SNAP-Alexa Fluor® 647 demonstrated selective surface binding to the cervical cancer cell lines (Figure 4 A,B,C,D,E). Similarly, binding to TROP-2-positive cervical cancer cell lines CaSki, HeLa, SiHa, and ME180 was observed (Figure 4F,G,H,I,J), while no detectable binding was observed on the TROP-2-negative HL60 control cell line (Figure 4H). The αMSLN(scFv)-SNAP-Alexa Fluor® 647 fusion protein showed preferential binding to the MSLN-expressing cervical cancer cell lines CaSki, HeLa, SiHa, and ME180. Consistent with the flow cytometry data, fluorescence was also detected on HaCaT cells, whereas little to no binding was observed on the MSLN-negative HEK293T control cell line (Figure 4K,L,M,N,O,P). Collectively, the confocal microscopy findings corroborated the flow cytometry results, confirming the selective cell-surface binding of the newly generated (scFv)-SNAP fusion proteins to their respective target antigens on cervical cancer cells.
3.8 Cytotoxicity assays
The dose-dependent cytotoxicity of LIV-1-, TROP-2-, and MSLN-targeting (scFv)-SNAP conjugated to auristatin F on cervical cancer cell lines was assessed using the XTT-based colorimetric assay (Figure 5).
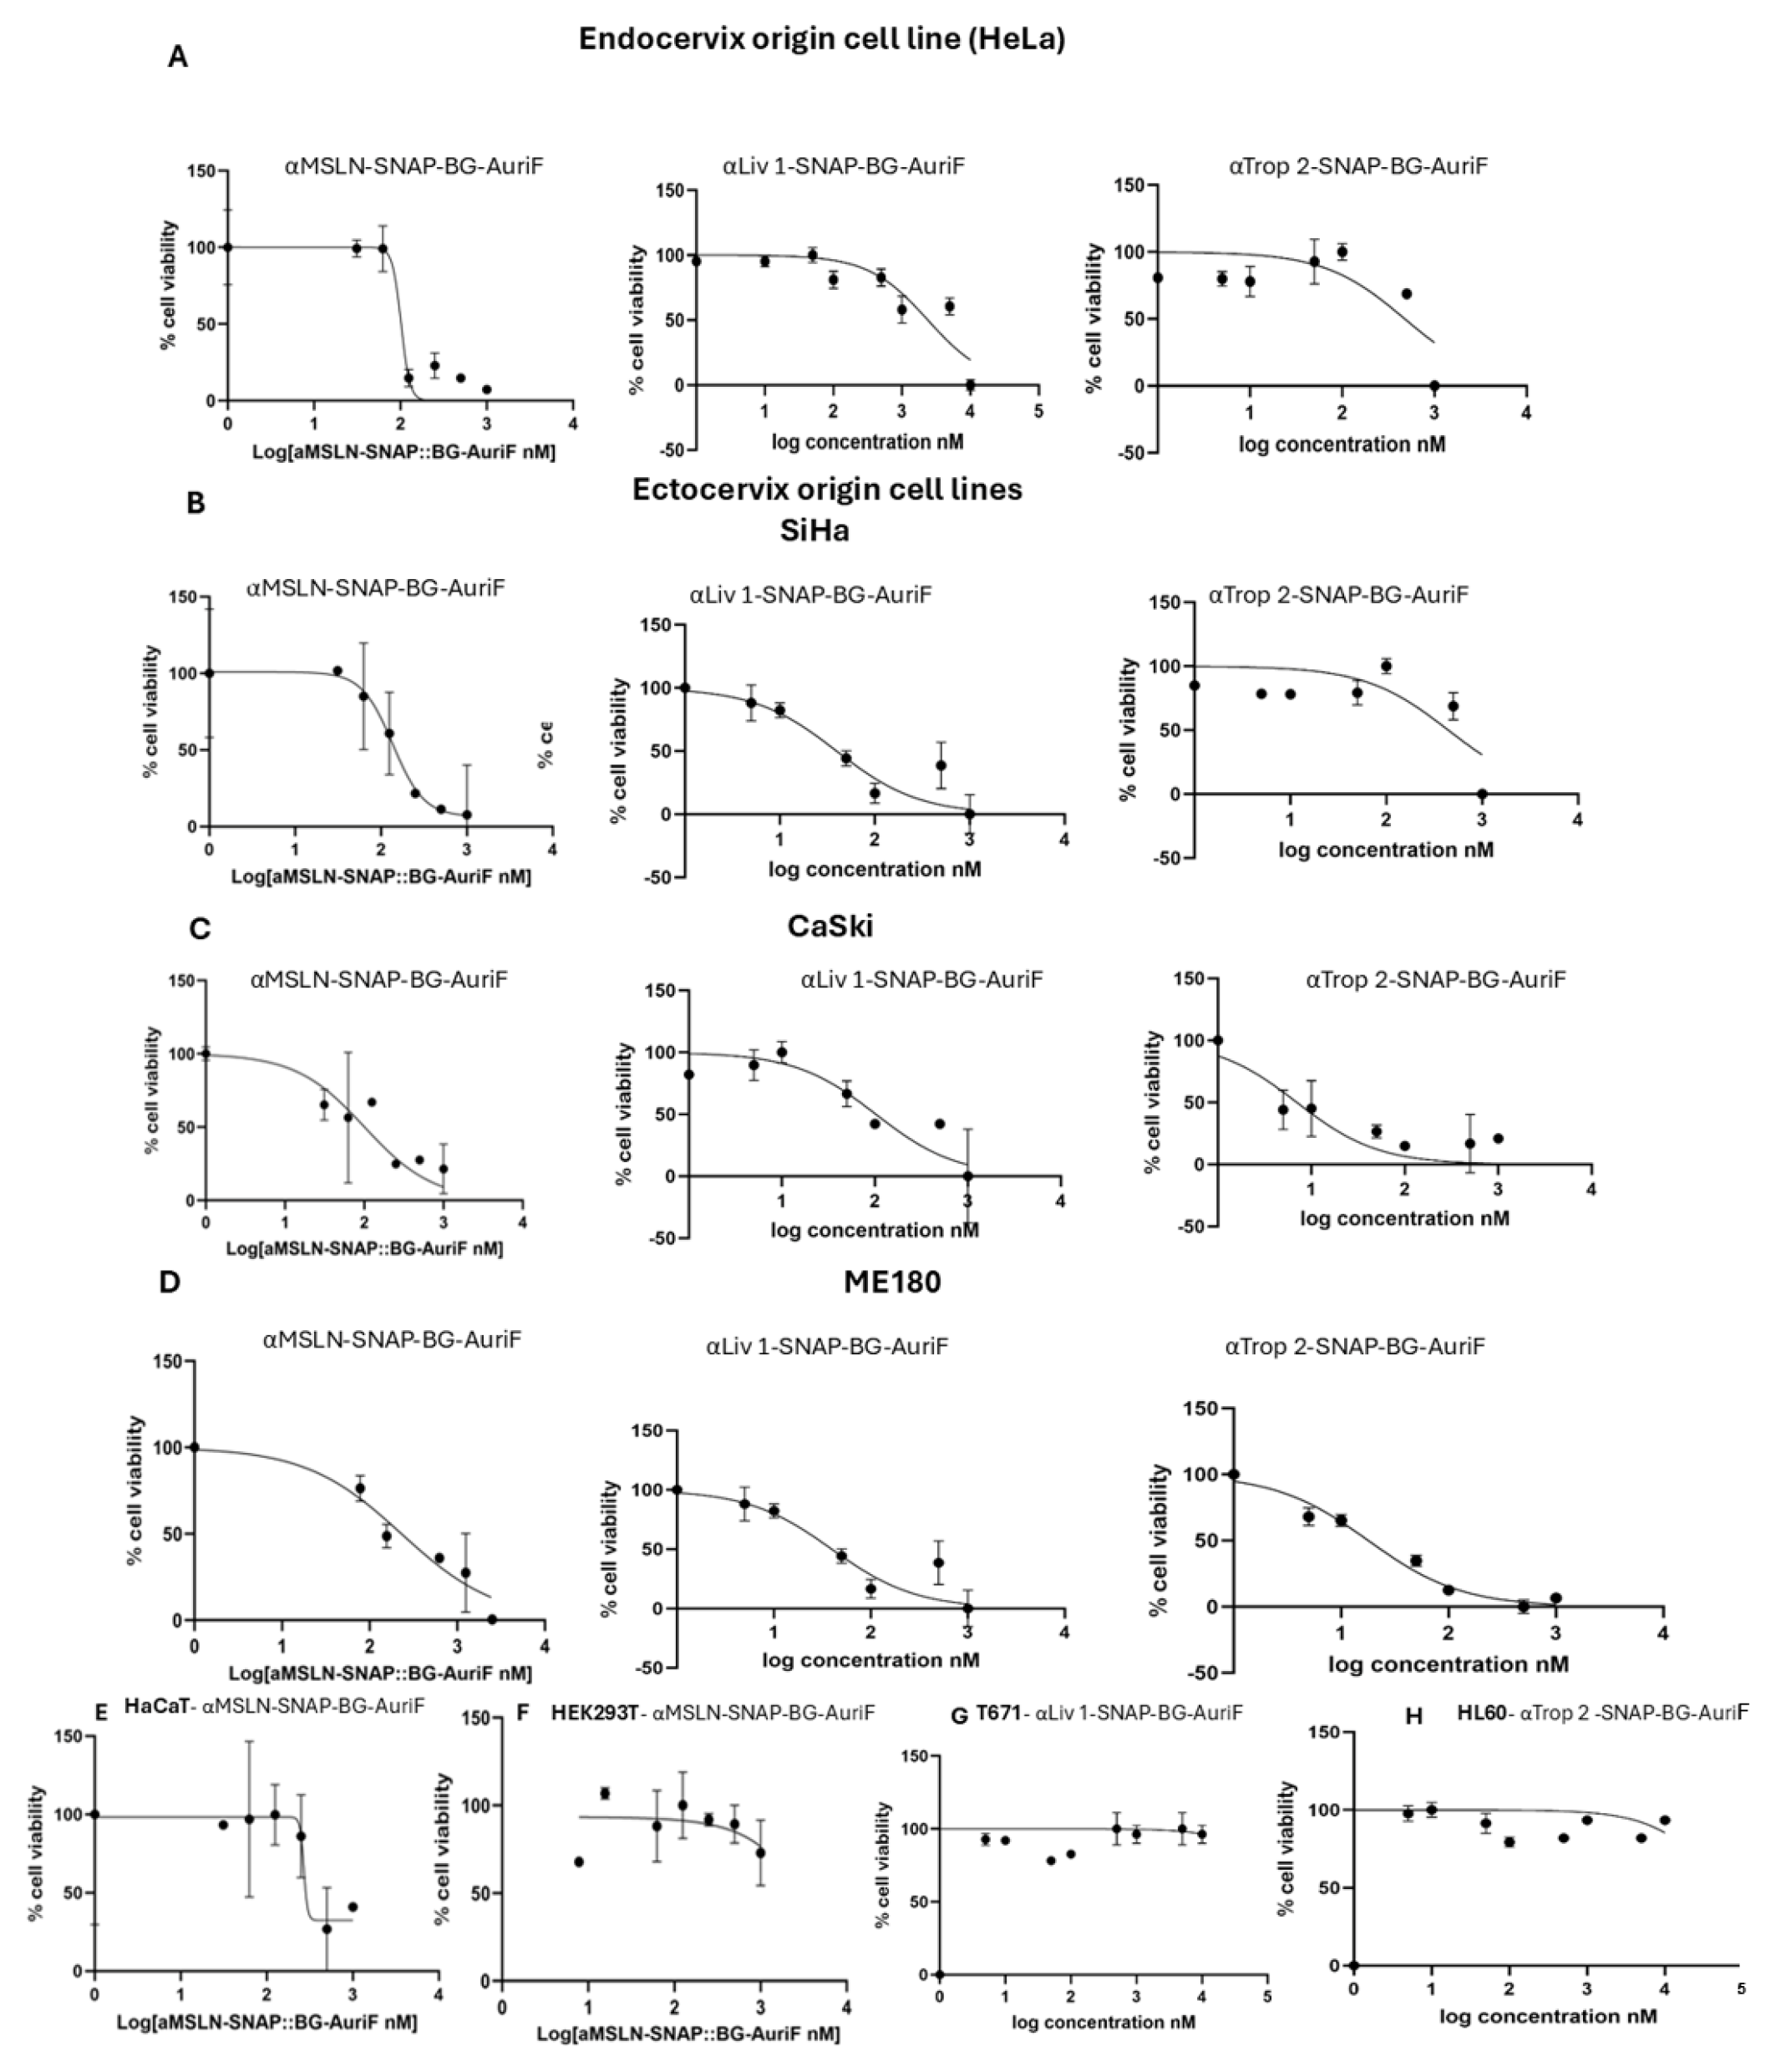
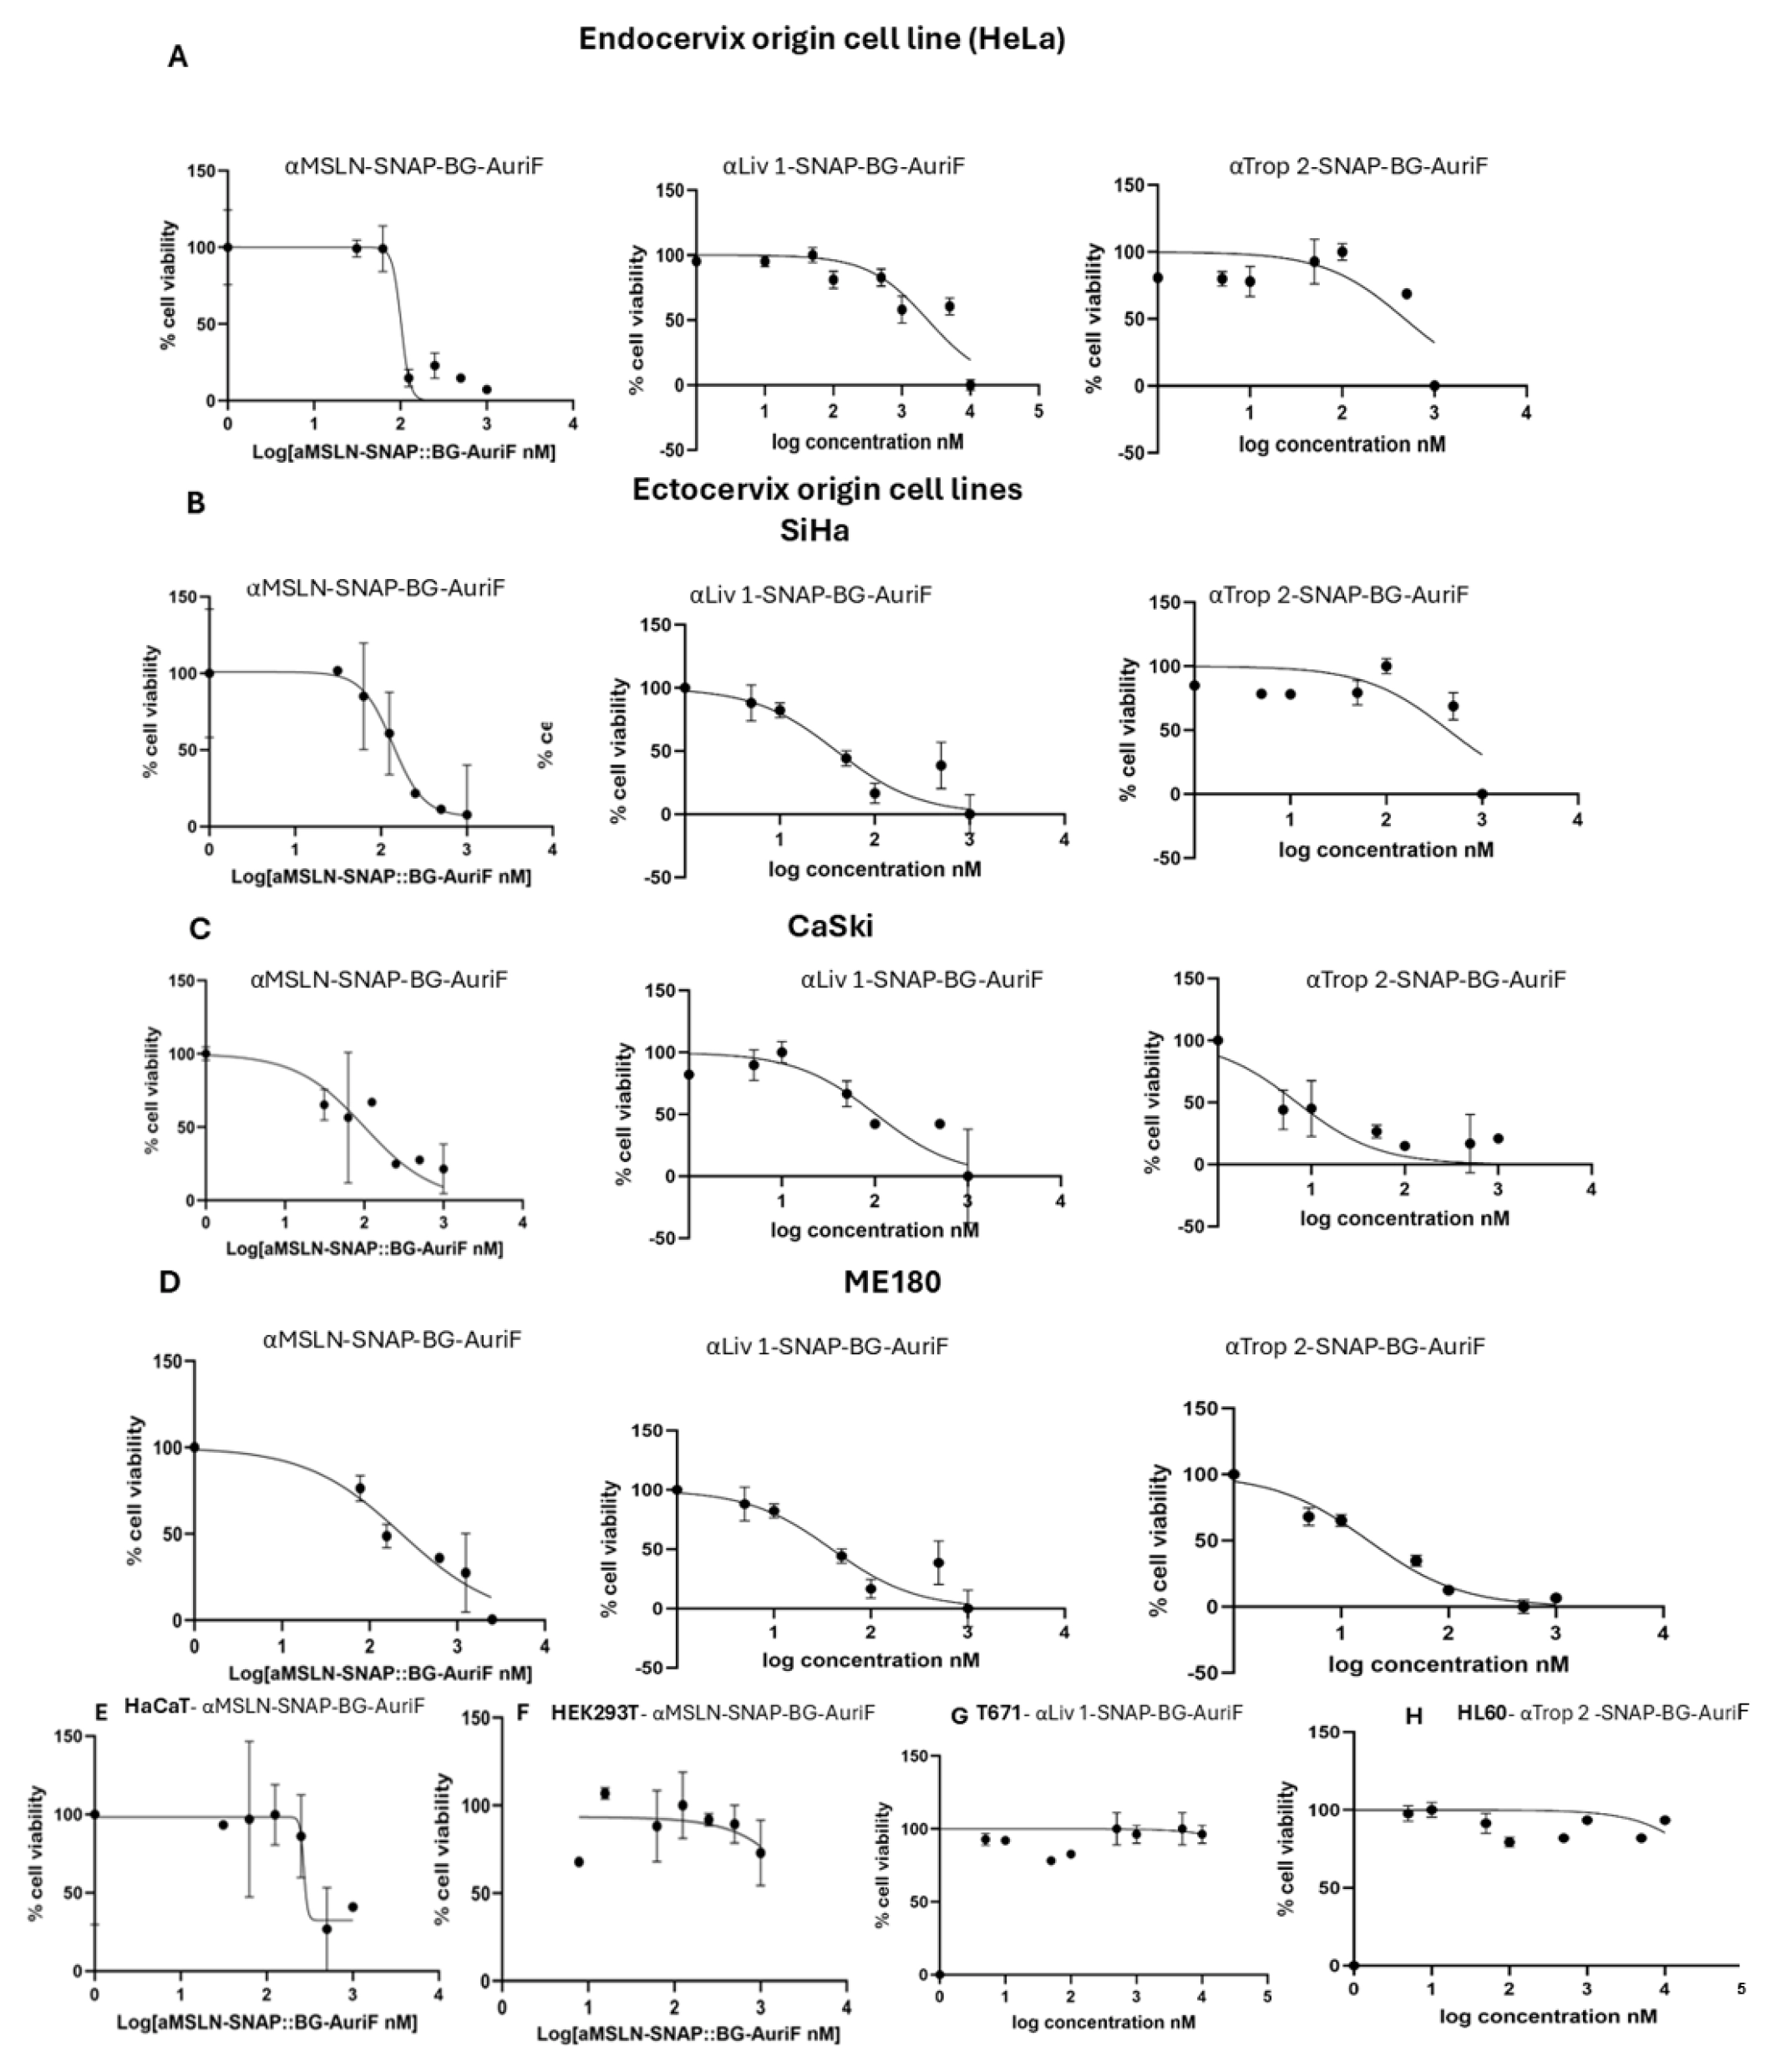
Figure 5. Cell viability curves for cervical cancer cell lines and control cell lines treated with ADCs. The (scFv)-SNAP fusion proteins were conjugated to BG-modified auristatin F, a tubulin inhibitor, to form ADCs. The ADCs were tested in vitro on cervical cancer cell lines and the control cell lines. The cell viability curves are stratified by cell line origin. Panel A shows the cell viability curves generated by treatment of the endocervical cell line HeLa with the MSLN-, LIV-1, and TROP-2-targeting ADCs. Panels B and C show the ectocervical cell lines SiHa and CaSki, respectively. Panel D shows the metastasis origin ME180 cell line, and the control cell lines are shown in panels E-H. ADCs: antibody–drug conjugates; scFv: single chain antibody fragment; SNAP: O6-alkylguanine-DNA alkyltransferase; MSLN: mesothelin; LIV-1: liver-specific protein 1; TROP-2: trophoblast cell surface antigen 2.
Cells were treated with two-fold serial dilutions of anti-αLIV-1, anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP-auristatin F (0.313 µM to 10 µM for anti-LIV-1 and 31.25 nM to 1,000 nM for αTROP-2 and αMSLN). Antigen-negative or less-expressing cells (HEK-293T) treated with anti-αLIV-1, anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP-auristatin F remained unaffected (Figure 5c). In contrast, a dose-dependent reduction in cell viability was observed in all antigen-positive cell lines treated with anti-αLIV-1, anti-TACSTD2 (αTROP-2), and anti-mesothelin (αMSLN) (scFv)-SNAP-auristatin F. The (scFv)-SNAP-auristatin F therapeutic induced antiproliferative effects (Figure 5). The αLIV-1(scFv)-SNAP-AuriF had relatively high IC50 values against the HeLa and ME180 cell lines. For HeLa cell line, this was notable given the high level of expression observed in the flow cytometric analysis. The ME180 cell line had a high IC50 as expected, given the moderate antigen expression observed in the flow cytometric analysis. Anti-TROP-2 (scFv)-SNAP-AuriF exhibited a similarly low potency against the HeLa and ME180 cell lines despite high antigen expression.
Table 5 shows the half-maximal inhibitory concentrations for the ADCs, which were determined from the cell viability studies presented in Figure 5. The αMSLN (scFv)-SNAP-AuriF ADC had a relatively high IC50 in the HaCaT cell line, indicating a lower potency against the non-cancerous cell line. Interestingly, for the same ADC, the SiHa cell line did not exhibit the highest IC50 value, despite having the lowest percentage of antigen-positive cells among the cervical cancer cell lines.
Table 5. Half maximal inhibitory concentrations with the standard deviations (nM) for ADC treatment of the cervical cancer cell lines and the control cell lines.
| Cell line | Origin | αLIV-1 (scFv)-SNAP-AuriF | αTROP-2 (scFv)-SNAP-AuriF | αMSLN (scFv)-SNAP-AuriF |
| CaSki | Cervical carcinoma-Ectocervix | 102.6 ± 1.04 nM | 7.0 ± 0.97 nM | 101.75 ± 1.48 nM |
| HeLa | Cervical carcinoma-Endocervix | 2,401 ± 3.20 nM | 476.2 ± 1.15 nM | 102.95 ± 1.34 nM |
| ME180 | Metastatic cervical carcinoma, (Ectocervical primary tumour) | 2,329 ± 8.27 nM | 443.3 ± 0.70 nM | 221.7 ± 12.59 nM |
| SiHa | Cervical carcinoma-Ectocervix | 39.5 ± 4.13 nM | 17.9 ± 1.10 nM | 138.4 ± 2.26 nM |
| TE671 | Rhabdomyosarcoma | No dose effects | - | - |
| HL60 | Myeloid leukemia | - | No dose effects | - |
| HEK293T | Embryonic cells | - | - | No dose effects |
| HaCaT | Human skin epithelium | - | - | 316.05 ± 65.83 nM |
ADCs: antibody-drug conjugates; MSLN: mesothelin; scFv: single chain antibody fragment; SNAP: O6-alkylguanine-DNA alkyltransferase; IC50: half-maximal inhibitory concentration; LIV-1: liver-specific protein 1; TROP-2: trophoblast cell surface antigen 2.
The αLIV-1(scFvLiv-1(scFv)-SNAP-Aurif had relatively high IC50 values against the HeLa and ME180 cell lines. In the case of the HeLa cell line, this was an interesting observation given the high level of expression observed in the flow cytometric analysis. The ME180 cell line had a high IC50 as was to be expected given the moderate antigen expression observed from the flow cytometric analysis. Anti-TROP-2(scFv)-SNAP-Aurif exhibited a similarly low potency against the HeLa and ME180Me180 cell lines despite their high levels of antigen expression.
Finally, the described novel ADCs achieved IC50 values in the nanomolar range against all cervical cancer cell lines, while showing no cytotoxic effect on the antigen-negative cell lines.
4. Discussion
This study applied a multi-layered global transcriptomic screen of 259 high-confidence surface protein genes across 304 primary cervical tumours, benchmarked against 7,597 healthy tissue samples spanning 52 tissue types. This approach is consistent with the principle that rational target prioritisation for ADC development requires an integrated, multi-layered analysis[15]. From this screen, 30 genes emerged as overexpressed surface candidates, all statistically significant after multiple testing correction. Three of these, TROP-2, MSLN, and EpCAM, are supported by independent evidence of cervical-cancer expression and/or therapeutic tractability in immunotherapy studies[17,28,29], providing confidence in the pipeline’s specificity. The recovery of known targets from a global screen confirms that our analytical framework is operating correctly without requiring any target-specific interpretation.
However, the global overexpression ranking alone proved insufficient to guide therapeutic prioritisation. Cervical cancer is not a single disease since SCC and adenocarcinoma arise from distinct cells of origin, namely the ectocervix and endocervix, respectively. A target overexpressed relative to a broad 52-tissue healthy composite may still be substantially expressed in the specific normal cervical tissue from which the tumour arises, raising on-target toxicity concerns that cohort-level analysis cannot detect. Tissue-of-origin refinement in this study, using dedicated GTEx v10 cervical reference profiles, materially changed the interpretation of several candidates. Genes that ranked highly in the global screen lost SCC- or adenocarcinoma-selectivity when compared directly to their tissue of origin, with fold-change estimates near zero and wide confidence intervals, confirming the instability of those estimates. This finding underscores that the choice of a normal reference is not merely a technical detail but a biologically critical decision that determines which targets are selected and for which patient populations.
Among the named candidates, MSLN emerged as the most consistent pan-CESC target, maintaining strong fold-change relative to both ectocervix and endocervix references, with tight bootstrap confidence intervals confirming the reliability of both estimates. This is consistent with the clinical cohort pattern of MSLN overexpression in cervical cancer [16], while more limited exploratory data support expression and targeting across histological subtypes[29]. TROP-2 presented a more nuanced picture: its global fold-change was the second highest in the entire screen, and it was expressed in 100% of tumours. But tissue-of-origin refinement revealed near-zero fold-change against normal ectocervix (FC = 0.04), with a wide confidence interval spanning negative values, formally indicating that TROP-2 is not selectively overexpressed relative to the SCC tissue of origin. Compared with the normal endocervix, however, it showed one of the highest fold changes, establishing it as a strong adenocarcinoma-selective target. It must be acknowledged that the tissue-of-origin fold-change estimates carry substantial uncertainty due to the limited sample sizes of both ectocervical (n = 6, Xena/Toil) and endocervical (n = 4, Xena/Toil) references. Therefore, external GTEx v10 cervical datasets (24 ectocervix, 23 endocervix) was used as the primary and only tissue-of-origin references. Although these datasets were processed using the same log2 (TPM + 0.001) transformation to maximise comparability, the use of datasets not natively integrated into the Xena/Toil pipeline represents a potential source of technical variability that cannot be fully excluded. This limitation should be addressed in future analyses using larger, natively integrated cervical tissue reference cohorts. Nevertheless, the current data are sufficient to warrant differential interpretation of TROP-2 by histological subtype, rather than treating it as a universal cervical cancer target. EpCAM showed consistent overexpression across both cervical subtypes and was taken forward for separate in vitro validation, which has been recently published by our group[19].
Perhaps the most instructive finding was the case of LIV-1. A review of the targetability literature flagged LIV-1 as a candidate of interest in cervical cancer based on its reported roles in EMT and invasive behaviour[22,26,30,31], yet it was entirely absent from the top 30 genes in the global screen, with a cohort-wide fold-change of only 0.97. Rather than dismissing the target, we asked whether its signal might be concentrated within a biologically distinct subpopulation diluted by the majority of non-expressing tumours. Stratification by expression z-score identified 14 high-expressing tumours, 4.6% of the cohort, with a subgroup median of 122.7 TPM and a fold-change of 3.07 (95% CI [2.81, 3.29]). This positions LIV-1 not only as a pan-tumour antigen but also as a prominent exploratory subgroup marker, identifying it as a precision medicine candidate that would have been entirely overlooked by a conventional ranked-list approach. Taken together, our three-tier analytical framework, global overexpression screening, tissue-of-origin subtype refinement, and subpopulation stratification, reveals that no single metric can adequately resolve cervical cancer heterogeneity and that each tier of analysis uncovers a distinct class of therapeutically relevant target.
The experimental validation largely mirrored these transcriptomic findings but also highlighted key limitations of mRNA-based prediction. Both αMSLN-SNAP and αTROP-2-SNAP exhibited strong surface binding across the cervical cancer cell line panel, confirming antigen accessibility at the protein level. MSLN binding ranged from 43.6% to 99.4% with selective nanomolar cytotoxicity, consistent with its robust tumour–normal transcript contrast (HaCaT IC50 = 316 nM reflects residual normal expression, N log2 = -1.44). TROP-2 showed strong potency in SCC lines (CaSki: IC50 = 7.0 nM; SiHa: IC50 = 17.9 nM) and remained potent in adenocarcinoma HeLa (IC50 = 476.2 nM). However, cell line data cannot reproduce the tumour:healthy tissue ratio that defines therapeutic safety. Transcriptomics reveals that the true therapeutic window lies in adenocarcinomas, where TROP-2 remains potent and normal endocervical tissue shows minimal expression, unlike SCC, where the normal ectocervical baseline limits selectivity. LIV-1 potency aligned with the transcriptomic subgroup prediction by virtue of a strong cytotoxicity in CaSki (IC50 = 102.6 nM; 39.5 nM in SiHa) but minimal activity in HeLa/ME180 (> 2,300 nM), suggesting that the LIV-1-high transcriptomic subtype corresponds to cell line-responsive phenotypes.
To date, research on LIV-1 in cervical cancer remains limited. Several studies have demonstrated its correlation with aggressive breast cancer phenotypes, an increased likelihood of lymph node metastasis[30], and its role in modulating apoptosis and mitotic cell fate[32]. Direct cervical evidence is confined to the HeLa cervical cancer cell line, in which RNAi-mediated knockdown significantly inhibited cell proliferation, colony formation, migration, and invasiveness[26]. No studies to date have targeted LIV-1 therapeutically in advanced cervical cancer, although it has been an attractive target in breast cancer, where multiple LIV-1 ADCs have demonstrated cytotoxicity. Ladiratuzumab vedotin, a monoclonal antibody conjugated to monomethyl auristatin E (MMAE) via a protease-cleavable linker targeting LIV-1 has been investigated in early-phase clinical trials in breast cancer[33]. In a recent study by Peng et al., the authors described Ladiratuzumab vedotin as the first LIV-1-targeting ADC to enter clinical trials but further noted that it has since been discontinued from clinical development[34]. They also described a novel anti-LIV-1 ADC conjugated to a topoisomerase 1 inhibitor, suggesting that LIV-1 is still a favourable target for cancer immunotherapy despite the performance of earlier LIV-1 targeting ADCs in clinical trials[34]. The present study provides encouragement for investigating LIV-1 as a therapeutic target in cervical cancer, in which the potent cytotoxic effect observed in SCC-derived cell lines highlights its potential in the biologically defined subpopulation identified transcriptomically.
In contrast, TROP-2 has accumulated substantial evidence in cervical cancer in recent years. Overexpression has been reported in squamous cell carcinomas of multiple organs, including the uterine cervix[35], with prognostic significance supporting its candidacy for targeted therapies[17]. The findings of this study are consistent with previously published observations of high TROP-2 expression in both SCC and adenocarcinoma[17,35], with overall TROP-2 positivity in cervical carcinoma reported to range from 84.6% to 98.5%[35]. At the time of writing, no TROP-2-directed ADC has yet been approved specifically for cervical cancer, but the class is advancing quickly in this setting given the frequent expression of TROP-2 in cervical tumours[17,35]. Sacituzumab govitecan, a humanised anti-TROP-2 antibody conjugated to SN-38 at a drug-to-antibody ratio (DAR) of 7 and already approved for triple-negative metastatic breast cancer[37], achieved an objective response rate of 43% in recurrent or metastatic cervical cancer in the phase 2 EVER-132-003 study[38]. Datopotamab deruxtecan (Dato-DXd), composed of a humanised anti-TROP-2 antibody linked to a topoisomerase I inhibitor via a cleavable tetrapeptide linker at a DAR of 4, has achieved IC50 values in the micromolar range against non-small cell Lung cancer (NSCLC) and breast cancers and has demonstrated preclinical activity in cervical carcinoma cell lines[36,39]. SKB264, a TROP-2 ADC with a DAR of 7 carrying the belotecan-derived payload KL610023, has demonstrated reductions in tumour cell survival and outperformed conventional chemotherapy in NSCLC[39].
MSLN has been widely explored as an immunotherapy target across multiple cancer types[40-42], given its overexpression in tumours such as mesothelioma and ovarian cancer[43]. Its appeal as a target stems from its restricted normal-tissue expression[43] and evidence that it is nonessential for healthy cell survival[27]. In a retrospective surgical cohort, high MSLN expression was observed in 80.4% of non-SCC patients and 49.2% of SCC patients [16], directly corroborating the transcriptomic findings of the current study, which showed robust overexpression in adenocarcinoma and lower but consistent expression in SCC. The apparent discrepancy between the percentage of SiHa cells expressing MSLN (43.6%) and the near-nanomolar IC50 obtained with αMSLN-SNAP-AuriF may reflect the transcriptomic observation of variable MSLN expression density in SCC, in which a subpopulation of SiHa cells expressing high MSLN density could drive cytotoxic response despite lower overall surface positivity. An additional contributing factor is the well-documented phenomenon of MSLN shedding from the cell membrane surface, which can generate variable surface expression across cell lines and remains a recognised limitation for MSLN-targeting immunotherapies[44-46]. Efforts to address shedding are ongoing, and MSLN-targeting ADCs such as anetumab ravtansine have shown promising in vivo potential[47].
Beyond the primary screen, the prioritised targets were examined against orthogonal evidence using protein immunohistochemistry, single-cell transcriptomics, and independent bulk cohorts. These lines were mutually reinforcing but target-specific rather than uniform: TROP-2’s staining in normal ectocervical but not endocervical epithelium independently supported its adenocarcinoma-selectivity; MSLN’s single-cell adenocarcinoma enrichment mirrored the histology-based pattern reported clinically[16]; and the weak protein and single-cell signal for LIV-1 was consistent with its restriction to a small subpopulation. The independent cervical datasets available are, however, imperfect since public cohorts are dominated by squamous carcinoma, single-cell studies include few adenocarcinoma patients, and no bulk RNA-seq dataset pairs tumours with matched normal cervical tissue at adequate surface-gene coverage. This scarcity is precisely why the primary screen was built on the UCSC Xena/Toil recompute, in which tumour and normal samples pass through one identical pipeline, giving an internally consistent, batch-effect-free tumour-versus-normal comparison that assemblies of separate datasets cannot reproduce. The convergent but incomplete external evidence therefore supports the targets while underscoring a broader need for matched tumour–normal and single-cell cervical datasets for definitive orthogonal validation.
All three (scFv)-SNAP fusion ADCs generated in this study share an important structural feature that distinguishes them from many current clinical ADCs, namely the irreversible SNAP-tag/BG reaction. By design, this reaction is expected to yield a defined 1:1 antibody-to-drug stoichiometry (theoretical DAR = 1), which should mitigate the heterogeneity associated with a high average DAR that is linked to reduced efficacy[48,49], although the actual DAR of the present conjugates was not measured analytically. The use of auristatin F rather than the more commonly employed auristatin E as the cytotoxic payload may further improve the tolerability profile, since auristatin E can passively diffuse through cell membranes, causing bystander off-target toxicity and hence limiting tolerable doses in clinical settings[50,51]. Auristatin F, by contrast, carries a slight charge that limits passive membrane diffusion and is expected to reduce off-target effects[52], though the general ADC safety literature cited here does not provide a direct comparative assessment for the present constructs. The present study serves as proof-of-concept for the efficacy of targeting LIV-1, TROP-2, and MSLN with SNAP-tag-based auristatin F-delivering ADCs in cervical cancer.
Several limitations of this study warrant discussion. Firstly, all transcriptomic findings are based on mRNA expression. The correlation between mRNA abundance and surface protein density in bulk data is real but moderate, and the LIV-1 case illustrates this directly: despite a limited cohort-level transcriptomic FC, clear protein-level surface accessibility was observed in specific cell lines, demonstrating that transcript-level analysis and surface protein validation are complementary rather than interchangeable. Secondly, the cell lines used for in vitro validation cannot replicate the tumour–normal safety contrast that population-level transcriptomics provides: cell lines confirm antigen accessibility and cytotoxic potency but do not model the tissue-of-origin expression context that determines therapeutic window in vivo. Patient-derived organoids, which preserve the tumour microenvironment and normal epithelial cellular context, represent a more physiologically relevant validation platform and are strongly recommended for future pre-clinical follow-up. Thirdly, bulk RNA sequencing averages expression across all cell types present in the tumour sample cancer cells, stromal cells, and immune infiltrate with the median expression therefore reflecting this mixture rather than the cancer cell population alone. This is particularly relevant for LIV-1, where subpopulation dynamics drive the biology and are partially obscured by bulk averaging. Single-cell RNA sequencing would allow direct characterisation of the LIV-1-high subpopulation, more precise assignment of expression to cancer cells versus stroma, and more accurate estimation of the proportion of patients likely to benefit from LIV-1-directed therapy. Finally, all TCGA samples analysed were primary resections expressed in recurrent or metastatic cervical cancer. Importantly, the clinical setting in which novel therapeutics are most urgently needed may differ substantially and should be evaluated in dedicated cohorts.
Looking beyond the targets validated here, this analysis points towards a broader strategic framework. At present, it is not possible to determine from transcriptomics alone how many distinct surface antigen profiles exist across cervical cancer subtypes, or how many markers would be required to achieve comprehensive diagnostic and therapeutic coverage across the full spectrum of SCC, adenocarcinoma, and exploratory high-expressing subgroups such as the LIV-1-high group identified here. Future analyses integrating single-cell transcriptomics, surface proteomics, and immunofluorescence on patient-derived samples could directly assign antigen subtype membership, enabling personalised antigen panel selection. An approach based on SNAP-tag fusion ADCs, with their modular and precisely controlled conjugation chemistry, may particularly well suited for implementation.
5. Conclusion
This study demonstrates how multi-layered transcriptomic analysis, progressing from global surface target discovery through tissue-of-origin subtype refinement to subpopulation stratification, can inform the rational engineering of (scFv)-SNAP fusion ADCs. Starting from a global computational screen and integrating targeted literature review at each analytical tier, we identified three candidates with distinct and complementary therapeutic profiles: MSLN as a pan-CESC target with broad subtype coverage, TROP-2 as an adenocarcinoma-selective target with the strongest global expression signal, and LIV-1 as a precision medicine candidate for a biologically defined subpopulation. The in vitro validation confirmed antigen accessibility, selective surface binding, and dose-dependent cytotoxicity across cervical cancer cell lines. Working in productive symbiosis with transcriptomic predictions, these approaches revealed complementary insights that together refine therapeutic prioritisation for next-generation immunotherapeutics.
Supplementary materials
The supplementary material for this article is available at: Supplementary materials.
Acknowledgements
The authors thank Tim Reid of the South African Tuberculosis Vaccine Initiative (SATVI), University of Cape Town, for his availability to assist with the use of the flow cytometers as needed. The authors thank Prof. Dirk Lang of the Department of Human Biology for his assistance in capturing microscopy images.
Authors contribution
Matshoba T: Conceptualization, methodology, writing-original draft, writing-review & editing.
Bolotnikov V: Conceptualization, methodology, writing-original draft.
Barth S: Conceptualization, resources, writing-review & editing, funding acquisition, supervision.
Henry M: Methodology.
Hunter R, Lekena N: Resources, writing-review & editing.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Funding
This research was funded by the South African Research Chairs Initiative of the Department of Science and Technology of South Africa with the National Research Foundation (NRF) (Grant NO. 47904). Scholarship from the National Research Foundation to support the first author of this work (Reference NO. PMDS230606114238).
Copyright
© The Author(s) 2026.
References
-
1. World Health Organization. Global strategy to accelerate the elimination of cervical cancer as a public health problem. Geneva: World Health Organization; 2020 Nov. 17 p. 56. Available from: https://www.who.int/publications/i/item/9789240014107
-
2. Arbyn M, Weiderpass E, Bruni L, de Sanjosé S, Saraiya M, Ferlay J, et al. Estimates of incidence and mortality of cervical cancer in 2018: A worldwide analysis. Lancet Glob Health. 2020;8(2):e191-e203.[DOI]
-
5. Li J, Wu T, Cai M, Xie C, Ding S, Zou W, et al. Prognostic analysis of nimotuzumab combined with concurrent chemoradiotherapy for locally advanced cervical cancer: A multicenter real-world study. Sci Rep. 2025;15(1):15877.[DOI]
-
6. Gerriets V, Kasi A. Bevacizumab. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026.[PubMed]
-
7. Jia Y, Zhang F, Zou K, Zou L. A clinical study on the efficacy of concurrent chemoradiotherapy combined with targeted therapy and hyperthermia in patients with locally advanced cervical cancer. Transl Oncol. 2025;61:102516.[DOI]
-
8. Huysamen AM, Fadeyi OE, Mayuni G, Dogbey DM, Mungra N, Biteghe FAN, et al. Click chemistry-generated auristatin F-linker-benzylguanine for a SNAP-tag-based recombinant antibody-drug conjugate demonstrating selective cytotoxicity toward EGFR-overexpressing tumor cells. ACS Omega. 2023;8(4):4026-4037.
-
9. Buyukgolcigezli I, Tenekeci AK, Sahin IH. Opportunities and challenges in antibody-drug conjugates for cancer therapy: A new era for cancer treatment. Cancers. 2025;17(6):958.[DOI]
-
10. Magagoum SH, Siwe GT, Biteghe FAN, Huysamen AM, Lang D, Hunter R, et al. Melanotransferrin as a potential target for the selective killing of melanoma and triple-negative breast cancer cells in vitro using novel SNAP-tag-based antibody-AURIF conjugate. Onco. 2025;6(1):1.[DOI]
-
12. Magagoum SH, Biteghe FAN, Siwe GT, Lang D, Lekena N, Barth S. SNAP-tag-based recombinant photoimmunotherapeutic agents for the selective detection and killing of light-accessible melanotransferrin-expressing melanoma and triple-negative breast cancer. Cancer Med. 2025;14(9):e70912.
-
13. Zhang C, Sheng W, Mohiuddin TM, Al-Rawe M, Schmitz R, Niebert M, et al. SNAP-tag-based antibody-drug conjugates targeting epidermal growth factor receptor 1, epidermal growth factor receptor 2, trophoblast cell-surface antigen 2, and tissue factor for ovarian cancer treatment. ACS Omega. 2026;11(11):17393-17403.
-
14. Fan Q, Chen H, Wei G, Wei D, Wang Z, Zhang L, et al. A review of conjugation technologies for antibody drug conjugates. Antib Ther. 2025;8(2):157-170.[DOI]
-
16. Takamizawa S, Yazaki S, Kojima Y, Yoshida H, Kitadai R, Nishikawa T, et al. High mesothelin expression is correlated with non-squamous cell histology and poor survival in cervical cancer: A retrospective study. BMC Cancer. 2022;22(1):1215.[DOI]
-
17. Chiba Y, Kojima Y, Yazaki S, Yoshida H, Takamizawa S, Kitadai R, et al. Trop-2 expression and the tumor immune microenvironment in cervical cancer. Gynecol Oncol. 2024;187:51-57.[DOI]
-
18. Mungra N, Nsole Biteghe FA, Huysamen AM, Hardcastle NS, Bunjun R, Naran K, et al. An investigation into the in vitro targeted killing of CD44-expressing triple-negative breast cancer cells using recombinant photoimmunotherapeutics compared to auristatin-F-based antibody-drug conjugates. Mol Pharm. 2024;21(8):4098-4115.[DOI]
-
19. Andong-Koung-Edzidzi UC, Matshoba T, Lang D, Hunter R, Barth S. Auristatin F-delivering SNAP-tag based recombinant antibody-drug conjugate targeting EpCAM demonstrating selective in vitro killing of cervical and triple-negative breast cancer cell lines. J Pharm Pharmacol Res. 2026;10(1):1-14.[DOI]
-
20. Vivian J, Rao AA, Nothaft FA, Ketchum C, Armstrong J, Novak A, et al. Toil enables reproducible, open source, big biomedical data analyses. Nat Biotechnol. 2017;35(4):314-316.[DOI]
-
21. Goldman MJ, Craft B, Hastie M, Repečka K, McDade F, Kamath A, et al. Visualizing and interpreting cancer genomics data via the Xena platform. Nat Biotechnol. 2020;38(6):675-678.[DOI]
-
22. Alzahrani AM, Taylor KM. Zinc transporters of the LIV-1 subfamily in various cancers: Molecular insights and research priorities for Saudi Arabia. Int J Mol Sci. 2025;26(16):8080.[DOI]
-
23. Song E, Zheng H, Zhang H, Lu J, Yan M, Wu J, et al. Association of LIV-1 expression with clinical efficacy in patients with advanced breast cancers treated with BRY812. J Clin Oncol. 2025;43(16_suppl):e15005.[DOI]
-
24. Dehghan R, Parikhani AB, Cohan RA, Shokrgozar MA, Mirabzadeh E, Ajdary S, et al. Specific targeting of zinc transporter LIV-1 with Immunocytokine Containing anti-LIV-1 VHH and human IL-2 and evaluation of its in vitro antitumor activity. Curr Pharm Des. 2024;30(11):868-876.[DOI]
-
25. Yamazoe S, Poudel Y, Sega E, Mukhopadhyay A, Ramakrishnan R, Ukairo O, et al. Discovery and characterization of a first-in-class LIV1-TLR7/8 immunomodulatory conjugate with robust myeloid activation and antitumor activity. J Med Chem. 2025;68(11):11322-11339.[DOI]
-
26. Zhao L, Chen W, Taylor KM, Cai B, Li X. LIV-1 suppression inhibits HeLa cell invasion by targeting ERK1/2-Snail/Slug pathway. Biochem Biophys Res Commun. 2007;363(1):82-88.[DOI]
-
27. Boisgard R, Chames P, Kerfelec B. Mesothelin biology and the evolving landscape of targeted immunotherapy. Mol Ther Oncol. 2026;34(1):201148.[DOI]
-
28. Li D, Guo X, Yang K, Yang Y, Zhou W, Huang Y, et al. EpCAM-targeting CAR-T cell immunotherapy is safe and efficacious for epithelial tumors. Sci Adv. 2023;9(48):eadg9721.[DOI]
-
30. Grattan BJ, Freake HC. Zinc and cancer: Implications for LIV-1 in breast cancer. Nutrients. 2012;4(7):648-675.[DOI]
-
31. Cheng X, Wei L, Huang X, Zheng J, Shao M, Feng T, et al. Solute carrier family 39 member 6 gene promotes aggressiveness of esophageal carcinoma cells by increasing intracellular levels of zinc, activating phosphatidylinositol 3-kinase signaling, and up-regulating genes that regulate metastasis. Gastroenterology. 2017;152(8):1985-1997.e12.
-
32. Chen P, Wang B, Mo Q, Wu P, Fang Y, Tian Y, et al. The LIV-1-GRPEL1 axis adjusts cell fate during anti-mitotic agent-damaged mitosis. eBioMedicine. 2019;49:26-39.[DOI]
-
36. Ettorre VM, Demirkiran C, Bellone S, Hartwich TMP, Greenman M, McNamara B, et al. Effective preclinical activity of datopotamab deruxtecan (Dato-DXd), an ADC targeting trophoblast cell-surface antigen 2 (TROP2), against primary cervical carcinoma cell lines and xenografts. Gynecol Oncol. 2025;201:195-202.[DOI]
-
37. Bardia A, Hurvitz SA, Tolaney SM, Loirat D, Punie K, Oliveira M, et al. Sacituzumab govitecan in metastatic triple-negative breast cancer. N Engl J Med. 2021;384(16):1529-1541.[DOI]
-
38. An J, Li G, Zhang Y, Feng M, Kong W, Jiang H, et al. Sacituzumab govitecan in Chinese patients with recurrent/metastatic cervical cancer: Results from the phase 2 EVER-132-003 basket study (NCT05119907). Gynecol Oncol. 2025;202:33-40.[DOI]
-
39. Zhang X, Xiao H, Na F, Sun J, Guan Q, Liu R, et al. Evolution of TROP2: Biological insights and clinical applications. Eur J Med Chem. 2025;296:117863.[DOI]
-
40. Zhu Y, Zuo D, Wang K, Lan S, He H, Chen L, et al. Mesothelin-targeted CAR-T therapy combined with irinotecan for the treatment of solid cancer. J Cancer Res Clin Oncol. 2023;149(16):15027-15038.[DOI]
-
41. Torchiaro E, Cortese M, Petti C, Basirico’ M, Invrea F, D’Andrea A, et al. Repurposing anti-mesothelin CAR-NK immunotherapy against colorectal cancer. J Transl Med. 2024;22(1):1100.[DOI]
-
43. Weidemann S, Gagelmann P, Gorbokon N, Lennartz M, Menz A, Luebke AM, et al. Mesothelin expression in human tumors: A tissue microarray study on 12,679 tumors. Biomedicines. 2021;9(4):397.[DOI]
-
44. Liu X, Chan A, Tai CH, Andresson T, Pastan I. Multiple proteases are involved in mesothelin shedding by cancer cells. Commun Biol. 2020;3(1):728.[DOI]
-
45. Luckett T, Abudula M, Ireland L, Glenn M, Bellomo G, Stafferton R, et al. Mesothelin secretion by pancreatic cancer cells co-opts macrophages and promotes metastasis. Cancer Res. 2024;84(4):527-544.[DOI]
-
46. Awuah P, Bera TK, Folivi M, Chertov O, Pastan I. Reduced shedding of surface mesothelin improves efficacy of mesothelin-targeting recombinant immunotoxins. Mol Cancer Ther. 2016;15(7):1648-1655.[DOI]
-
47. Hassan R, Blumenschein GR Jr, Moore KN, Santin AD, Kindler HL, Nemunaitis JJ, et al. First-in-human, multicenter, phase I dose-escalation and expansion study of anti-mesothelin antibody-drug conjugate anetumab ravtansine in advanced or metastatic solid tumors. J Clin Oncol. 2020;38(16):1824-1835.
-
49. Wen M, Yu A, Park Y, Calarese D, Gerber HP, Yin G. Homogeneous antibody-drug conjugates with dual payloads: Potential, methods and considerations. mAbs. 2025;17(1):2498162.[DOI]
-
50. Nguyen TD, Bordeau BM, Balthasar JP. Mechanisms of ADC toxicity and strategies to increase ADC tolerability. Cancers. 2023;15(3):713.[DOI]
-
52. Jain S, Griffith JI, Porath KA, Rathi S, Le J, Pasa TI, et al. Bystander effects, pharmacokinetics, and linker-payload stability of EGFR-targeting antibody-drug conjugates losatuxizumab vedotin and depatux-M in glioblastoma models. Clin Cancer Res. 2024;30(15):3287-3297.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Matshoba T, Bolotnikov V, Henry M, Lekena N, Hunter R, Barth S. Multi-database transcriptomic screening to identify subtype-selective cell surface targets for development of SNAP-tag based immunotherapeutics. Comput Biomed. 2026;1:202615. https://doi.org/10.70401/cbm.2026.0023
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

 Get citation
Science Exploration Style

Matshoba T, Bolotnikov V, Henry M, Lekena N, Hunter R, Barth S. Multi-database transcriptomic screening to identify subtype-selective cell surface targets for development of SNAP-tag based immunotherapeutics. Comput Biomed. 2026;1:202615. https://doi.org/10.70401/cbm.2026.0023
copy
Share Link
copy