AS01 adjuvant is a trained immunity inducer with potent antitumor activity

Mihai Simioniuc
1

,
Athina Boumpas
2,3
,
Martin Jaeger
1
,
Pepijn van Houten
4
,
Titus Schlüter
1
,
Romana T. Netea-Maier
4
,
Athanasios Ziogas
1,5
,
Panayotis Verginis
2,3,6
,
Mihai G. Netea
1,7,*
*Correspondence to:
Mihai G. Netea, Department of Internal Medicine and Radboud Center for Infectious Diseases, Radboud University Medical Center, Nijmegen, Gelderland 6500 HB, Netherlands; Department of Immunology and Metabolism, Life and Medical Sciences Institute, University of Bonn, Bonn, North Rhine-Westphalia 53113, Germany.
E-mail: Mihai.Netea@radboudumc.nl
Myeloid Cells. 2026;1:202615. 10.70401/mc.2026.0011
Received: June 16, 2026Accepted: August 21, 2026Published: August 21, 2026
Abstract
Aims: Trained immunity, defined as long-term functional reprogramming of innate immune cells, has been implicated in the heterologous protective effects of certain vaccines against infection and cancer. AS01-adjuvanted vaccines have been suggested to provide such heterologous protective effects. We therefore aimed to investigate the capacity of AS01 to induce trained immunity and evaluated its potential as an antitumoral therapeutic.
Methods: Acute cytokine production was assessed in human monocytes after AS01 stimulation. Trained immunity was subsequently evaluated by interleukin-6 (IL-6) and tumor necrosis factor (TNF) quantification following heterologous restimulation. Antitumor efficacy of AS01 was assessed in mice bearing B16-F10 melanoma, MB49 bladder cancer, or Lewis lung carcinoma by monitoring tumor growth. Immune phenotyping of B16-F10 and MB49 tumor microenvironments was determined with flow cytometry.
Results: Although AS01 did not stimulate acute inflammation, it induced trained immunity, marked by increased responsiveness upon secondary stimulation in human monocytes. Treatment of mice bearing B16-F10 melanoma or MB49 bladder cancer with AS01 strongly diminished tumor growth, whereas no effect was observed in the Lewis lung carcinoma model. In these responsive models, the antitumor effects of AS01 were associated with an altered tumor microenvironment, characterized by increased infiltration of CD8+ T cells, regulatory T cells, neutrophils, and monocytes, along with a decrease in tumor-associated macrophages. AS01 also decreased expression of immune checkpoint protein PD-L1 in monocytes and neutrophils, suggesting enhanced antitumor immune responsiveness.
Conclusion: Our findings show the capacity of AS01 to induce trained immunity and support its potential to be repurposed as an immunotherapeutic approach for cancer.
Keywords
Trained immunity, AS01, Shingrix, cancer immunotherapy
1. Introduction
Cancer is one of the most important causes of mortality worldwide, representing a substantial global disease burden that is projected to increase in the coming decades[1-3]. It is generally accepted that the immunosuppressive tumor microenvironment (TME) plays a key role in cancer initiation, progression and metastasis[4]. While innate immune cells such as monocytes, macrophages and neutrophils serve as the first line of defense against infections, TME-specific cues can polarize myeloid-derived cells of cancer patients toward an immunosuppressive, pro-tumorigenic phenotype[4,5]. Consequently, strategies aimed at rewiring innate immune cells toward an antitumor phenotype represent an attractive prospect for cancer immunotherapy.
Traditionally, the ability to mount an immune memory response was believed to be restricted to the T and B cells of the adaptive immune compartment[6]. However, a growing body of literature has shown that innate immune cells undergo long-term metabolic and epigenetic reprogramming as a response to pathogen exposure, a process termed ‘trained immunity’[7-9]. Following a secondary challenge, even if different from the first one, trained cells exhibit heightened effector functions, such as increased reactive oxygen species (ROS) production, upregulated phagocytosis, and elevated transcription and secretion of pro-inflammatory cytokines[10-12]. While the therapeutic induction of trained immunity has been predominantly investigated in the context of infections[13-15], trained immunity-inducing vaccines such as Bacille Calmette Guerin have been known to have therapeutic efficacy in various types of cancer, especially bladder carcinoma[16-18]. In addition, recent studies have also shown the effectiveness of training stimuli in experimental cancer models[11,19-23].
There is increasing epidemiological evidence suggesting that vaccines containing Adjuvant System AS01, a liposomal formulation consisting of immunostimulants 3-O-desacyl-monophosphoryl lipid A (MPL) and the saponin QS-21[24], induce heterologous protection against other infections. In a large retroactive cohort study, the administration of AS01-adjuvanted Shingrix recombinant zoster vaccine was associated with a 16% lower rate of COVID-19 diagnosis and a 32% decrease in COVID-19 hospitalization compared to unvaccinated controls[25]. The RTS,S/AS01 (Mosquirix) malaria vaccine was shown to reduce all-cause mortality by 13% in children, beyond what can be explained by malaria prevention alone[26-28]. Besides the heterologous protection characteristic of trained immunity, AS01 has also been shown to induce long-term epigenetic and transcriptomic remodeling in human monocytes[29]. Considering these biological effects of AS01, as well as its known safety profile[30], we hypothesized that AS01 may exert useful immunostimulatory effects in non-infectious diseases as well, including cancer.
In this study, we show that AS01 induced a functional in vitro training phenotype in human monocytes, leading to the upregulation of inflammatory cytokine production upon lipopolysaccharide rechallenge. Subsequently, AS01 administration reduced tumor growth in both melanoma and bladder cancer mouse models. Tumors from AS01-treated mice exhibited increased infiltration of CD8+ T cells and monocytes. These findings support the assumption that AS01 can induce a trained immunity phenotype in myeloid cells, and this may have beneficial effects against malignancies.
2. Materials and Methods
2.1 Monocyte isolation
Venous blood was drawn in 10 mL EDTA tubes from healthy consenting donors, with ethical approval given by the Medical Ethical Committee Oost-Nederland (NL84281.091.23). Within 1 hour of the phlebotomy, blood was diluted in a 1:1 ratio with phosphate buffered saline (PBS, Gibco, Life Technologies, MA) before pipetting over 14 mL of Ficoll-Paque Plus (Sigma-Aldrich, St. Louis, MO, USA) in SepMateTM-50 tubes (STEMCELLTM Technologies, Vancouver, Canada). The tubes were centrifuged at 1,200 g for 10 minutes at room temperature, and the peripheral blood mononuclear cell (PBMC) fraction was poured in a separate 50 mL tube. The cells were washed twice by adding cold PBS and centrifuging at 500 g for 10 minutes at 4 °C. Peripheral monocytes were enriched from the PBMC fractions by utilizing a hyper-osmotic Percoll (Sigma-Aldrich) gradient, as described previously[31]. PBMCs and monocytes were resuspended in Roswell Park Memorial Institute (RPMI) 1640 Dutch Modified (Gibco, Life Technologies, MA) supplemented with 50 μg/mL gentamycin (Centafarm, Etten-Leur, The Netherlands), 1 mM pyruvate and 2 mM GlutaMAX (Gibco, Life Technologies, MA), which is referred to as ‘RPMI +’. To obtain the PBMC and monocyte cellularity, a Sysmex hematology analyzer (XN-450, Sysmex, Kobe, Japan) was used.
2.2 Cell viability assay of AS01-treated human monocytes
The adjuvant vial/component supplied with Shingrix (GlaxoSmithKline, Rixensart, Belgium), containing the AS01B adjuvant (200 μg/mL of AS01 in 0.5 mL, consisting of 100 μg/mL MPL and 100 μg/mL QS-21)[30] was used as provided by the manufacturer and is hereafter referred to as “AS01”. To assay the viability of cells treated with different AS01 concentrations, the CellTiter Glo 2.0 (Promega, Madison, WI, USA) Cell Viability assay was employed. Monocytes derived from overnight-rested blood were brought to a concentration of 1.5 × 10⁶ cells/mL, then 1.5 × 10⁵ cells (100 μL) were seeded per well in a white-bottom 96-well plate. Cells were incubated at 37 °C for 2 hours, then washed with 200 μL warm PBS. The monocytes were then stimulated for 48 hours at 37 °C with 100 μL RPMI + supplemented with 10% human pooled serum (HPS) containing either 4, 40, or 400 ng/mL of AS01, 100 μg/mL digitonin (Promega) as a cytotoxic positive control or RPMI +. Following the incubation period, 50 μL of cold RPMI + was added per well, together with 50 μL of Cell Titer Glo reagent. The plate was placed on a shaker at 300 rpm for 2 minutes, before resting for 10 minutes and recording the emitted luminescence.
2.3 In vitro induction of trained immunity
Cells were diluted to a concentration of 1.5 × 10⁶ cells/mL in RPMI + and 1.5 × 10⁵ cells (100 μL) were plated per well in 96-well flat-bottom plates. After 1-2 hours of incubation at 37 °C to let the monocytes adhere, wells were washed with 200 μL warm PBS. Cells were stimulated with positive controls Bacillus Calmette-Guérin vaccine (BCG) SSI 5 μg/mL (Danish strain 1331, AJVaccines, Copenhagen, Denmark), β-1,3/1,6-glucan preparation ABB i16 10 μg/mL (AB Biotek HNH, Barcelona, Spain), 40 ng/mL of AS01 or RPMI + alone in final volumes of 200 μL/well. After 24 hours, supernatants were collected and stored at -20 °C. Cells were washed with 200 μL warm PBS to remove any remaining training stimuli and further incubated with 200 μL warm RPMI + supplemented with 10% HPS for 5 days, with the medium being refreshed on day 2. After the resting period, the cells were restimulated with 10 ng/mL lipopolysaccharide (LPS) (serotype O55:B5; Sigma-Aldrich) or RPMI + at 37 °C for 24 hours. After restimulation, supernatants were collected and stored at -20 °C until cytokine measurement.
2.4 Cytokine concentration measurements
Cytokine production was quantified using commercial enzyme-linked immunosorbent assay (ELISA) kits for supernatant TNF, IL-6 and IL-1β (R & D Systems, Minneapolis, MN, USA) according to the manufacturer’s protocols. The assays’ lower limits of detection were 78 pg/mL for TNF, 93 pg/mL for IL-6, and 39 pg/mL for IL-1β.
Additionally, the inflammatory markers in AS01-trained macrophages were quantified with the Target 96 Inflammation panel from Olink Proteomics AB (Uppsala, Sweden).
2.5 ROS production of monocytes and macrophages
ROS production of monocytes was performed with a luminol-based luminescence assay. Cells were seeded at 1.5 ×10⁵ monocytes per well in a 96-well white, flat bottom plate. Cells were left to adhere at 37 °C for 1-2 hours, washed with 200 μL warm PBS and left unstimulated in RPMI + or treated with 200 μL of 40 ng/mL AS01 or 5 μg/mL BCG SSI, followed by incubation for 24 hours at 37 °C. The cells were then treated with opsonized zymosan (Sigma-Aldrich) and luminol (Sigma-Aldrich) per well, with final concentrations of 833 μg/mL and 14.75 μg/mL, respectively. Chemiluminescence was then measured every 142 seconds for one hour at 37 °C.
2.6 Mice
C57BL/6 mice were purchased from Jackson Laboratory (stock #000664). All mice were maintained in the specific pathogen-free (SPF) animal facility of the Biomedical Research Foundation of the Academy of Athens (BRFAA); the mice were kept in a 12 h light-dark cycle at a room temperature of 20-24 °C and a humidity range of 45-65%. Experimental and control animals were co-housed. The protocols used for animal experimentation were in accordance with institutional guidelines and approved by the Welfare Institutional Committee of Protocol Evaluation together with the Directorate of Agriculture and Veterinary Policy, Region of Attika, Greece (protocol 285279/04-04-2022). In all experiments, sex-matched mice aged between 8 and 12 weeks were used, and at the experiment endpoint, mice were euthanized by cervical dislocation. Male mice were used in the melanoma and bladder cancer models, while female mice were used in the lung carcinoma.
2.7 Tumor cell lines
The B16-F10 mouse melanoma, Lewis Lung Carcinoma (LLC), and MB49 mouse bladder carcinoma cell lines were kindly provided by Dr. Eliopoulos (School of Medicine, University of Athens, Greece). All cell lines were negative for mycoplasma, as confirmed by PCR. B16-F10 and LLC cells were maintained in RPMI Medium (Gibco) supplemented with 10% fetal bovine serum (FBS, STEMCELLTM Technologies), 0.1% β-mercaptoethanol (Gibco) and 1% of a mix of Penicillin/Streptomycin (P/S, Gibco). MB49 cells were maintained in DMEM Medium (Gibco) supplemented with 10% FBS, 0.1% β-mercaptoethanol and 1% of a mix of P/S.
2.8 Solid tumor induction
Mice were implanted subcutaneously (s.c.) on the back with 3 × 10⁵ B16-F10 melanoma, or 3 × 10⁵ LLC cells, or 75 × 104 MB49 bladder cancer cells. Tumor growth was monitored every day from Day 7 to Day 16 by measurement of two perpendicular diameters (d) of the tumor by caliper; tumor volume was calculated using the equation (d1 * d2 * d2)/2. Mice that manifested tumor ulceration were excluded from the experimental processes. The experimental endpoint (sacrifice day) was determined for each model based on its growth rate. B16-F10, LLC and MB49 tumors were excised and analyzed on days 16, 12 and 13 after inoculation, respectively.
2.9 AS01 administration
C57BL/6 mice were anesthetized and administered intramuscular injections of AS01 at doses of 10 µg or 20 μg, corresponding to 1/10 or 1/5 of the AS01B dose from the Shingrix vaccine. For the 1/5 dose, mice received a single intramuscular injection (50 μL). For the 1/10 dose, AS01 was diluted 1:1 with PBS (50 μL AS01 + 50 μL PBS) and administered as two bilateral intramuscular injections (50 μL per leg). Control mice received PBS. Injections were performed at tumor induction (day 0), and a subset received a second injection on day 4.
2.10 Cell isolation from mouse tumors
For tumor cell analysis, tumor tissues were excised and cut into the smallest possible fragments by using an ophthalmic scissor. The minced tissues were incubated for 45 min at 37 °C in RPMI medium containing DNase I (0.25 mg/mL, Sigma) and collagenase D (1 mg/mL, Roche) before passing through a 40-μm cell strainer (BD falcon).
2.11 Flow cytometry analysis
For staining of extracellular markers, cell suspensions were incubated with antibodies for 20 min at 4 °C. The following antibodies were used (all antibodies were purchased from BioLegend): CD45 (clone 30-F11), CD3 (clone GB11), CD4 (clone RM4-4), CD8 (clone 53-6.7), CD19 (clone 6D5), B220 (clone RA3-6B2), I-Ab (clone AF6-120.1), CD11c (clone N418), CD11b (clone M1/70), Ly6C (clone HK1.4), Ly6G (clone 1A8), F4/80 (clone BM8), and PD-L1 (10F.9G2). For Foxp3 (BioLegend, clone 150D), intracellular staining, cells were stained for the extracellular markers and then fixed and stained using the Foxp3/Transcription Factor Staining Buffer Set (eBioscience) according to the manufacturer instructions. Data acquisition was performed on FACS Celesta (BD Biosciences, San Jose, California, USA). Flow cytometry data were analyzed with FlowJo (v10 and v10.7.2) software (Tree Star).
2.12 Statistical analysis
Graphical representations of the data and statistical analyses were performed with GraphPad version 10.2.3 (GraphPad Software, La Jolla, CA, USA). Each statistical test performed is specified in its respective figure legend. Data are presented as the mean ± one standard deviation (SD). A p value of < 0.05 was considered statistically significant, with *p ≤ 0.05, **p ≤ 0.01, ***p ≤ 0.001, and ****p ≤ 0.0001.
For the Olink data, NPX values between AS01 and RPMI + trained samples were subtracted to obtain fold-changes. Markers which were non-detectable in more than 25% of the samples were removed as quality control, after which 57 proteins remained. Computational analyses were performed in R 4.5.2. Protein levels were compared between AS01 and RPMI + conditions with paired t tests. Multiple testing correction was performed with FDR.
3. Results
3.1 AS01 induces trained immunity in human monocytes
To determine the optimal concentrations of the AS01 in the in vitro experiments, human peripheral monocytes were exposed to three different concentrations of AS01 (4, 40, and 400 ng/mL) after which viability was assessed. Cells incubated with 400 ng/mL AS01 showed a 20% decrease in viability, whereas the two lower concentrations were well tolerated without decrease in cell viability (Figure 1a). We chose the intermediary 40 ng/mL as working AS01 concentration.
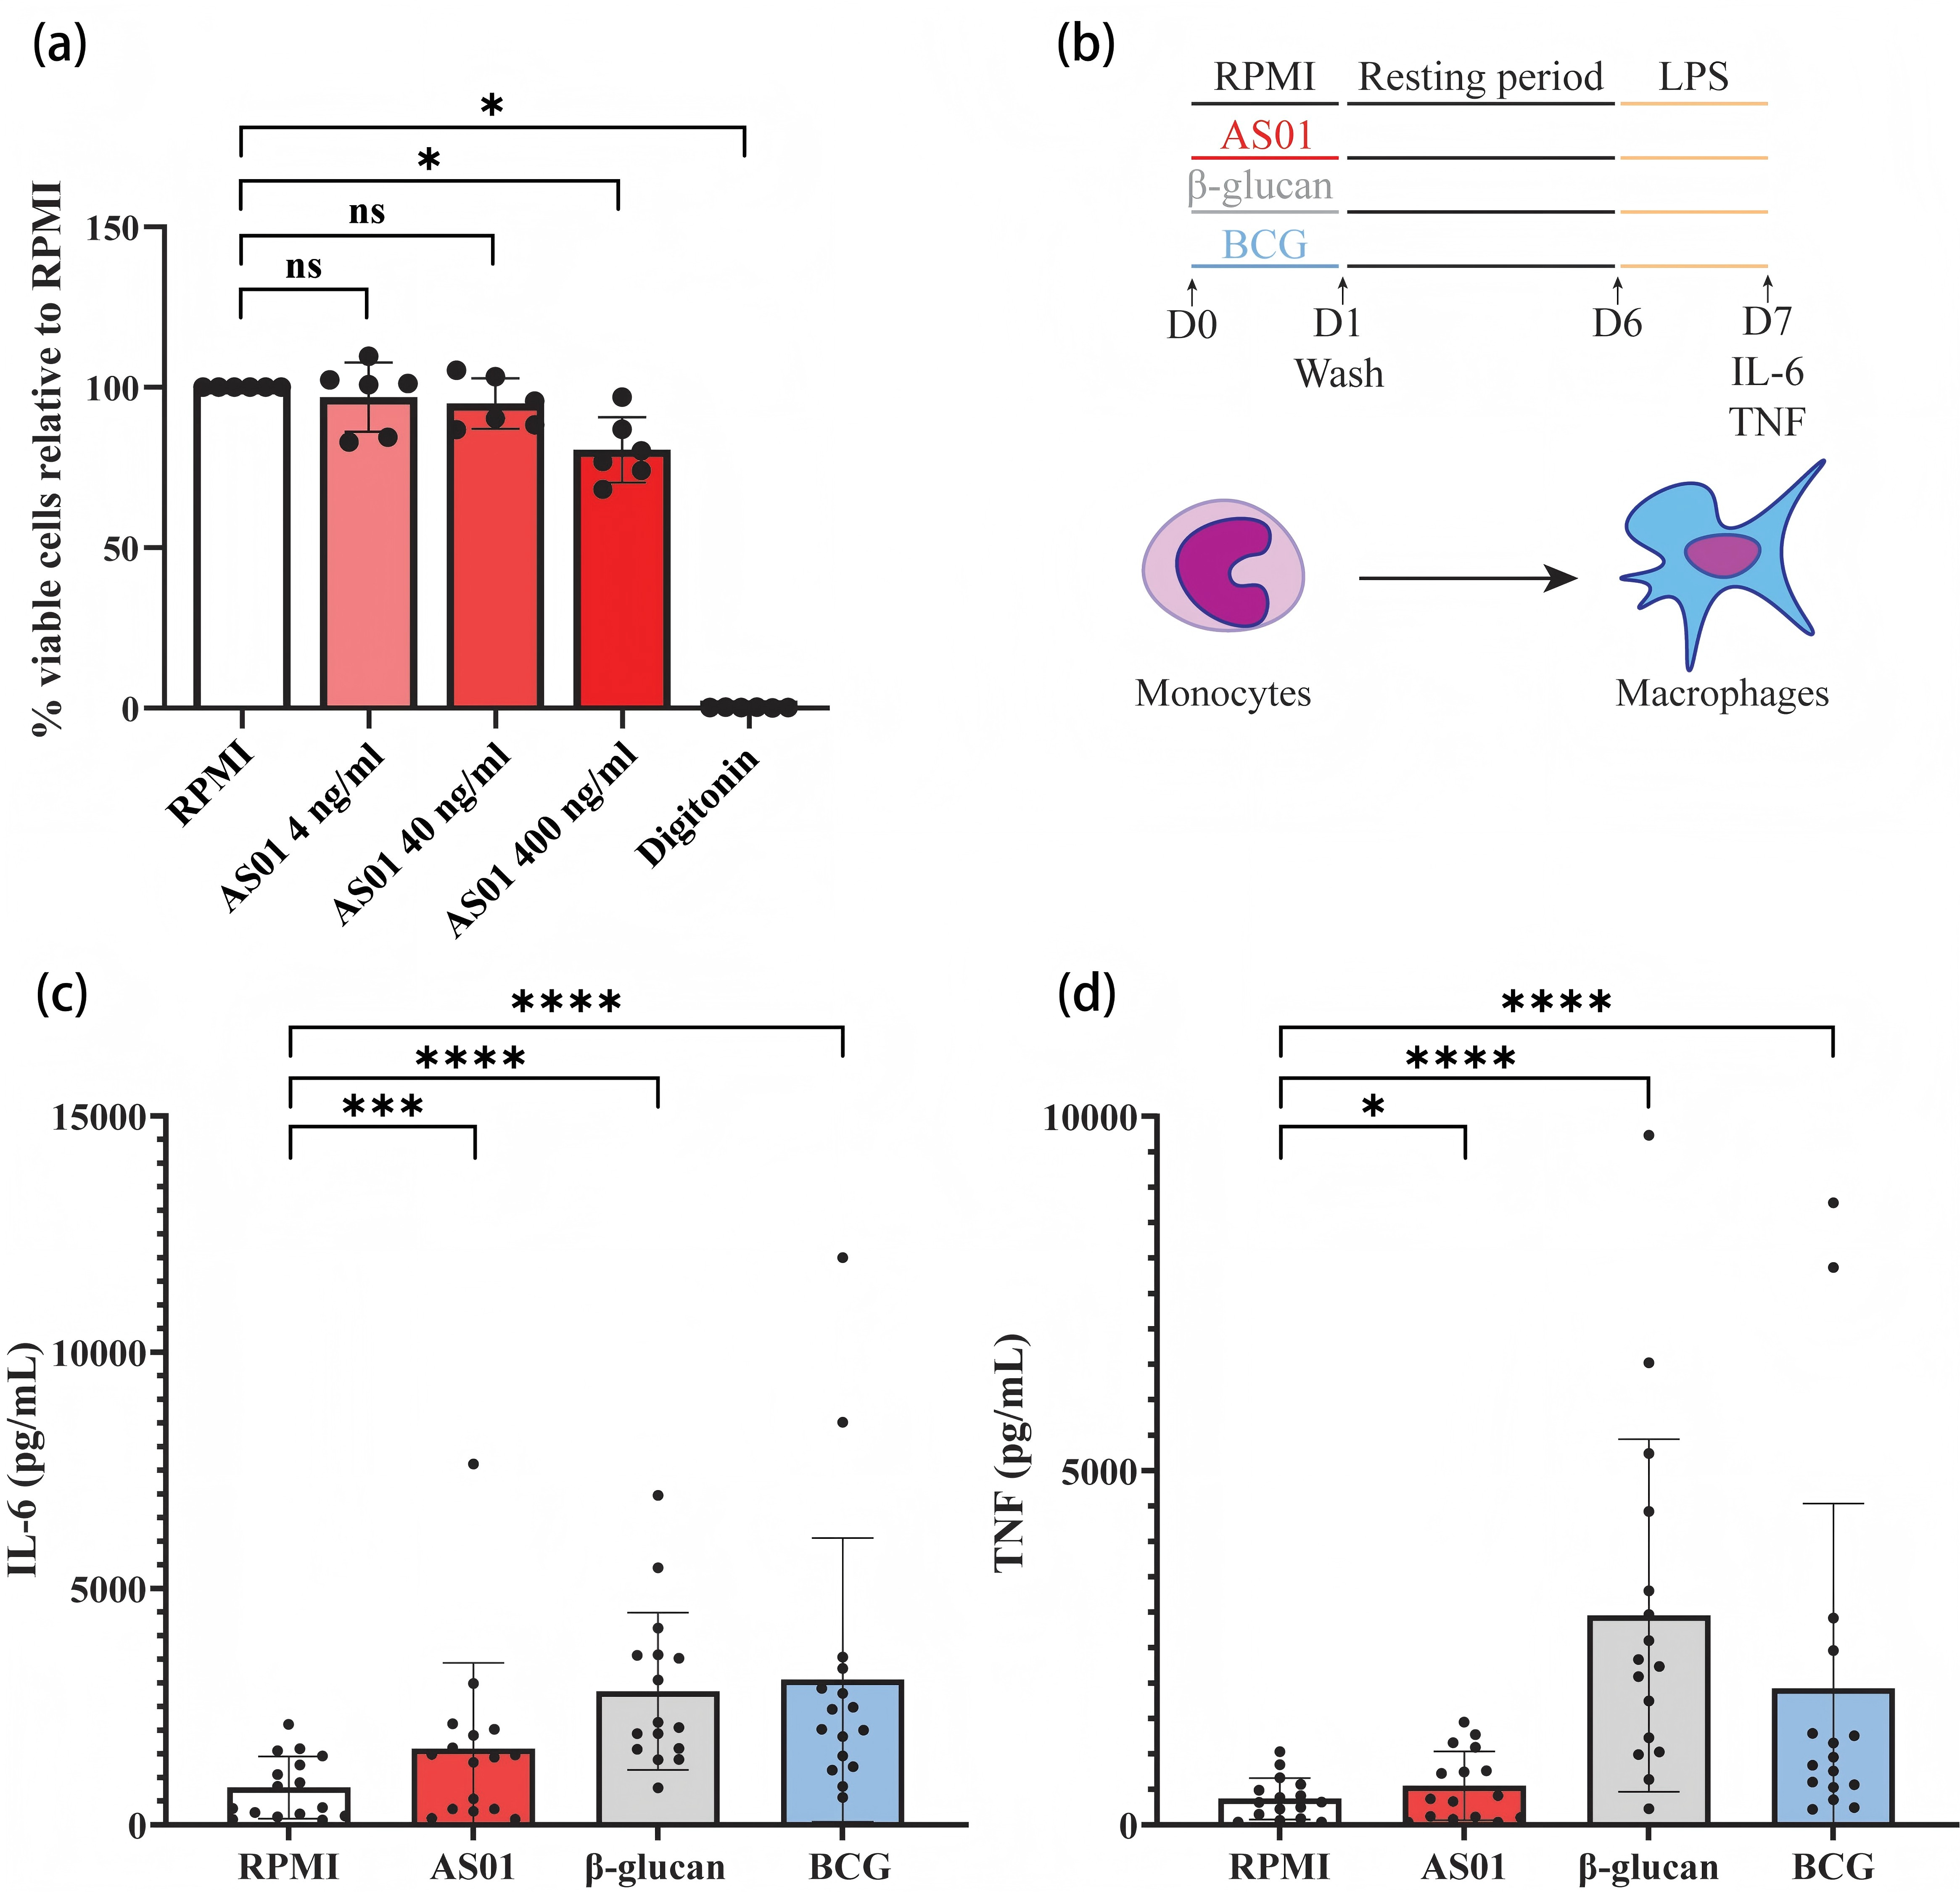
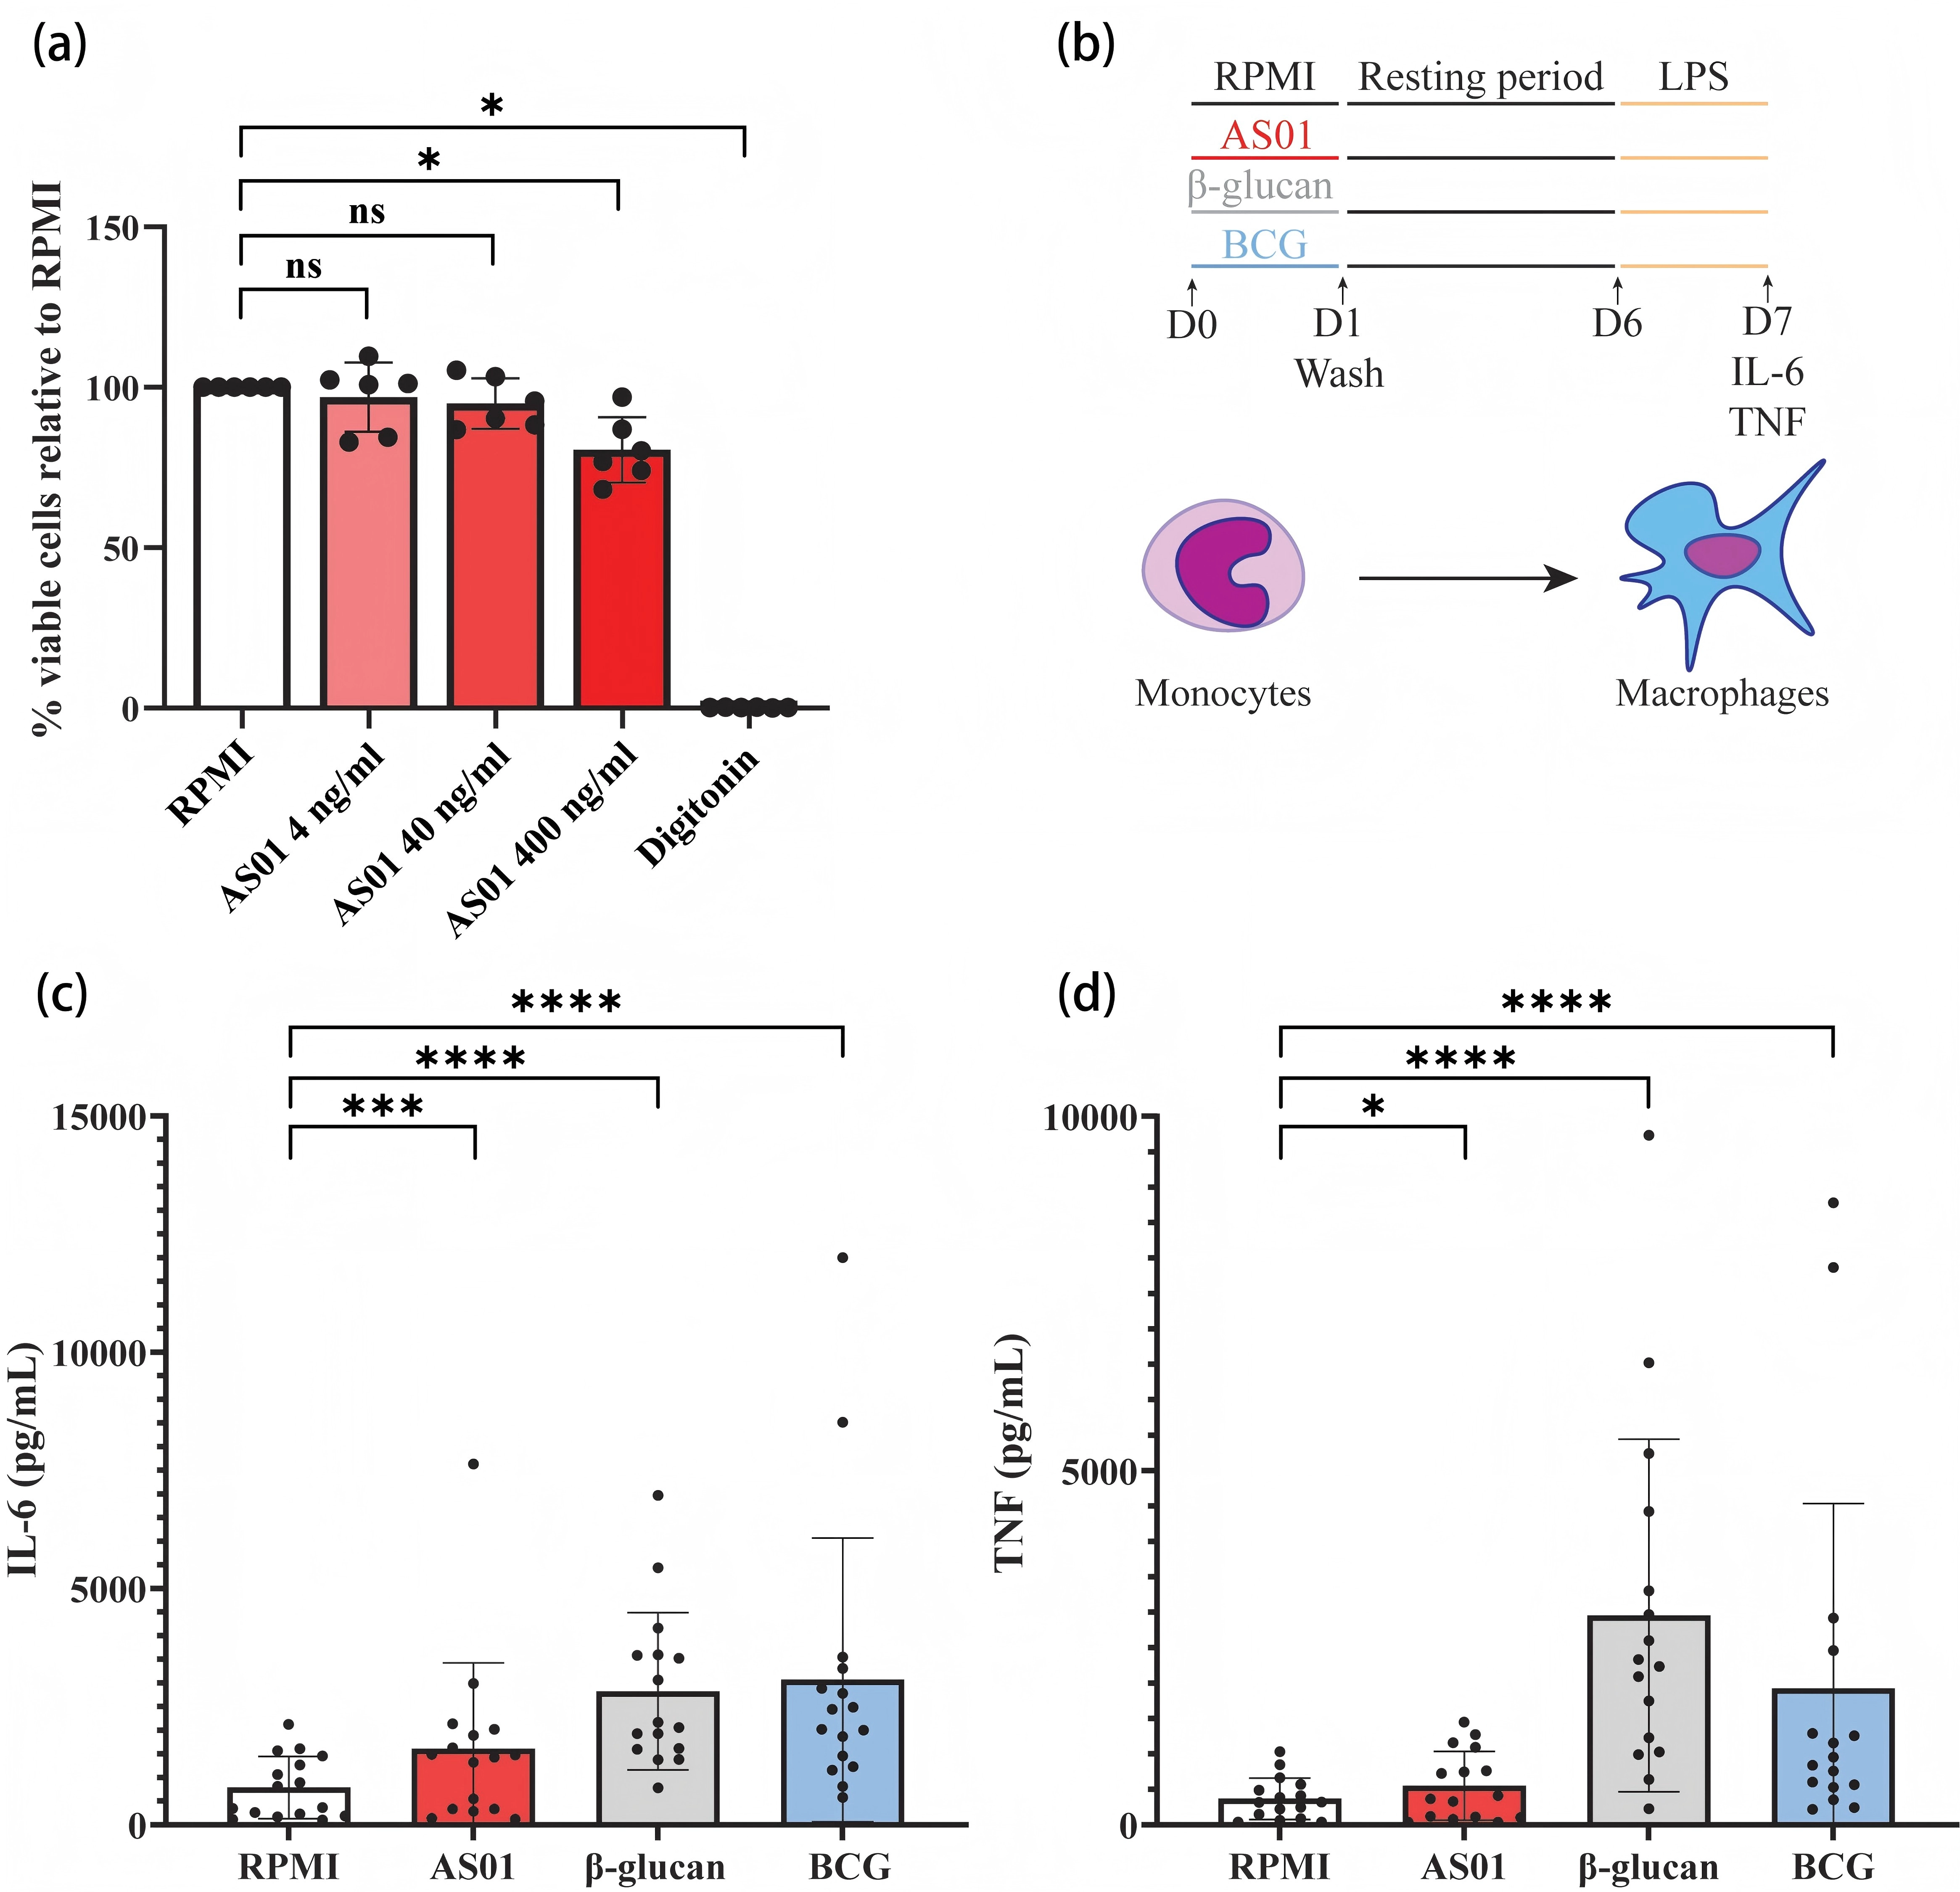
Figure 1. AS01 induces trained immunity in human monocytes. (a) Normalized cell viability of monocytes incubated with different concentrations of AS01 or left unstimulated (RPMI +) for 48 hours. Monocytes treated with digitonin served as a cytotoxic positive control. n = 6, pooled from two independent experiments; (b) Schematic of the in vitro trained immunity protocol employed. Monocytes were stimulated for 24 hours with either 10 μg/mL β-glucan, 5 μg/mL BCG, or 40 ng/mL AS01 or left unstimulated in RPMI +, after which the cells were washed with PBS and rested for 5 days. The macrophages were then restimulated with 10 ng/mL LPS for 24 hours and IL-6 (c) and TNF (d) concentrations were determined in supernatants with ELISA. n = 16, pooled from five independent experiments. Data shown as mean ± SD, *p ≤ 0.05, **p ≤ 0.01, ***p ≤ 0.001, and ****p ≤ 0.0001 by Wilcoxon matched-pair signed-rank tests. RPMI: Roswell Park Memorial Institute; BCG: Bacillus Calmette-Guérin vaccine; PBS: phosphate buffered saline; ELISA: enzyme-linked immunosorbent assay; LPS: lipopolysaccharide; IL-6: interleukin-6; TNF: tumor necrosis factor.
To investigate the potential of AS01 to trigger innate immune memory, an established protocol of in vitro trained immunity was employed[31]. Monocytes were stimulated with AS01 for 24 h, after which cells were washed and allowed to rest in culture medium for 5 days. On day 6, the cells were restimulated with LPS for an additional 24 h (Figure 1b). The well-described trained-immunity inducers BCG and β-glucan triggered a clear increase in the production of both IL-6 and TNF on day 7 after LPS rechallenge (Figure 1c,d). Similarly, AS01-trained macrophages exhibited a two-fold increase in IL-6 production compared to the RPMI-exposed cells that were restimulated with LPS (Figure 1c). AS01 exposure also upregulated LPS-induced TNF production capacity, although the extent of the increase was lower than for IL-6 and lower than the effects induced by BCG or b-glucan (Figure 1d). IL-1β was below the limit of detection in all conditions, consistent with the fact that macrophages require a secondary stimulus for IL-1β release, due to the absence of active caspase-1[32].
To obtain a more comprehensive overview of the cytokine production upregulation in AS01-trained cells, we performed a proximity extension assay encompassing 96 inflammatory proteins in supernatants of stimulated cells from a subset of donors. While the variation in protein expression was mainly explained by inter-donor differences, AS01 samples showed a consistent shift along the same principal component axis (Figure S1A). While we did not have sufficient power to identify statistically significant differences after multiple-test correction, AS01-trained macrophages exhibited a general trend toward increased expression of inflammatory proteins, including CXCL1, CXCL9, and oncostatin M (OSM), consistent with enhanced responsiveness to restimulation (Figure S1B). TNF and IL-6 production after LPS stimulation was upregulated by AS01-induced training, consistent with our ELISA data (Figure S1C).
3.2 AS01 does not trigger an acute pro-inflammatory phenotype in monocytes
Considering that trained immunity reflects long-term functional reprogramming rather than continuous activation or priming[33], we next assessed whether AS01 can also induce an acute inflammatory phenotype during the primary stimulation phase (Figure 2a). AS01-treated monocytes did not produce detectable amounts of IL-6, TNF or IL-1β, while β-glucan led to consistent inflammatory cytokine induction (Figure 2b,c,d). Consistent with our cytokine data, AS01 stimulation did not increase ROS production in monocytes (Figure 2e). Collectively, these findings suggest that AS01 can induce trained immunity in human macrophages, characterized by upregulated cytokine production upon LPS restimulation, but without triggering acute inflammation.
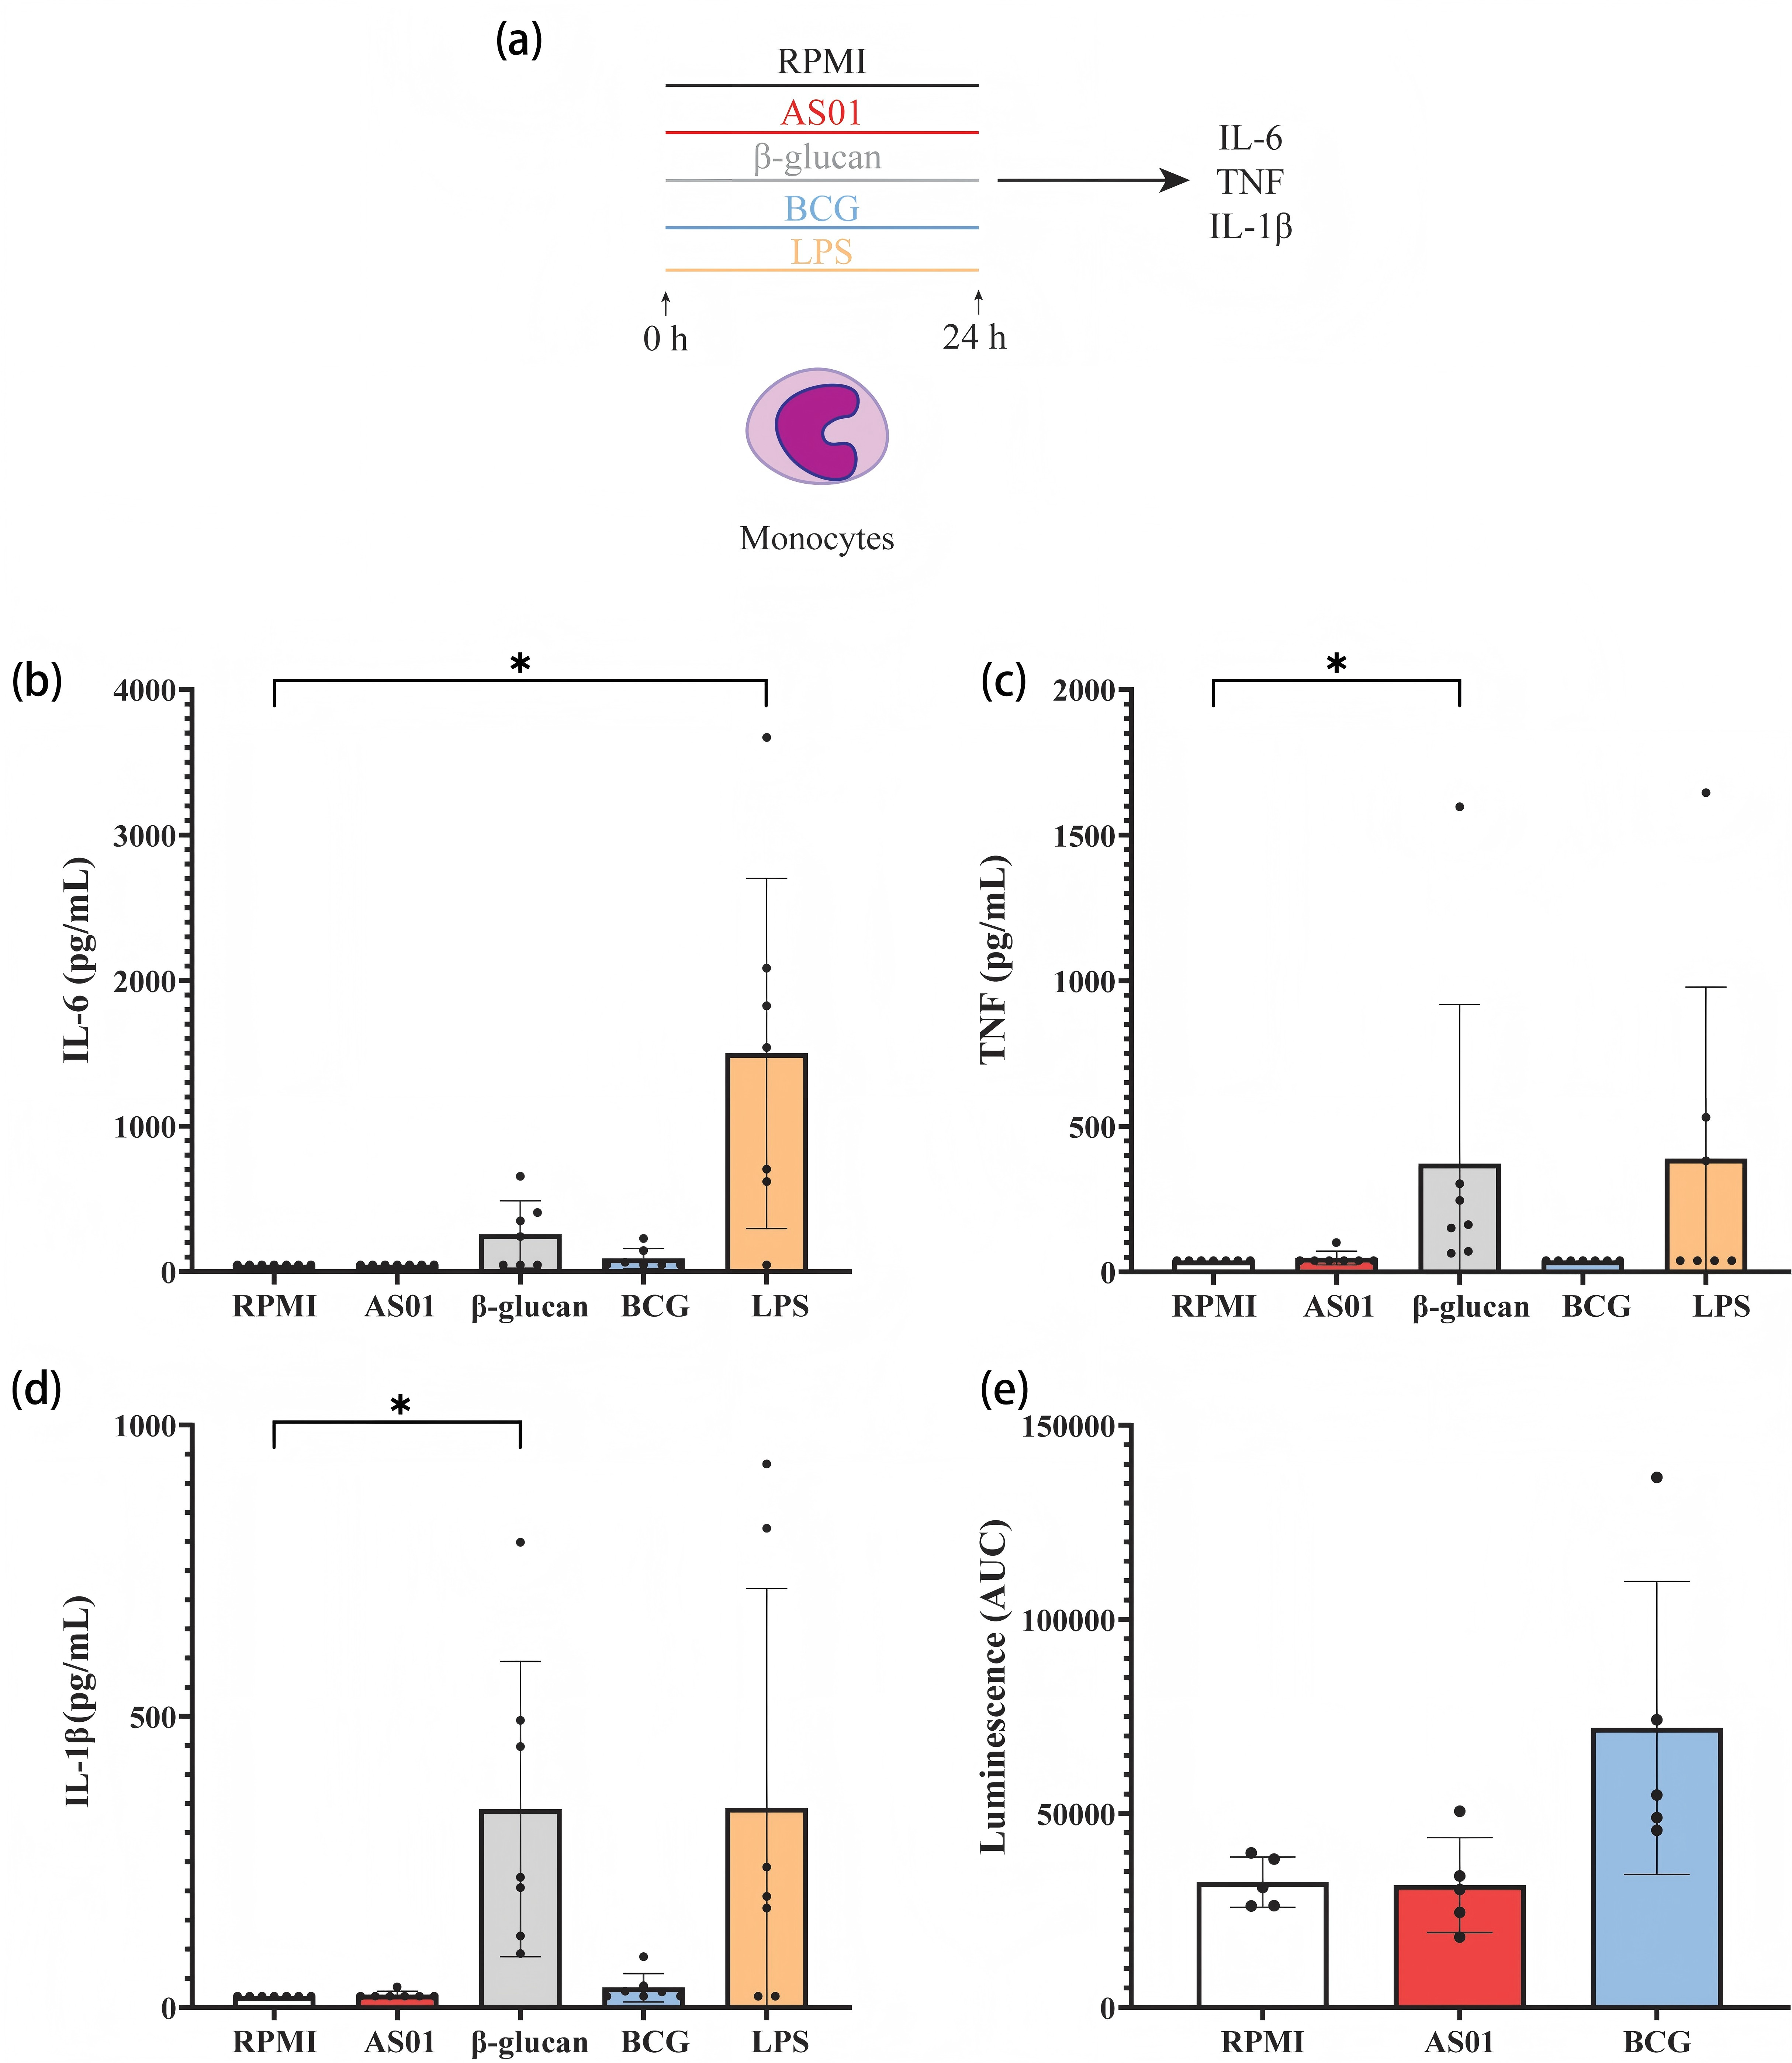
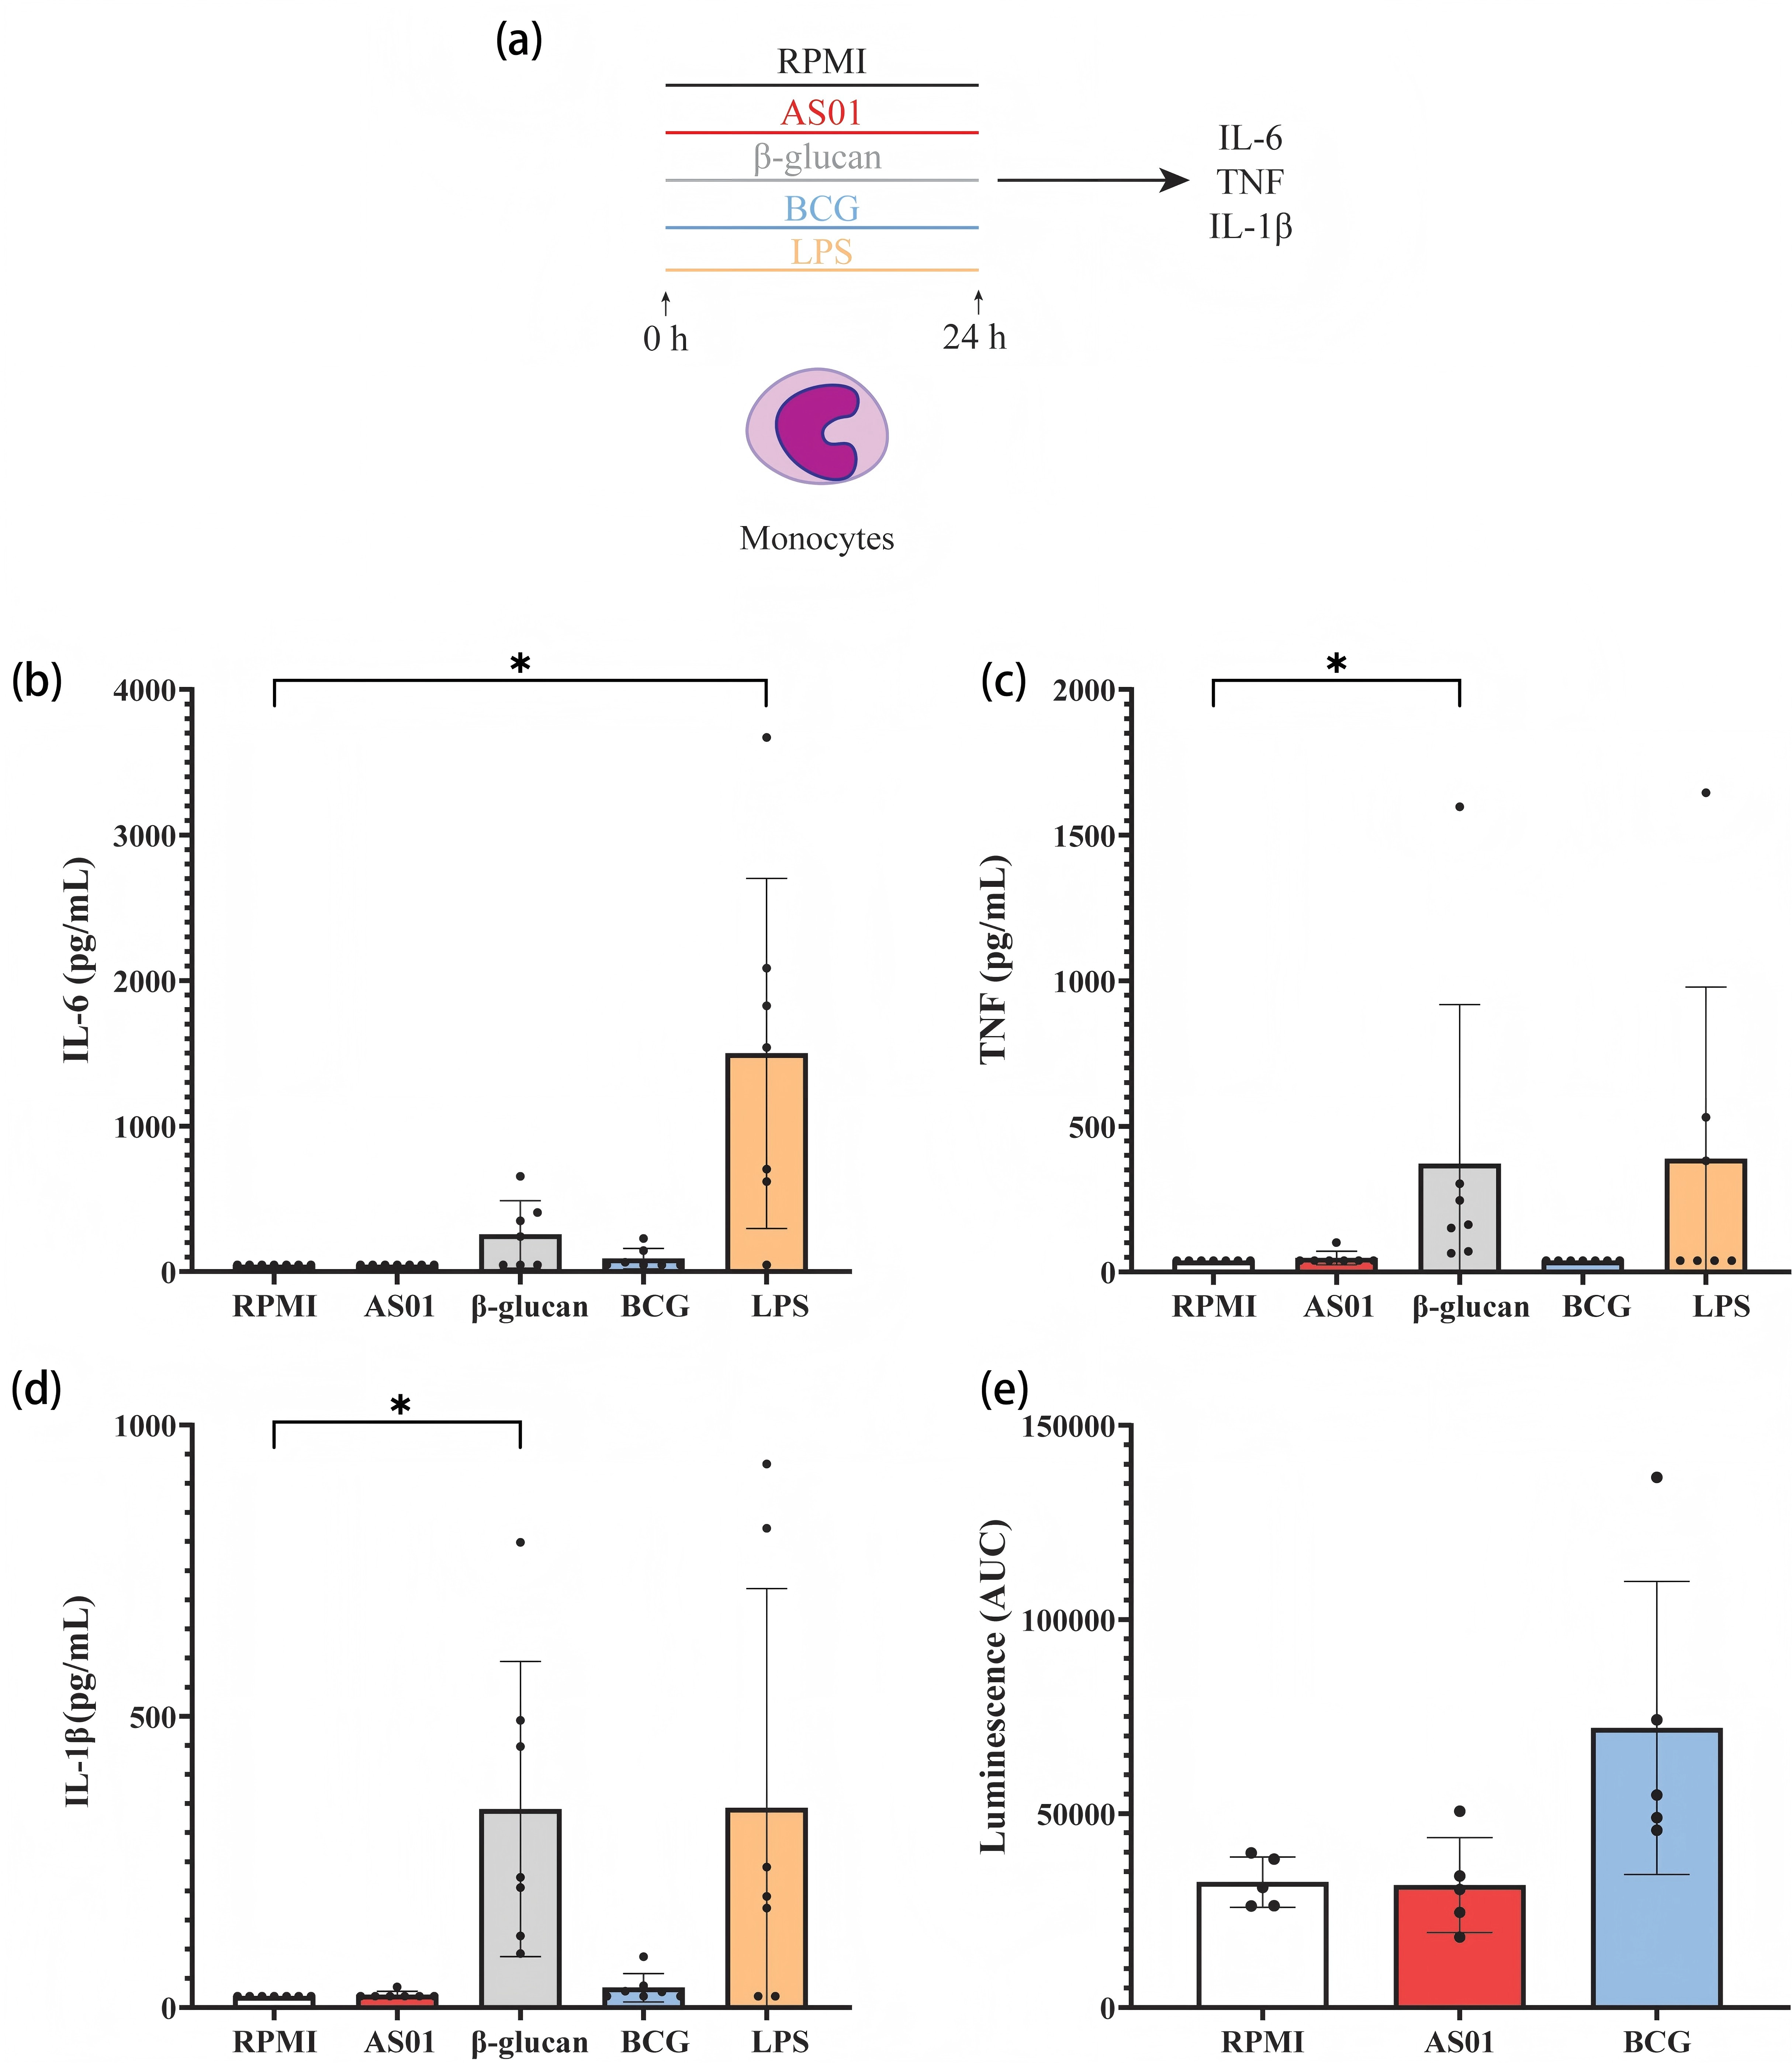
Figure 2. AS01 does not induce a pro-inflammatory acute phenotype in monocytes. (a) Schematic of the experimental design. Monocytes were stimulated for 24 hours with 10 μg/mL β-glucan, 5 μg/mL BCG, 10 ng/mL LPS, 40 ng/mL AS01 or left unstimulated in RPMI +; Supernatant concentrations of IL-6 (b), TNF (c) and IL-1β (d) were determined by ELISA; n = 7, data from two independent experiments; (e) ROS production of monocytes after 24-hour incubation with the indicated stimuli, followed by zymosan stimulation. n = 5, data from two independent experiments. Data are shown as mean ± SD, p values obtained by Wilcoxon matched-pair signed-rank tests, *p ≤ 0.05. Non-significant comparisons are omitted for clarity. AUC: area under the curve; BCG: Bacillus Calmette-Guérin vaccine; RPMI: Roswell Park Memorial Institute; ELISA: enzyme-linked immunosorbent assay; ROS: reactive oxygen species; LPS: lipopolysaccharide; IL-6: interleukin-6; TNF: tumor necrosis factor.
3.3 AS01 suppresses tumor growth in vivo
Given the tumor suppressor effects of many inducers of trained immunity[11,21-23], we next evaluated whether AS01 exerts antitumor activity in vivo. To test this, mice inoculated with B16-F10 melanoma cells were treated with either control PBS, or one or two intramuscular injections of 10 μg or 20 μg of AS01, corresponding to 1/10 or 1/5 of the AS01B dose from the Shingrix vaccine (Figure 3a). AS01 significantly reduced the tumor burden in AS01-injected mice compared to controls, with the degree of tumor suppression dependent on both the dose and the treatment frequency (Figure 3b). Having identified the optimal AS01 treatment regimen, we next investigated whether AS01’s effects extend to other cancer types. When administering AS01 to mice injected with MB49 bladder cancer cells (Figure 3c), AS01 again prevented tumor growth (Figure 3d,e). In Lewis lung carcinoma (LLC) bearing mice, however, AS01 did not result in a change of tumor growth or weight (Figure S2).
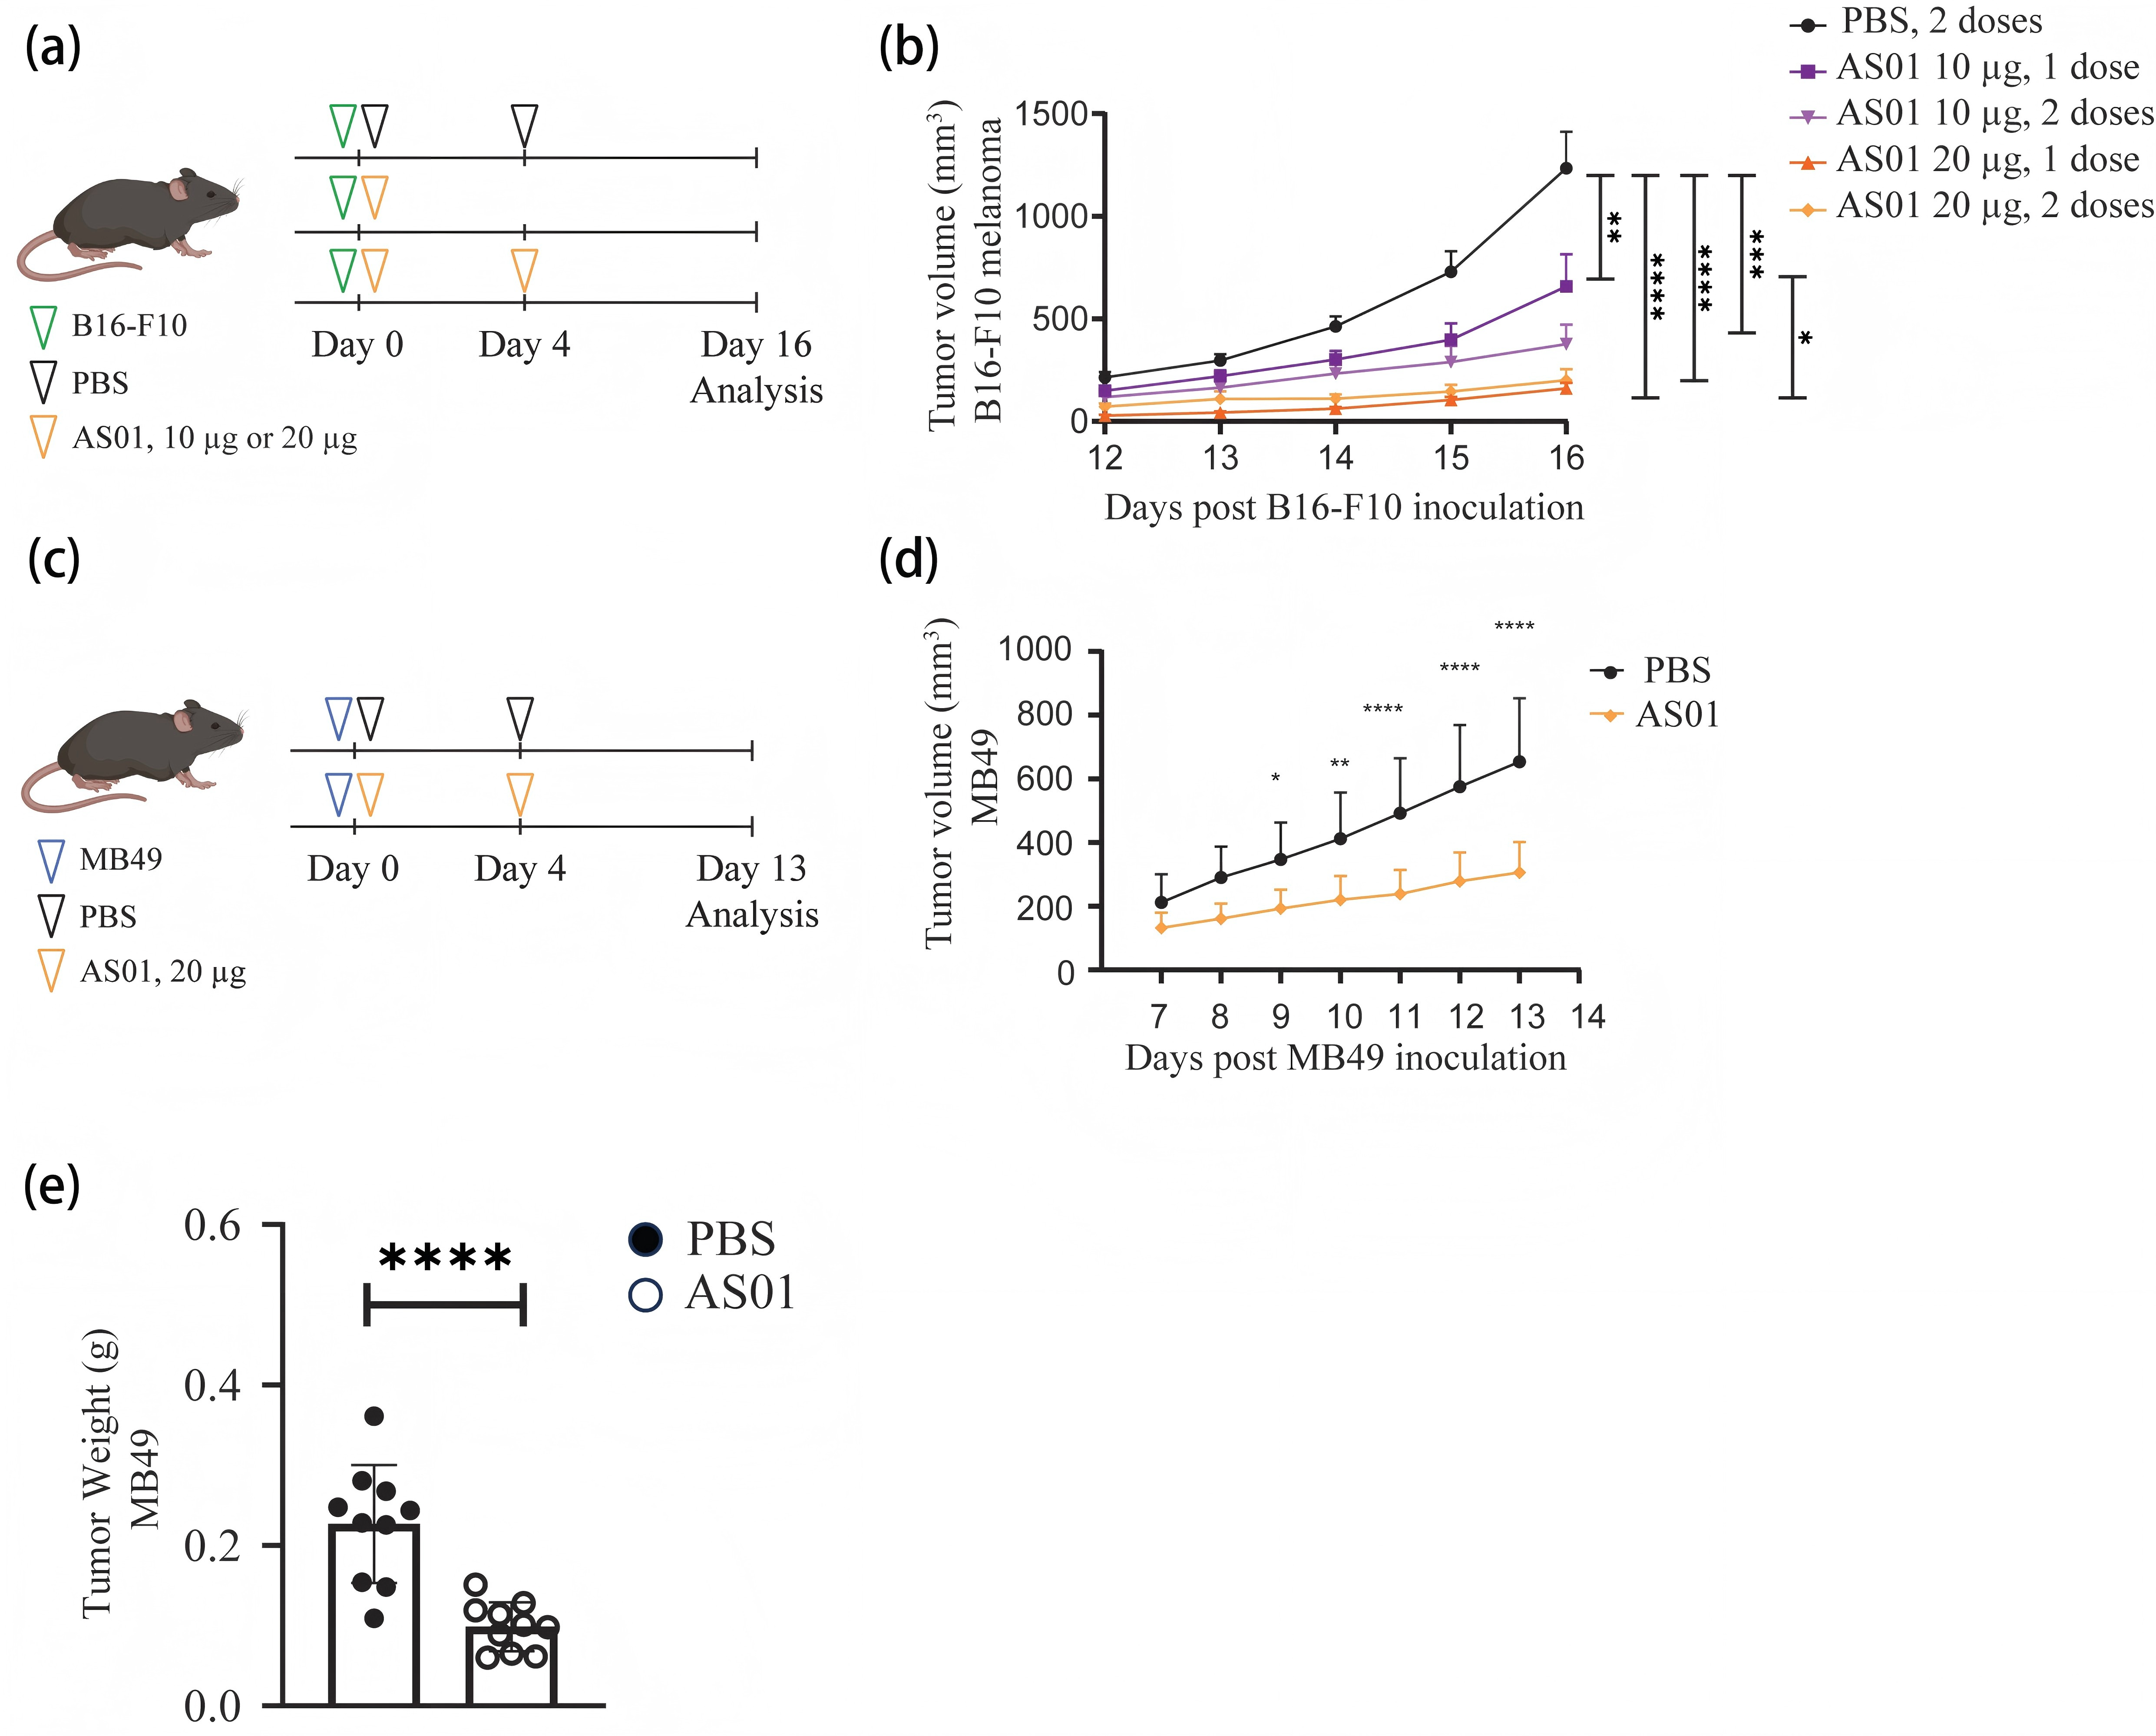
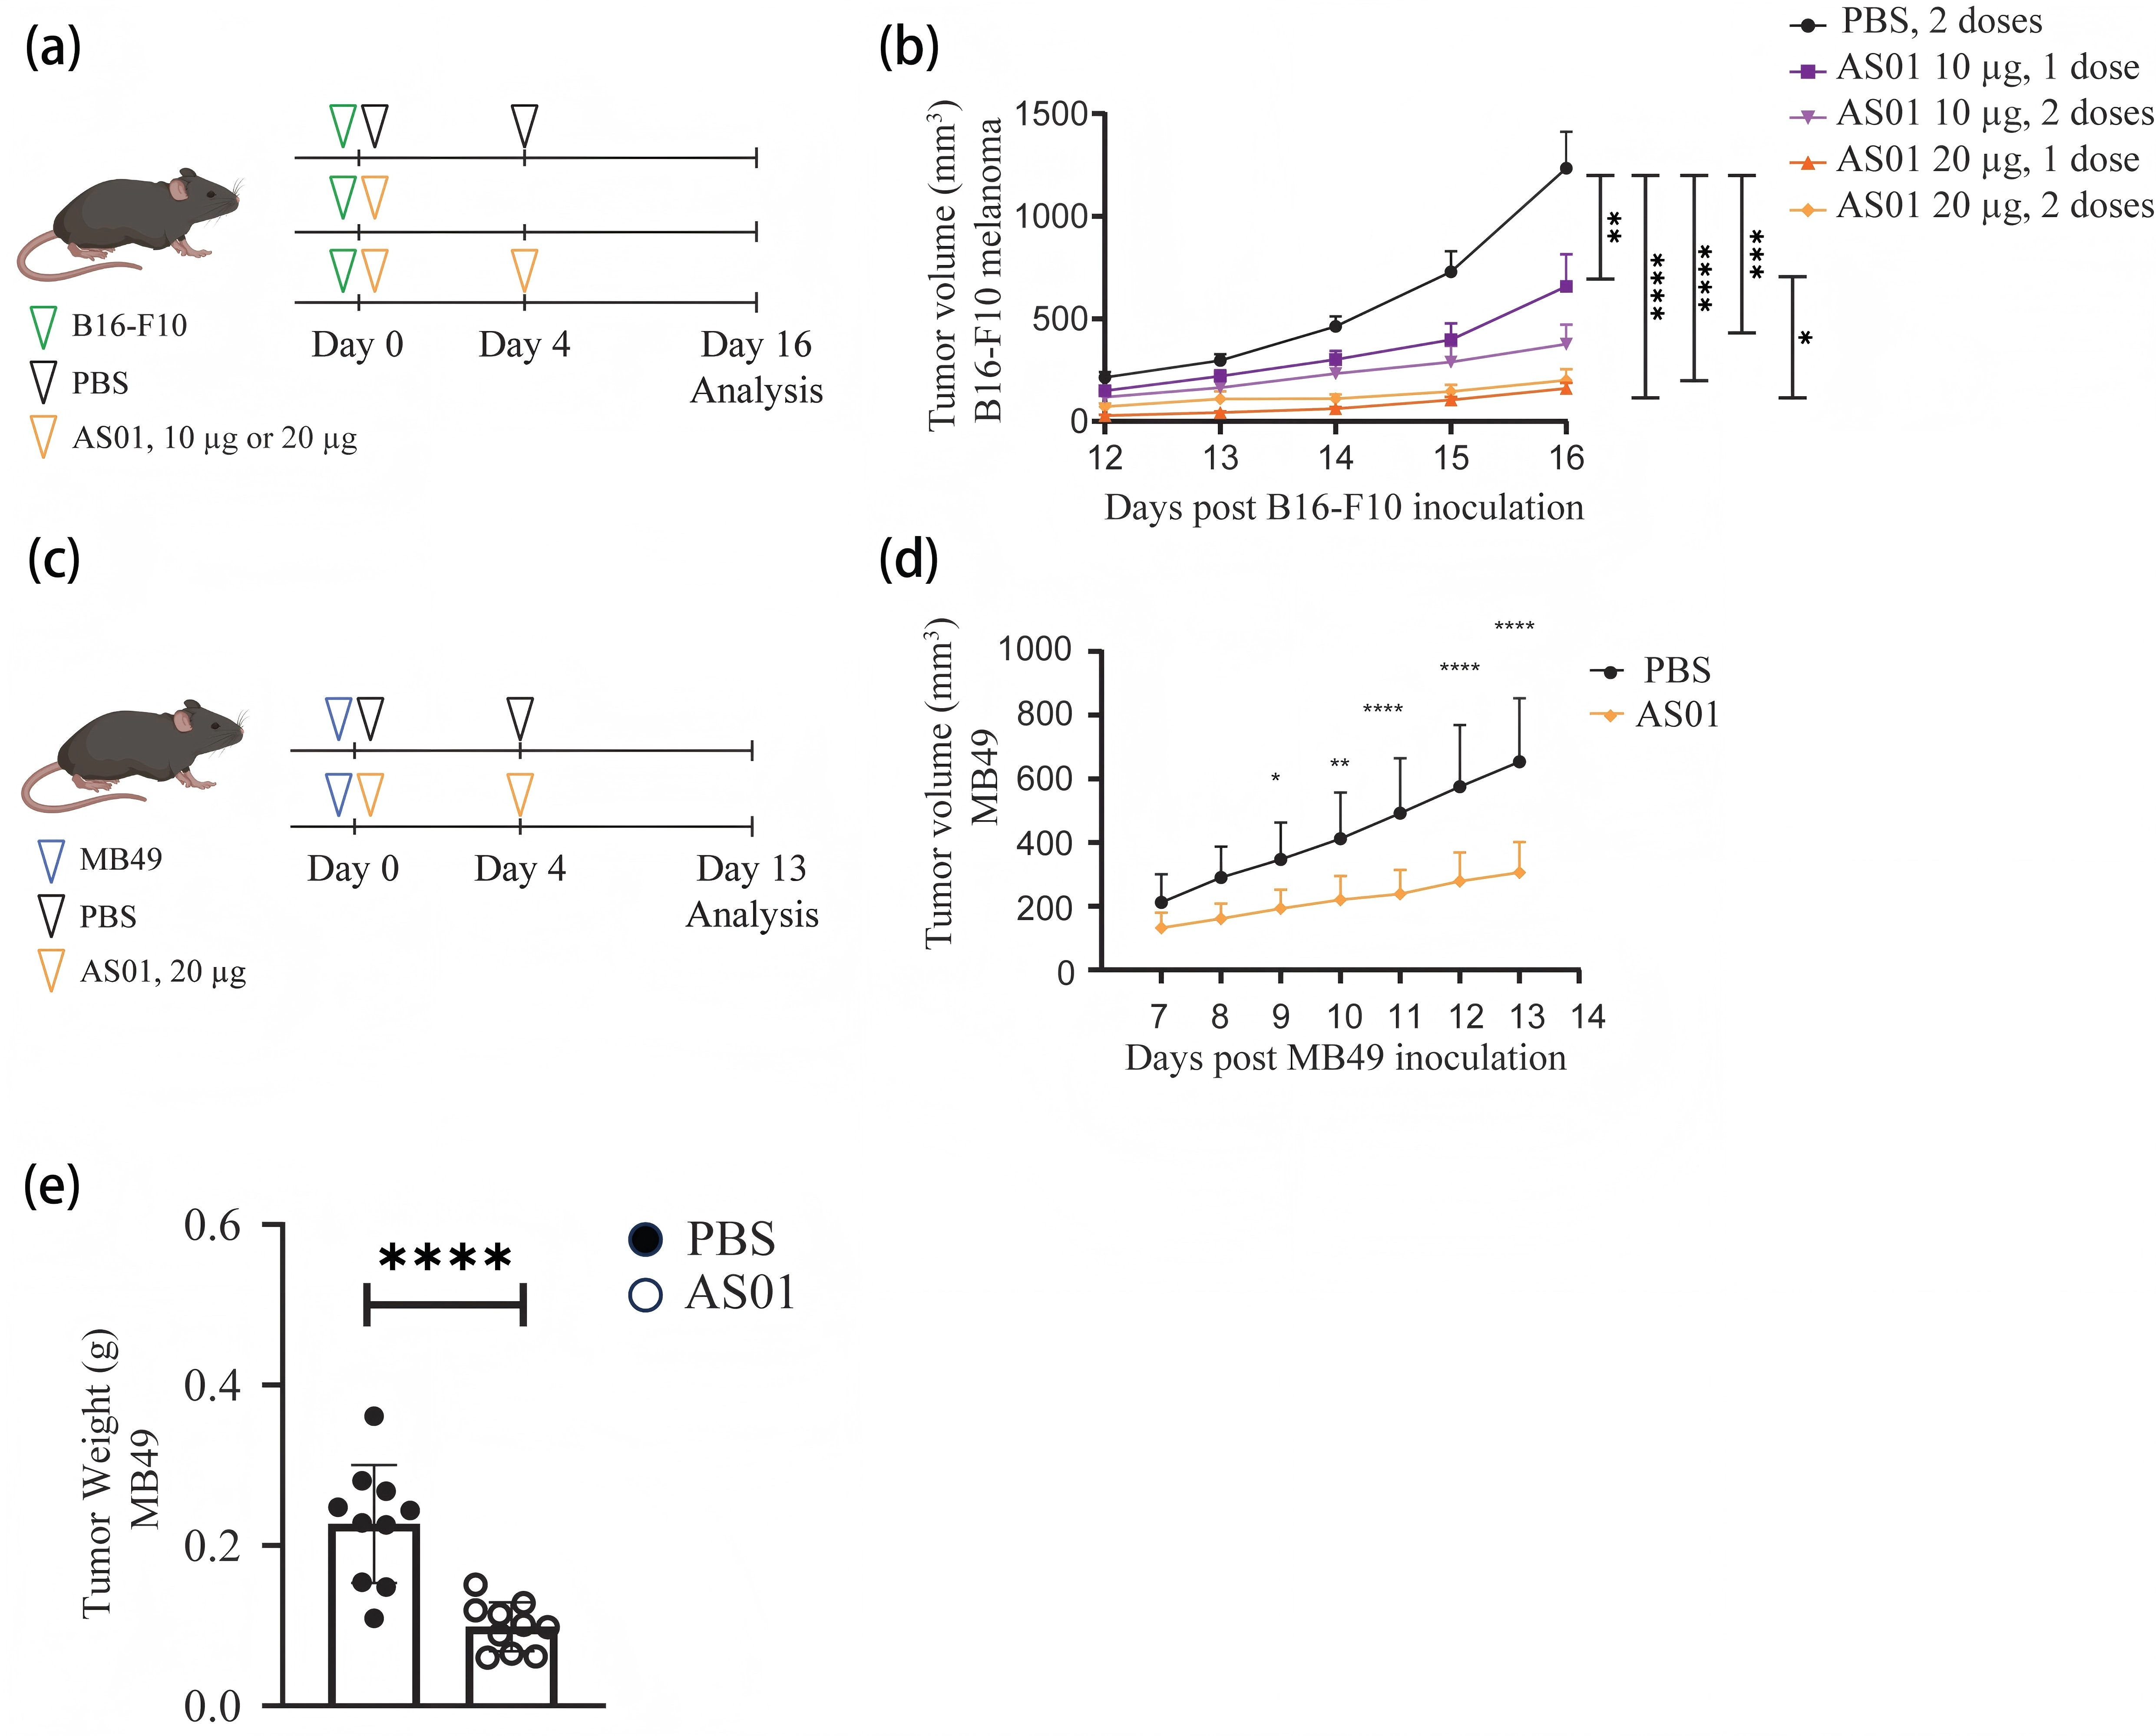
Figure 3. AS01 suppresses tumor growth in preclinical melanoma and bladder cancer models. C57BL/6 mice were injected with B16-F10 or MB49 cells and then treated with intramuscular PBS or AS01 at the specified days relative to tumor injection. (a) Experimental design for the B16-F10 melanoma model; (b) Mice received either two doses of PBS or one or two doses of 10 or 20 μg AS01 at days 0 and 4 after B16-F10 injection. Tumor volumes were monitored for 16 days after tumor inoculation (n = 7 mice for the PBS group, n = 9 for 10 μg AS01 single dose, n = 9 for 10 μg AS01 double dose, n = 10 for 20 μg AS01 single dose, n = 10 for 20 μg AS01 double dose); (c) Experimental design for the MB49 bladder cancer model. Only the double injection (day 0 + day 4) of the higher AS01 concentration was employed in the bladder cancer model; (d) Mice received either two doses of PBS or 20 μg AS01 at days 0 and 4 after MB49 injection; Tumor volumes were monitored for 13 days after tumor inoculation (n = 10 mice for the PBS group, n = 9 for the AS01 group) (e) Excised MB49 tumor weights at day 13 after tumor inoculation. Data are shown as mean ± SD, p values obtained by one-way ANOVA on day 16 tumor volumes (b) and two-way ANOVA (d) with Tukey’s multiple comparisons and unpaired t test (E), *p ≤ 0.05, **p ≤ 0.01, ***p ≤ 0.001, and ****p ≤ 0.0001. PBS: phosphate buffered saline.
3.4 AS01 is associated with immune changes in the TME
As multiple immune cell types in the TME are known to influence tumor progression[5], we next investigated whether AS01’s anticancer effect was associated with changes in tumoral leukocyte populations. Flow cytometry immunophenotyping of B16-F10 tumors revealed a persistent increase in the proportion of CD45+ cells and classical DCs (cDCs; CD11c+ MHCII+) in melanoma of mice that received two 20 μg AS01 doses (Figure 4a,b, gating strategy in Figure S3A,S3B). Neutrophils (CD11c- CD11b+ Ly6C+ Ly6G+) and monocytes (CD11c- CD11b+ Ly6C+ Ly6G- F4/80-) were also significantly increased in the melanoma of the AS01-treated group (Figure 4b). Intratumoral Ly6C- macrophages (CD11c- CD11b+ Ly6C- Ly6G- F4/80+) showed a significant reduction in relative frequency compared to the PBS control, whereas the proportion of inflammatory Ly6C+ macrophages (CD11c- CD11b+ Ly6C+ Ly6G- F4/80+) was not statistically affected by AS01 treatment (Figure 4b).
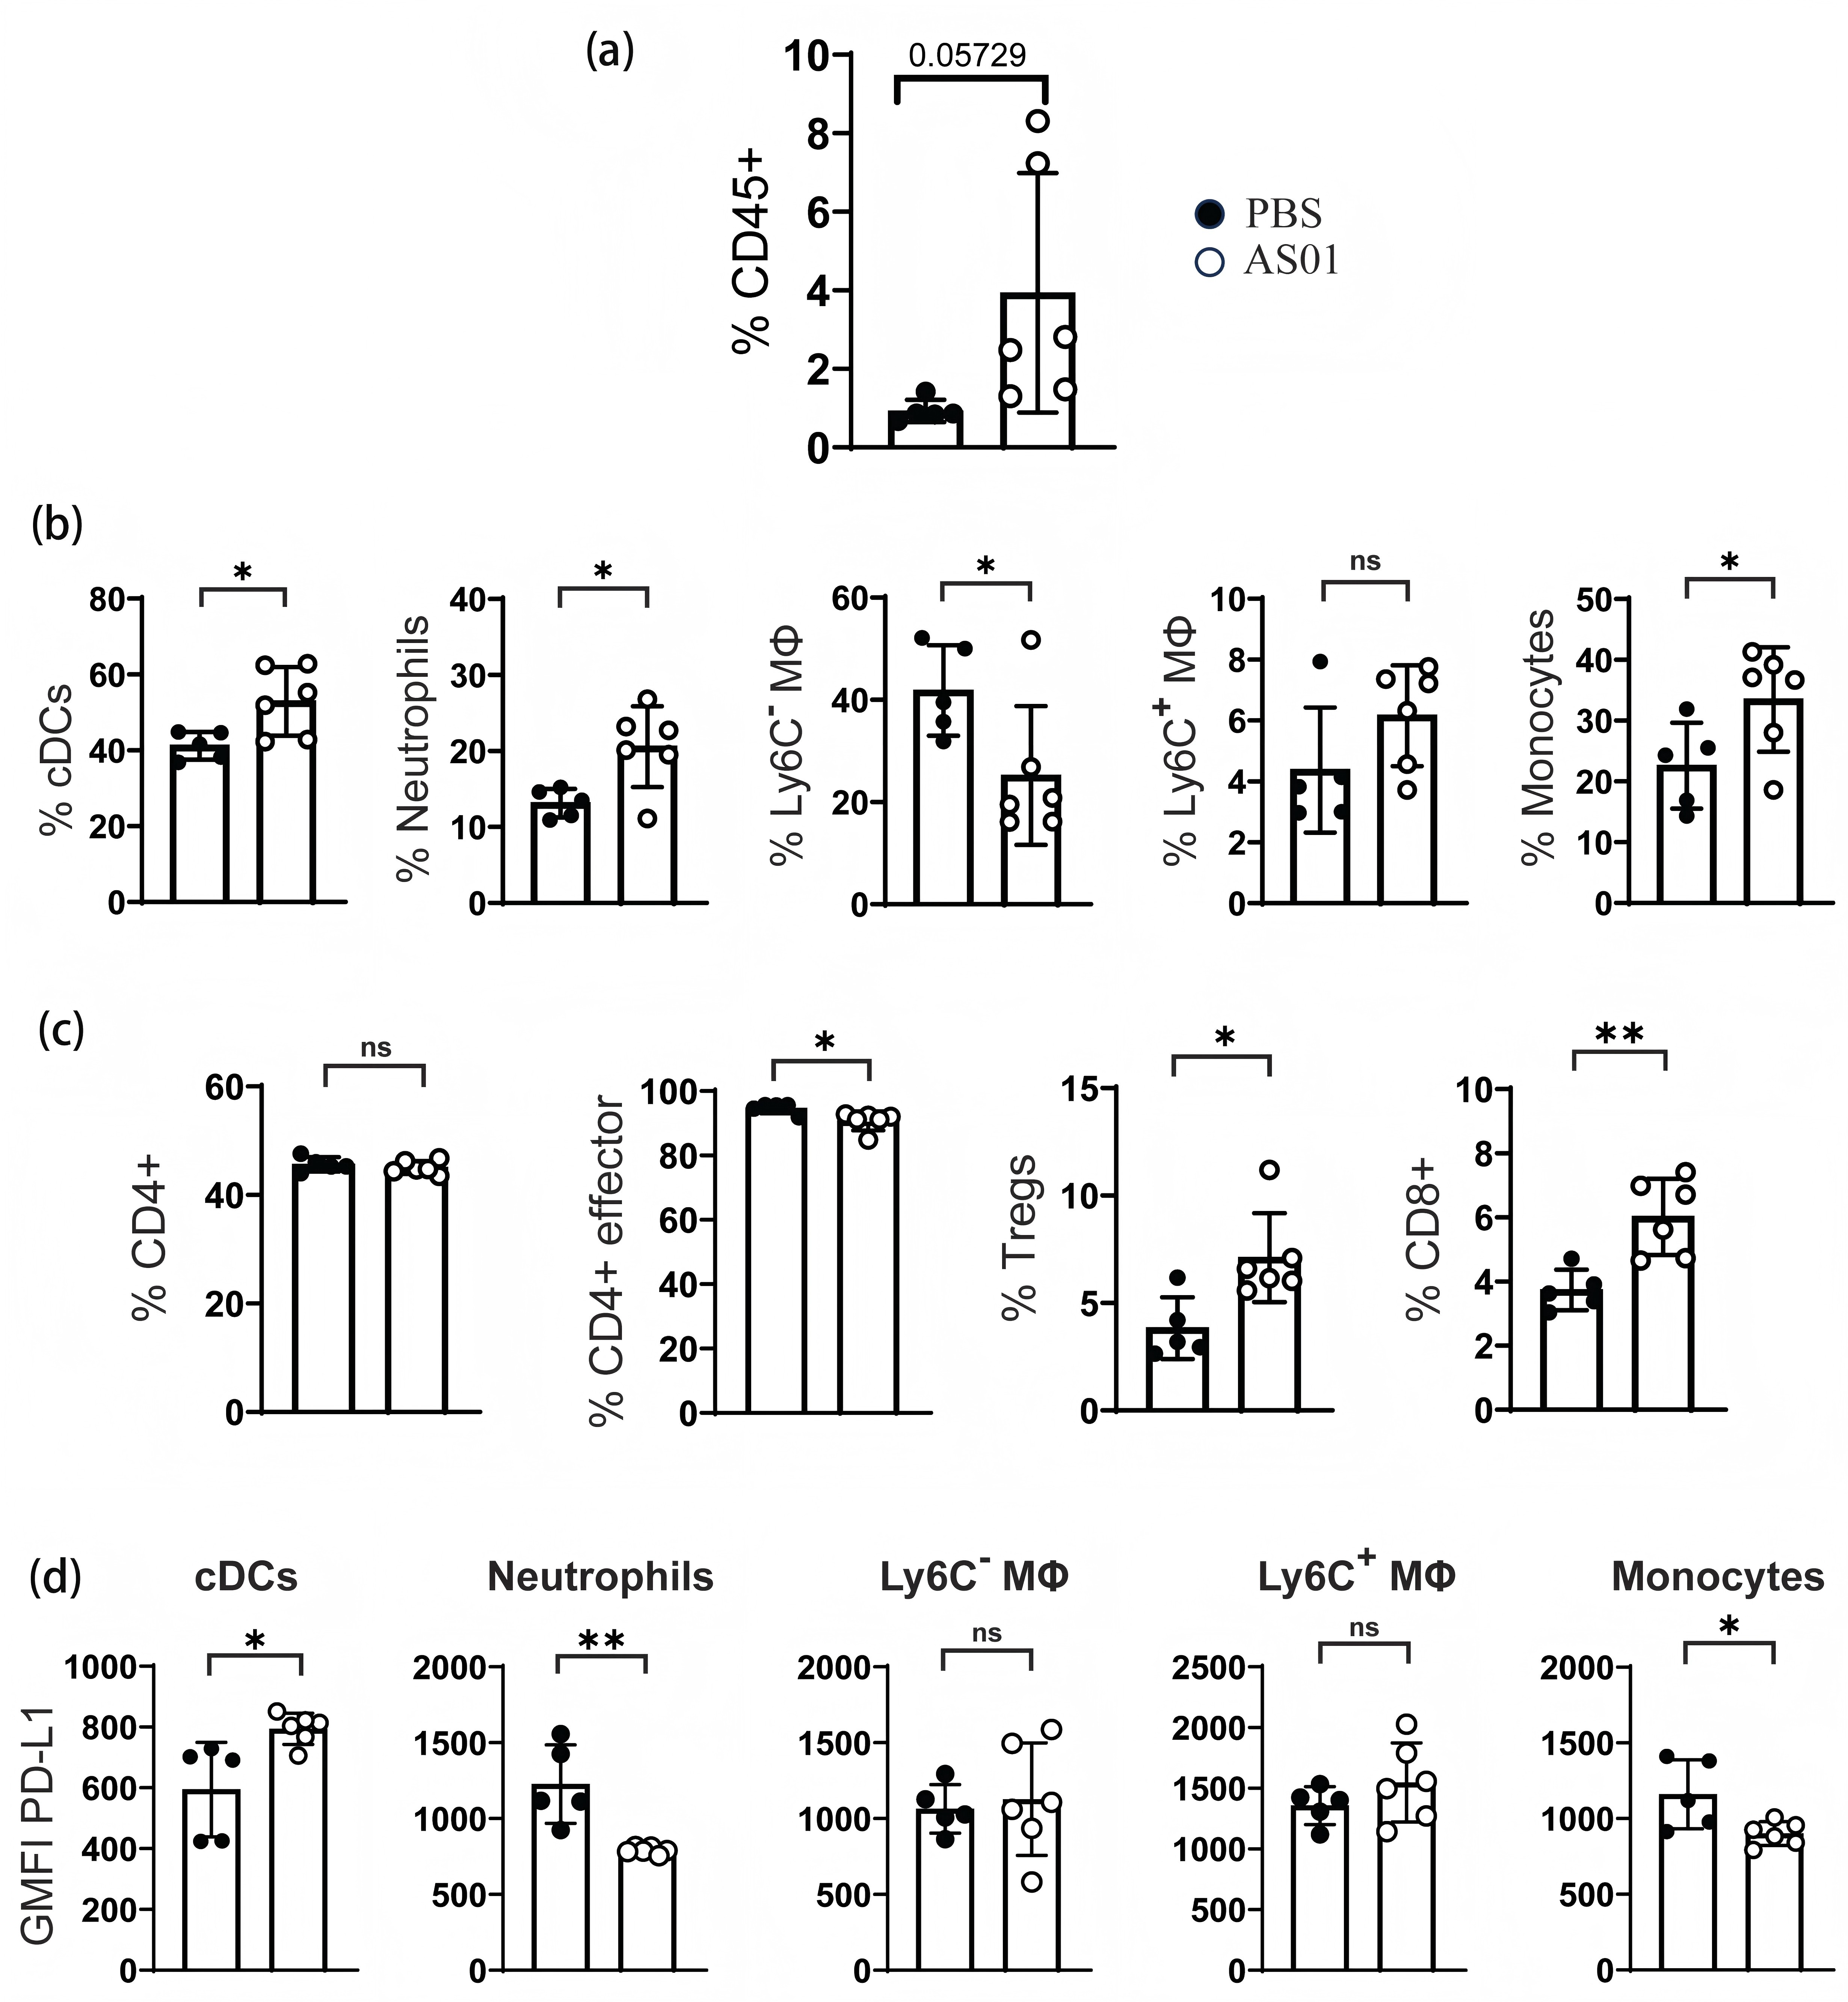
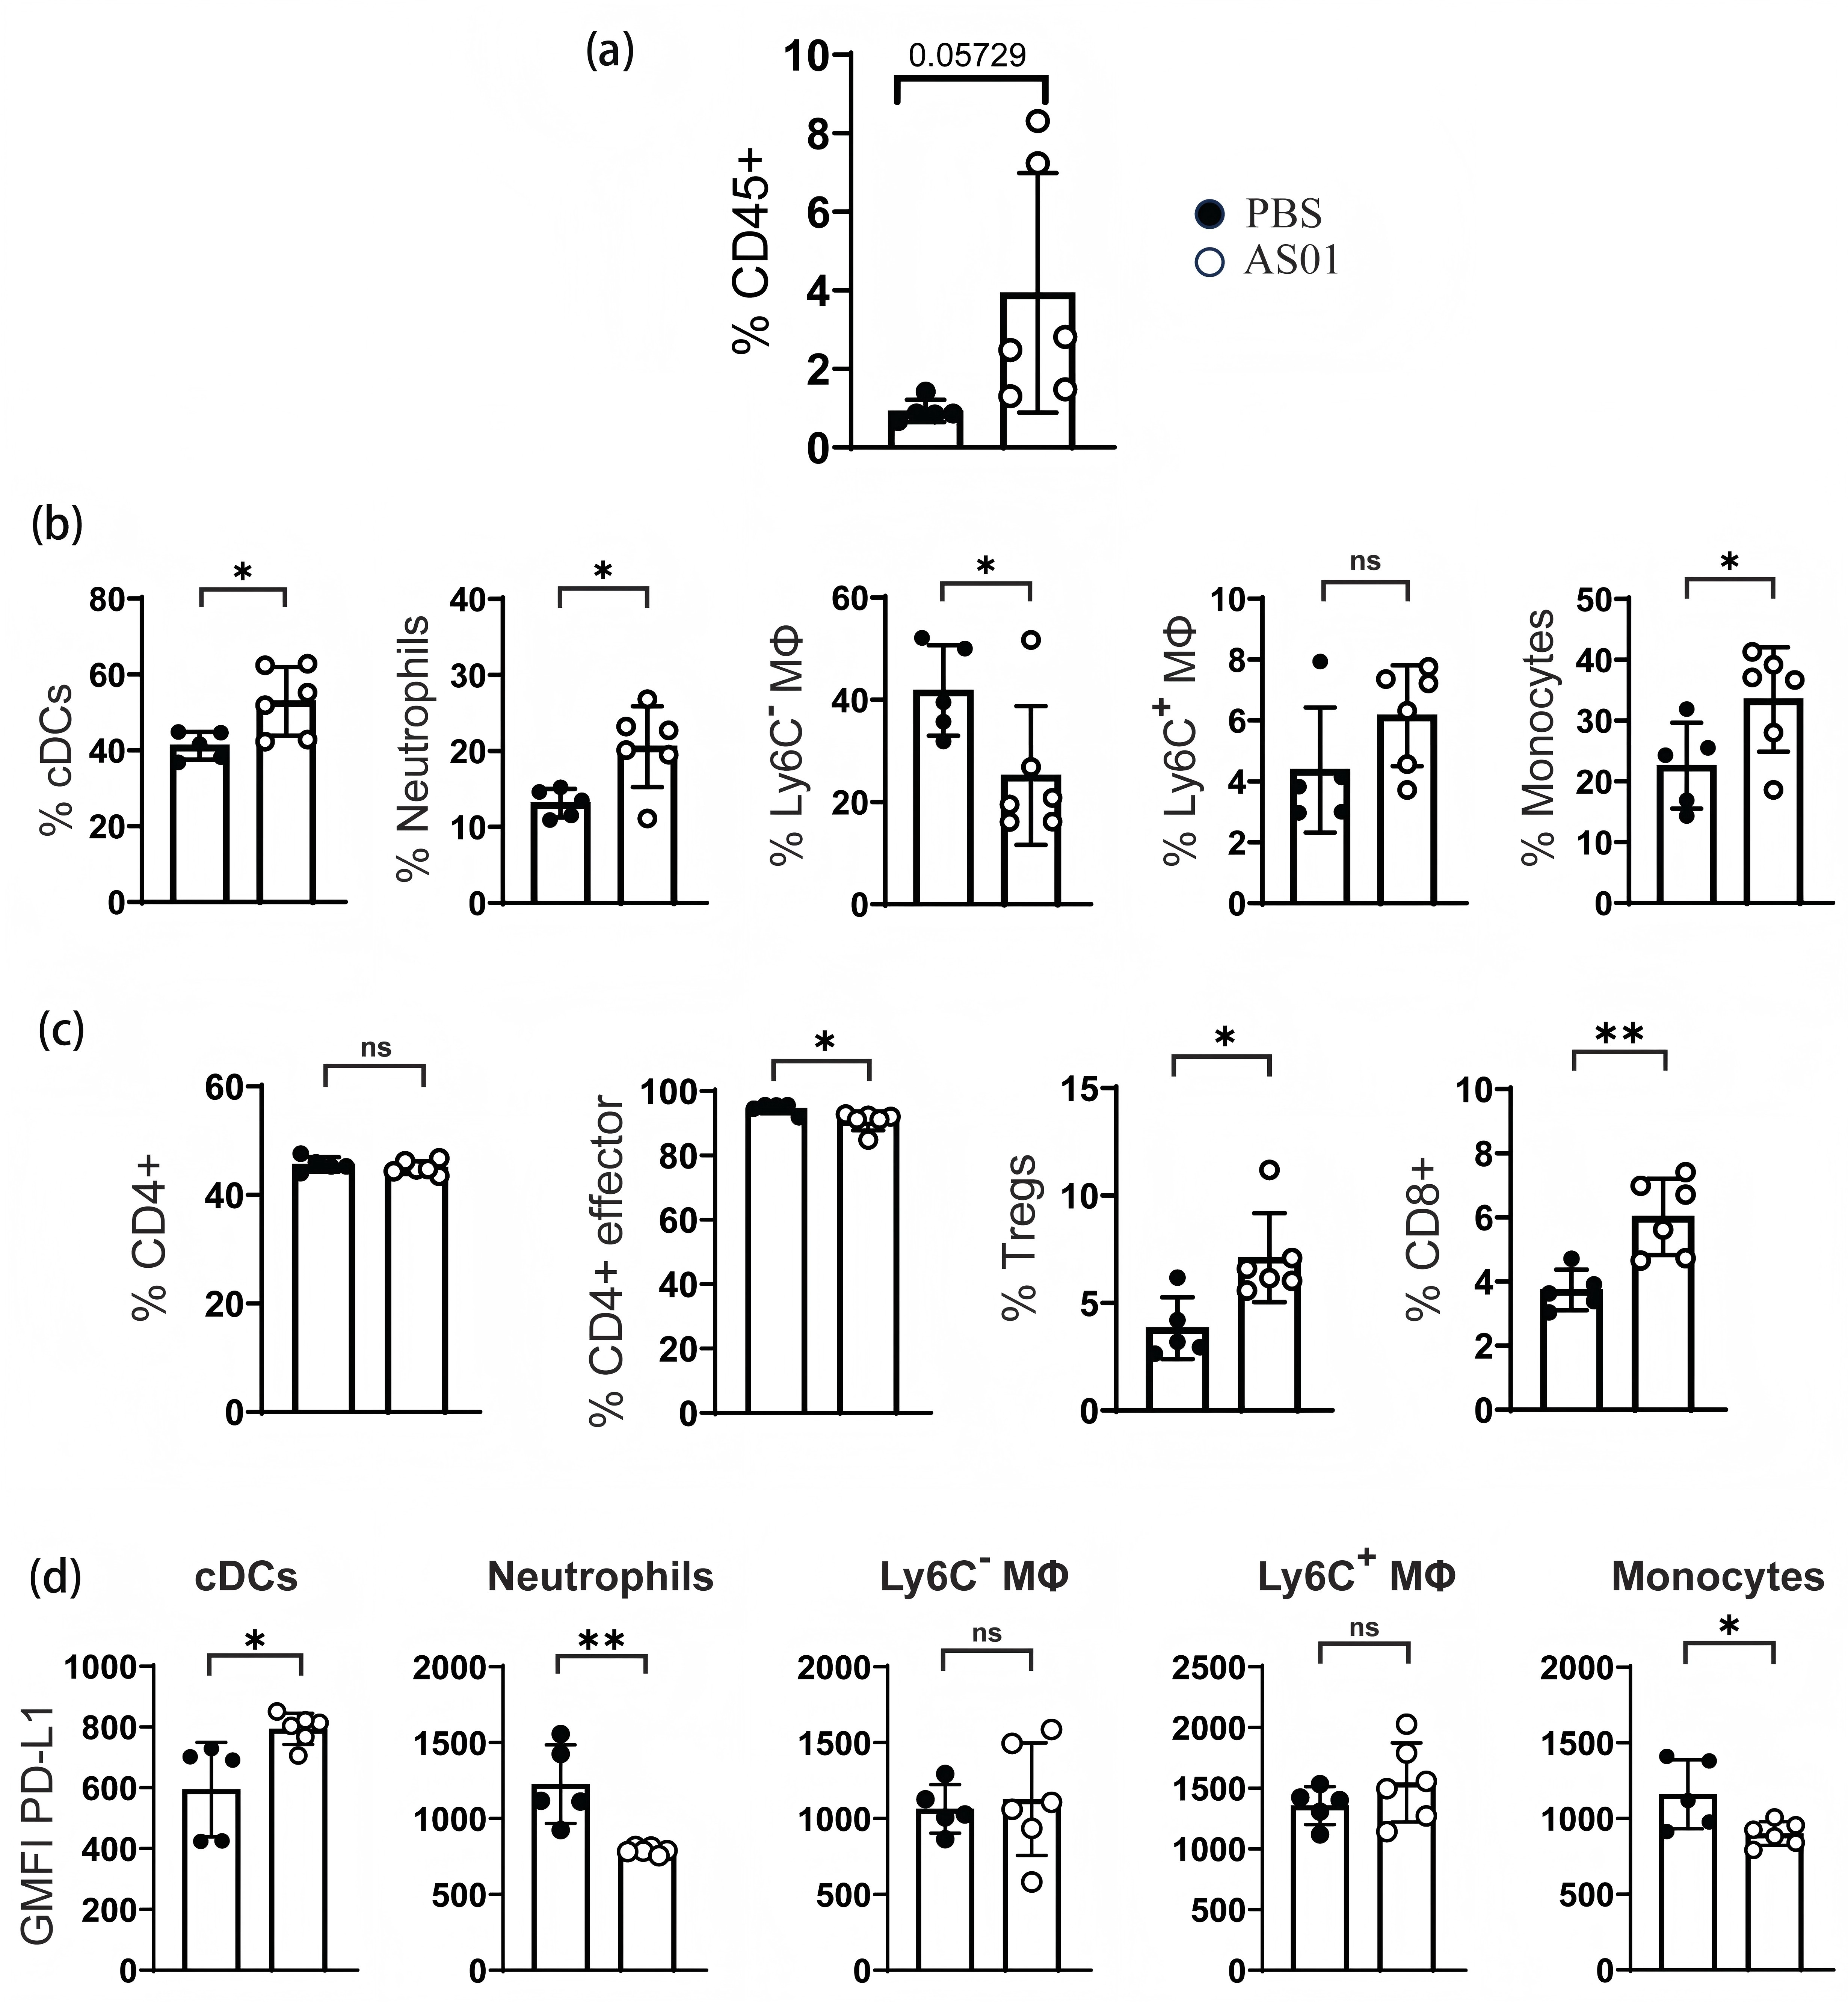
Figure 4. AS01 shifts the TME toward an anti-tumorigenic phenotype. B16-F10 tumors of mice treated with PBS or AS01 (two doses of 20 μg) were excised at day 16 after inoculation and analyzed by flow cytometry. Percentages for (a), (b) and (c) are shown for the parent populations. (a) CD45+ leukocytes as a percentage of live cells within the tumors; (b) Myeloid lineage changes in tumor infiltrating cells. cDCs (CD45+ CD11c+ MHCII+) as percentage of CD45+ CD11c+ cells. Neutrophils (CD45+ CD11c- CD11b+ Ly6G+) as percentage of CD45+ CD11c- CD11b+ cells. Ly6C- or Ly6C+ Macrophages (MΦ, CD45+ CD11c- CD11b+ Ly6G- Ly6C-/+ F4/80+) and monocytes (CD45+ CD11c- CD11b+ Ly6G- Ly6C+ F4/80-) as percentages of CD45+ CD11c- CD11b+ Ly6G- Ly6C+ cells; (c) Tumor-infiltrating lymphoid cell changes. T helper cells (CD45+CD4+) and cytotoxic T cells (CD45+ CD8+) are shown as percentages of CD45+ cells. CD4+ effector T helper cells (CD45+ CD4+ Foxp3-) and Tregs (CD45+ CD4+ Foxp3+) are shown as percentages of CD45+ CD4+ cells; (d) GMFI of PD-L1 in specified myeloid populations. n = 5-6. n = biologically independent mouse samples. Data are shown as mean ± SD, p values obtained by unpaired t tests, *p ≤ 0.05 and **p ≤ 0.01. TME: tumor microenvironment; PBS: phosphate buffered saline; GMFI: geometric mean fluorescence intensities.
Analysis of T cell populations revealed a significant increase in CD8+ cytotoxic T cells and T regulatory cells (Tregs, CD4+ Foxp3+) in the tumors of the mice that received AS01, with a decrease in CD4+ Foxp3- T effector helper cells (Figure 4c, gating strategy in Figure S3C). Indicative of increased antigen uptake[34], intratumoral cDCs upregulated their expression of immune checkpoint molecule PD-L1 in the AS01-treated mice (Figure 4d). Interestingly, tumor-associated neutrophils and monocytes exhibited a markedly decreased expression of PD-L1, suggesting a shift of the TME toward a more immunoresponsive, ‘hot’ tumor phenotype (Figure 4d).
Total leukocyte numbers were also increased in the TME of MB49 bladder tumors after AS01 treatment (Figure S4A, gating strategy in Figure S5). Similar lymphocyte trends as in B16-F10 tumors were observed (Figure S4C). In the myeloid compartment, neutrophils and monocytes were also enriched in the tumors of AS01-treated mice. However, no increased recruitment of cDCs was observed and the decrease in intratumoral Ly6C- macrophages was less pronounced than in B16-F10 melanomas and not statistically significant (Figure S4B), suggesting a tumor type-specific immune remodeling effect of AS01.
4. Discussion
AS01 is an adjuvant used in several vaccines (both clinically approved and candidate), and its use has been associated with heterologous protective effects[25,30]. However, the mechanism underlying these heterologous effects remains poorly understood. In this study, we have assessed the potential of AS01 to induce trained immunity in in vitro studies using human primary cells, and subsequently in experimental cancer models. We show that AS01 can trigger a trained immunity phenotype, as monocytes exposed to AS01 displayed an enhanced IL-6 and TNF production in response to LPS challenge. This response did not result from sustained early inflammatory activation, as AS01 did not trigger the acute release of pro-inflammatory cytokines or ROS production. Subsequently, administration of AS01 slowed the growth of experimental melanoma and bladder carcinoma in mice.
There is strong evidence that trained immunity inducers can reprogram the immune cells of the TME toward an anti-tumorigenic phenotype[11,20,21,35]. Moreover, recent studies have demonstrated that the protection induced by BCG against bladder cancer carcinoma is due to epigenetic reprogramming of myeloid immune cells and their progenitors in the bone marrow[16,36]. Nonetheless, the identification of alternative vaccines or adjuvants with antitumorigenic effects remains desirable, as 40-50% of bladder cancer patients do not respond to BCG treatment[37]. Moreover, BCG is an attenuated strain of Mycobacterium bovis that carries the risk of infectious complications in immunocompromised individuals. In this study, we show that AS01 successfully slows tumor growth in preclinical models of both melanoma and bladder cancer, supporting its potential as a trained-immunity antitumor therapy. AS01 treatment resulted in increased recruitment of neutrophils and monocytes, consistent with an acute inflammation response. Furthermore, these monocytes and neutrophils exhibited decreased PD-L1 expression, indicative of functional reprogramming. The TME of AS01-injected mice also showed fewer tumor-associated macrophages (TAMs), a cell type frequently associated with immune suppression and poor prognosis[5,23]. Altogether, these findings suggest that AS01 reshapes the myeloid cell landscape of the TME toward a more pro-inflammatory and tumor-suppressive phenotype.
Despite the reduction in tumor burden, AS01 did not result in a complete inhibition of cancer progression in the experimental models tested. Combination therapies incorporating trained immunity inducers and immune checkpoint inhibitors (ICI) have been used synergistically with promising results in other cancer models[21,22]. In our study, AS01-treated mice exhibited increased intratumoral infiltration of CD8+ cytotoxic T cells, accompanied by an upregulated PD-L1 expression on tumor-associated DCs. This immune profile indicates the establishment of a TME that may be more responsive to ICI therapy[34,38]. Interestingly, AS01 administration was also associated with increased Treg frequency. Although Tregs are classically linked to immunosuppression and poor cancer prognosis[39,40], ‘fragile’ Tregs (fTregs) have been described to be pro-inflammatory, boost anti-tumor immunity and synergize with ICI therapy[41,42]. Considering fTregs’ dependence on interferon-gamma (IFN-γ)[42] and AS01’s documented induction of IFN-γ in lymphocytes[43], it is tempting to speculate that AS01 induces fTregs, but this remains to be demonstrated. Supporting the rationale of combining AS01 with ICI, a recent phase-I clinical trial evaluated AS01 together with the CTLA-4 inhibitor ipilimumab in a DC vaccine for melanoma patients, with favorable safety results[44]. Consequently, future studies should investigate AS01’s effectiveness in combination with ICI therapy.
Trained immunity is defined as the long-term metabolic and epigenetic rewiring of innate immune cells[45,46]. Interestingly, a recent study found that AS01-vaccinated individuals exhibit long-term monocyte epigenetic rewiring, including altered chromatin accessibility for AP-1, C/EBP, GATA and IRF transcription factors[29]. These findings suggest that AS01 may induce trained immunity at the level of the bone marrow hematopoietic cells.
This study focused on the in vitro capacity of AS01 to induce trained immunity in cells of the monocytic lineage, as these are the best-characterized effector cells of trained immunity-mediated antitumor protection[11,19,21,23]. Nonetheless, other cell types, including neutrophils, dendritic cells, natural killer cells, as well as non-immune stromal and epithelial cells may also mount an innate memory response[46,47]. Notably, neutrophils have been identified as the principal effector cells mediating the antitumoral effect of β-glucan-induced trained immunity[20], and in a separate study, neutrophils primed with low-dose LPS suppressed tumor growth in a murine colon cancer model[48]. Further studies are needed to identify the principal effector cell types involved in AS01-mediated tumor suppression.
Beyond the nature of the stimulus, its timing, concentration and dosing frequency can greatly influence the magnitude of the innate response in trained immunity, as well as in immune tolerance and priming[12,48-52]. It is well documented that LPS, a TLR4 ligand closely related to AS01 constituent MPL, can either suppress or enhance innate immune responsiveness depending on its concentration, duration and number of stimulations and the interval before rechallenge[48-52]. Future experiments varying AS01 concentrations and the timing of administration relative to tumor inoculation, combined with functional, epigenetic and metabolic profiling of immune cells in the TME, may help elucidate the link between AS01-induced trained immunity and its antitumor effects.
Another important aspect to consider is that AS01 failed to inhibit tumor growth in the Lewis lung carcinoma model, suggesting that the anticancer efficacy of trained immunity inducers may depend on tissue, tumor type or TME composition. A sex-dependent effect cannot be excluded, as male mice were used for the melanoma and bladder cancer models, whereas the non-responsive LLC model was performed in female mice. Previous studies have identified sex-dependent differences in trained immune responses in both in vitro and murine models[53-56]. Notably, Earhart et al. reported a diminished trained immune response in female mice upon rechallenge with a heterologous pathogen, which was associated with decreased survival[53]. Mechanistic insight into AS01’s mode of action, together with evaluation of sex as a biological variable, may help determine which malignancies are most likely to respond to therapeutic strategies containing this adjuvant. In addition, further studies should define biomarkers that predict host responsiveness to AS01 administration.
Although acute inflammatory markers were not induced by AS01 in our in vitro model, we cannot completely exclude induction of inflammation in vivo. Indeed, one study found that AS01 can induce intracellular IL-1β and TNF in monocytes, albeit when PBMCs were stimulated with 50-fold higher concentrations than used in our study[57]. Notably, the same study documented that AS01 stimulation induces HIF1α transcription factor overexpression[57], a hallmark molecular feature associated with trained immunity in monocytes[58].
There are several limitations to our study. First, in the murine cancer models, AS01 treatment was initiated at the time of tumor inoculation, rather than in established tumors. While this regimen was chosen to investigate AS01’s potential protective effects associated with trained immunity, future studies should administer AS01 after tumors have been established to better model the clinical setting. Second, the absence of component-specific studies limits our ability to determine which constituents of AS01 (MPL, QS-21 or the liposomal formulation) or which signaling pathways contribute to the observed immunological and antitumor effects. Third, the lack of response in the LLC model should be interpreted cautiously, as this model was conducted in female mice, whereas the melanoma and bladder cancer models were performed in male mice. Therefore, sex represents a potential confounder in our study that cannot be separated from tumor type-specific effects. Fourth, the phenotyping of tumor microenvironments reported relative frequencies, rather than absolute immune cell counts, which limits our ability to distinguish true changes in abundance from shifts in relative immune composition. Finally, although the proximity extension assay identified a pattern of increased secretion of inflammatory proteins in AS01-trained macrophages, the sample size was insufficient to identify statistically significant changes after correction for multiple testing.
5. Conclusion
In summary, our data establish AS01 as an inducer of trained immunity capable of reshaping the tumor microenvironment and suppressing tumor growth in preclinical models of melanoma and bladder cancer. By increasing tumor-infiltrating monocytes, neutrophils and CD8+ T cells, while reducing immunosuppressive TAMs, AS01 induces a shift in the TME toward a more antitumoral immune landscape. These findings support the repurposing of clinically approved adjuvants like AS01 for trained immunity-based cancer immunotherapies and warrant further investigation of their use in combination with immune checkpoint inhibitors.
Supplementary materials
The supplementary material for this article is available at: Supplementary materials.
Authors contribution
Simioniuc M: Investigation, conceptualization, methodology, formal analysis, writing-original draft.
Boumpas A: Investigation, formal analysis.
van Houten P, Jaeger M: Conceptualization, methodology, formal analysis, supervision, writing-review & editing.
Schlüter T: Formal analysis.
Netea-Maier RT: Conceptualization, methodology, formal analysis, supervision.
Ziogas A: Conceptualization, methodology, supervision, writing-review & editing.
Verginis P, Netea MG: Conceptualization, supervision, formal analysis, writing-review & editing.
Conflicts of interest
M.G.N. is a scientific founder of Trained Therapeutics and Discovery (TTxD), Lemba, Salvina, and Biotrip. The other authors declare no conflicts of interest.
Ethical approval
Ethical approval concerning the blood draws was given by the Medical Ethical Committee Oost-Nederland (NL84281.091.23). The protocols used for animal experimentation were in accordance with institutional guidelines and approved by the Welfare Institutional Committee of Protocol Evaluation together with the Directorate of Agriculture and Veterinary Policy, Region of Attika, Greece (protocol 285279/04-04-2022).
Consent to participate
Written consent was obtained from all participants before inclusion in the study.
Consent for publication
Not applicable.
Availability of data and materials
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Funding
M.G.N. was supported by a Spinoza Grant of the Netherlands Organization for Scientific Research (Grant No. SPI 94-212).
Copyright
© The Author(s) 2026.
References
-
1. Force LM, Kocarnik JM, May ML, Bhangdia K, Crist A, Penberthy L, et al. The global, regional, and national burden of cancer, 1990-2023, with forecasts to 2050: A systematic analysis for the Global Burden of Disease Study 2023. Lancet. 2025;406(10512):1565-1586.[DOI]
-
2. Kocarnik JM, Compton K, Dean FE, Fu W, Gaw BL, Harvey JD, et al. Cancer incidence, mortality, years of life lost, years lived with disability, and disability-adjusted life years for 29 cancer groups from 2010 to 2019: A systematic analysis for the global burden of disease study 2019. JAMA Oncol. 2022;8(3):420.[DOI]
-
3. Siegel RL, Kratzer TB, Giaquinto AN, Sung H, Jemal A. Cancer statistics, 2025. CA Cancer J Clin. 2025;75(1):10-45.[DOI]
-
4. Garner H, de Visser KE. Immune crosstalk in cancer progression and metastatic spread: A complex conversation. Nat Rev Immunol. 2020;20(8):483-497.[DOI]
-
7. Netea MG, Quintin J, van der Meer JWM. Trained immunity: A memory for innate host defense. Cell Host Microbe. 2011;9(5):355-361.[DOI]
-
8. Bowdish DME, Loffredo MS, Mukhopadhyay S, Mantovani A, Gordon S. Macrophage receptors implicated in the “adaptive” form of innate immunity. Microbes Infect. 2007;9(14-15):1680-1687.[DOI]
-
9. Christ A, Günther P, Lauterbach MAR, Duewell P, Biswas D, Pelka K, et al. Western diet triggers NLRP3-dependent innate immune reprogramming. Cell. 2018;172(1-2):162-175.e14.[DOI]
-
15. Moorlag SJCFM, Khan N, Novakovic B, Kaufmann E, Jansen T, van Crevel R, et al. β-glucan induces protective trained immunity against mycobacterium tuberculosis infection: A key role for IL-1. Cell Rep. 2020;31(7):107634.[DOI]
-
18. Kremenovic M, Schenk M, Lee DJ. Clinical and molecular insights into BCG immunotherapy for melanoma. J Intern Med. 2020;288(6):625-640.[DOI]
-
21. Geller AE, Shrestha R, Woeste MR, Guo H, Hu X, Ding C, et al. The induction of peripheral trained immunity in the pancreas incites anti-tumor activity to control pancreatic cancer progression. Nat Commun. 2022;13:759.[DOI]
-
23. Vuscan P, Kischkel B, Joosten LAB, Netea MG. Microbial-induced trained immunity for cancer immunotherapy. Pharmacol Rev. 2025;77(5):100074.[DOI]
-
26. Wadman M. First malaria vaccine slashes childhood deaths. Science. 2023;382(6669):357.[DOI]
-
27. Hamel M. Update on malaria vaccines. Background document for Session 2, Malaria Policy Advisory Group Meeting, 2024 Mar 4-5; Yaoundé, Cameroon. 2024. Available from: https://cdn.who.int/media/docs/default-source/malaria/mpac-documentation/mpag-march2024-session2-malaria-vaccines-rev.pdf?sfvrsn=7b97c37_3
-
28. Mwapasa V, Asante KP, Milligan P, Akech S, Oduro A, Mathanga DP, et al. Impact of introducing RTS,S/AS01E malaria vaccine on mortality in young children in Ghana, Kenya, and Malawi: an observational evaluation of a cluster-randomised implementation programme. The Lancet. 2026;407(10541):1796-1808.[DOI]
-
31. Domínguez-Andrés J, Arts RJW, Bekkering S, Bahrar H, Blok BA, de Bree LCJ, et al. In vitro induction of trained immunity in adherent human monocytes. STAR Protoc. 2021;2(1):100365.[DOI]
-
35. Schlüter T, van Elsas Y, Priem B, Ziogas A, Netea MG. Trained immunity: Induction of an inflammatory memory in disease. Cell Res. 2025;35(11):792-802.[DOI]
-
39. Zou W. Regulatory T cells, tumour immunity and immunotherapy. Nat Rev Immunol. 2006;6(4):295-307.[DOI]
-
44. Tijtgat J, Geeraerts X, Boisson A, Stevens L, Vounckx M, Dirven I, et al. Intratumoral administration of the immunologic adjuvant AS01B in combination with autologous CD1c (BDCA-1)+/CD141 (BDCA-3)+ myeloid dendritic cells plus ipilimumab and intravenous nivolumab in patients with refractory advanced melanoma. J Immunother Cancer. 2024;12(1):e008148.
-
45. Vuscan P, Kischkel B, Joosten LAB, Netea MG. Trained immunity: General and emerging concepts. Immunol Rev. 2024;323(1):164-185.[DOI]
-
51. Foster SL, Hargreaves DC, Medzhitov R. Gene-specific control of inflammation by TLR-induced chromatin modifications. Nature. 2007;447(7147):972-978.[DOI]
-
53. Earhart AP, Karasseva NG, Storey KM, Olthoff B, Sarker MB, Laffey KG, et al. Lower female survival from an opportunistic infection reveals progesterone-driven sex bias in trained immunity. Cell Rep. 2023;42(8):113007.[DOI]
-
55. Koeken VACM, de Bree LCJ, Mourits VP, Moorlag SJCFM, Walk J, Cirovic B, et al. BCG vaccination in humans inhibits systemic inflammation in a sex-dependent manner. J Clin Invest. 2020;130(10):5591-5602.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Simioniuc M, Boumpas A, Jaeger M, van Houten P, Schlüter T, Netea-Maier RT, et al. AS01 adjuvant is a trained immunity inducer with potent antitumor activity. Myeloid Cells. 2026;1:202615. https://doi.org/10.70401/mc.2026.0011
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

 Get citation
Science Exploration Style

Simioniuc M, Boumpas A, Jaeger M, van Houten P, Schlüter T, Netea-Maier RT, et al. AS01 adjuvant is a trained immunity inducer with potent antitumor activity. Myeloid Cells. 2026;1:202615. https://doi.org/10.70401/mc.2026.0011
copy
Share Link
copy