Spatial single-cell profiling reveals macrophage niches in severe COVID-19 lungs

Joan Abinet
1,2,#

,
Cecilia Ruscitti
1,2,#
,
Mutien Garigliany
2,3
,
Maude Liégeois
1,2
,
Coraline Radermecker
1,2,†,*
,
Thomas Marichal
1,2,4,†,*
*Correspondence to:
Thomas Marichal, Laboratory of Immunophysiology, GIGA Institute, University of Liège, Liège 4000, Belgium; Faculty of Veterinary Medicine, University of Liège, Liège 4000, Belgium.
E-mail: t.marichal@uliege.be
Coraline Radermecker, Laboratory of Immunophysiology, GIGA Institute, University of Liège, Liège 4000, Belgium; Faculty of Veterinary Medicine, University of Liège, Liège 4000, Belgium. E-mail: c.radermecker@uliege.be
Coraline Radermecker, Laboratory of Immunophysiology, GIGA Institute, University of Liège, Liège 4000, Belgium; Faculty of Veterinary Medicine, University of Liège, Liège 4000, Belgium. E-mail: c.radermecker@uliege.be
Myeloid Cells. 2026;1:202612. 10.70401/mc.2026.0014
Received: May 26, 2026Accepted: September 14, 2026Published: September 15, 2026
Abstract
Aims: Severe coronavirus disease 2019 (COVID-19) is characterized by marked heterogeneity in lung pathology, including diffuse alveolar damage, inflammation, and fibrosis. However, how spatially organized cellular interactions contribute to these divergent pathological outcomes remains incompletely understood. We aimed to define the spatial organization of cellular microenvironments in severe COVID-19 lungs and identify niche-specific cellular interactions associated with distinct histopathological states.
Methods: We applied imaging-based single-cell spatial transcriptomics to post-mortem lung tissues from patients with severe COVID-19 and control subjects, enabling high-resolution mapping of cellular composition, spatial neighborhoods, and predicted ligand-receptor interactions within intact tissue architecture.
Results: Analysis of 76,973 cells identified 20 distinct cell populations and revealed marked heterogeneity between COVID-19 samples, corresponding to different histopathological states. Spatial niche analysis identified discrete macrophage-associated microenvironments. Fibrotic niches were enriched in chitinase 3-like 1 (CHI3L1)/matrix metalloproteinase 9 (MMP9hi) macrophages spatially associated with collagen type I alpha 1 chain (COL1A1+) fibroblasts and basal cells. Ligand-receptor inference predicted macrophage-derived transforming growth factor beta (TGF-β) and galectin-3 signaling as drivers of pathogenic fibroblast activation and extracellular matrix remodeling. In contrast, alveolar niches contained secreted phosphoprotein 1 (SPP1hi) macrophages exposed to epithelial-derived cues, including WNT ligands and granulocyte-macrophage colony-stimulating factor (GM-CSF), consistent with differentiation toward an alveolar macrophage-like state.
Conclusion: Severe COVID-19 lungs are organized into distinct spatial niches associated with divergent immunopathological trajectories. Imaging-based spatial transcriptomics provides a platform to link histopathological states with localized cellular interactions and macrophage-driven tissue remodeling programs.
Keywords
Macrophage, single-cell spatial transcriptomics, COVID-19
1. Introduction
Since its emergence in late 2019, infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) has resulted in nearly 800 million confirmed cases worldwide and approximately 7 million deaths[1]. While most individuals develop mild, self-limiting respiratory symptoms resembling the common cold[2], severe coronavirus disease 2019 (COVID-19) is characterized by acute lung injury, often progressing to acute respiratory distress syndrome (ARDS) and other life-threatening complications requiring hospitalization, intensive care unit admission, and mechanical ventilation[3,4]. Moreover, survivors may develop long-term post-acute sequelae following primary infection, including diffuse pulmonary fibrosis[5]. A defining feature of severe COVID-19 is the remarkable heterogeneity of pulmonary pathology, with co-existing patterns of diffuse alveolar damage (DAD), inflammation, and fibrosis[6-8]. DAD is the main COVID-19-associated histological pattern, reflecting evolving stages of lung injury[7] and often associated with capillary congestion and microthrombi[9,10]. Early SARS-CoV-2 pneumonia is characterized by exudative DAD with hyaline membranes and inflammatory infiltrates[6,11], followed by an epithelial proliferative phase and, in some patients, progression to fibrosis[12].
This heterogeneity reflects, at least in part, dysregulated immune responses[13,14]. Severe disease is indeed associated with impaired antiviral signaling, excessive myeloid-driven inflammation, and altered macrophage composition[15-17]. In particular, the accumulation of monocyte-derived macrophages and the persistence of secreted phosphoprotein 1 (SPP1+) macrophages have been linked to disease severity, tissue remodeling, and fibrosis[18,19]. Such dysregulated immune responses can be orchestrated by[20] and result in[21,22] modifications in structural cell activation. Indeed, structural cells such as epithelial cells, fibroblasts, and endothelial cells undergo profound changes, contributing to tissue damage and repair processes. However, how these diverse cell populations interact within the lung microenvironment to drive distinct pathological outcomes remains poorly understood.
Emerging evidence suggests that the functional behavior of immune and structural cells is critically shaped by their spatial organization within tissues. Recent studies combining single-cell and spatial transcriptomics have begun to map the cellular landscape of COVID-19 lungs, revealing associations between specific cell populations and disease severity[11,12,23,24]. Imaging-based spatial transcriptomics (ST) further enables high-resolution, single-cell mapping of gene expression within intact tissue sections, providing insights into tissue architecture, cell-cell interactions, and local cellular states within their native microenvironment.
Here, we hypothesized that severe COVID-19 lungs are organized into distinct spatial niches that integrate specific cellular compositions and intercellular signaling networks, thereby modulating divergent pathological trajectories. We applied the imaging-based ST method CosMx (Nanostring)[25] to post-mortem lung tissues from patients with severe COVID-19 and control subjects. Our analyses revealed that severe COVID-19 lungs comprise discrete, macrophage-centered niches associated with specific histopathological states. Pro-fibrotic niches contained chitinase 3-like 1 (CHI3L1)/matrix metalloproteinase 9 (MMP9hi) macrophages spatially coupled to pathogenic fibroblasts and predicted to promote their activation through transforming growth factor beta (TGF-β) signaling. In contrast, alveolar niches were enriched in SPP1hi macrophages exposed to epithelial-derived signals that may promote an alveolar macrophage-like state. Together, these findings highlight how localized cellular interactions may contribute to divergent immunopathological outcomes within the same organ.
2. Methods
2.1 Sample collection
Lung samples from six subjects were collected post-mortem at the University Hospital of Liege (Belgium), including three patients who died of severe COVID-19[15] and three subjects who died from unrelated, non-pulmonary causes (Table 1). Samples were collected within 5 minutes after death by the same dedicated pulmonologist following a standardized procedure. For COVID-19 cases, tissue was collected from macroscopically identified lesional areas, without systematic preference for a particular pulmonary lobe. Non-COVID-19 control samples consisted of archived tissues selected from the available biobank material to provide the best possible match for age and sex. All tissues were provided by the Biobank of the Liege University Hospital. Lung samples were formalin-fixed, paraffin-embedded (FFPE), and 4-μm-thick serial tissue sections were prepared.
Table 1. Characteristics of human subjects from which lung samples originate.
| Patient number | Gender | Age (years) | Cause of death | SARS-CoV-2 (PCR) |
| 1 | M | 39 | Cardiac death | No |
| 2 | F | 39 | Cardiac death | No |
| 3 | M | 63 | Cardiac death | No |
| 4 | M | 63 | Pneumonia | Yes |
| 5 | M | 67 | ARDS | Yes |
| 6 | M | 56 | ARDS | Yes |
SARS-CoV-2: severe acute respiratory syndrome coronavirus 2; ARDS: acute respiratory distress syndrome; F: female; M: male; PCR: polymerase chain reaction.
2.2 Histopathological evaluation
Hematoxylin & eosin (H&E)-stained serial sections were evaluated by a trained pathologist. Histopathological features were assessed using descriptive and semi-quantitative criteria. Fibrosis was graded based on the extent of alveolar septal thickening due to fibrotic tissue deposition using a 4-point scale: 0, absent/minimal; 1, mild; 2, moderate; and 3, severe, as previously described[26]. Inflammatory infiltration was graded as mild, moderate, or severe according to the extent and density of lymphoplasmacytic and histiocytic infiltrates. Other histopathological features, including pulmonary congestion, edema, air trapping, emphysematous changes, hemorrhage, and bronchiolar remodeling, were recorded qualitatively.
2.3 Single cell spatial transcriptomic analysis with CosMx
FFPE tissue section preparation for CosMx spatial molecular imager (CosMx SMI) and in situ hybridization were performed according to the manufacturer’s instructions. Briefly, 4-µm tissue sections were mounted on VWR Superfrost Plus Micro slides. Precisely, within each slide, tissue sections measuring 5 × 12 mm were arranged side by side to fit within the designated “Tissue Scan Area” of the slide, which allows a maximum space of 15 × 20 mm. The slides were subsequently baked overnight at 60 °C. In situ hybridization probes (from Human Universal Cell Characterization RNA Panel-1,000 plex) from Nanostring were used for hybridization. RNA target readout was performed on the CosMx SMI instrument and 40 imaging sections (i.e., fields of view (FOV), 0.5 × 0.5 mm each) were randomly selected for imaging in each whole-slide scan. Transcript localization was achieved with an approximate spatial resolution of 50 nm. After RNA readout, the tissue samples were incubated with a 4-fluorophore-conjugated antibody cocktail against CD298/B2M, PanCK, CD45, and CD68 proteins and DAPI stain in the CosMx SMI instrument. Images for the 5 channels (4 antibodies and DAPI) were captured. The imaging results were subsequently automatically exported to the cloud-based AtoMxTM Spatial Informatics Platform. Single cells were segmented post-acquisition to obtain cell boundaries, transcripts were assigned to their corresponding cell based on the segmentation map and further localized to a specific cellular compartment (e.g., nucleus, cytoplasm), and a transcript-by-cell count matrix was obtained.
2.4 Data analysis
Count matrix, transcripts positions, and segmentation data were exported from the AtoMxTM Spatial Informatics Platform and were loaded with the Seurat[27] package (5.2.1) using the LoadNanostring function. The gene counts were normalized and scaled with the SCTransform method. After merging cells from the 2 slides, 39 clusters were identified using the FindClusters function (30 Principal Components (PC) included and a resolution of 1.25 was selected) and the differentially expressed genes (DEG) were calculated using the FindAllMarkers function. A filtered version of the data was obtained by keeping a subset of cells with a gene count higher than 100 and an RNA count superior to 250. A total of 29 clusters were identified in the filtered object. These clusters were subsequently annotated based on marker gene expression. The annotated cell identities were then mapped back onto the unfiltered dataset to assess the cellular composition of the original clusters. Clusters that could not be confidently annotated were labeled as “unidentified”. The bioinformatic workflow for data analysis can be found in Figure S1.
Some observations were validated in an independent CosMx dataset of a COVID-19 lung cohort[28]. The corresponding Seurat object was downloaded, and autopsy sample #6, which contained the macrophage population of interest, was selected for separate analysis. Cells from this sample were clustered using FindClusters with 25 PCs and a resolution of 1.25, resulting in 20 clusters. Clusters were subsequently annotated based on marker gene expression and the original annotations provided by the authors.
2.5 Automatic cell annotations by Robust Cell Type Decomposition
Cells were annotated using Robust Cell Type Decomposition (RCTD)[29] using the spacexr package (version 2.2.1). A reference dataset was required for the annotation, and a single-cell transcriptomics dataset was obtained from the Human Lung Cell Atlas (HLCA)[30]. The reference consisted of cells from both normal and COVID-19 conditions using the most granular level of annotation called “ann_finest_level”. This dataset was then subsampled and only a maximum of 2,000 cells per “finest annotation” was kept (7.6 × 10⁴ cells in total). An RCTD reference was created using the create.RCTD function and the Seurat object was annotated using the run.RCTD function in doublets mode. When double annotations were obtained for a cell, we only considered the first one.
2.6 Gene Ontology
The DEG lists for enrichment analyses were calculated using the Seurat function FindMarkers; only positively regulated genes were included, and p-values were adjusted with a Bonferroni correction using all features in the dataset. Thresholds of an average log2 fold change of 1 and an adjusted P value of 0.05 were applied to filter the gene lists. Gene Ontology (GO) enrichment analyses were made using enrichGO functions from the clusterProfiler[31] package with default arguments. Ontology gene sets from the Molecular Signatures Database (MSigDB) were used to test for enrichment. Gene Ratio is the proportion of DEG overlapping with a given gene set. It was calculated as the number of enriched genes in a gene set divided by the total number of genes in that gene set.
2.7 Cell-based niche analysis
After cell annotation, niche annotation was performed using the BuildNicheAssay function (Seurat). The function works by first creating a single-cell neighborhood matrix based on the cell types that compose the neighborhood, then by clustering the cells based on the composition of their neighborhood. The neighborhood of a cell was defined as its 30 nearest neighboring cells in physical space. The niche analysis was performed on both slides jointly. The K number of niches to be returned by the function was fixed to 10. This number was decided with the objective of having the highest number of niches while keeping a specific cell composition for each of them. The number of cells from each annotated cell population within each niche was placed in a count matrix. A z-score normalization was applied to the matrix for each cell type and the matrix was plotted in a heatmap using ComplexHeatmap[32].
2.8 Ligand-receptor analysis
Cell-cell interactions were assessed using NicheNet (version 2.2.0)[33]. For the initial analysis, CHI3L1/MMP9hi macrophages were designated as sender cells, while fibroblasts were defined as receiver cells. For the second analysis, AT2 were defined as sender cells and macrophages were defined as receiver cells. Genes were considered as potential ligands if they were expressed in at least 5% of the sender cell population. In receiver cells, 2 gene sets of interest were defined by identifying DEGs between alveolar fibroblasts and COL1A1+ fibroblasts and between SPP1+ macrophages and alveolar macrophages (AM). Genes were included in the target gene set if they had an average log2 fold change greater than 1 and an adjusted p-value below 0.05.
Ligand prioritization was then performed using NicheNet’s scoring framework, and the top 30 ligands were selected based on their area under the precision-recall curve. A ligand-target gene heatmap was generated to visualize the predicted regulatory potential of each ligand on its target genes. The top ligand-target interactions were further visualized using a circos plot. ST outputs from CosMx SMI were imported into Giotto[34] (version 4.2.1) using the createGiottoCosMxObject function. Spatial density plots of gene markers were then generated with the spatInSituPlotDensity function to visualize the localization patterns of relevant cell populations and marker gene expression.
3. Results
3.1 Single cell spatial transcriptomic profiling of COVID-19 and control lung tissue
Lung tissue sections from 3 severe COVID-19 patients[15] and three subjects who died from non-pulmonary causes were analyzed using CosMx SMI (Table 1 and Figure 1a). Tissue blocks from COVID-19 patients and control subjects were mounted on separate slides, referred to as the “COVID-19” and “Control” slides, respectively. All samples were processed according to the experimental workflow outlined in Figure 1a and as explained in the Methods section.
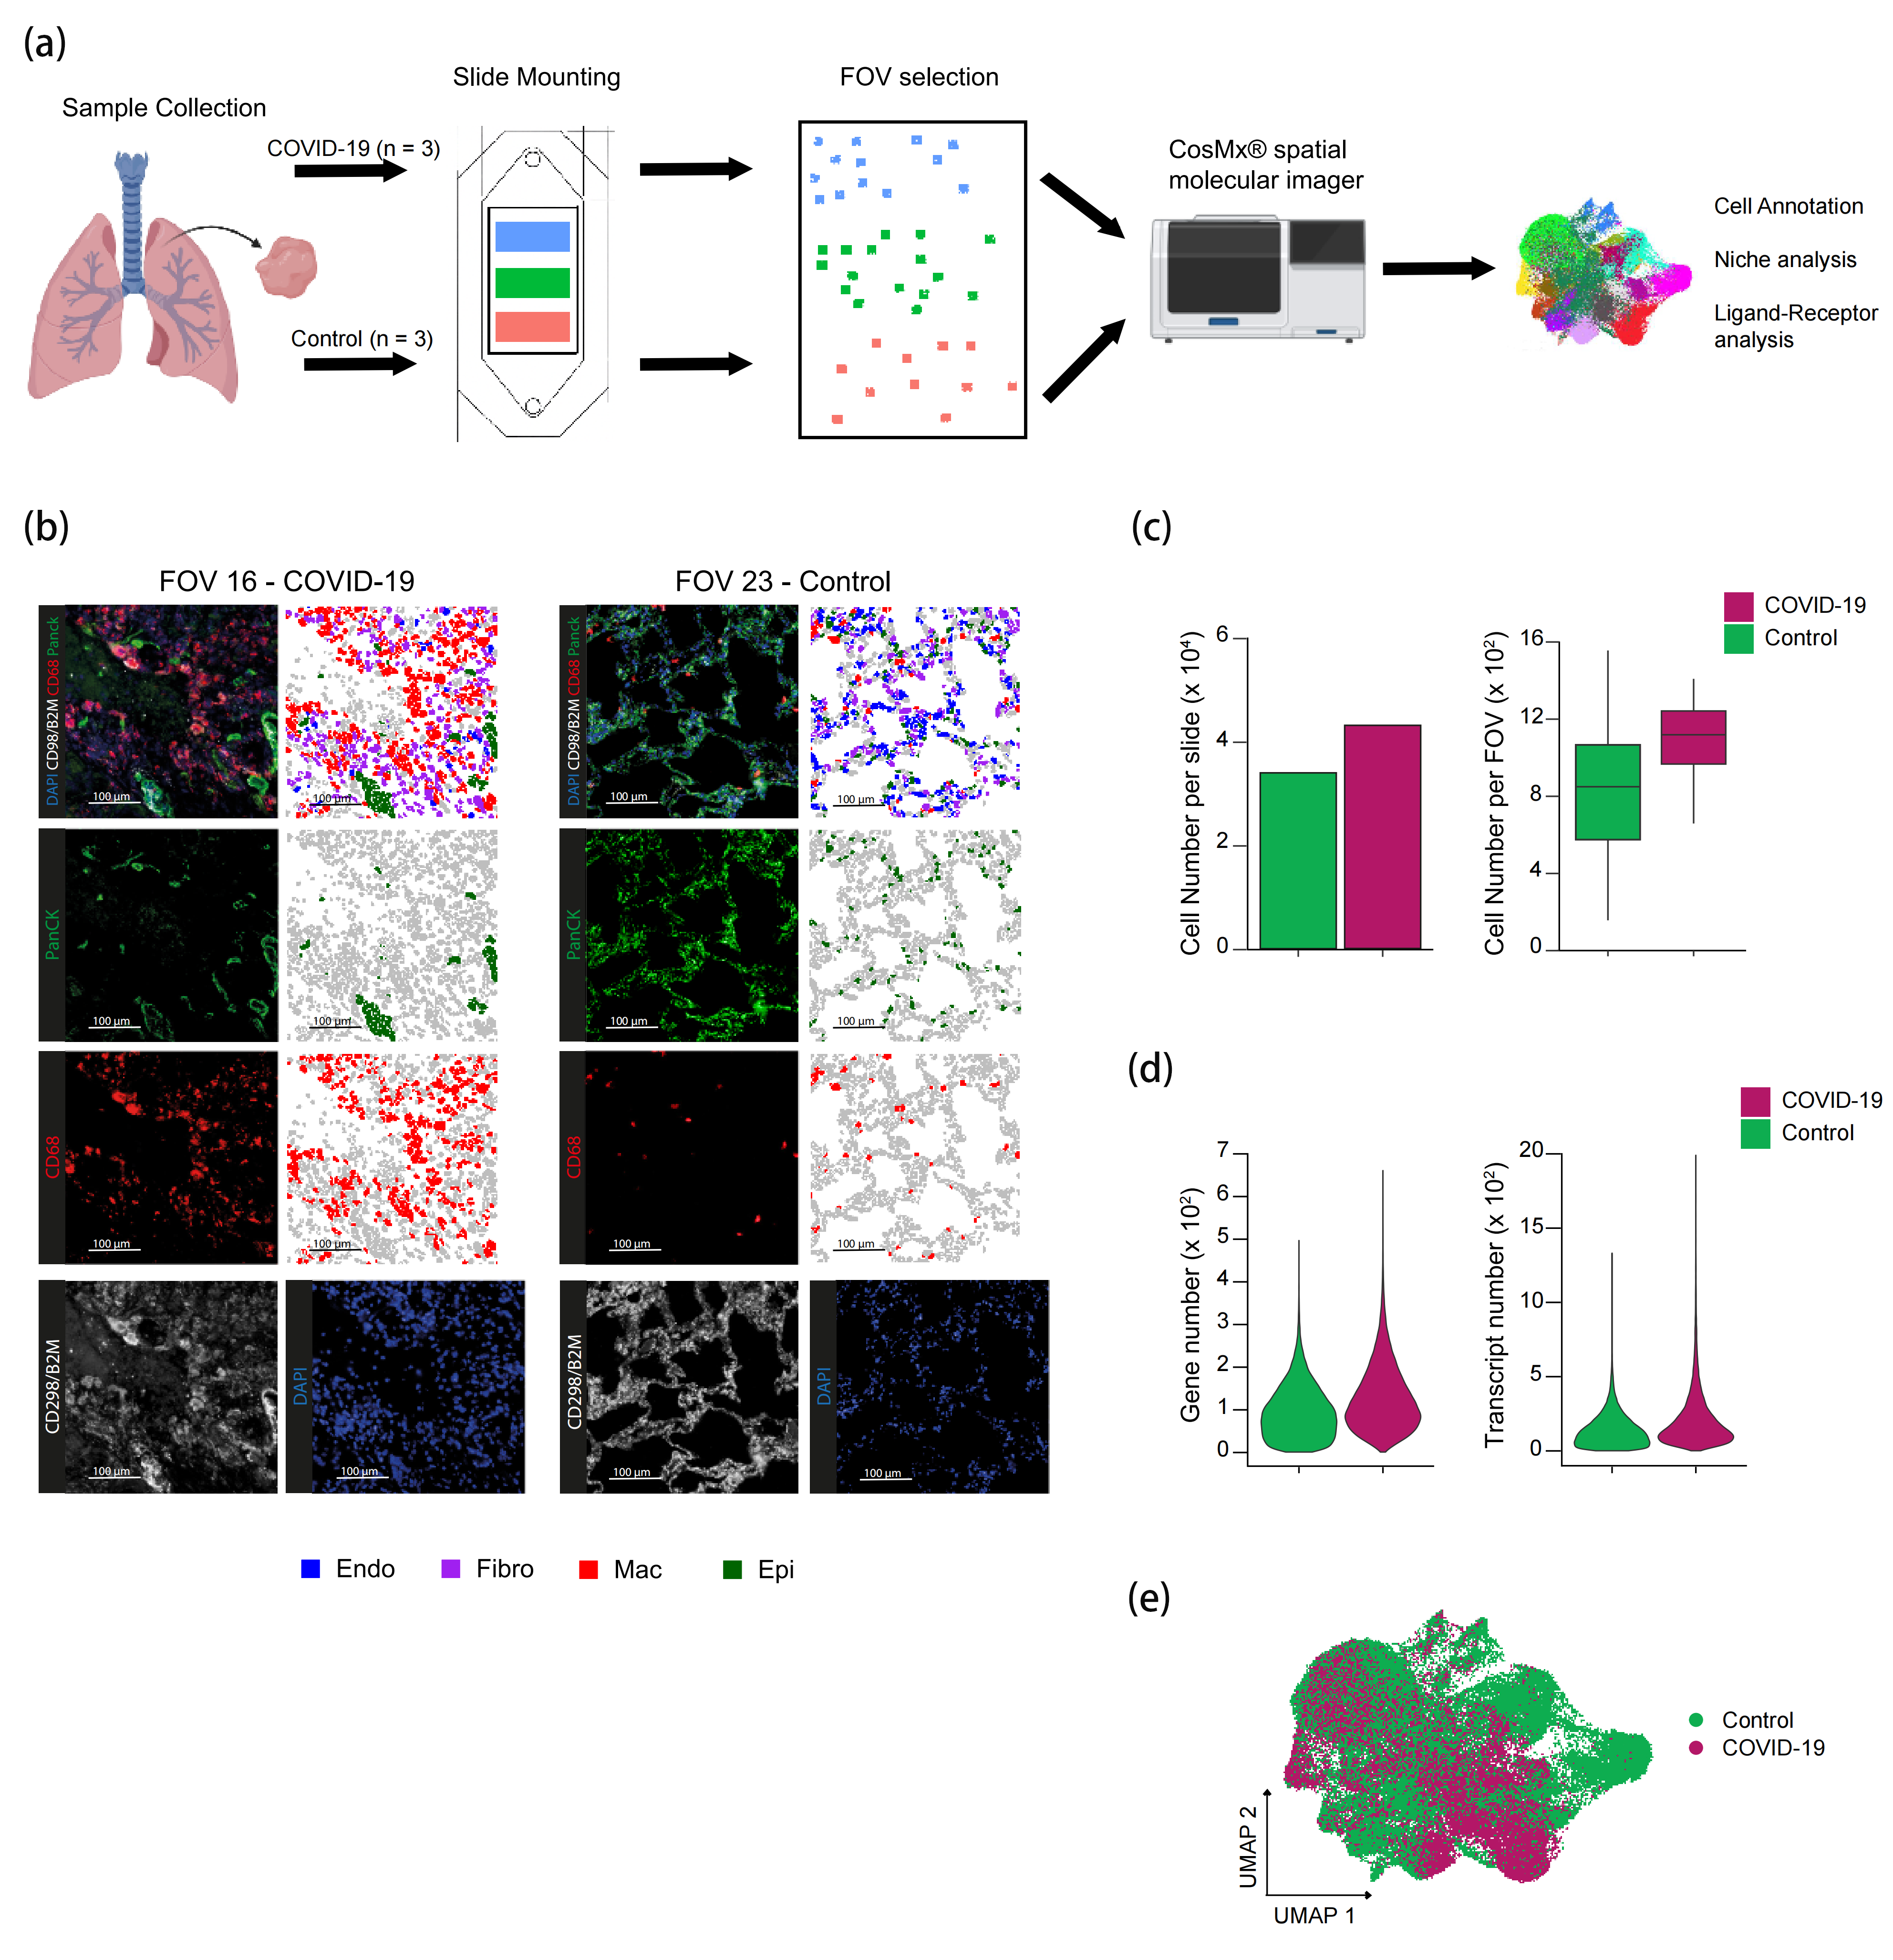
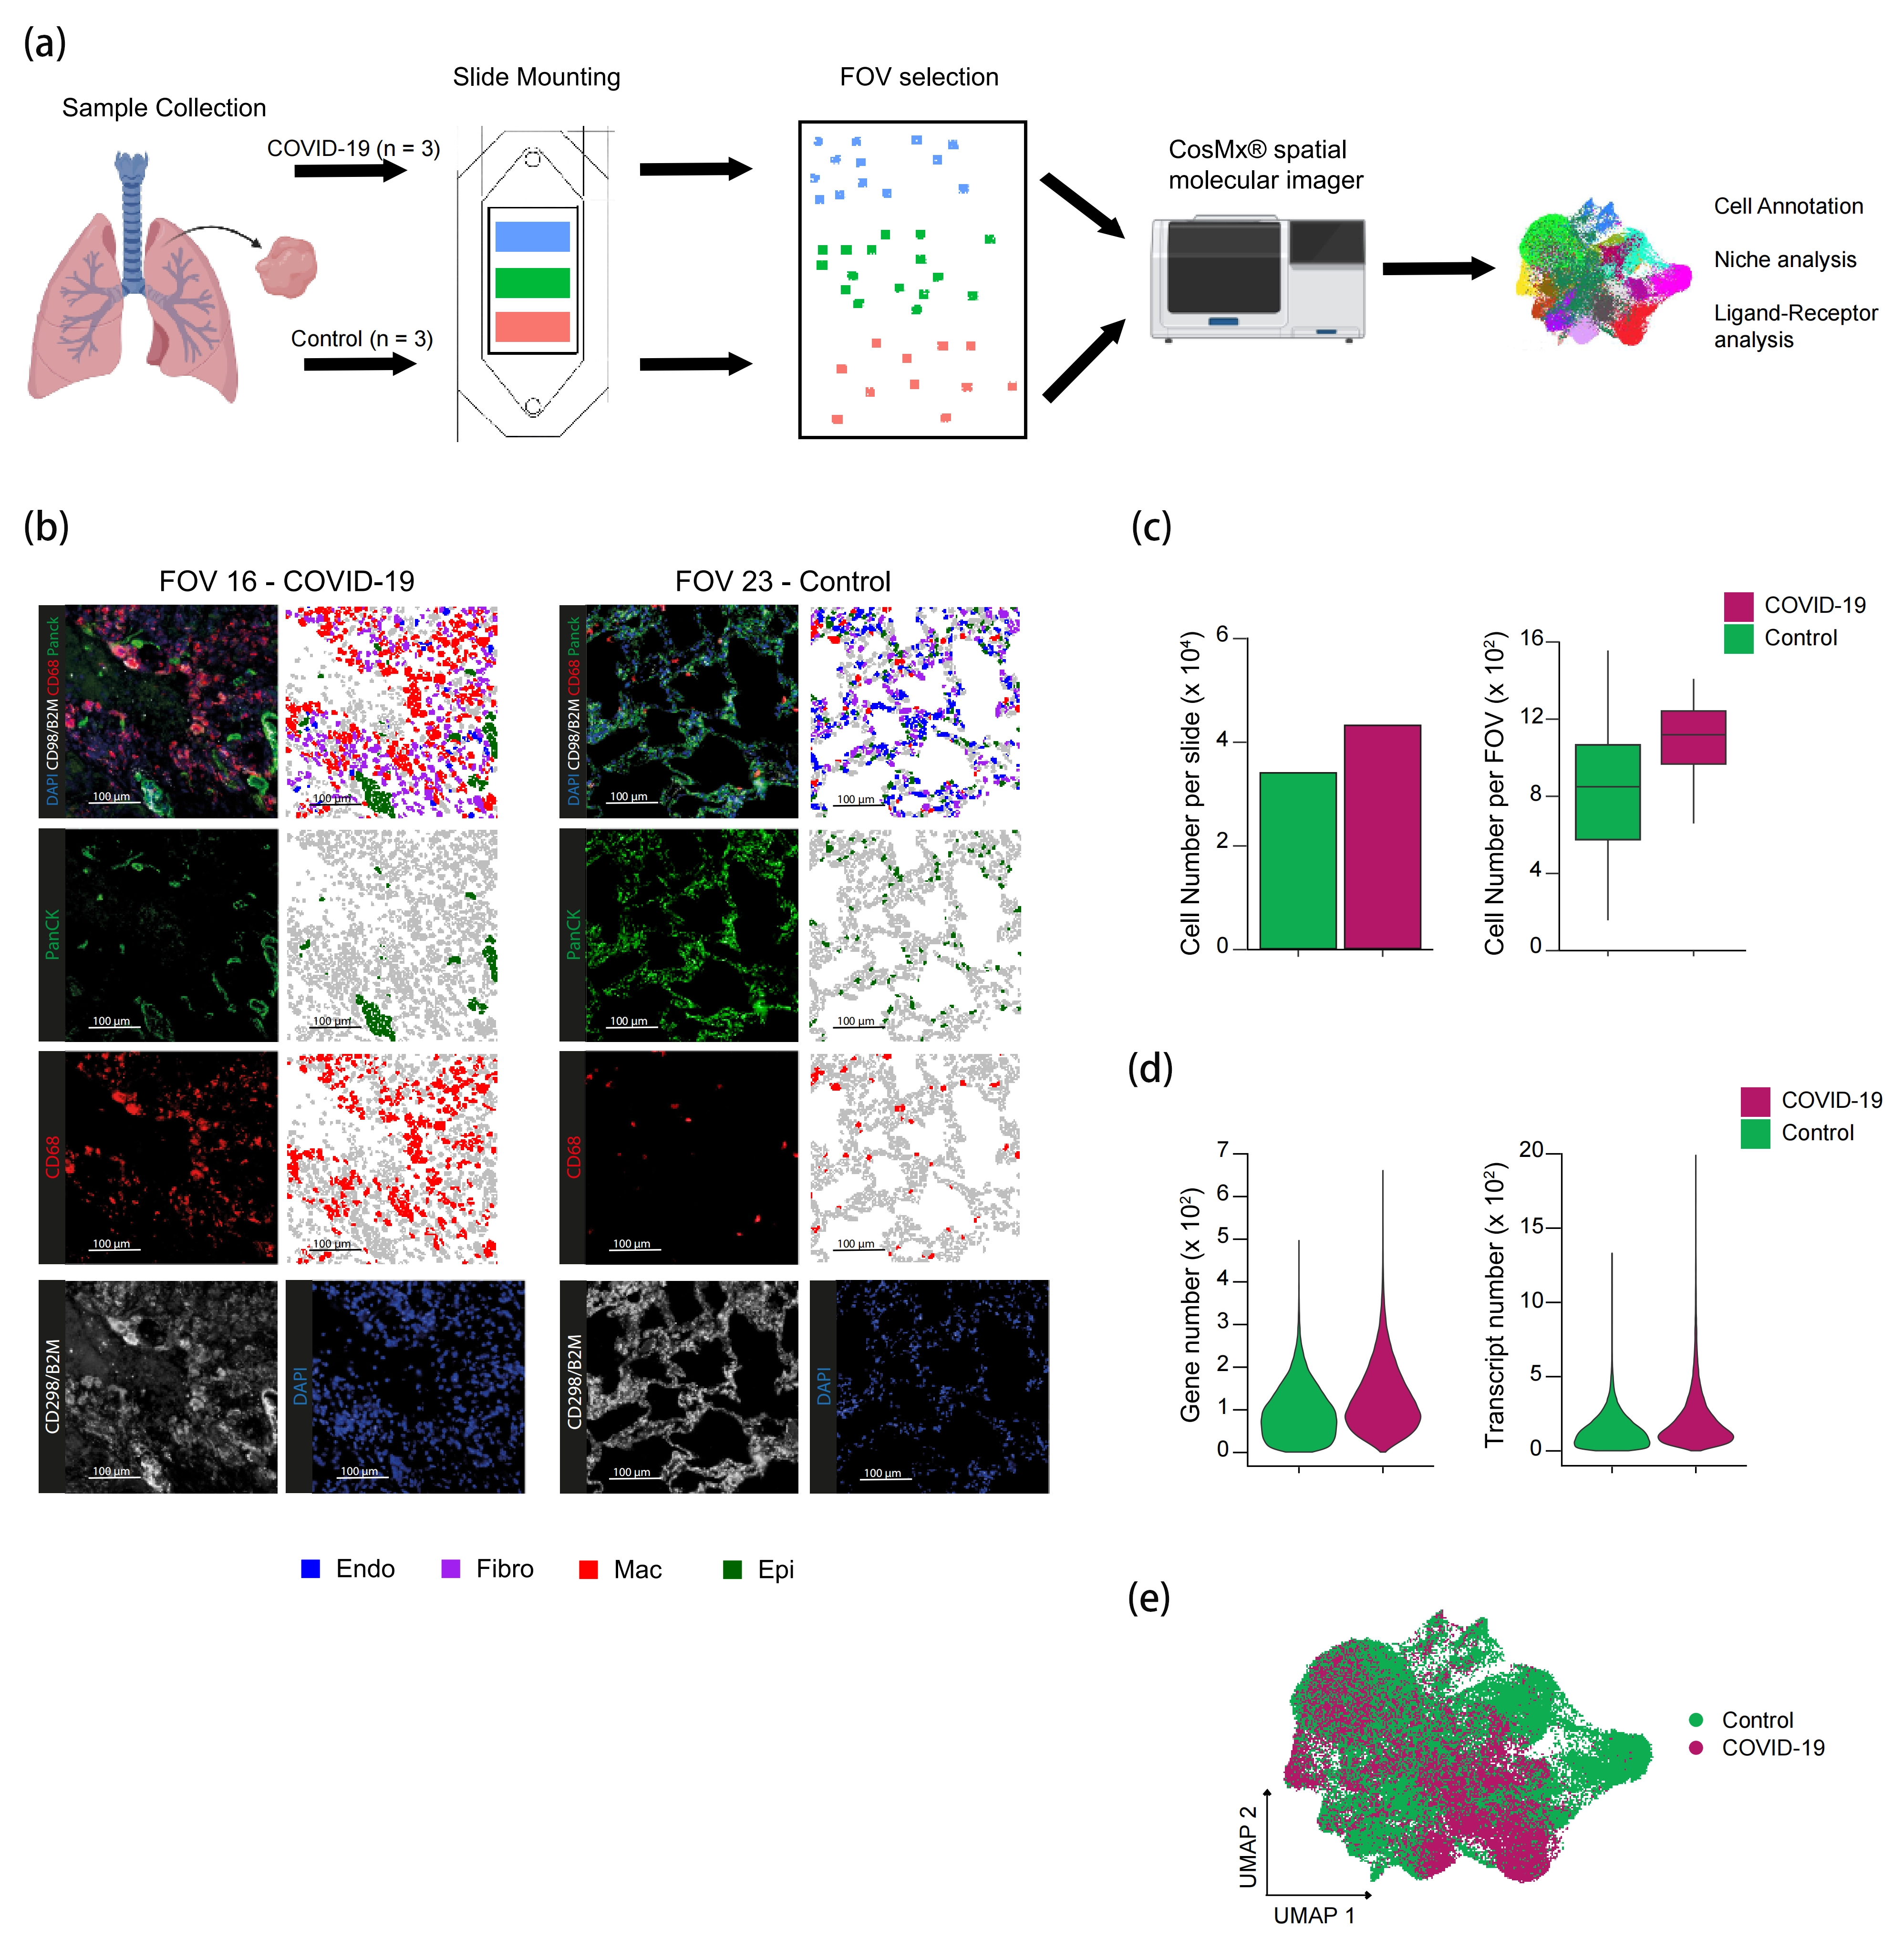
Figure 1. Overview of the experimental workflow, cell segmentation and QC metrics. (a) Schematic representation of the technical workflow, from post-mortem lung tissue collection to downstream analyses. All steps were carried out separately for COVID-19 and control samples before pooling of the data during downstream analyses; (b) Representative immunofluorescence images of FOV 16 from COVID-19 slide (left) and FOV 23 from Control slide (right), of nuclear stain DAPI (blue), cytoplasmic stain CD298/B2M (white), CD68+ macrophages (Mac, red) and pan-cytokeratin+ epithelial cells (Epi, green) present alongside the subsequent cellular annotation of FOV; (c) Cell numbers per condition represented by a barplot and cell numbers per FOVs within each condition represented by a boxplot; (d) Violin plots depicting gene and transcript numbers of each sample (width = abundance of cells); (e) UMAP plot of CosMx output. Endo: endothelial cells; Fibro: fibroblasts. FOV: field of view; COVID-19: coronavirus disease 2019; UMAP: Uniform Manifold Approximation and Projection; DAPI: 4’,6-diamidino-2-phenylindole.
Briefly, cyclic RNA readout using the SMI was performed as described[25] and the 1,000-plex CosMx Human Universal Cell Characterization Panel (NanoString) was used. For each slide, a total of 40 FOVs were randomly selected with the aim of maximizing spatial coverage across the slide. Within each FOV, cells were identified using a machine learning-based preprocessing pipeline, followed by segmentation with a pre-trained Cellpose neural network model (Figure 1b), and each detected transcript was assigned to its corresponding cell based on the segmentation map.
We detected a total of 33,925 Control and 43,048 COVID-19 cells, corresponding to 848 ± 351 and 1,076 ± 200 (mean ± SD) cells per FOV, respectively (Figure 1c). An average of 142 ± 112 and 214 ± 204 transcripts per cell were detected in Control and COVID-19 samples, respectively (Figure 1d). Following processing in Seurat (Figure S1), the 76,973 cells across 80 FOVs were integrated and visualized by Uniform Manifold Approximation and Projection (UMAP) (Figure 1e).
3.2 Cellular landscape of COVID-19 and control lung samples
Graph-based clustering identified 20 cell populations, which were annotated based on marker gene expression, reference mapping to the HLCA[30] and, when required, GO analysis (Figure 2a,b,c and Figures S1,S2,S3). To facilitate manual cluster annotation, we first filtered and subset cells with the highest amounts of transcripts (> 250 transcripts) and genes (> 100 genes), which were then re-integrated to the global dataset (Figures S1,S2).
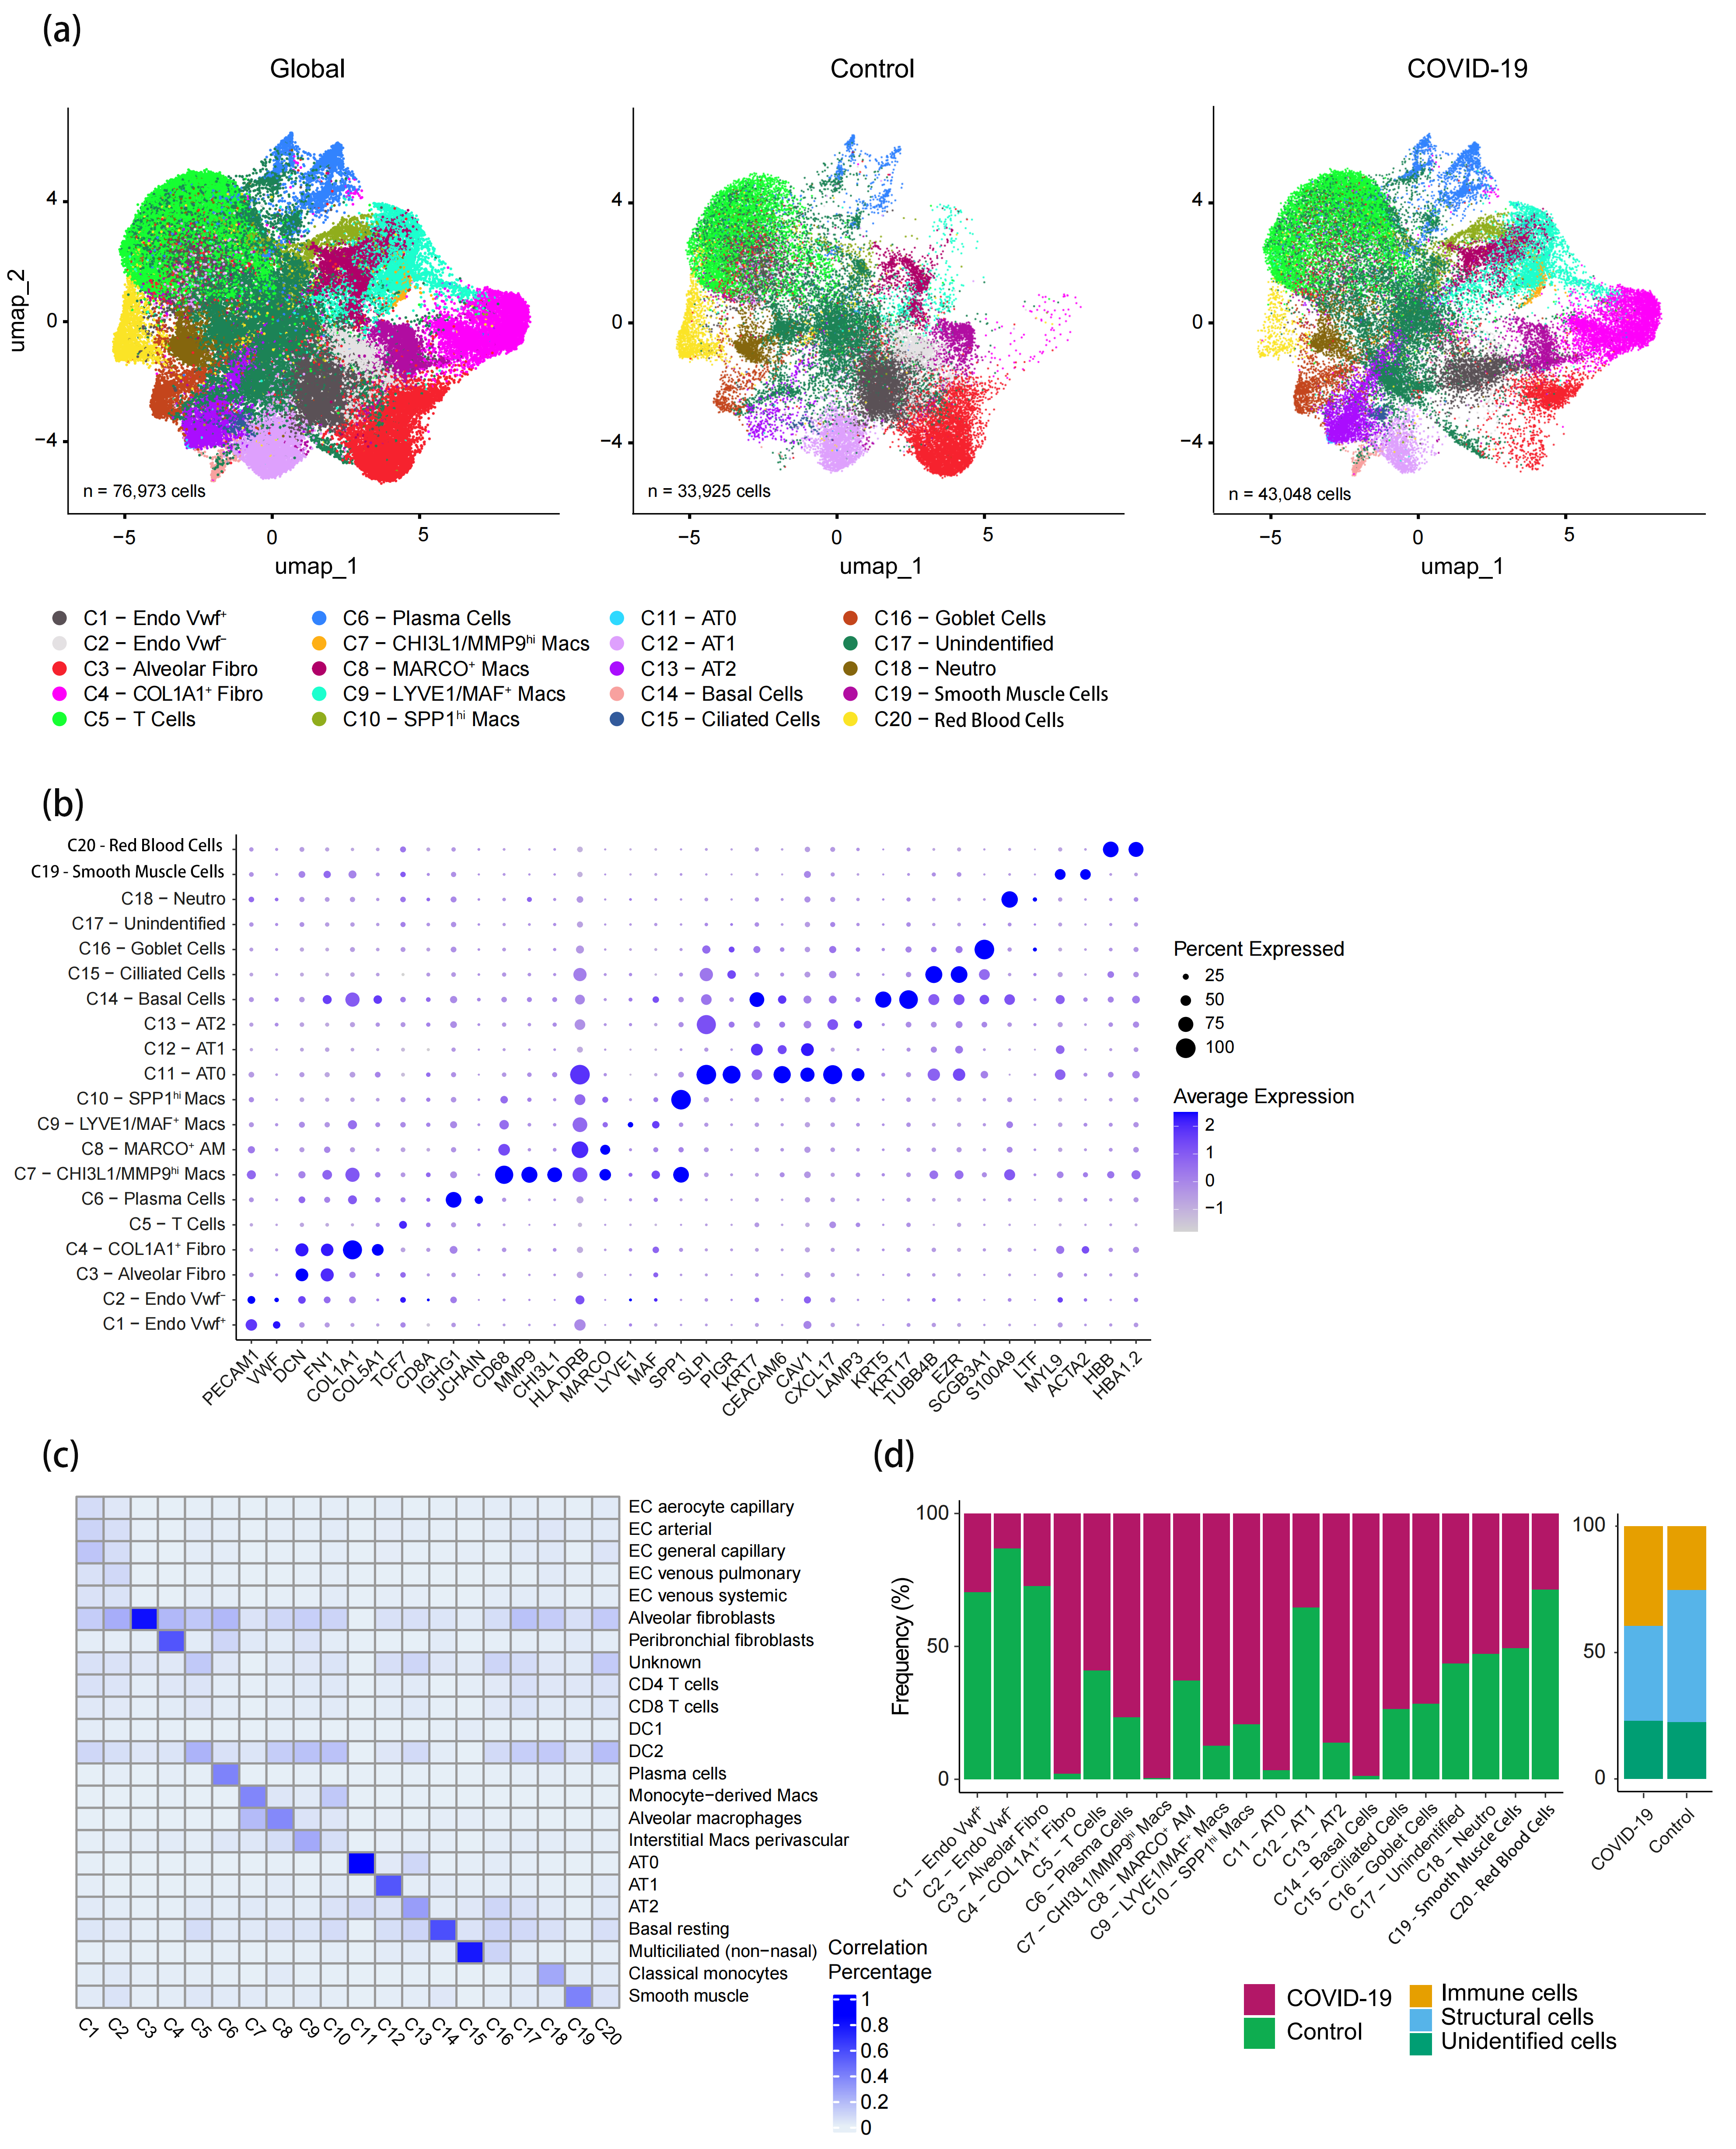
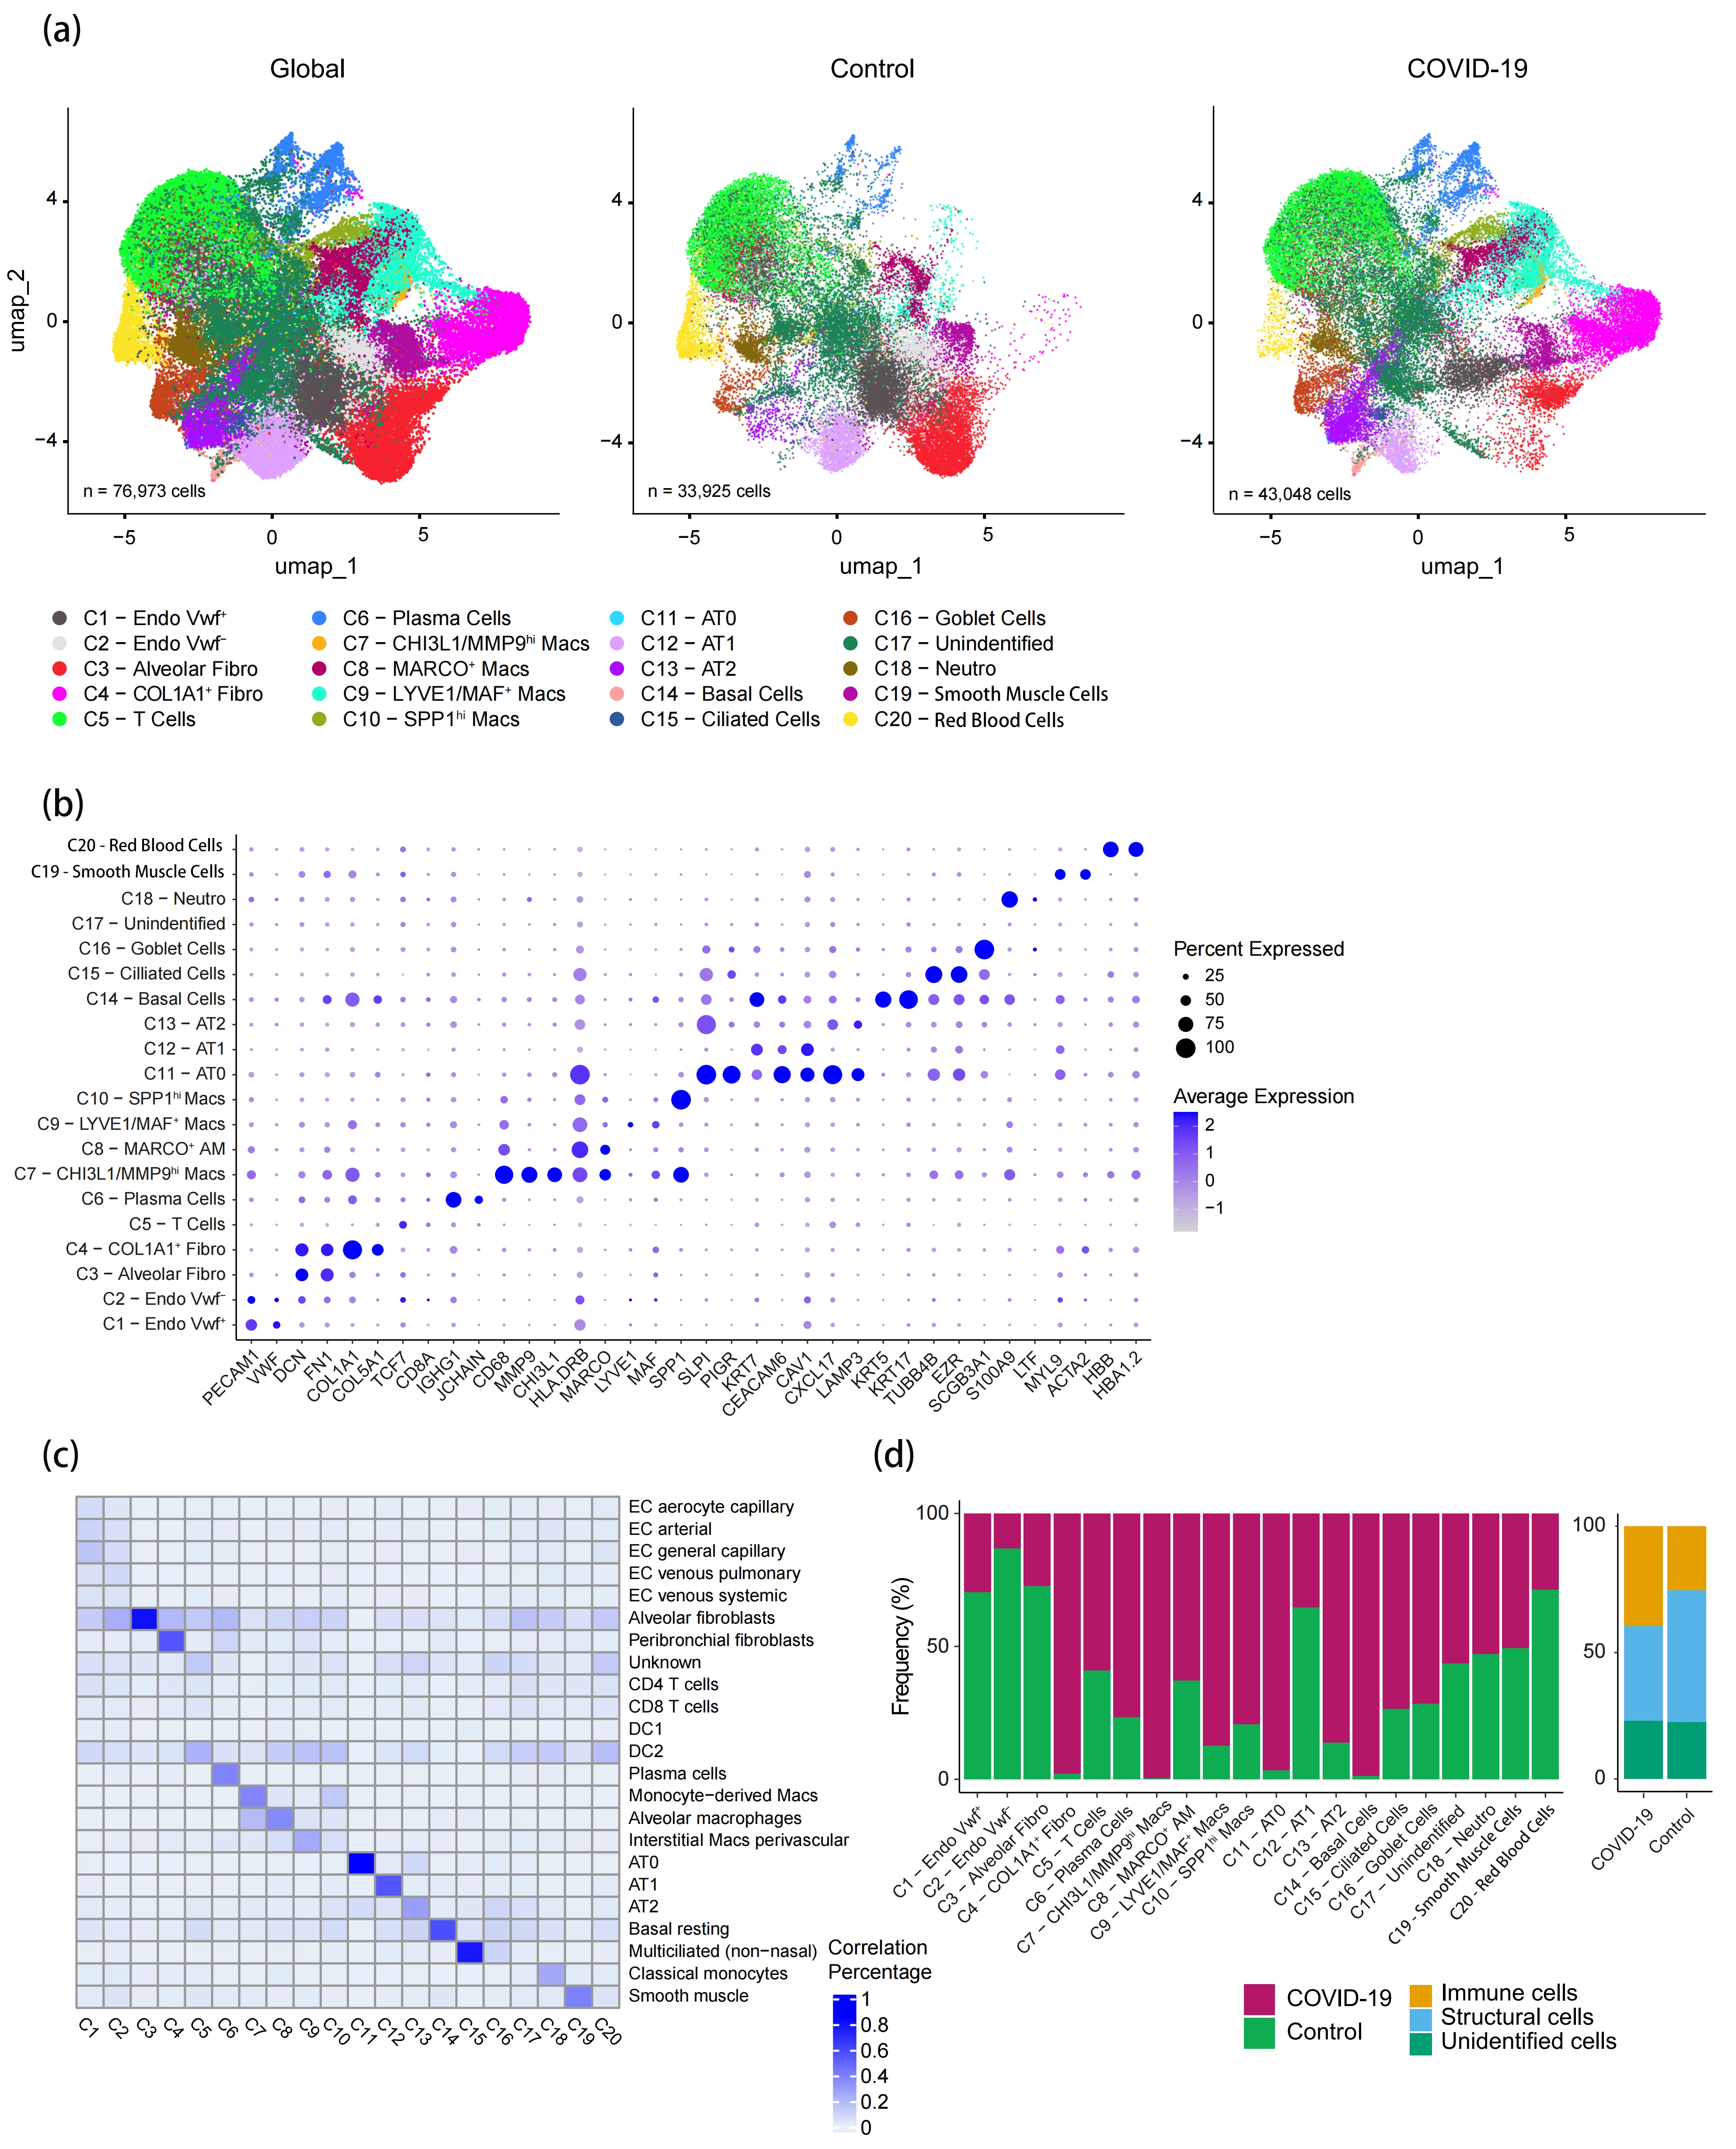
Figure 2. Annotation of cell populations. (a) UMAP plot of CosMX SMI output including cells from COVID-19 and Control samples. Cells are colored according to their annotated identity; (b) Dotplot showing average expression of the indicated genes and the percentage of cells expressing the genes within each cluster; (c) Correlation matrix showing the percentage of cells of manually annotated clusters overlapping with each automatic reference-based annotation; (d) Histogram showing the frequency of COVID-19 and Control condition within each annotated cell population (left) and showing the frequency of cell categories in each condition (right). COVID-19: coronavirus disease 2019; CosMX SMI: CosMx spatial molecular imager; UMAP: Uniform Manifold Approximation and Projection; Endo: endothelial cells; COL1A1+: collagen type I alpha 1 chain; MMP9hi: matrix metalloproteinase 9; CHI3L1: chitinase 3-like 1; MARCO+: macrophage receptor with collagenous structure.
Clusters 1 and 2 (C1 and C2) expressed PECAM1 and were annotated as endothelial cells (Endos). Notably, C1 showed higher expression of VWF compared to C2. C3 and C4 were identified as fibroblasts (Fibros) based on the expression of canonical markers such as DCN and FN1 (Figure 2b). Most cells in C3 were annotated as alveolar Fibros by reference-based annotation (Figure 2c). In contrast, Fibros in C4 overexpressed collagen-related genes, including COL1A1 and COL5A1, and were annotated as COL1A1+ Fibros. C5 was annotated as T lymphocytes (T cells) based on the expression of lineage-specific genes such as TCF7 and CD8A (Figure 2b), associated with the enrichment of T cells-associated responses (Figure S3). C6 was identified as plasma cells based on IGHG1 and JCHAIN expression, which was confirmed by reference-based annotation. Cells in C7-C10 were annotated as macrophages (Macs) based on expression of the canonical macrophage marker CD68 (Figure 2b). C7 was characterized by high levels of CHI3L1 and MMP9 and was labelled CHI3L1/MMP9hi Macs. C8 was annotated as macrophage receptor with collagenous structure (MARCO+) AM, given the expression of MARCO, an AM-specific gene[35]. Macs in C9 expressed high levels of MAF and LYVE1, markers classically associated with interstitial Macs (IMs)[36,37]. C10 was characterized by elevated expression of SPP1 and was labeled SPP1hi Macs (Figure 2b). Both C7 and C10 were mapped to monocyte-derived Macs (Figure 2c), suggesting a hematopoietic origin. C11-C13 exhibited high expression of epithelial markers such as SLPI and CAV1 and were annotated as AT0, AT1, and AT2 cells, respectively, based on reference-based classification (Figure 2c). C14 was identified as basal cells (KRT5 and KRT17). C15 was identified as ciliated cells based on EZR and TUBB4B expression[38,39]. C16 was identified as SCGB3A1-expressing goblet cells. C18 was labelled as neutrophils based on LTF and S100A9 expression[40,41], which was confirmed by GO analysis (Figure 2b and Figure S3). C19 encompassed smooth muscle cells (ACTA2 and MYL9) and C20 expressed high levels of hemoglobin-related genes (HBB, HBA1 and HBA2). Hence, these cells were considered as red blood cells (RBC) (Figure 2a). The remaining cells in C17 were considered unidentified, as they did not express any markers specific for a given cell type and were not annotated by reference-based annotation.
Cellular composition differed markedly between COVID-19 and Control samples (Figure 2d). COVID-19 lungs showed an enrichment of immune cells (39% in COVID-19 vs. 25% in Control), together with expansion of several epithelial populations and COL1A1+ fibroblasts (Figure 2d). Overall, 33.2% of cells were immune cells and 44.1% were structural cells, while 22.7% remained unannotated.
3.3 Histopathology and spatial transcriptomics reveal distinct pathological states
Given the limited cohort size and the spatial heterogeneity of COVID-19 lung pathology[42,43], we first characterized the histopathological features of each analyzed tissue section rather than performing broad comparisons between COVID-19 and Control groups.
H&E-stained serial sections were evaluated by a trained pathologist (Table 2). Control samples already displayed some histological alterations, including interstitial pneumonia, alveolar edema and air trapping (Table 3 and Figure S4).
Table 2. Histopathological features of COVID-19 lung sections.
| Histological Features | COVID-19 #1 | COVID-19 #2 | COVID-19 #3 |
| Type of Pneumonia | Interstitial, moderate, chiefly lymphoplasmacytic and histiocytic | Interstitial, moderate, uneven, chiefly lymphoplasmacytic | Interstitial, moderate, chiefly lymphoplasmacytic and histiocytic |
| Fibrosis | Mild, diffuse. Score 1 | Severe, diffuse, at different stages, mostly active. Score 3 | Mild, interstitial, uneven in distribution. Score 1 |
| Hemorrhages | Multiple foci of hemorrhage | Severe congestion with multifocal hemorrhages | Small multifocal hemorrhages |
| Alveolar compartment | Diffuse alveolar damage | - | Type II cell hyperplasia and/or bronchiolization |
| Bronchiolar Remodeling | - | Present, with frequent squamous differentiation | Fibrin/mucus bronchiolar plugs |
| Immune infiltration | Severe lymphoplasmacytic and histiocytic Moderate hyperplasia of alveolar macrophages | Moderate Lymphoplasmacytic Moderate hyperplasia of alveolar macrophages, giant cell formation | Severe lymphoplasmacytic and histiocytic Severe hyperplasia of alveolar macrophages |
COVID-19: coronavirus disease 2019.
Table 3. Histopathological characterization of Control samples.
| Control-1 | Control-2 | Control-3 | |
| Histological characterization | Mild to moderate lymphoplasmacytic and histiocytic interstitial pneumonia. Severe pulmonary congestion. Multifocal atelectasis. Minimal to mild pulmonary fibrosis. Score 1 | Severe pulmonary congestion. Mild mixed, chiefly lymphocytic, interstitial pneumonia. Score 0 | Moderate to focally severe alveolar edema. Air trapping. Moderate emphysema. Score 0 |
COVID-19 samples showed markedly different histopathological features, particularly in terms of alveolar damage, bronchiolar remodeling and immune infiltration (Table 2). COVID-19 #1 displayed features consistent with an acute phase of infection and lung injury, whereas COVID-19 #2 showed a more advanced, chronic pattern characterized by extensive fibrosis. COVID-19 #3 showed an intermediate pathological pattern with milder fibrosis and prominent immune infiltration (Figure 3a and Table 2). These distinct profiles are consistent with the heterogeneous pathological states described during the evolution of COVID-19-associated lung injury[6].
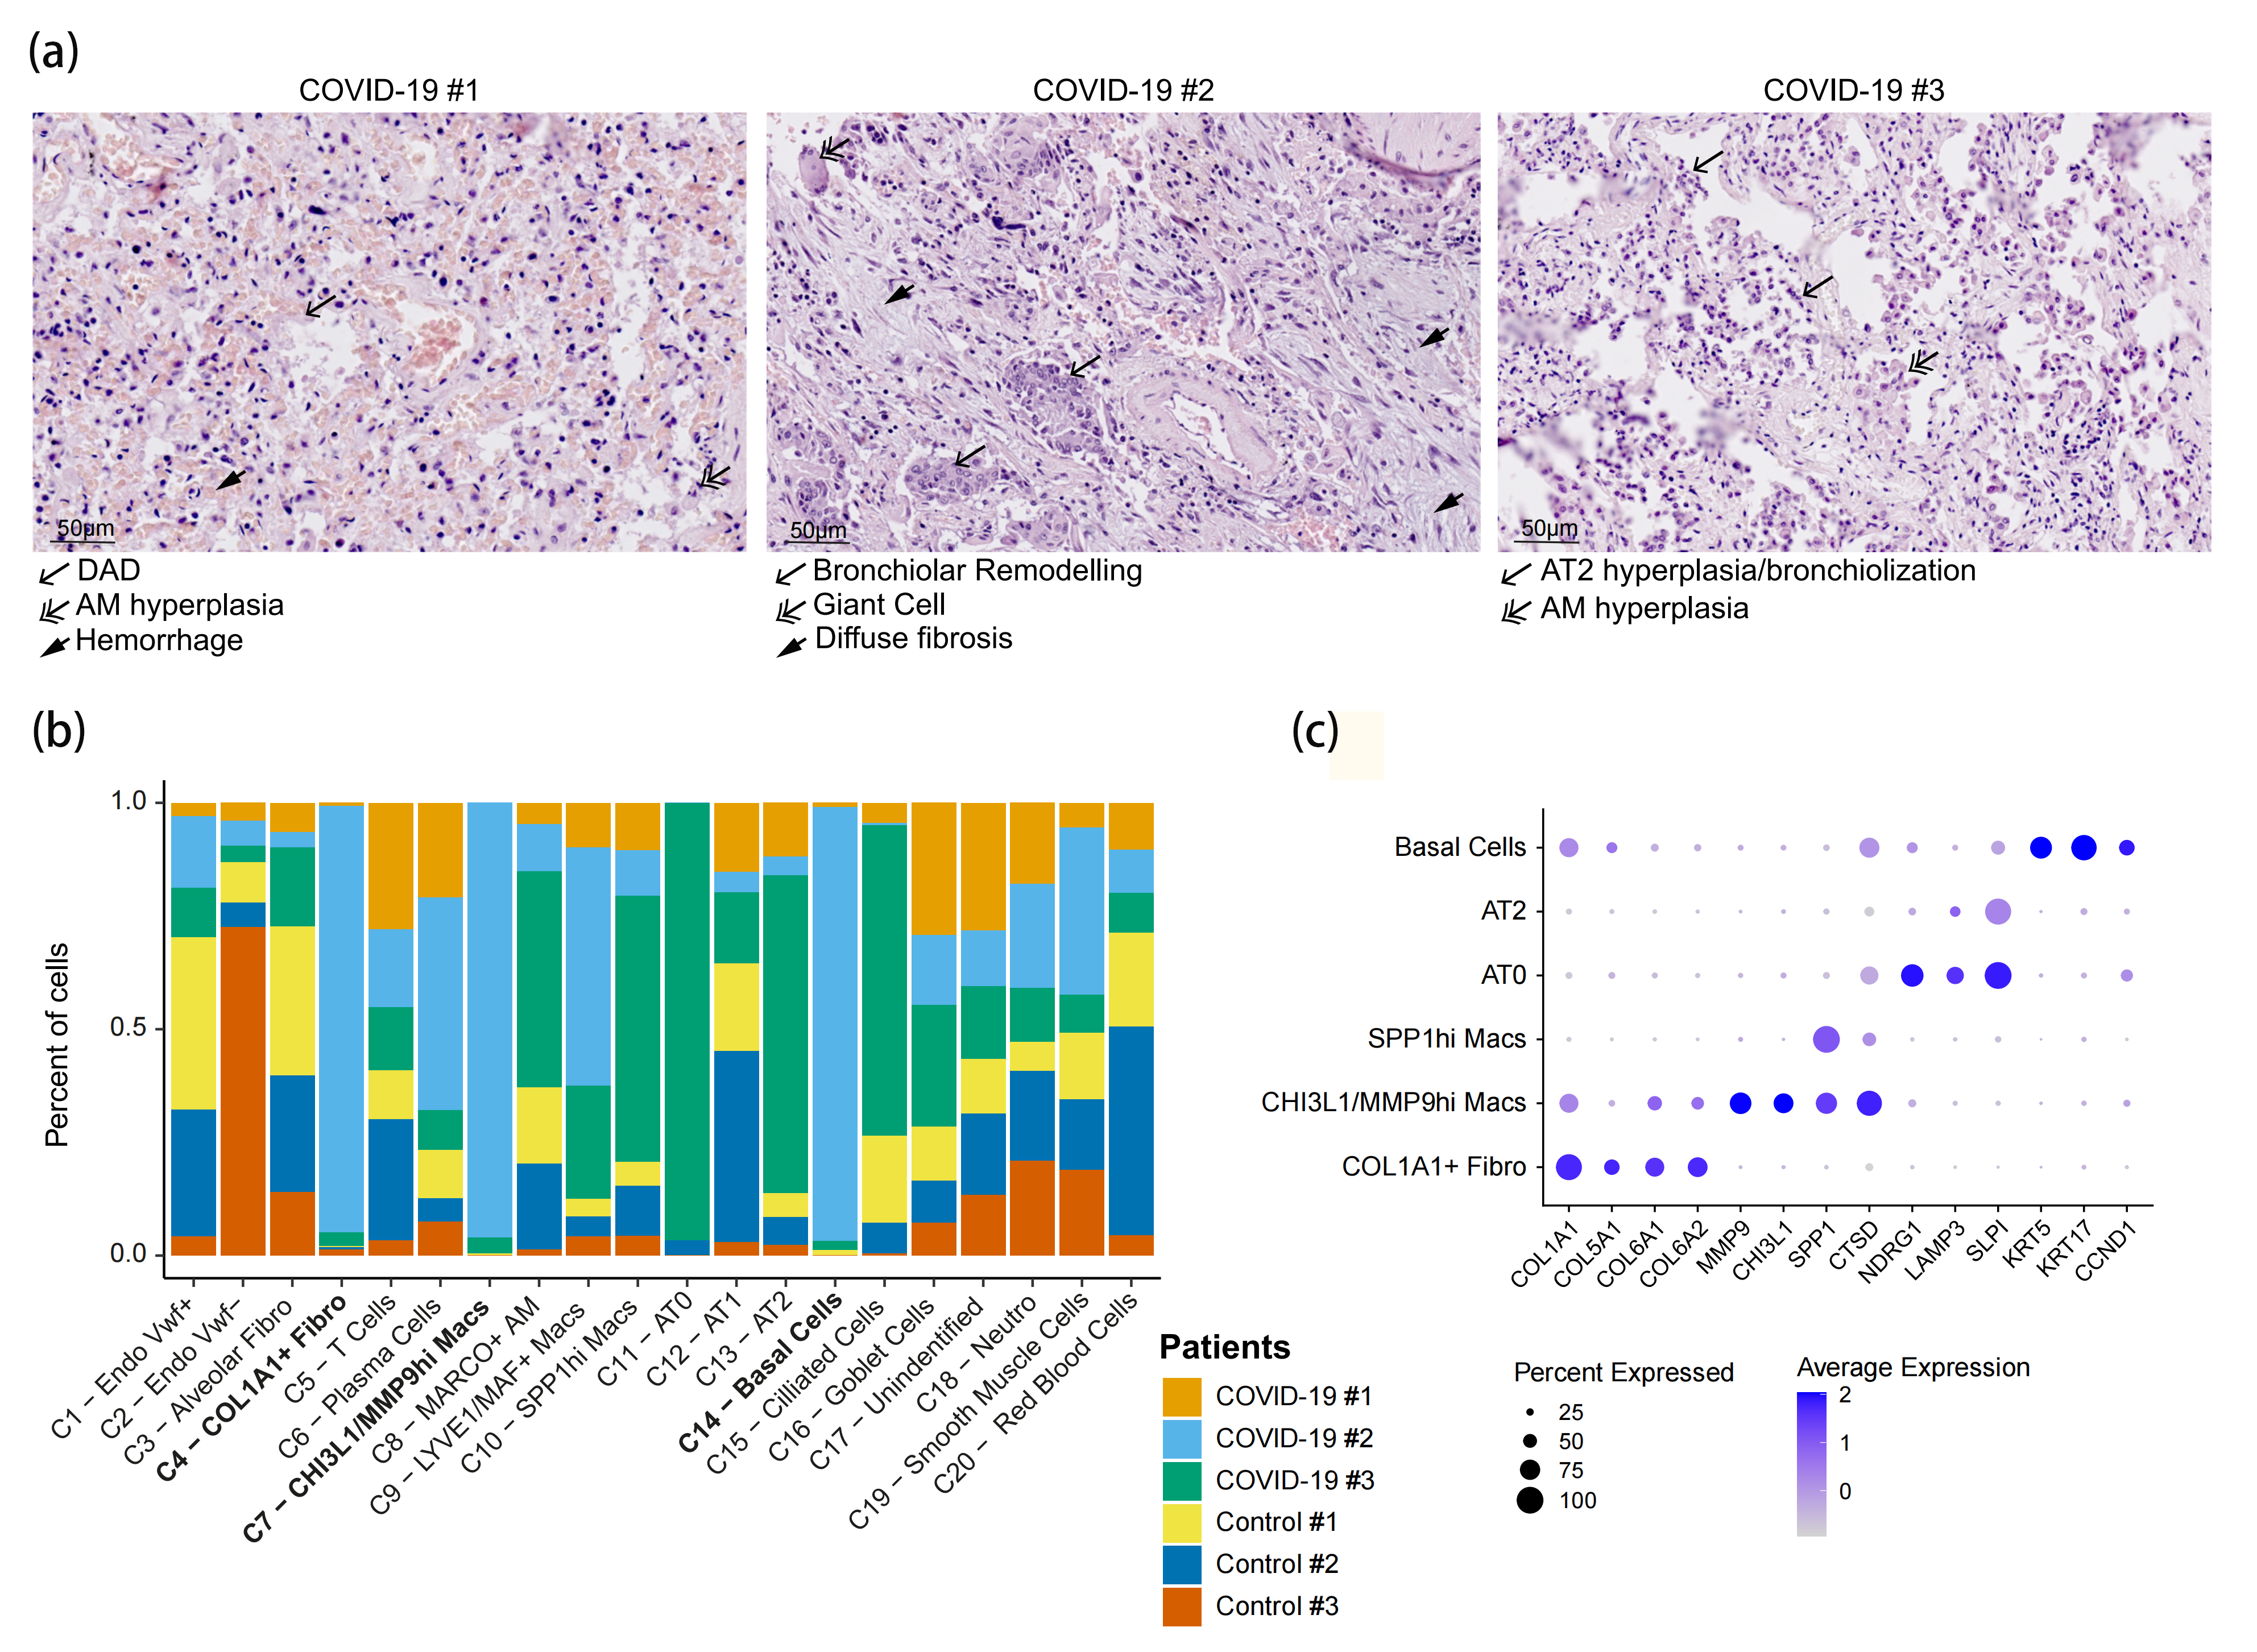
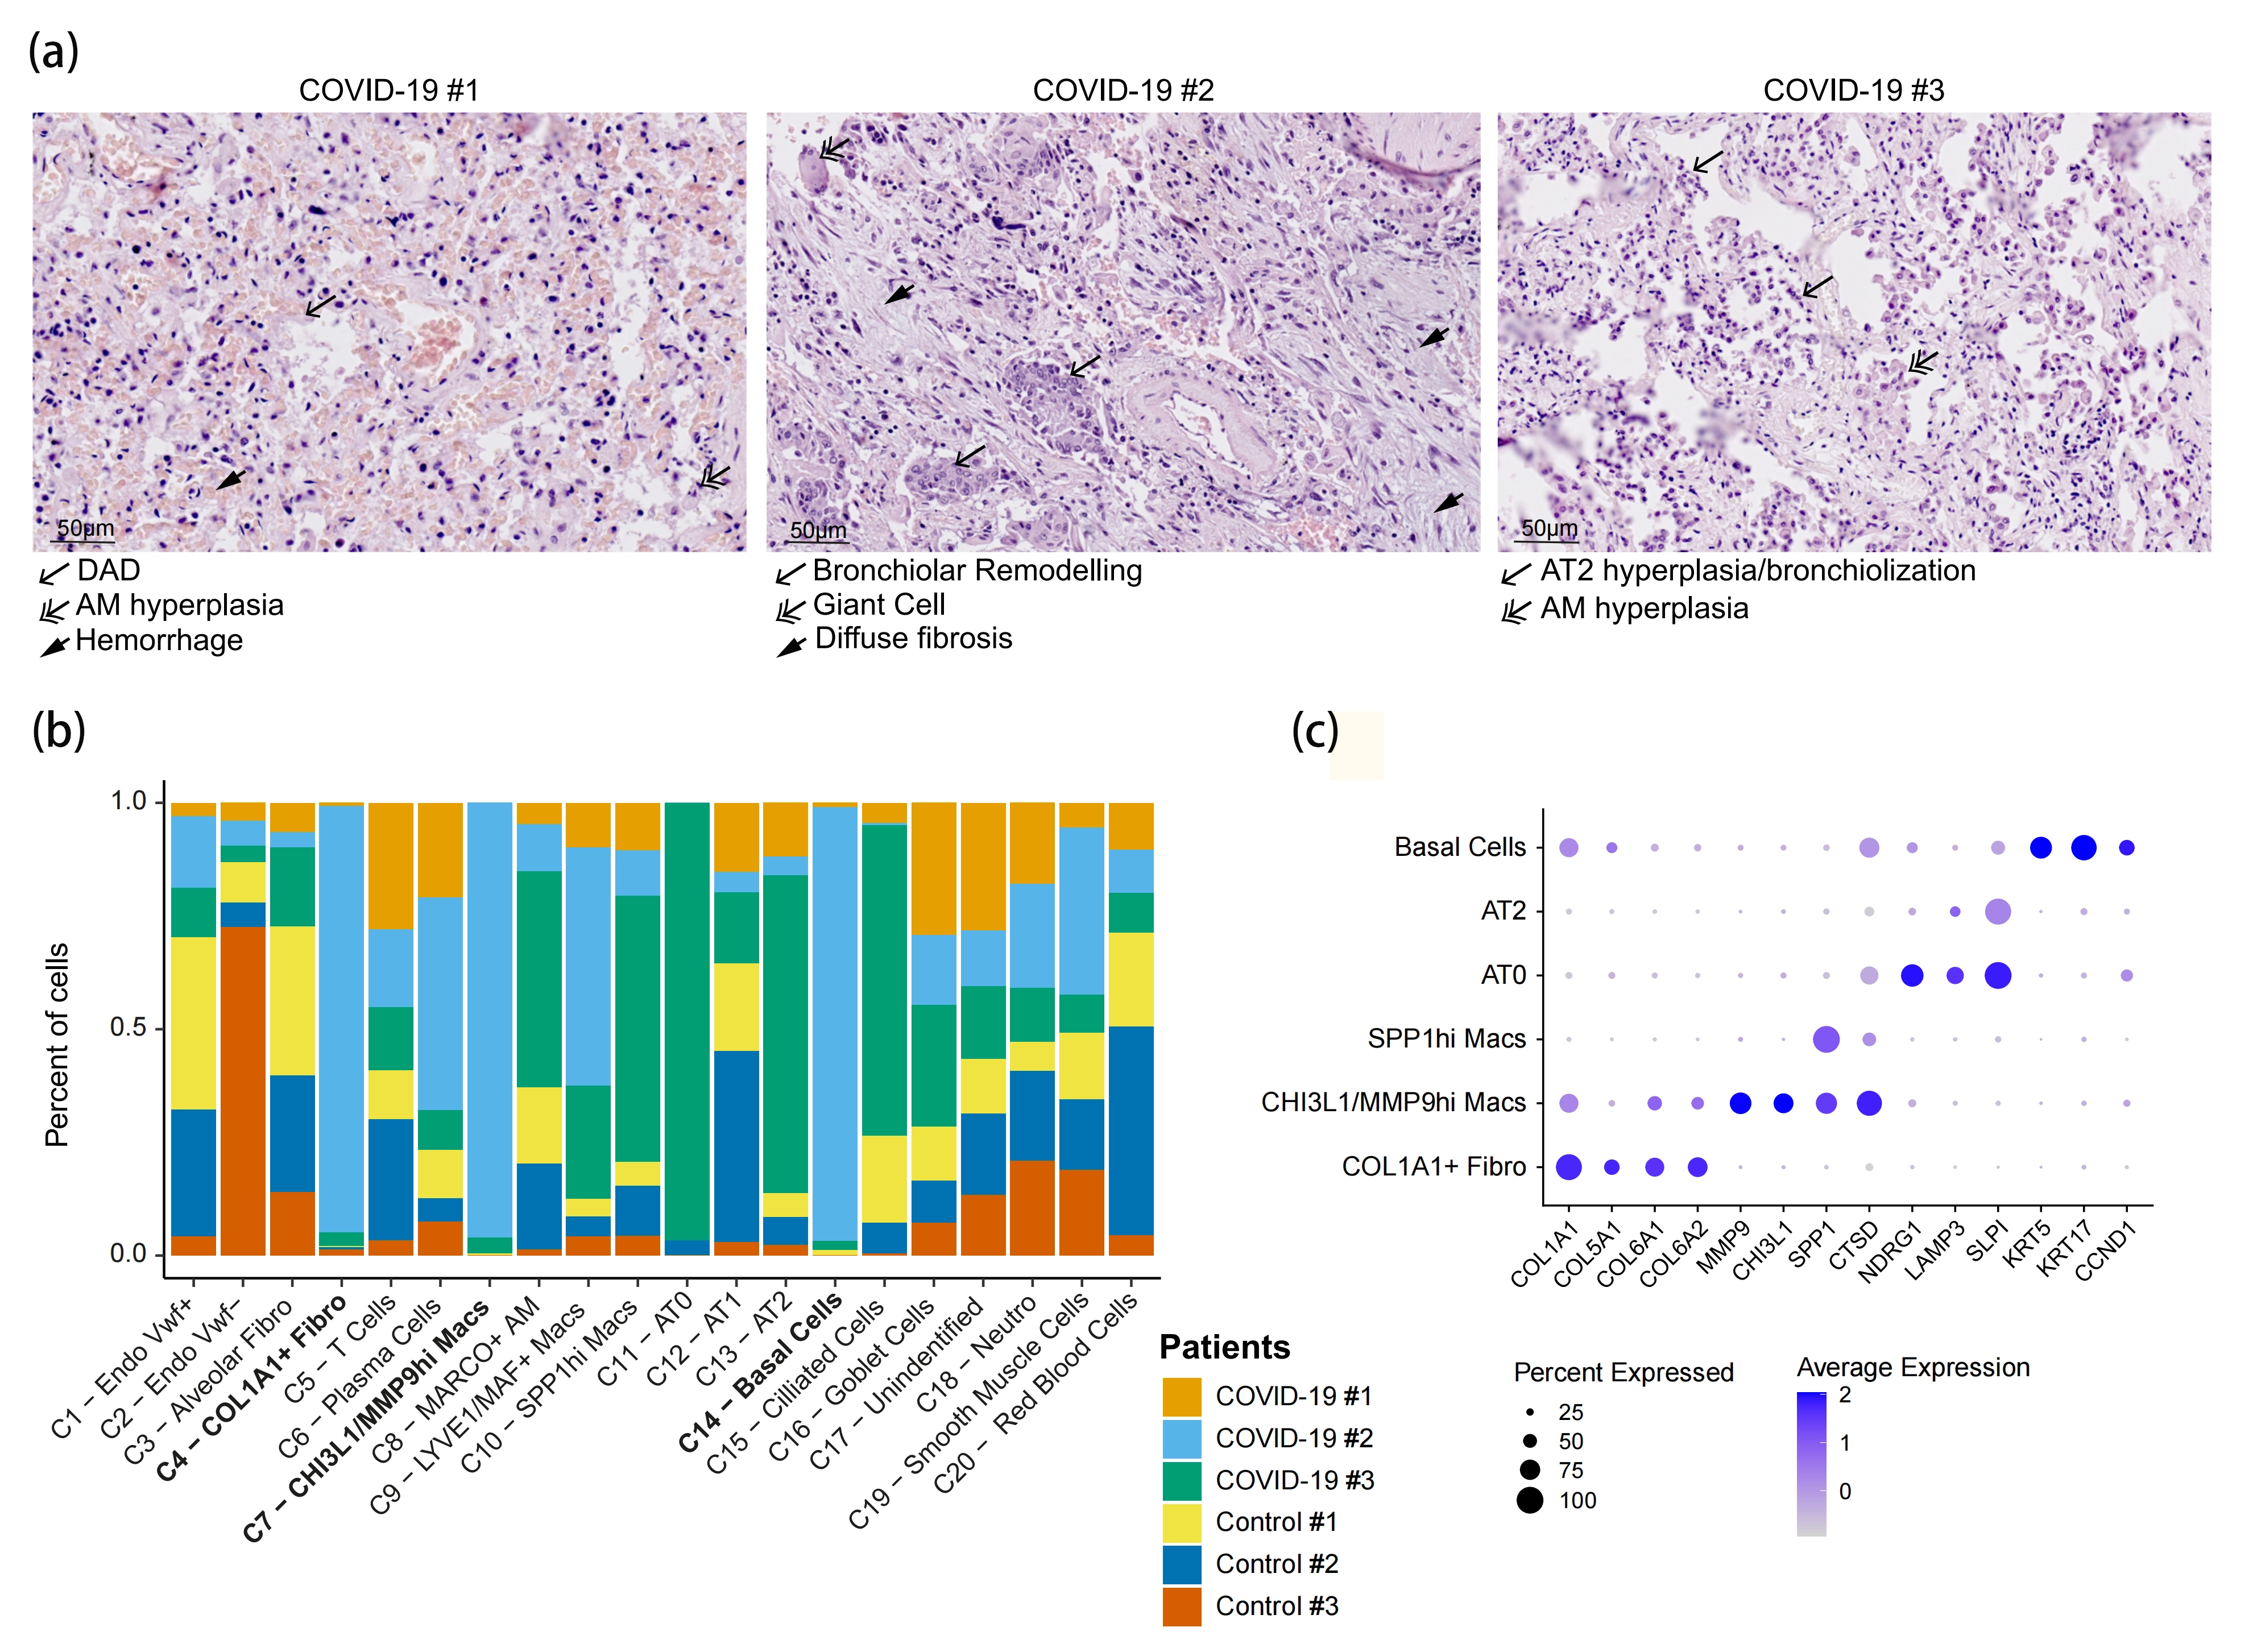
Figure 3. Marked inter-patient heterogeneity in histopathological features and cellular composition in COVID-19 lung samples. (a) Annotations of main histopathological features in H&E lung sections from COVID-19 patients; (b) Histogram depicting the proportion of all samples in each annotated cell population; (c) Dotplot showing average expression of the indicated genes and the percentage of cells expressing the genes within each cell type. COVID-19: coronavirus disease 2019; DAD: diffuse alveolar damage; Endo: endothelial cells; AM: alveolar macrophage; MARCO+: macrophage receptor with collagenous structure; COL1A1+: collagen type I alpha 1 chain; Fibro: fibroblasts; SPP1hi: secreted phosphoprotein 1; CHI3L1: chitinase 3-like 1; MMP9hi: matrix metalloproteinase 9.
Spatial transcriptomic analysis further revealed cell populations preferentially associated with these histopathological states. Three clusters were almost exclusively associated with the COVID-19 #2 sample characterized by severe fibrosis: COL1A1+ fibroblasts, expressing high levels of extracellular matrix (ECM)-related genes; CHI3L1/MMP9hi macrophages, and KRT5+/KRT17+ basal cells expressing high levels of cell-cycle activation gene CCND1 (Figure 3b,c and Figure S5). Notably, CHI3L1/MMP9hi macs and basal cells were relatively rare in the CosMx output (214 and 274 cells) compared with other populations. In contrast, clusters such as AT0, AT2, SPP1hi macrophages, and ciliated cells were overrepresented in the COVID-19 #3 sample (Figure 3b,c).
3.4 Distinct cellular niches characterize COVID-19 pathological states
To identify cellular microenvironments associated with distinct histopathological states, we performed an unbiased cellular neighborhood analysis, which identified 10 niches (N1-N10) (Figure 4a). Several niches (N2, N4, N6, N7, N9) were predominantly composed of structural cells and were either enriched in Control samples (N4, N7, N9) or shared across conditions (N2, N6). N2 was enriched in basal, goblet, and ciliated cells and localized around airway structures, whereas N6, enriched in smooth muscle cells, was mainly associated with airways and blood vessels (Figure 4). N8 was enriched in immune cells, including T cells, neutrophils, and plasma cells, and was markedly expanded in COVID-19 #1, consistent with its acute inflammatory phenotype (Figure 4a,b). Niche distributions also varied among Control samples, further highlighting inter-individual tissue heterogeneity (Figure 4b).
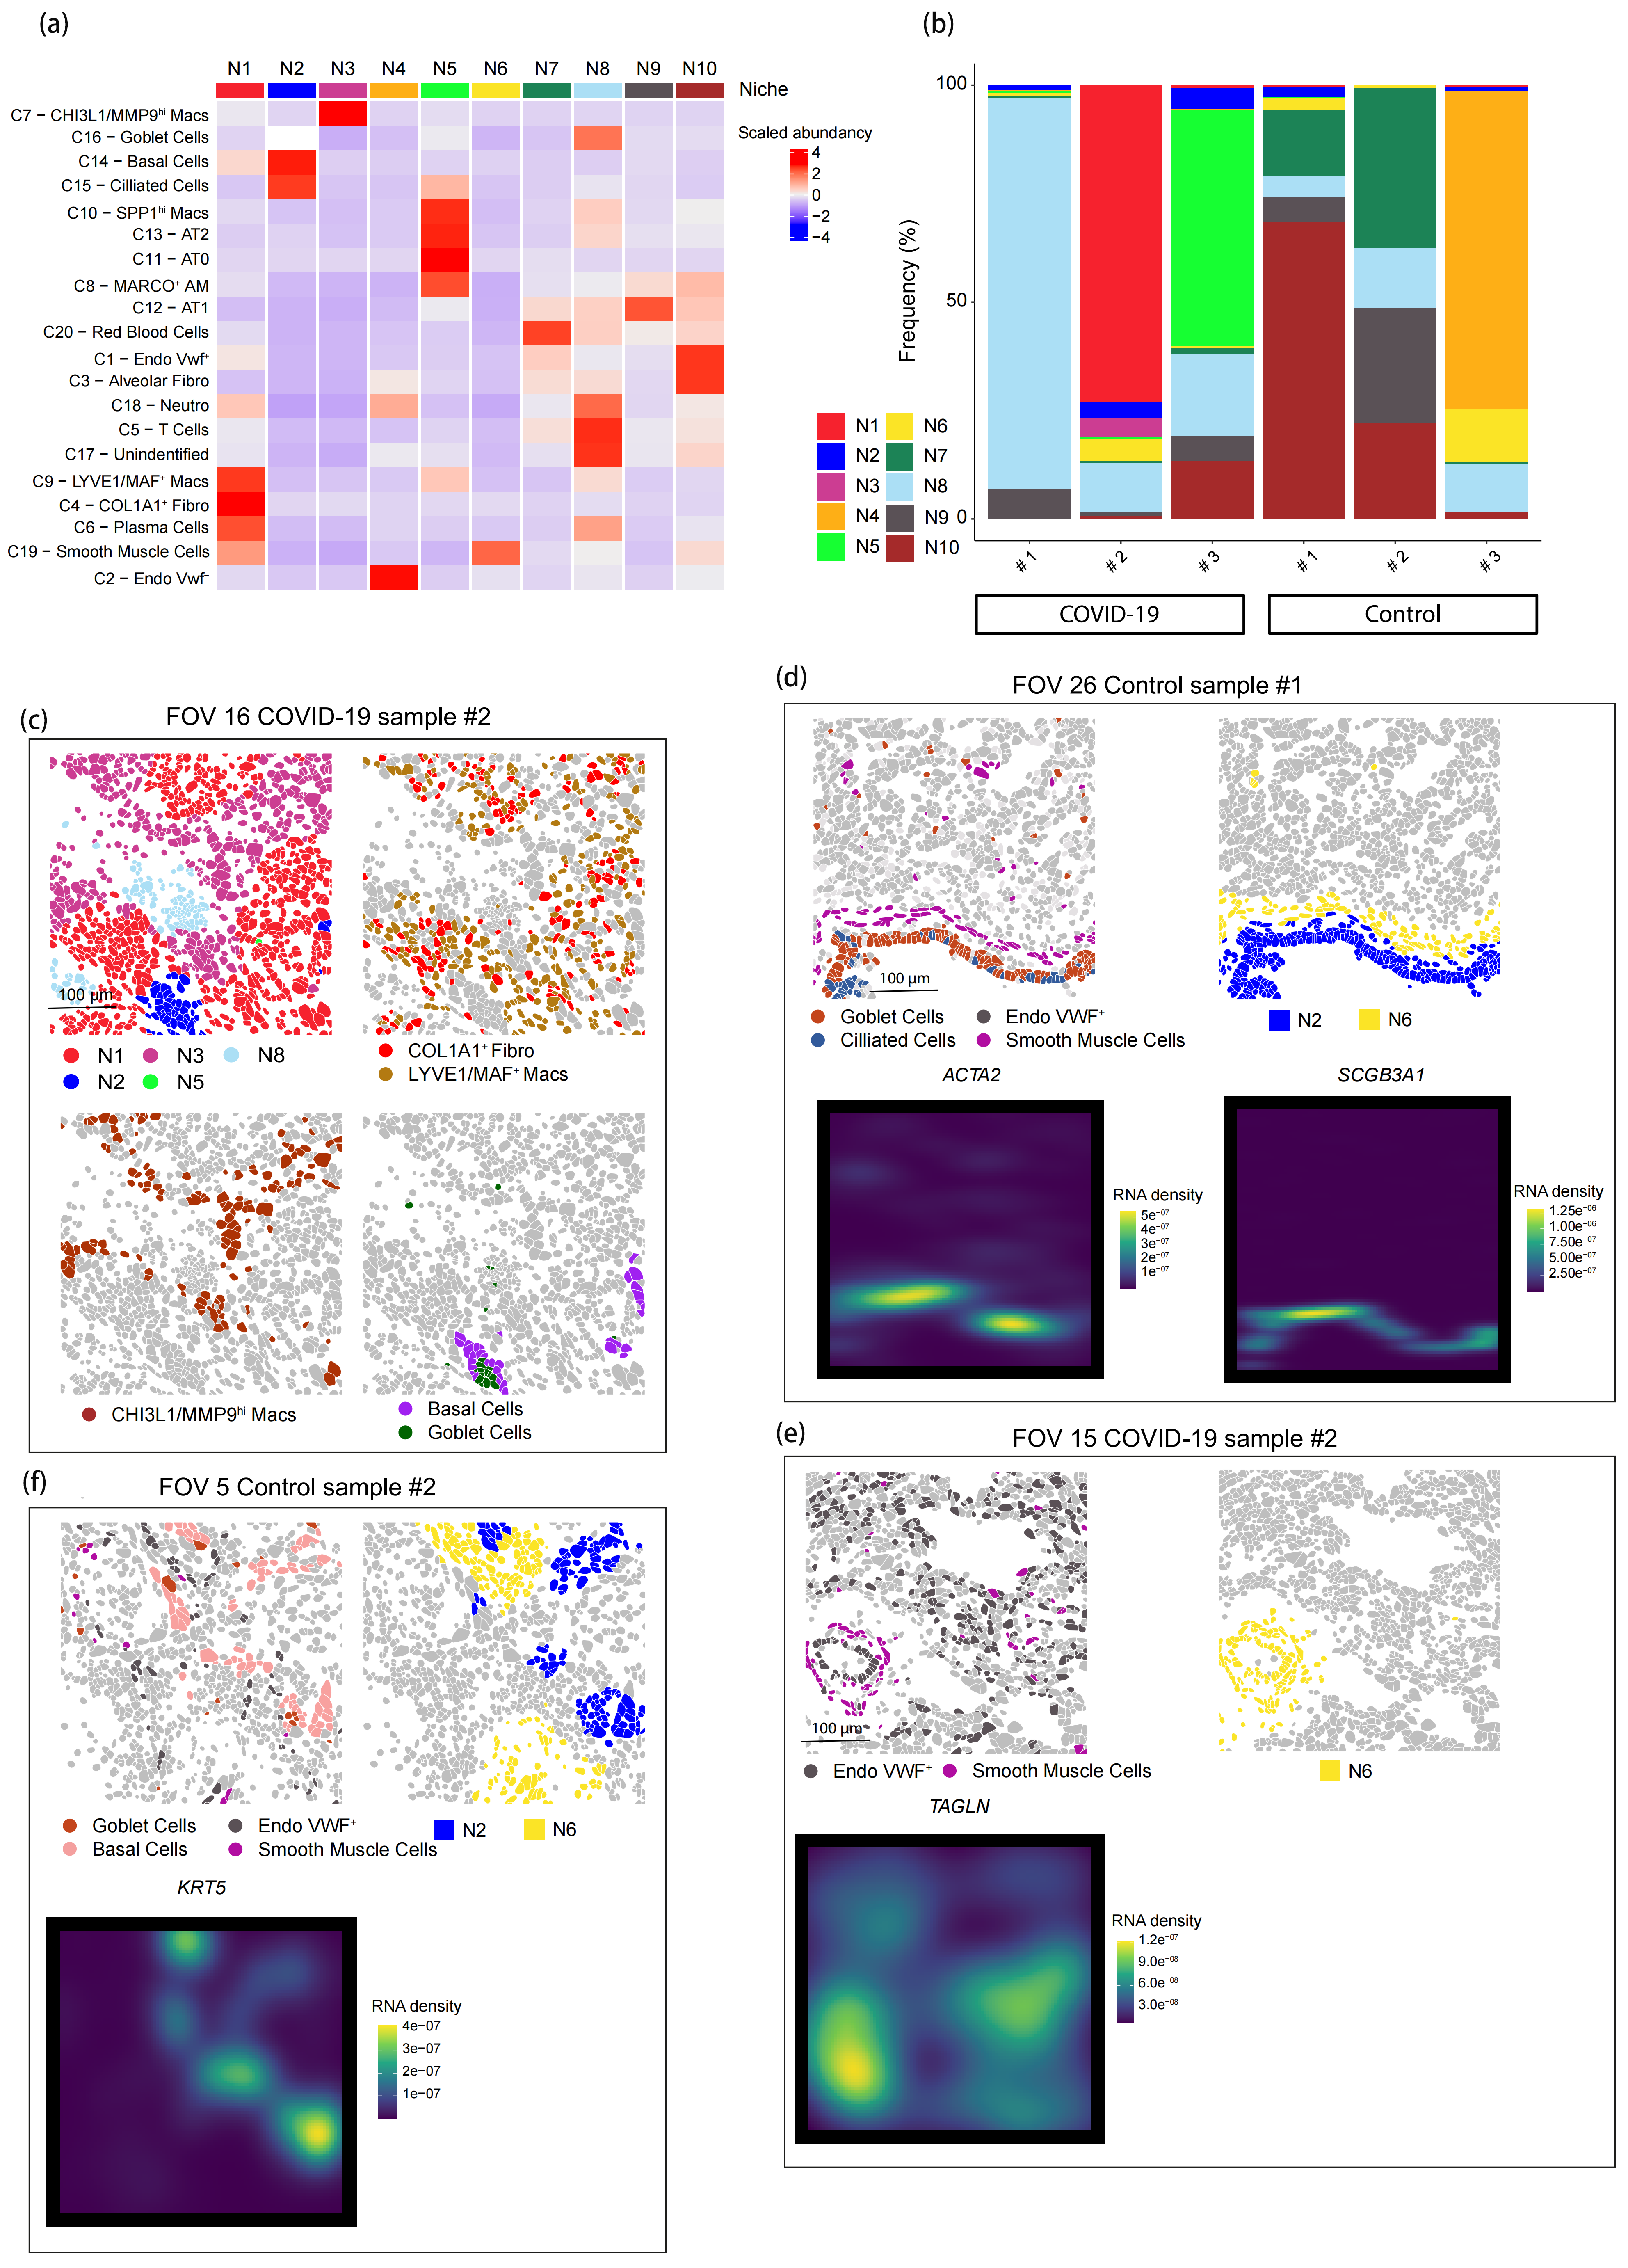
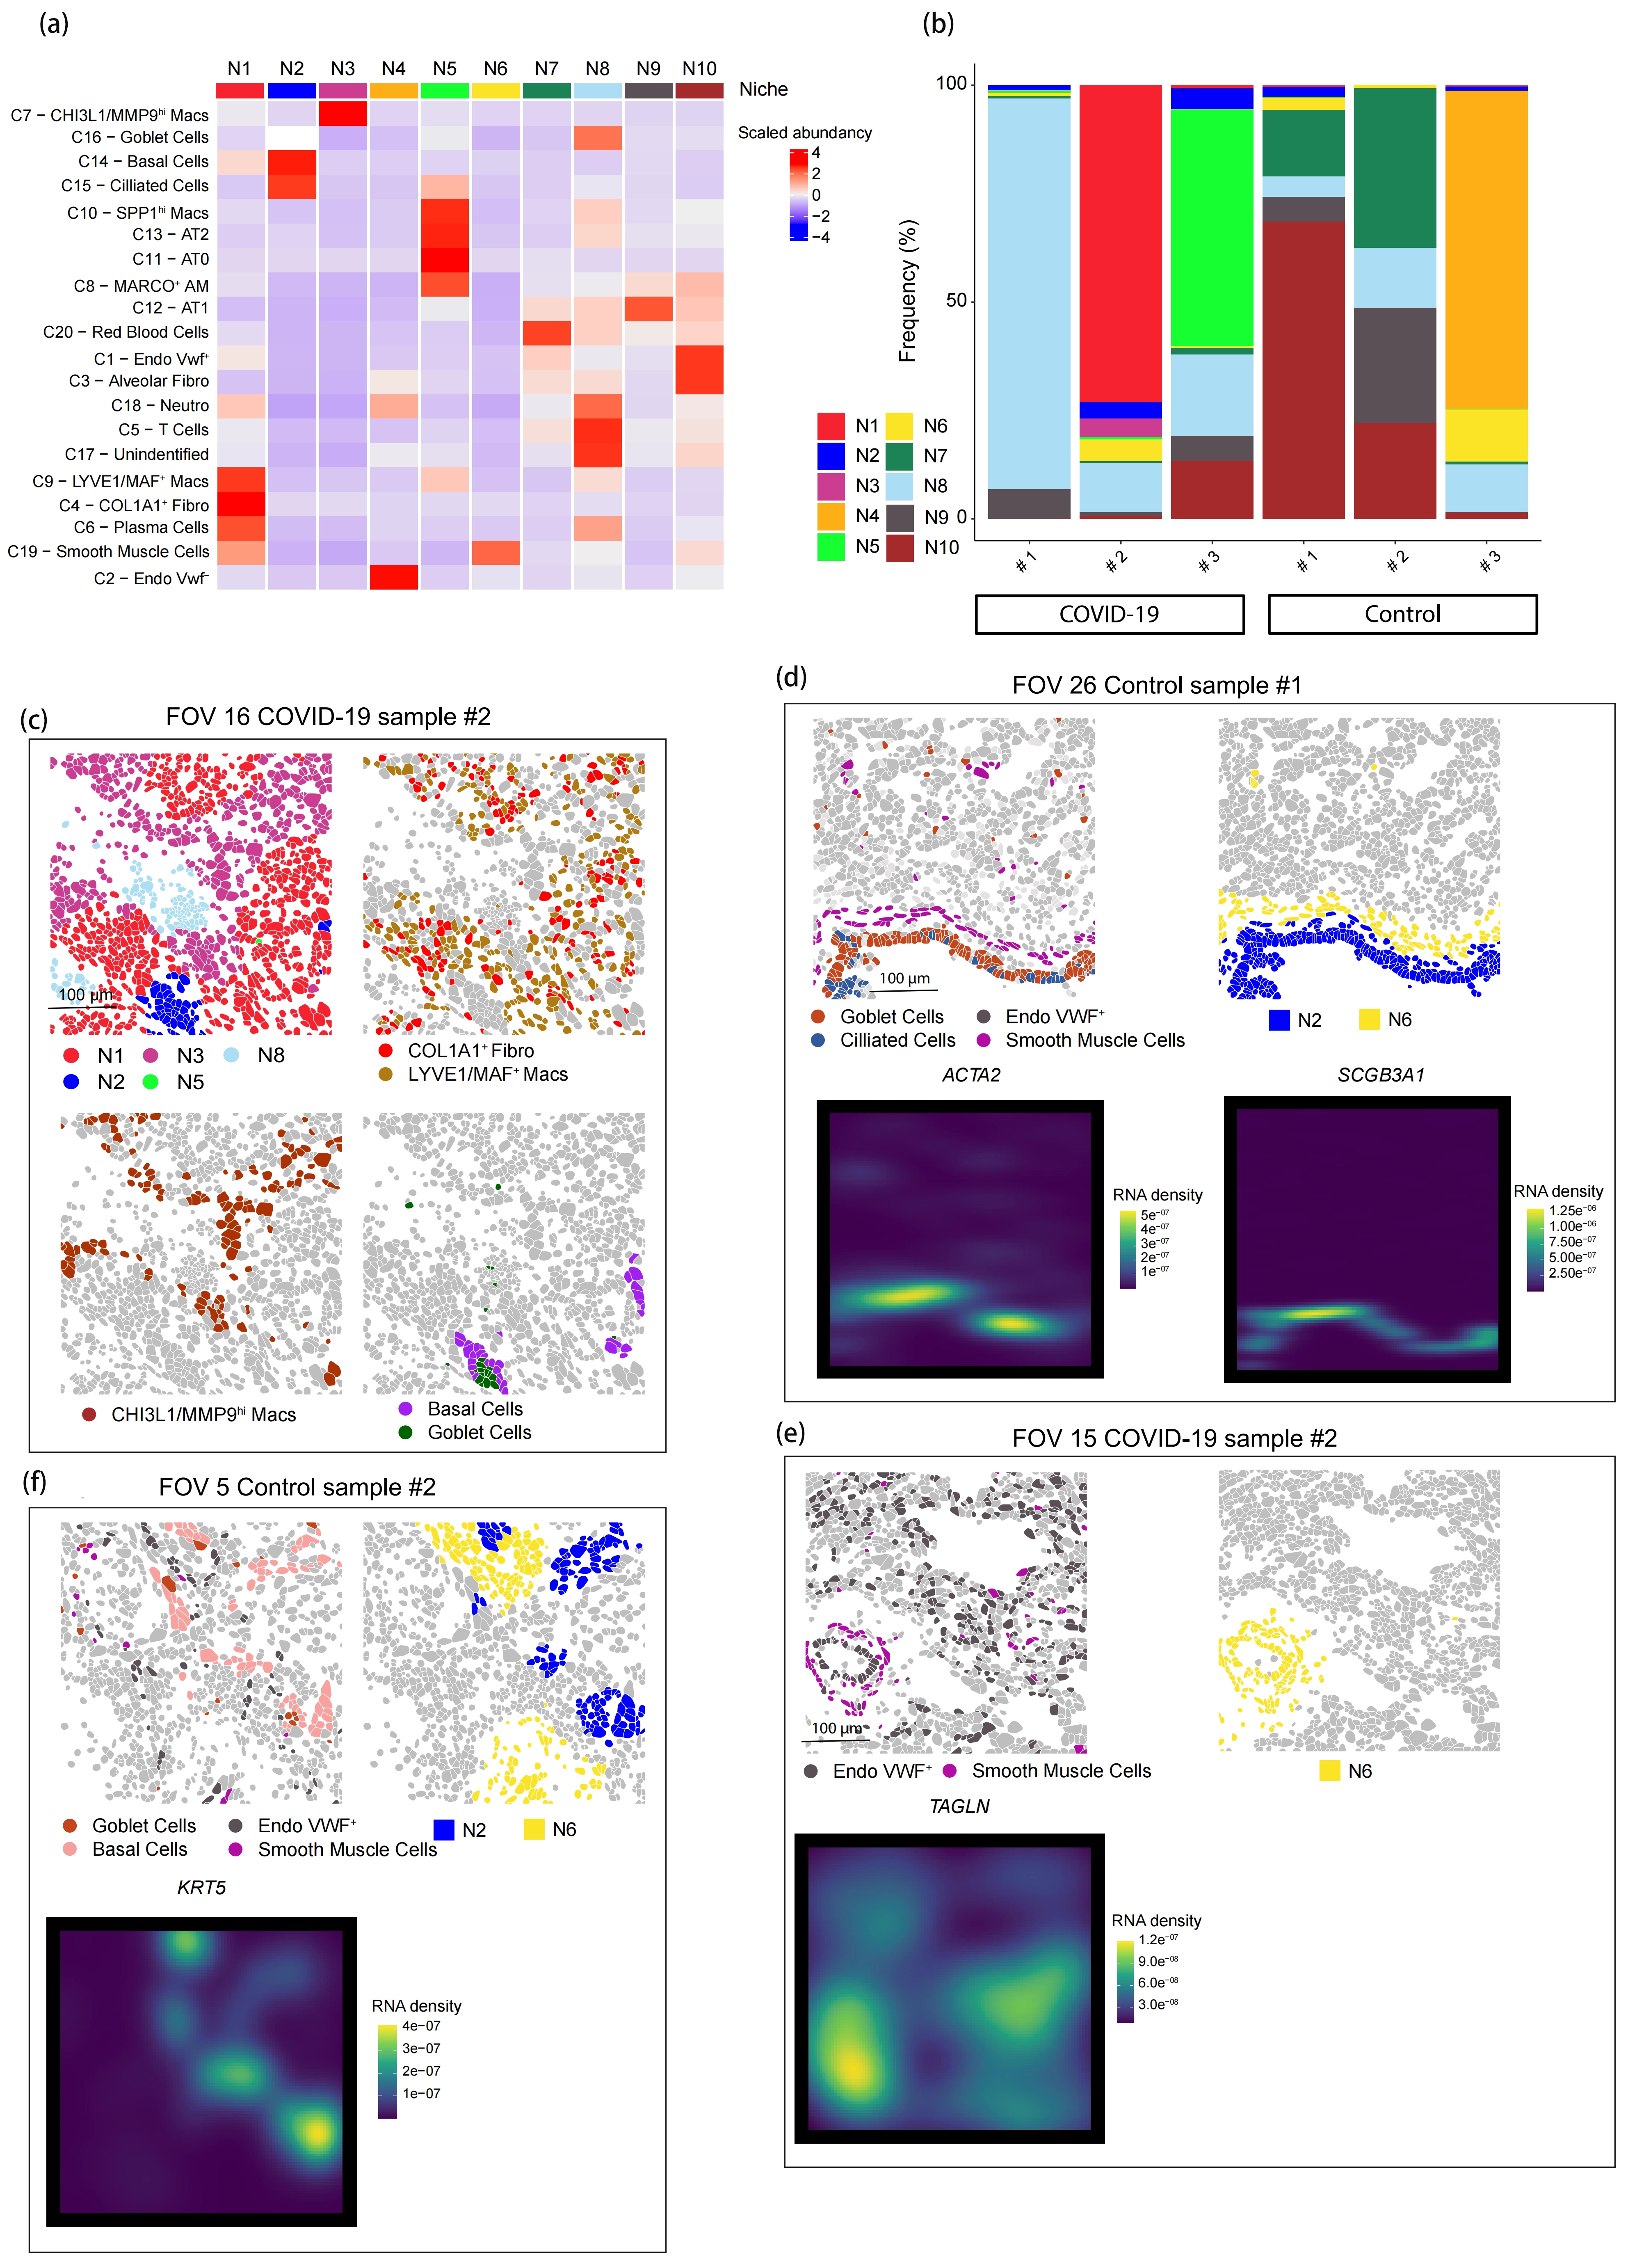
Figure 4. Cellular niche identification in COVID-19 and Control samples. (a) Scaled abundance matrix representing the count of each annotated cell population across niches. Z-score normalization was applied by row; (b) Histogram showing the frequency of each niche per sample; (c) Representative dimension plot of FOV 16 from COVID-19 sample #2 where cells are colored by niche and cell types; (d-f) Dimension plot of FOVs representing (d) FOV Control 26, (e) FOV Covid 15 and (f) FOV Control 5, with niche N2 and N6 highlighted (upper right), annotated cell type highlighted (upper left) and density plots representing RNA density (lower) of genes specific of smooth muscle cells (ACTA2, TAGLN), goblet cells (SCGB3A1) and basal cells (KRT5). COVID-19: coronavirus disease 2019; FOV: fields of view; COL1A1+: collagen type I alpha 1 chain; Endo: endothelial cells; SPP1hi: secreted phosphoprotein 1; MARCO+: macrophage receptor with collagenous structure; CHI3L1: chitinase 3-like 1; MMP9hi: matrix metalloproteinase 9; Fibro: fibroblasts; AM: alveolar macrophages.
In contrast, niches N1, N3, and N5 were detected almost exclusively in COVID-19 samples (Figure 4a,b). N1 displayed features of fibrotic remodeling, including an abundance of plasma cells[44], and COL1A1+ Fibros[45], together with numerous endothelial and smooth muscle cells[46] (Figure 4a,c). N3 was primarily defined by CHI3L1/MMP9hi Macs (Figure 4a,b), while otherwise sharing a cellular composition similar to N1 (Figure S6). Hence, the identification of this distinct niche suggests a spatial clustering of CHI3L1/MMP9hi Macs (Figure 4c). Even though N1, N2 and N3 are three separated niches, we observed that such niches tended to be spatially adjacent inside COVID-19 #2 (Figure 4c). N5, in contrast, was predominantly composed of alveolar-associated cells, including AT0 and AT2 cells, and MARCO+ an AM, together with SPP1hi macrophages. Importantly, these niches segregated by samples: N1 and N3 were detected exclusively in COVID-19 sample #2, while N5 was specific to COVID-19 sample #3, and COVID-19 sample #1 was characterized by the expansion of the immune-rich N8 niche (Figure 4b).
Together, these findings support the conclusion that each COVID-19 sample represents a distinct pathological state, associated with a unique constellation of cellular niches. These data are consistent with a model in which distinct histopathological contexts are linked to specific tissue architectures and cellular compositions, ultimately reflecting divergent underlying mechanisms of immunopathology.
3.5 Macrophage-derived TGF-β signaling is predicted in pro-fibrotic niches
Next, we focused on the fibrotic COVID-19 sample #2 and its associated niches N1 and N3 to identify candidate cell-cell interactions underlying fibrotic remodeling. COL1A1+ Fibros exhibited a pathological phenotype characterized by high expression of ECM genes (COL1A1, COL5A1, COL6A1) (Figure 3d), reminiscent of pathogenic CTHRC1+ Fibros differentiating from alveolar Fibros[47], although CTHRC1 was not included in the gene panel. Notably, CHI3L1/MMP9hi Macs, which expressed pro-fibrotic genes (SPP1, CHI3L1, MMP9)[21], were spatially adjacent to COL1A1+ Fibros (Figure 5a,b), suggesting local interactions between these two cell types. NicheNet analysis[33], using CHI3L1/MMP9hi Macs as sender cells and fibroblasts as receivers, identified TGFB1 and TGFB2 as top ligands predicted to regulate fibrosis-associated gene programs in receiver cells, including ECM components (COL1A1, COL2A1, COL5A1) as well as the myofibroblast-related gene ACTA2 (Figure 5c,d). In addition, LGALS3, encoding for GALECTIN-3, which can potentiate TGF-β-mediated fibrosis[48], was also identified as a high-priority ligand. Consistently, CHI3L1/MMP9hi Macs exhibited elevated and selective expression of both TGFB1 and LGALS3 (Figure 5e). Of note, the proximity between these macrophages and COL1A1+ Fibros was also observed upon reanalysis of an independent CosMx dataset from COVID-19 lungs[28] (Figure S7).
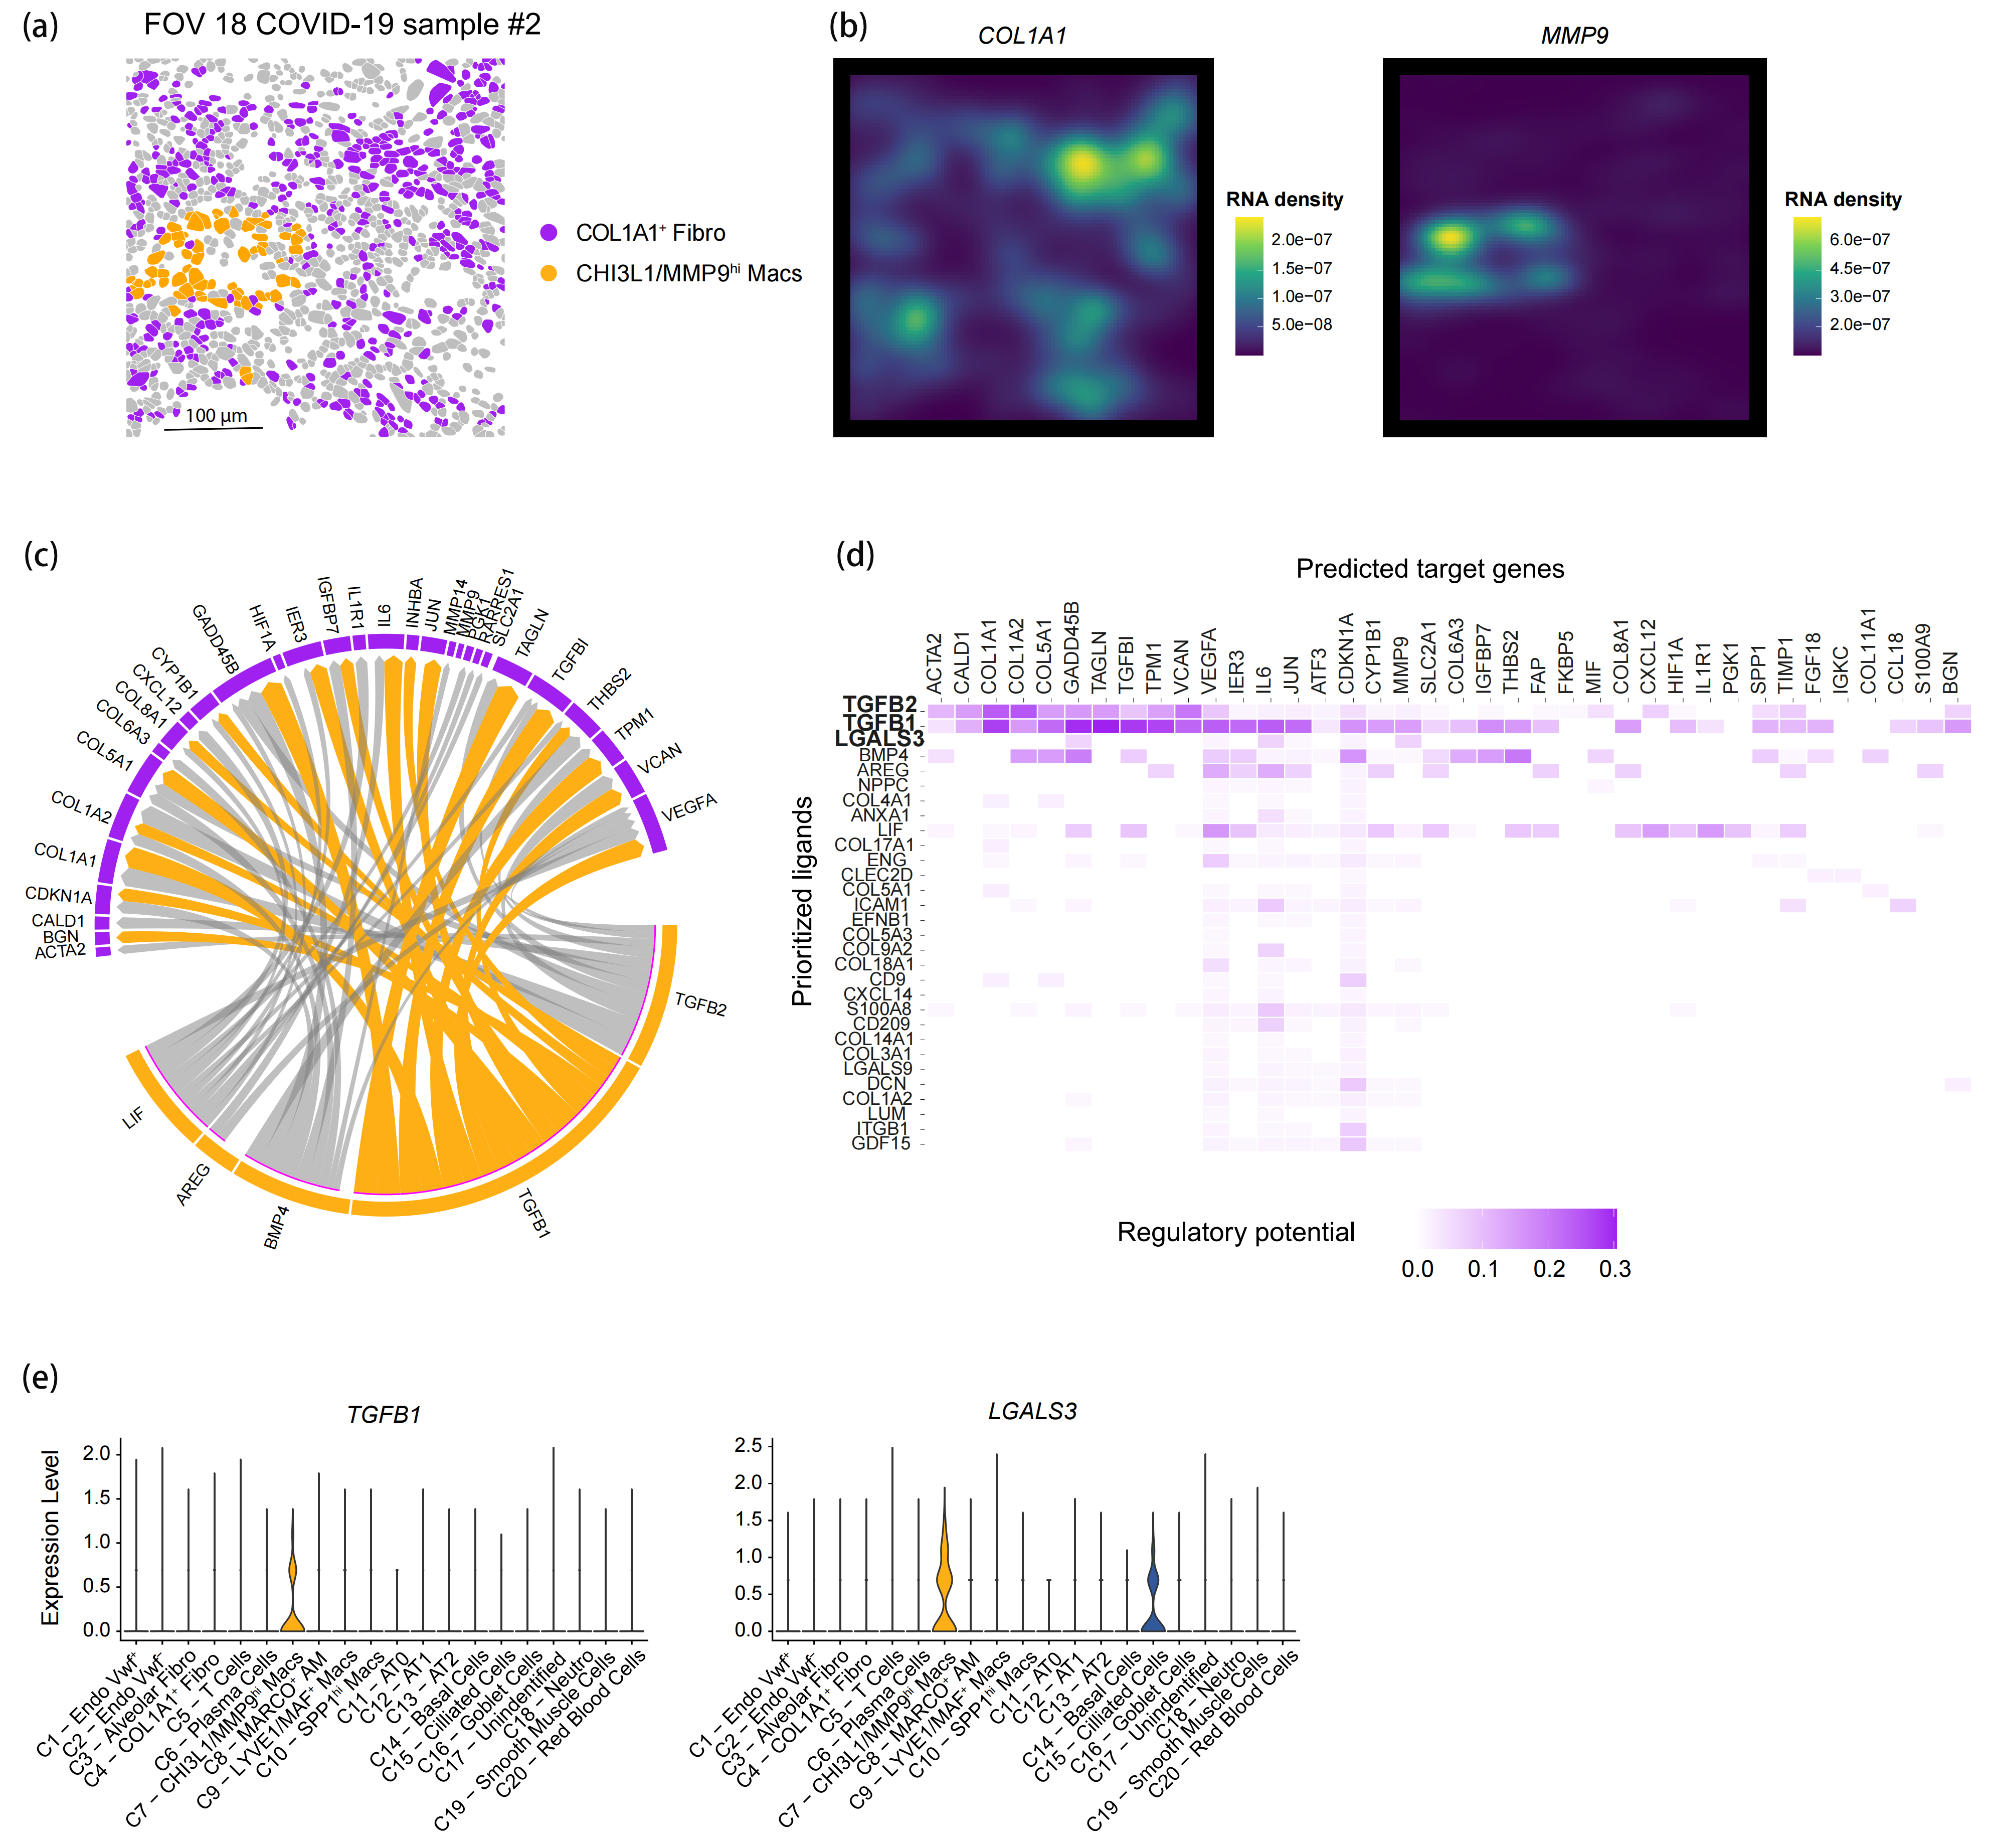
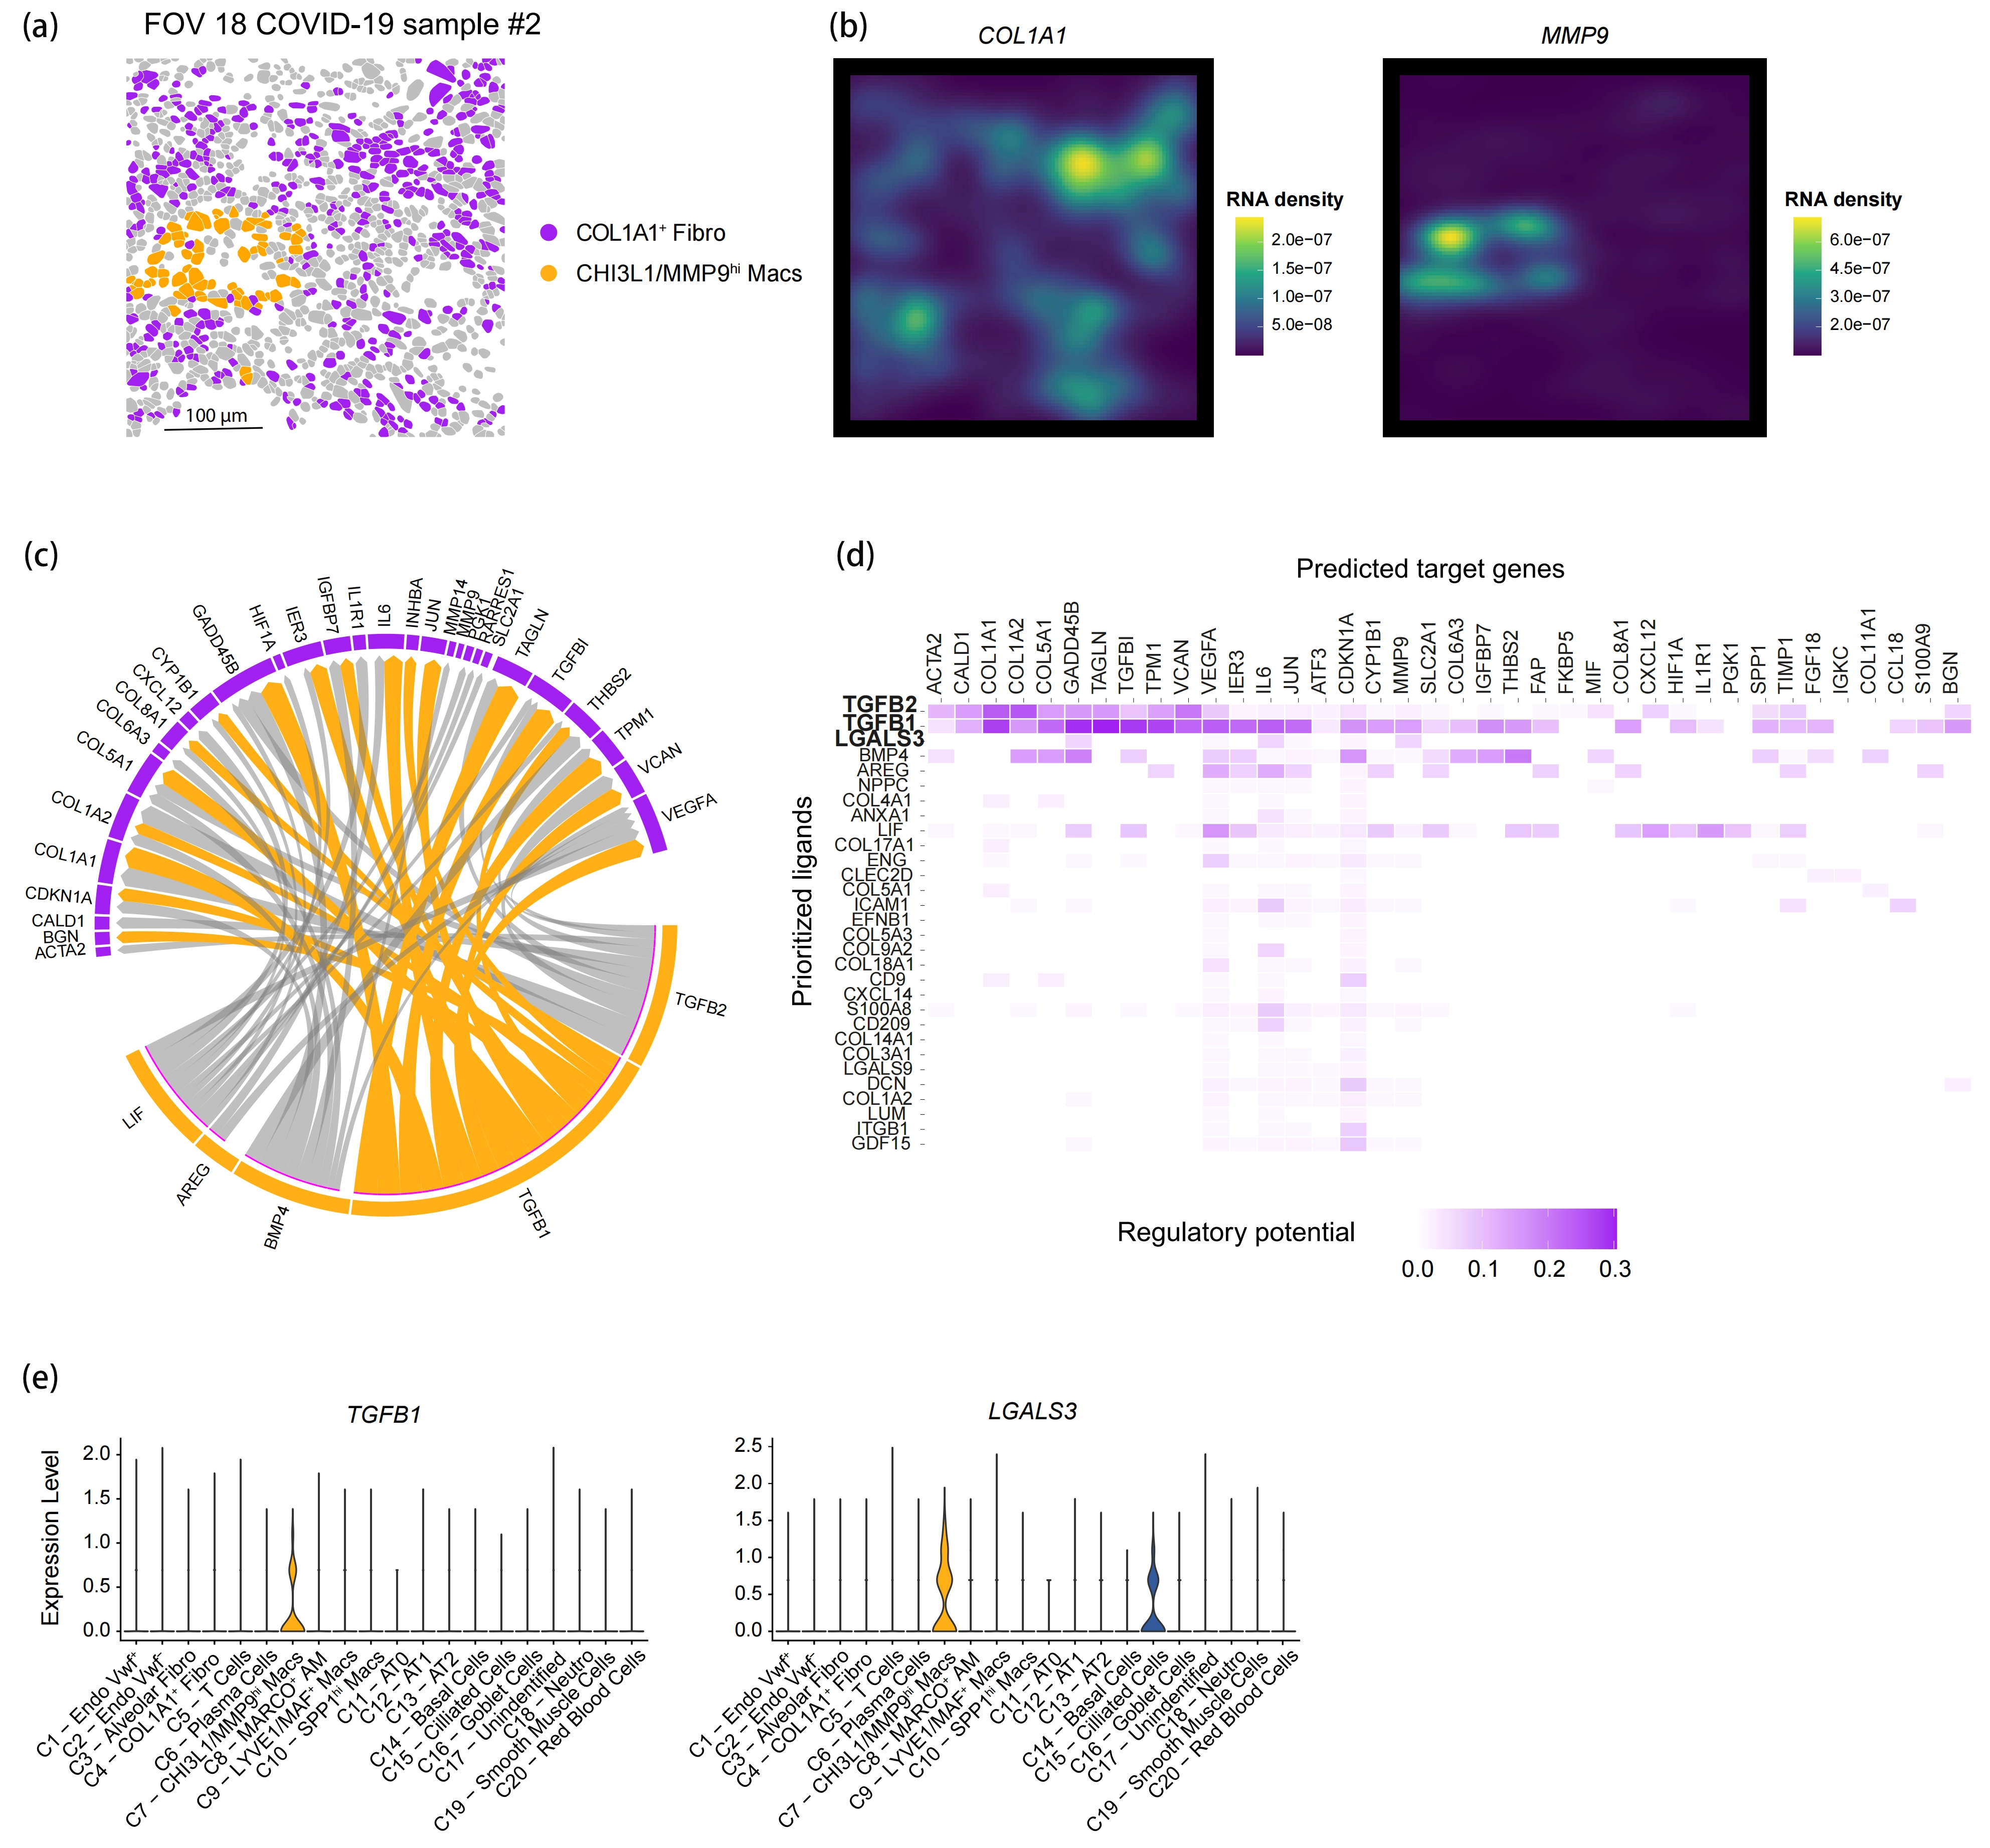
Figure 5. Ligand-receptor analysis supports pro-fibrotic macrophages driving pathogenic fibroblasts within fibrotic niches N1 & N3. (a) Dimension plot of FOV 18 from COVID-19 sample #2 representing the segmentations of cells; (b) Density plots of FOV 18, as in (A), representing RNA densities for the genes COL1A1 and MMP9; (c) Circoplot representing the putative interactions between CHI3L1/MMP9hi Macs (orange) and Fibros (purple) from a NicheNet analysis. Interaction between TGFB1 and target genes in Fibros identified by Nichenet are highlighted; (d) Heatmap depicting predicted ligand activity within CHI3L1/MMP9hi Macs and fibroblasts target gene activation during a potential evolution of alveolar Fibros to COL1A1+ Fibros on the basis of NicheNet analyses as in (c); (e) Expression levels of TGFB1 and LGALS3 in the indicated cell types. COVID-19: coronavirus disease 2019; CHI3L1: chitinase 3-like 1; MMP9hi: matrix metalloproteinase 9; Fibros: fibroblasts; FOV: fields of view; COL1A1: collagen type I alpha 1 chain; Fibro: fibroblasts; Endo: endothelial cells; MARCO+: macrophage receptor with collagenous structure; AM: alveolar macrophage.
Together, these findings support a model in which CHI3L1/MMP9hi Macs promote fibroblast reprogramming within fibrotic niches through TGF-β-mediated signaling, thereby contributing to the emergence and persistence of pathogenic COL1A1+ Fibros.
3.6 Alveolar niche-derived signals may shape SPP1hi macrophage identity
The alveolar-associated niche N5, predominantly observed in COVID-19 sample #3, contained two distinct macrophage populations, namely SPP1hi Macs and MARCO+ AMs (Figure 6a). SPP1hi Macs were identified as monocyte-derived Macs by reference-based mapping, similar to CHI3L1/MMP9hi Macs (Figure 2c). However, their localization to alveolar regions suggested exposure to a distinct microenvironment. To identify signals potentially shaping their phenotype, we performed a sender-agnostic NicheNet analysis. Among the top predicted ligands were WNT5A[49,50] and WNT7B[50], as well as CSF1 and CSF2, encoding macrophage-CSF (M-CSF)[51] and granulocyte-macrophage colony-stimulating factor (GM-CSF)[52], respectively (Figure 6b). These factors have established roles in macrophage differentiation and activation. In particular, GM-CSF has been shown to contribute to alveolar macrophage development and maintenance and is produced by AT2 cells[52], which were enriched in N5 (Figure 6a).
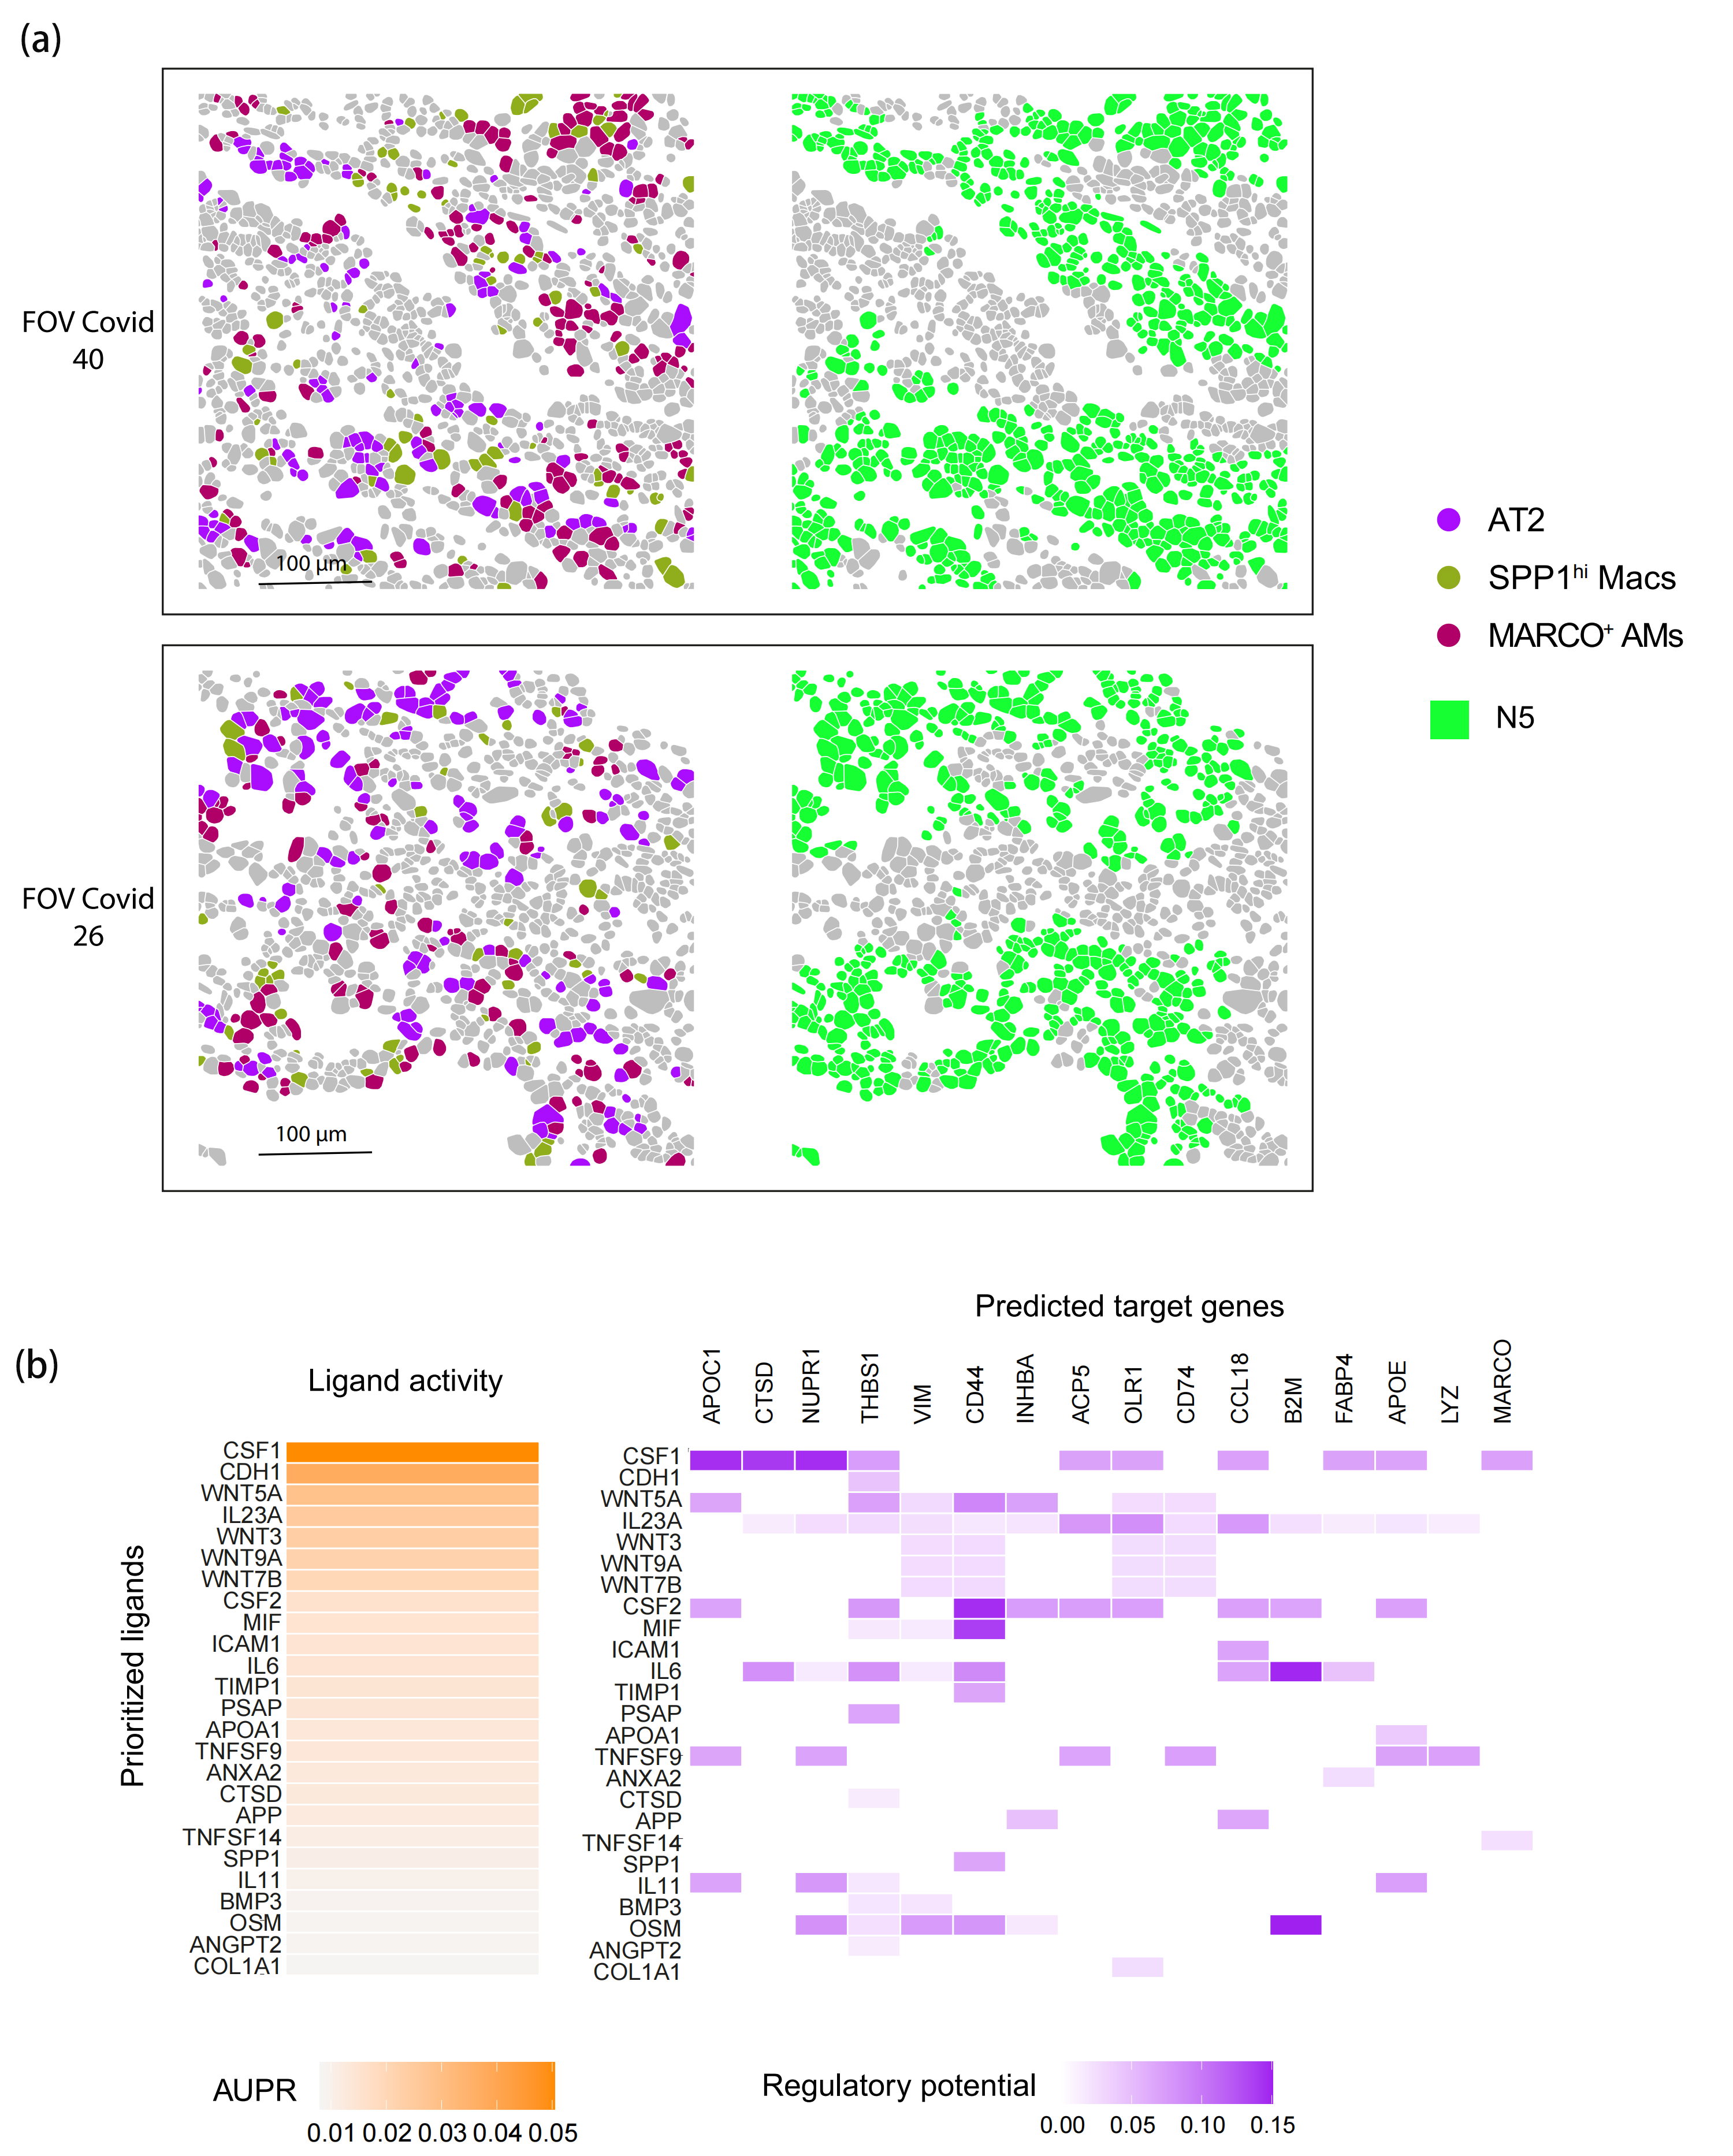
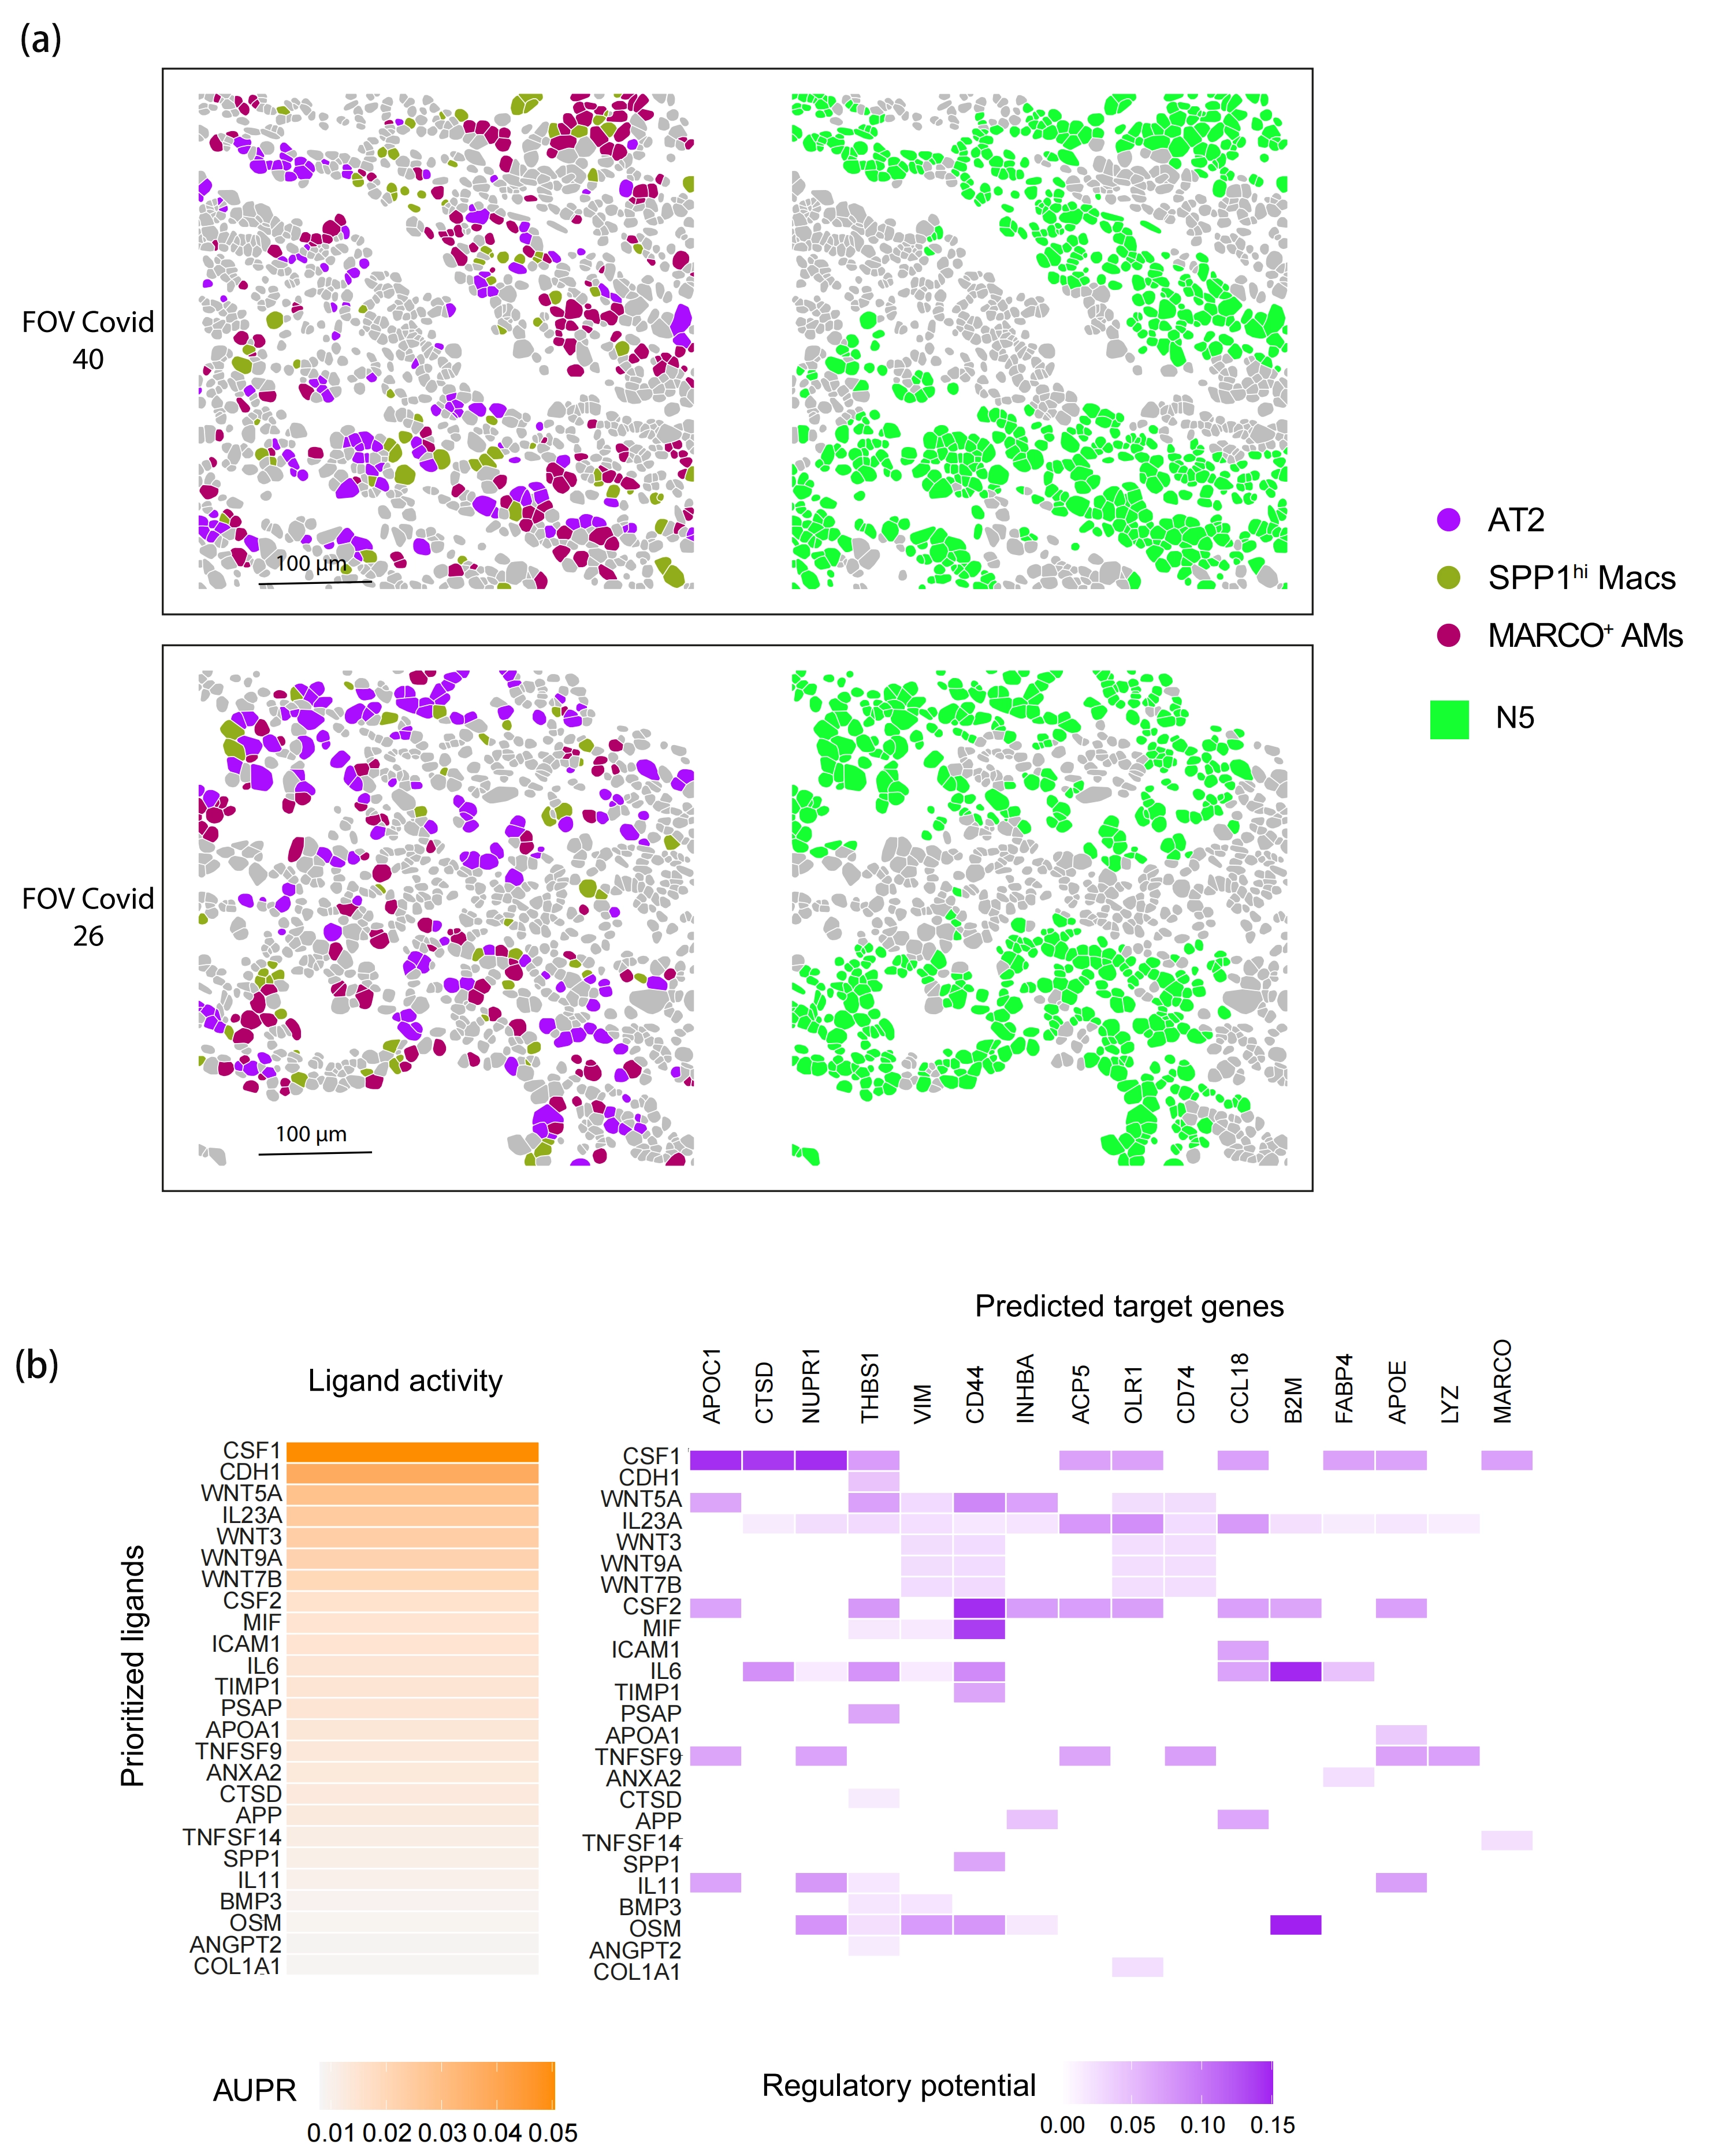
Figure 6. Ligand-receptor analysis of macrophages inside alveolar niches. (a) Representative dimension plot of FOV 26 and 40 from the COVID-19 slide where cells are colored first by annotated cell types (left) and then where N5 is highlighted (right); (b) Heatmap depicting predicted ligand activity on AM-intrinsic target gene activation during macrophage differentiation, evaluated by NicheNet. COVID-19: coronavirus disease 2019; FOV: fields of view; SPP1hi: secreted phosphoprotein 1; MARCO+: macrophage receptor with collagenous structure; AM: alveolar macrophage.
Together, these findings are consistent with the hypothesis that SPP1hi macrophages within alveolar niches are exposed to local signals, including WNT ligands, M-CSF, and GM-CSF, which may contribute to their adaptation toward an alveolar macrophage-like state.
4. Discussion
In this study, we applied imaging-based ST using the CosMx platform to post-mortem human lung samples and provide a framework for the processing and interpretation of imaging-based ST data in the context of severe COVID-19. Rather than aiming to define broadly applicable mechanisms of COVID-19 pathology, this proof-of-concept study was designed to identify spatially organized cellular patterns and generate biologically testable hypotheses from human tissue.
Our findings highlight the value of imaging-based ST for the in-depth characterization of pathological processes in archived tissue samples. This approach enables mapping of cellular composition and spatial organization while capturing phenotypic changes within specific cell populations. Importantly, it reveals spatial associations between cell types and thereby identifies tissue niches from which candidate cell-cell interactions can be inferred. The concordance between ST-defined niches and the histopathological features of corresponding tissue sections illustrates how spatial molecular information can complement conventional histopathological assessment.
Several limitations should be acknowledged. First, the small cohort size, analysis of a single anatomical region per subject, and marked spatial and inter-individual heterogeneity of COVID-19 lung pathology preclude generalization of the identified niches to the broader population of patients with severe COVID-19[42,43]. Accordingly, the niches described here should be considered as representative of the pathological states captured in these particular tissue sections rather than as universal features of severe COVID-19. The use of post-mortem control tissues with pre-existing histopathological alterations represents an additional limitation. Although samples were collected according to a standardized procedure, the potential impact of fixation and FFPE processing on transcript abundance and spatial organization cannot be directly assessed in this study. Furthermore, the restricted gene panel and the relatively low number of detected RNA molecules per cell limit the depth of transcriptomic characterization. Integrating imaging-based ST with high-throughput approaches such as single-cell RNA sequencing may help overcome these limitations by improving both cell-type resolution and transcriptomic coverage.
Despite these constraints, several observations are consistent with previous studies. The increased proportion of immune cells, particularly macrophages, in COVID-19 samples aligns with previous reports[53]. We identified cell populations corresponding to previously described subsets, including CHI3L1/MMP9hi Macs, which resemble profibrotic macrophages described in severe COVID-19[21], and COL1A1+ Fibros, which are reminiscent of pathogenic CTHRC1+ Fibros derived from alveolar fibroblasts[45,47]. In addition, the presence of basal cells in fibrotic samples may reflect dysplastic repair processes associated with chronic lung injury in COVID-19[53]. Importantly, our spatial approach places these cellular states within defined histopathological contexts rather than considering them independently of tissue architecture. Profibrotic niches corresponded to regions of fibrosis evaluated by histopathology and contained specific cell populations organized into spatially defined microenvironments. Similar observations have been reported using complementary spatial transcriptomic approaches. A sequencing-based GeoMx study of COVID-19 lungs identified fibrosis- and TGF-β-associated transcriptional programs in regions of organizing DAD, whereas SPP1 expression was enriched in regions corresponding to earlier stages of DAD[11]. Imaging-based Xenium analysis of fibrotic human lungs has likewise identified profibrotic niches containing macrophages, activated fibroblasts, and aberrant epithelial cells within remodeled distal lung regions[54]. Together, these observations support the concept that distinct histopathological contexts are associated with specific spatial cellular organizations. Whether these niches represent sequential stages of lung injury and repair or distinct context-dependent responses remains to be determined.
Within these niches, our ligand-receptor analyses generated candidate mechanisms of intercellular communication that will require functional validation. In fibrotic niches, CHI3L1/MMP9hi Macs expressing TGFB1 and LGALS3 were spatially adjacent to COL1A1+ Fibros, supporting a model in which macrophage-derived signals contribute to pathogenic fibroblast reprogramming through the TGF-β axis. Importantly, reanalysis of an independent COVID-19 CosMx dataset[28] reproduced the spatial proximity between CHI3L1/MMP9hi macrophages and COL1A1+ fibroblasts, indicating that this cellular association is not restricted to the original sample. However, our data do not directly demonstrate that macrophage-derived TGF-β drives fibroblast activation, and dedicated functional studies will be required to establish causality. Thus, TGF-β should be considered a candidate signaling axis emerging from the spatial analysis rather than a demonstrated mechanism.
In contrast, alveolar-associated niches displayed distinct environments, including WNT ligands and M-CSF/GM-CSF-related pathways. Notably, SPP1+ macrophages, often described as pro-fibrotic[18,21], were predominantly localized within alveolar niches and were largely absent from severely fibrotic regions. Together with the reported enrichment of SPP1 in earlier stages of DAD[11], this suggests that the phenotype and potential functions of SPP1hi macrophages may depend strongly on their local tissue environment and stage of injury. The corresponding SPP1hi macrophage-associated alveolar niche could not be identified in the independent CosMx dataset[28], which may reflect differences in the nature or stage of the lesions captured rather than absence of this interaction in other patients. Consistent with another report[55,56], this observation suggests that SPP1+ macrophages may represent an early or context-dependent response to lung injury, potentially contributing to alveolar remodeling or repair rather than exclusively to advanced fibrosis.
Overall, our study should therefore be viewed as hypothesis-generating: it identifies spatially-restricted macrophage states and candidate interaction networks associated with distinct histopathological contexts, providing specific cellular and molecular relationships that could be tested experimentally. Larger cohorts encompassing different disease stages and anatomical regions, together with functional and longitudinal approaches, will be required to determine the recurrence, temporal dynamics, and biological significance of these niches.
5. Conclusion
Our study provides a proof-of-concept supporting the utility of imaging-based ST for investigating the spatial organization of immunopathology in severe COVID-19 and other lung disorders. By integrating histopathology with single-cell spatial information, we identified distinct macrophage-associated niches and generated candidate mechanisms linking local cellular interactions to fibrotic or alveolar tissue states. The recurrence of CHI3L1/MMP9hi macrophage-COL1A1+ fibroblast proximity in an independent dataset, together with concordant observations from other spatial studies, supports the biological relevance of this association while emphasizing the need for validation in larger cohorts. Future studies integrating spatial transcriptomics with functional approaches will be required to establish causality, particularly for the predicted TGF-β axis, and to determine whether these niche-specific macrophage programs contribute directly to disease progression or repair.
Supplementary materials
The supplementary material for this article is available at: Supplementary materials.
Acknowledgements
The authors thank all members of the Immunophysiology laboratory (GIGA Institute, University of Liège, Belgium) and Monica Di Cesare, Mélanie Gardier and Ilham Sbai for their excellent technical and administrative support. This manuscript incorporates and extends material previously presented as an ERS Lung Science Conference 2026 abstract (PS329): https://publications.ersnet.org/content/erjor/12/suppl18/ps329. More detailed analyses are presented and discussed in the manuscript.
Authors contribution
Abinet J: Methodology, formal analysis, visualization, writing-original draft.
Ruscitti C: Methodology, investigation, writing-review & editing.
Garigliany M: Investigation.
Liégeois M: Formal analysis, writing-review & editing.
Radermecker C, Marichal T: Conceptualization, supervision, funding acquisition, writing-review & editing.
All authors provided feedback on the manuscript.
Conflicts of interest
Cecilia Ruscitti and Maude Liégeois are postdoctoral fellows of the F.R.S.-FNRS. Coraline Radermecker is a Research Associate of the F.R.S.-FNRS. The other authors declare no conflicts of interest.
Ethical approval
The samples were collected with the approval of the Ethics Reviewing Board of the University Hospital of Liege, Belgium (Ref. 2020/119).
Consent to participate
Informed consent was obtained from all participants included in the study or, where applicable, from their legal representatives.
Consent for publication
Not applicable.
Availability of data and materials
The processed data files can be accessed in the Expression Omnibus database under the accession number GSE327879. The scripts used to analyze these data have been uploaded to GitHub (https://github.com/JoanAbinet/COVID19_niche).
Funding
Thomas Marichal acknowledges support from the F.R.S.-FNRS (Incentive Grant for Scientific Research: F.4508.18), from the FRFS-Welbio (Starting Grant: CR-2017s-04; Advanced Grant: CR-2022A-10), and from the European Research Council (Grant No. ERC StG 2018 IM-ID: 801823). Thomas Marichal is supported by Research Project (PDR-T.0200.25) and a Research Credit Grant (CDR-J0141.24) of the F.R.S.-FNRS, by a FRFS-Welbio Advanced Grant (CR-X.1520.26), by an ERC Consolidator Grant (ERC CoG 2023 MoMacTrajectALI: 101124390), and by the Baillet Latour Fund (Infection-Immunity_2022). Cecilia Ruscitti and Maude Liégeois are supported by the F.R.S.-FNRS as postdoctoral fellows. Coraline Radermecker is supported by a Research Credit Grant (CDR-J.0175.26) of the F.R.S.-FNRS and by the Baillet Latour Fund (Cardiovascular-Pulmonary_2025). This research was supported by the European Regional Development Fund (Grant No. FEDER-SYSTIMM).
Copyright
© The Author(s) 2026.
References
-
1. World Health Organization. COVID-19 cases|WHO COVID-19 dashboard [Internet]. Geneva: World Health Organization; 2023. Available from: https://data.who.int/dashboards/covid19/cases
-
3. Tzotzos SJ, Fischer B, Fischer H, Zeitlinger M. Incidence of ARDS and outcomes in hospitalized patients with COVID-19: A global literature survey. Crit Care. 2020;24(1):516.[DOI]
-
4. Azagew AW, Beko ZW, Ferede YM, Mekonnen HS, Abate HK, Mekonnen CK. Global prevalence of COVID-19-induced acute respiratory distress syndrome: Systematic review and meta-analysis. Syst Rev. 2023;12(1):212.[DOI]
-
6. Milross L, Hunter B, McDonald D, Merces G, Thomson A, Hilkens CMU, et al. Distinct lung cell signatures define the temporal evolution of diffuse alveolar damage in fatal COVID-19. EBioMedicine. 2024;99:104945.[DOI]
-
9. Menter T, Haslbauer JD, Nienhold R, Savic S, Hopfer H, Deigendesch N, et al. Postmortem examination of COVID-19 patients reveals diffuse alveolar damage with severe capillary congestion and variegated findings in lungs and other organs suggesting vascular dysfunction. Histopathology. 2020;77(2):198-209.[DOI]
-
12. Rendeiro AF, Ravichandran H, Bram Y, Chandar V, Kim J, Meydan C, et al. The spatial landscape of lung pathology during COVID-19 progression. Nature. 2021;593(7860):564-569.[DOI]
-
14. Ganesan A, Moore AR, Zheng H, Toh J, Freedman M, Magis AT, et al. A conserved immune dysregulation signature is associated with infection severity, risk factors prior to infection, and treatment response. Immunity. 2025;58(8):2104-2119.e5.[DOI]
-
18. MacDonald L, Alivernini S, Tolusso B, Elmesmari A, Somma D, Perniola S, et al. COVID-19 and RA share an SPP1 myeloid pathway that drives PD-L1+ neutrophils and CD14+ monocytes. JCI Insight. 2021;6(13):e147413.[DOI]
-
22. Chua RL, Lukassen S, Trump S, Hennig BP, Wendisch D, Pott F, et al. COVID-19 severity correlates with airway epithelium–immune cell interactions identified by single-cell analysis. Nat Biotechnol. 2020;38(8):970-979.[DOI]
-
31. Xu S, Hu E, Cai Y, Xie Z, Luo X, Zhan L, et al. Using clusterProfiler to characterize multiomics data. Nat Protoc. 2024;19(11):3292-3320.[DOI]
-
32. Gu Z. Complex heatmap visualization. IMeta. 2022;1(3):e43.[DOI]
-
33. Browaeys R, Saelens W, Saeys Y. NicheNet: Modeling intercellular communication by linking ligands to target genes. Nat Methods. 2020;17(2):159-162.[DOI]
-
40. Umekita K, Miyauchi S, Nomura H, Umeki K, Okayama A. Neutrophil-derived lactoferrin induces the inflammatory responses of rheumatoid arthritis synovial fibroblasts via Toll-like receptor 4. Clin Exp Rheumatol. 2019;37(5):834-841.[PubMed]
-
42. Desai N, Neyaz A, Szabolcs A, Shih AR, Chen JH, Thapar V, et al. Temporal and spatial heterogeneity of host response to SARS-CoV-2 pulmonary infection. Nat Commun. 2020;11(1):6319.[DOI]
-
50. Zhu B, Wu Y, Huang S, Zhang R, Son YM, Li C, et al. Uncoupling of macrophage inflammation from self-renewal modulates host recovery from respiratory viral infection. Immunity. 2021;54(6):1200-1218.e9.[DOI]
-
54. Vannan A, Lyu R, Williams AL, Negretti NM, Mee ED, Hirsh J, et al. Spatial transcriptomics identifies molecular niche dysregulation associated with distal lung remodeling in pulmonary fibrosis. Nat Genet. 2025;57(3):647-658.[DOI]
-
55. Ruscitti C, Abinet J, Maréchal P, Meunier M, de Meeûs C, Vanneste D, et al. Recruited atypical Ly6G+ macrophages license alveolar regeneration after lung injury. Sci Immunol. 2024;9(98):eado1227.[DOI]
-
56. Cong B, Dong X, Yang Z, Yu P, Chai Y, Liu J, et al. Single-cell spatiotemporal analysis of the lungs reveals Slamf9+ macrophages involved in viral clearance and inflammation resolution. Cell Discov. 2024;10:104.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Abinet J, Ruscitti C, Garigliany M, Liégeois M, Radermecker C, Marichal T. Spatial single-cell profiling reveals macrophage niches in severe COVID-19 lungs. Myeloid Cells. 2026;1:202612. https://doi.org/10.70401/mc.2026.0014
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

 Get citation
Science Exploration Style

Abinet J, Ruscitti C, Garigliany M, Liégeois M, Radermecker C, Marichal T. Spatial single-cell profiling reveals macrophage niches in severe COVID-19 lungs. Myeloid Cells. 2026;1:202612. https://doi.org/10.70401/mc.2026.0014
copy
Share Link
copy