Immune evasion of senescent cells: Mechanisms, pathological significance, and targeted interventions

Qikun Ou
1
,
Jinran Zhao
2
,
Yuanlong Ge
1

,
Shu Wu
1,*
*Correspondence to:
Shu Wu, Key Laboratory of Regenerative Medicine of Ministry of Education, Institute of Aging and Regenerative Medicine, Department of Developmental & Regenerative Medicine, College of Life Science and Technology, Jinan University, Guangzhou 510632, Guangdong, China.
E-mail: wushu@jnu.edu.cn
Ageing Cancer Res Treat. 2026;3:202617. 10.70401/acrt.2026.0034
Received: April 21, 2026Accepted: August 10, 2026Published: August 10, 2026
Abstract
Cellular senescence is a stress-induced cell-cycle arrest program accompanied by the senescence-associated secretory phenotype (SASP). While senescent cells are typically eliminated through immune surveillance under normal physiological conditions, they tend to accumulate progressively during aging and in chronic diseases. This review summarizes current evidence suggesting that such persistence is attributable not only to immune system decline but also to active, cell-intrinsic mechanisms of immune evasion. We discuss how senescent cells escape clearance by weakening immune recognition, suppressing phagocytic removal, resisting apoptosis, remodeling the inflammatory and structural microenvironment through SASP, and activating inhibitory checkpoint pathways in aged tissues. Furthermore, we investigate the contribution of these mechanisms to representative age-related diseases across multiple organs. Finally, we highlight emerging therapeutic strategies aimed at targeting the immune evasion of senescent cells, including checkpoint modulation, chimeric antigen receptor (CAR)-based cell therapies, vaccination approaches, and other immune-bypass strategies. Collectively, these insights underscore immune evasion as a critical determinant of senescent cell persistence and a promising target for interventions in aging and age-related diseases.
Keywords
Cellular senescence, immune evasion, senescence surveillance, SASP, immunosenescence
1. Introduction
Cellular senescence is a stable and generally irreversible state of cell-cycle arrest triggered by a wide range of intrinsic and extrinsic stressors[1,2]. Senescent cells remain metabolically active and display a spectrum of distinctive phenotypic characteristics, including the secretion of the senescence-associated secretory phenotype (SASP), resistance to apoptosis, alterations in cell size, increased lysosomal content, mitochondrial dysfunction, and nuclear remodeling[3]. While senescence serves a protective role against malignancy and facilitates wound healing[4,5], its persistent accumulation drives chronic inflammation, tissue dysfunction, and age-related pathologies[1,2,6]. Emerging evidence indicates that the failure to eliminate these accumulated cells is itself a key driver of aging phenotypes, raising the fundamental question of why senescent cells persist in vivo.
Under physiological conditions, senescent cells can be recognized and eliminated by natural killer (NK) cells, macrophages, and T cells through a coordinated immunosurveillance process that recognizes senescence-associated surface ligands and secreted signals[7]. Nevertheless, in aged or diseased tissues, this surveillance system proves insufficient, not owing to its absence, but rather to its progressive subversion by three converging mechanisms: immunosenescence, which impairs immune effector function with age; inflammaging, which chronically reshapes the tissue microenvironment toward an inflammatory niche; and, most importantly, the active implementation of immune evasion strategies employed by senescent cells themselves[8].
In this review, we summarize the major mechanisms by which senescent cells evade immune surveillance and further discuss how senescent cell immune evasion contributes to the progression of age-related diseases. Finally, we highlight current and emerging therapeutic strategies targeting senescent-cell immune evasion, with a particular focus on immune-based interventions, and additional approaches designed to promote the selective elimination or functional control of pathogenic senescent cells.
2. Immune Cells Mediating Senescence Surveillance
Senescence immunosurveillance is a coordinated immune process that clears senescent cells, involving both innate and adaptive immunity[8,9]. Here we focus on the major immune effectors and how their functions are subverted in senescence contexts.
2.1 Immune effector cells targeted by senescent cell immune evasion
The immune-mediated clearance of senescent cells represents a critical process for maintaining tissue homeostasis. NK cells, macrophages, and T cells constitute the primary immune cell types involved in this process. However, senescent cells actively subvert this process through a spectrum of immune-evasion strategies deployed at each step of immune-mediated elimination (Table 1).
Table 1. Immune cell-mediated recognition and clearance of senescent cells.
| Immune Cell Type | Normal Function (Senescence Surveillance) | Subversion by Senescent Cells | References |
| NK cells | NKG2D-mediated activation of MICA/MICB/ULBP→perforin/granzyme-mediated cytotoxicity | ① NKG2D ligand shedding (MMP-mediated)→decoy effect ② HLA-E upregulation→NKG2A inhibitory signaling ③ ST8SIA1/GD3→disrupted immune synapse | [10-16] |
| Macrophages | TAM receptor/CD44-mediated phagocytic clearance | ① CD47-SIRPα “don’t eat me” signaling ② CD24-Siglec-10 phagocytosis inhibition ③ TAM receptor modulation→suppressed efferocytosis | [17-20] |
| CD4+ T cells | MHC-II-mediated antigen presentation→CD4+ CTL cytotoxicity | ① PD-L1 upregulation (p16-dependent)→PD-1 engagement ② SASP chemokine skewing→Treg recruitment ③ Altered MHC-II antigen presentation | [5,21] |
| CD8+ T cells | MHC-I-mediated antigen presentation→CTL cytotoxicity | ① HLA-E/NKG2A checkpoint→suppressed cytotoxicity ② PD-1/PD-L1 axis→functional exhaustion ③ Chronic SASP→immune exhaustion ④ ECM remodeling→physical barrier | [7,22-24] |
SASP: senescence-associated secretory phenotype; ECM: extracellular matrix; PD-L1: programmed death-ligand 1; PD-1: programmed cell death protein 1; HLA-E: human leukocyte antigen E; NKG2A: natural killer group 2 member A; CTL: cytotoxic T lymphocyte; MHC-Ⅱ: major histocompatibility complex class II; SIRPα: signal regulatory protein α; MMP: metalloproteinase; NK: natural killer; NKG2D: natural killer group 2 member D; ULBP: UL16-binding protein; MICA: MHC class I polypeptide-related sequence A; MICB: MHC class I polypeptide-related sequence B; CD4+: CD4-positive; CD8+: CD8-positive; CD47: cluster of differentiation 47; CD24: cluster of differentiation 24.
NK cells represent the most well-characterized immune effectors in the clearance of senescent cells. They recognize senescent cells primarily through the activating receptor natural killer group 2 member D (NKG2D), which binds stress-induced ligands MHC class I polypeptide-related sequence A (MICA) and UL16-binding protein (ULBP) family members upregulated on the senescent cell surface, triggering perforin/granzyme-mediated cytotoxicity[25]. Genetic deletion of the NKG2D receptor results in the accumulation of senescent hepatic stellate cells and exacerbates liver fibrosis in mice[10]. Senescent cells counter NK cell activity through multiple evasion strategies: metalloproteinase (MMP)-mediated shedding of NKG2D ligands creates a decoy effect[26]; upregulation of human leukocyte antigen-E (HLA-E) engages the inhibitory natural killer group 2 A (NKG2A) receptor[7,14,15]; and ST8SIA1/ganglioside 3 (GD3) signaling disrupts immune synapse formation[16]. These mechanisms collectively impair NK cell-mediated surveillance and contribute to senescent cell persistence.
Macrophages are key effectors for clearing senescent cells through phagocytic mechanisms. Under physiological conditions, macrophage-mediated clearance is regulated by TAM receptor tyrosine kinases (TYRO3, AXL, MER) and cluster of differentiation 44 (CD44), which mediate the recognition and engulfment of apoptotic and senescent cells[18,27,28]. Critically, senescent cells subvert macrophage function through multiple immune-evasion strategies: upregulation of cluster of differentiation 47 (CD47) engages the signal regulatory protein α (SIRPα) “don’t-eat-me” signal to inhibit phagocytosis[19]; upregulation of cluster of differentiation 24 (CD24) binds Siglec-10 on macrophages to suppress engulfment[19]; and promoting MerTK cleavage dampens efferocytosis efficiency[20]. These mechanisms collectively impair macrophage-mediated senescent cell clearance, contributing to the persistence of senescent cells in aged tissues.
In addition, adaptive immune cells participate in senescent-cell clearance in a context-dependent manner. CD4-positive cytotoxic T lymphocytes (CD4+ CTLs) can directly eliminate senescent tumor cells by recognizing antigens presented by major histocompatibility complex class II (MHC-II), even when MHC-II expression is limited to specific populations[5]. CD8-positive (CD8+) CTLs recognize major histocompatibility complex class Ⅰ (MHC-I)-presented antigens expressed on virtually all cells, and mediate target-cell elimination through cytotoxic granule release[9]. Although CD8+ CTLs serve as potent immune effectors, their activity is tightly regulated by inhibitory checkpoints. Among these, the HLA-E-NKG2A axis represents a critical checkpoint governing CD8+ T cell activity in both cancer and senescence; therapeutic blockade of NKG2A with antibodies such as monalizumab enhances CD8+ T cell-mediated antitumor immunity[7]. However, both the selectivity and efficiency of cytotoxic T cell responses decline with advancing age. Chronic SASP signaling promotes the recruitment of immunosuppressive regulatory T cells (Tregs) and drives T cell exhaustion[21,29]. Additionally, extracellular matrix (ECM) remodeling by senescent cells creates a physical barrier that limits T cell infiltration[23,24]. Engineering T cells with CARs to recognize tumor-associated antigens has achieved success in cancer immunotherapy. Since senescent cells display unique surface antigens, this strategy can be adapted to eliminate senescent cells that evade immunosurveillance, as exemplified by NKG2D-CAR-T cells, which target senescence-associated ligands to achieve selective clearance[30].
2.2 Molecular basis of immune recognition of senescent cells
Immune recognition of senescent cells is driven by characteristic alterations in both cell-surface ligand expression and secretory phenotypes. One of the best-defined mechanisms is the upregulation of stress-induced ligands, including MICA, MHC class I polypeptide-related sequence B (MICB), and ULBP family members, which enhance susceptibility to NK-cell recognition through NKG2D[10,31]. Importantly, these ligands function not only as markers but also as active mediators of immune surveillance across diverse senescence contexts. In parallel, senescent cells develop SASP, characterized by the release of cytokines and chemokines that shape the local microenvironment[4,5]. Notably, SASP recruits and activates immune cells, including NK cells, macrophages, and T cells, thereby facilitating immune-mediated clearance of senescent cells, while their persistent presence contributes to chronic low-grade inflammation and immune exhaustion[22,32]. Crucially, immune recognition is counterbalanced by inhibitory mechanisms. For instance, senescent cells can upregulate the non-classical MHC-I molecule HLA-E, which suppresses NK cell and CD8+ T cell cytotoxicity via interaction with NKG2A, thereby limiting immune-mediated elimination[7,33].
Thus, the fate of senescent cells, whether they are efficiently cleared or allowed to persist and accumulate in tissues, is determined by the dynamic balance between pro-clearance signals and immune inhibitory pathways. Understanding this balance is essential for developing therapeutic strategies that selectively eliminate harmful senescent cells to ameliorate age-related pathologies and extend healthspan.
3. Multilevel Architecture of Senescent Cell Immune Evasion
During aging and under conditions of chronic stress, immune surveillance becomes compromised, allowing senescent cells to persist and transition into a chronic, tissue-damaging state characterized by sustained SASP production[2,25]. Recent studies further indicate that senescent cells may actively contribute to impaired clearance by modulating immune responses within their local microenvironment, balancing immune activation and evasion to promote their persistence[26,34]. Consequently, the accumulation of senescent cells reflects not only an increased induction of senescence but also a context-dependent decline in immune-mediated clearance. These mechanisms can be conceptually organized into interconnected layers, including impaired recognition, defective clearance execution, resistance to cell apoptosis, microenvironmental remodeling, spatial restriction, and host-level immune decline (Figure 1).
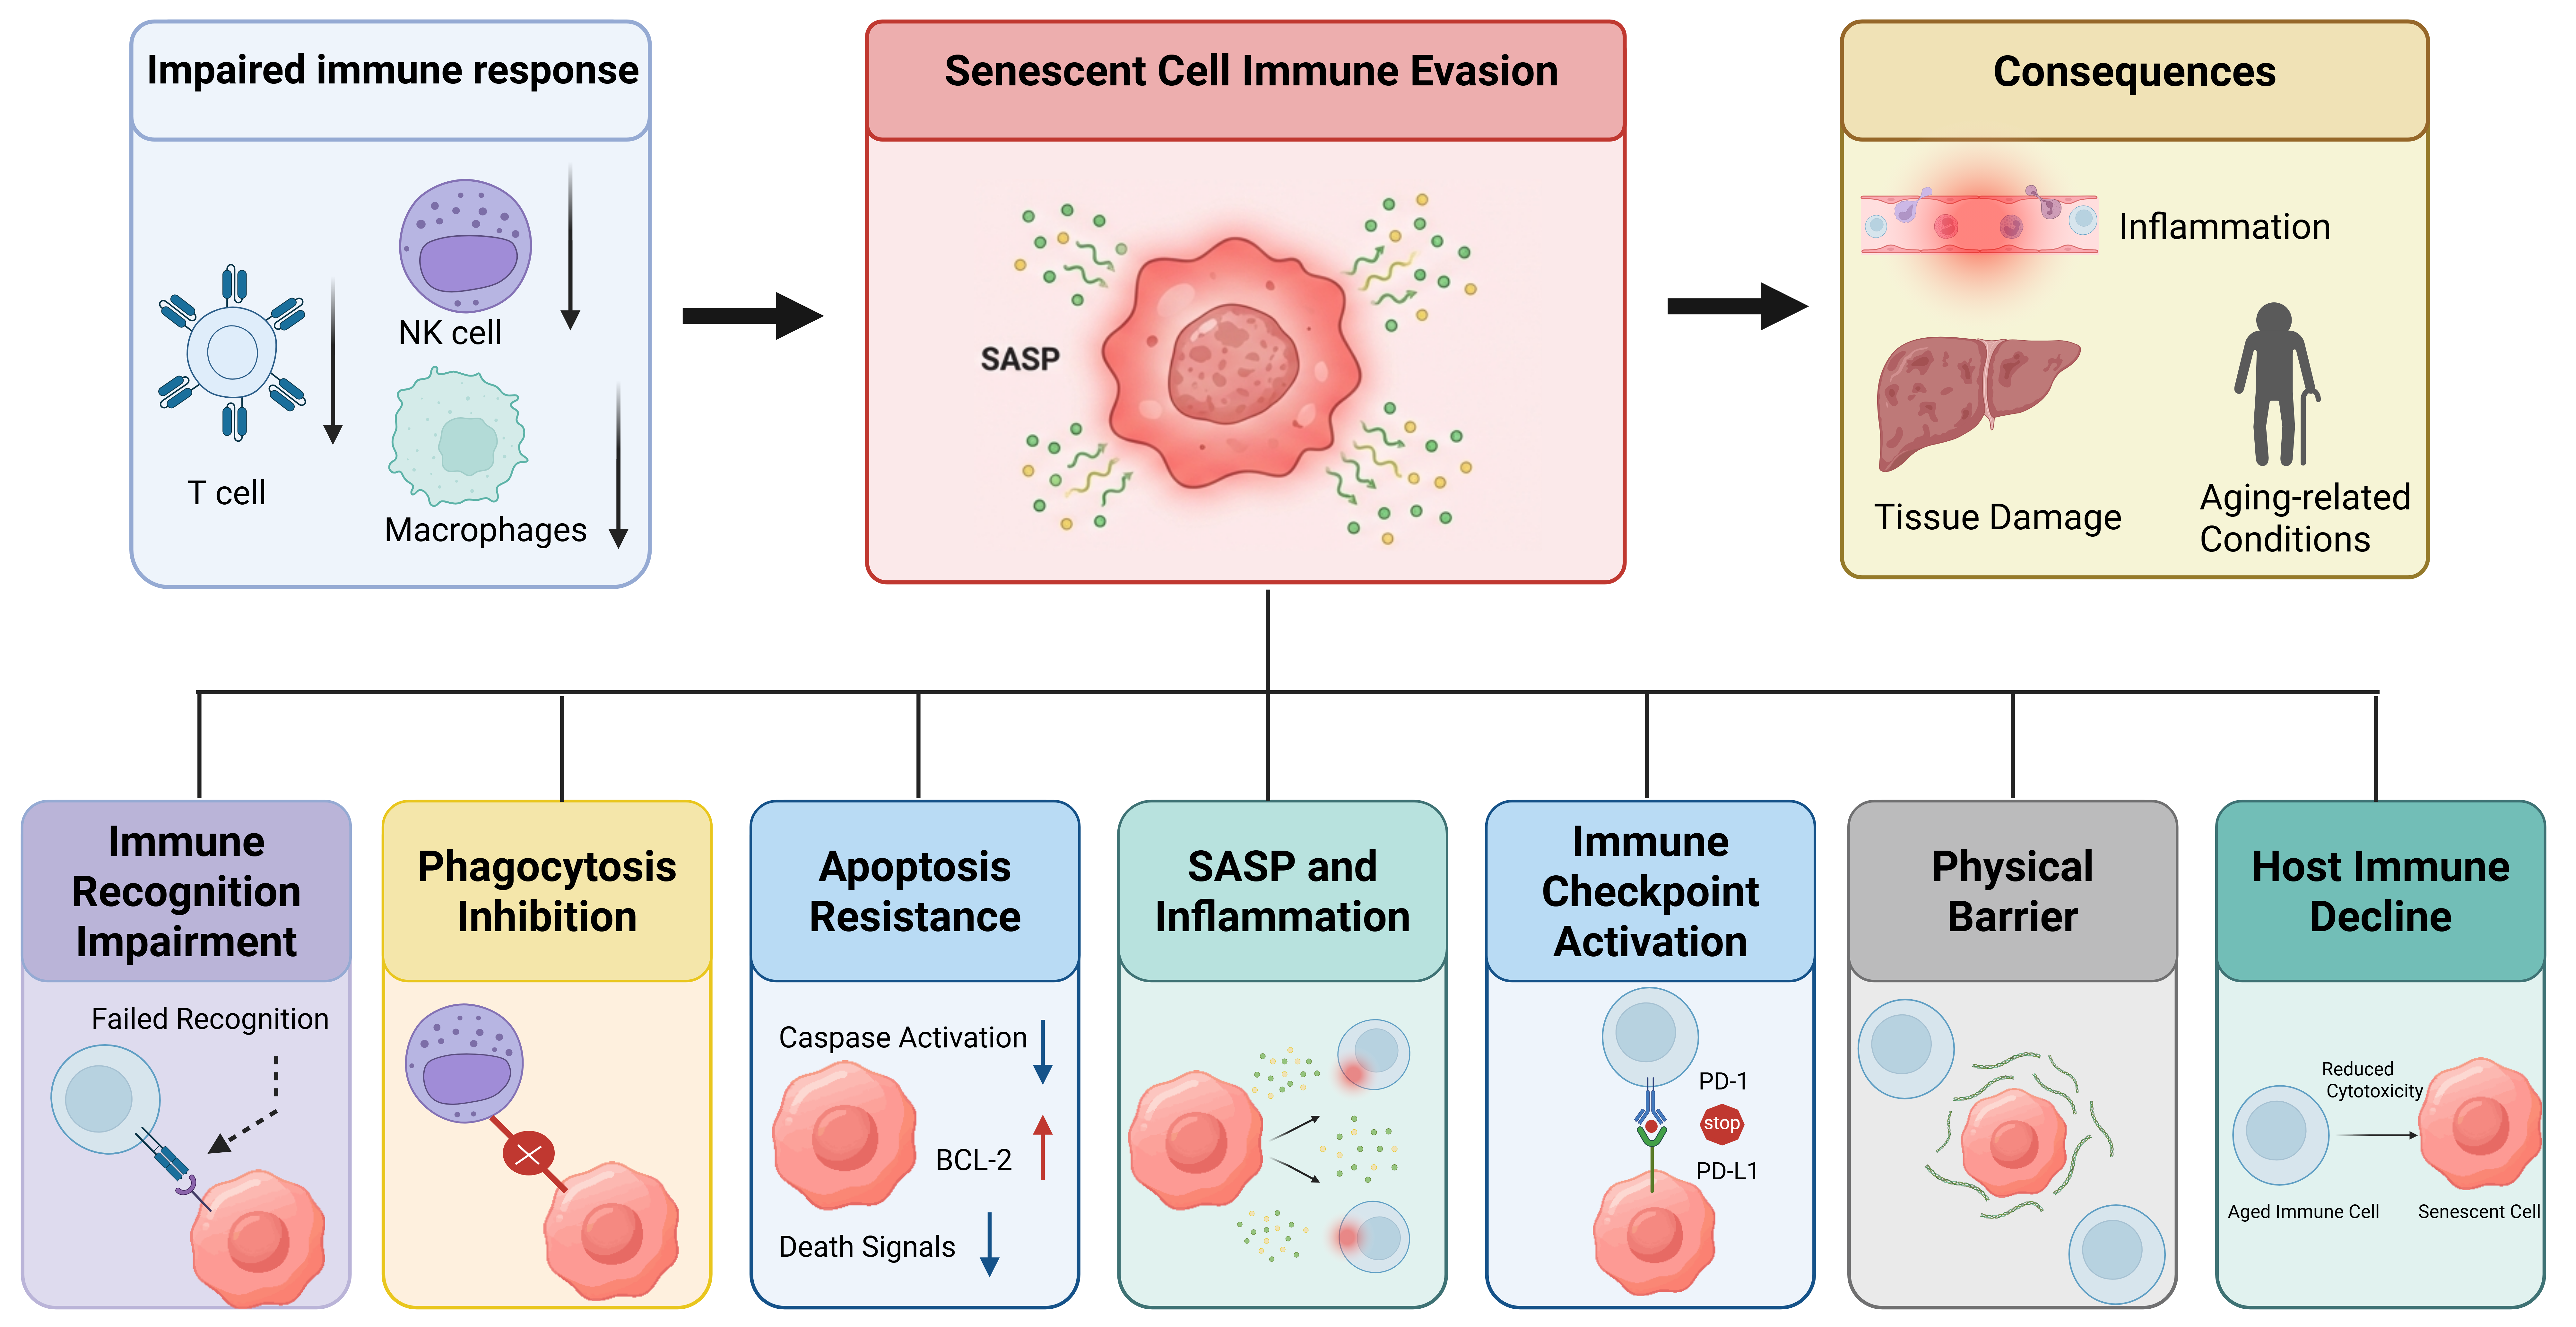
Figure 1. Mechanisms of immune evasion in senescent cells. Senescent cells evade immune-mediated clearance through coordinated alterations at multiple levels, including impaired immune recognition, inhibition of phagocytosis, resistance to apoptosis, persistent SASP-associated inflammation, immune checkpoint activation, and physical barriers that restrict immune cell access. In parallel, host-level immune decline further reduces cytotoxic capacity. Together, these mechanisms promote senescent cell persistence, chronic inflammation, and tissue damage. Created in BioRender. Wang, L. (2026) https://www.biorender.com/qebzwiy. NK: natural killer; SASP: senescence-associated secretory phenotype; PD-1: programmed cell death protein 1; PD-L1: programmed death-ligand 1; BCL-2: B-cell lymphoma 2.
3.1 Attenuated immune recognition: How senescent cells become less visible
Target recognition initiates the immune clearance cascade, yet senescent cells actively undermine this process. Specifically, effective immune-mediated clearance of senescent cells requires precise recognition by innate and adaptive effectors. However, senescent cells evade this process by shifting the balance between activating and inhibitory signals, thereby reducing their “immunogenic visibility”. Although NKG2D-dependent surveillance can facilitate the elimination of senescent cells, alterations in ligand availability, including the release of soluble or vesicle-associated NKG2D ligands, can attenuate NKG2D signaling and impair NK cell activation[10,14]. In parallel, the upregulation of inhibitory ligands such as HLA-E engages NKG2A/CD94, thereby increasing the activation threshold for cytotoxic responses[7,14,15]. Recent studies further reveal that senescent cells upregulate ST8SIA1, which synthesizes and presents the surface-associated inhibitory ligand GD3, directly suppressing NK cell degranulation and cytotoxicity. Notably, oncogene-induced senescence lacks ST8SIA1 upregulation and is thus cleared by NK cells[16].
Beyond surface ligand modulation, senescent cells may further evade immunity by altering antigen presentation programs and interferon-associated signaling pathways[9,35-37]. In therapy-induced or tumor-associated senescence, changes in MHC class I expression and interferon response pathways can reshape T-cell recognition and effector priming. Such alterations may variably enhance or impair adaptive immune engagement depending on the biological context, suggesting that senescence-associated immunogenicity is not uniform but dynamically regulated[9,35,36]. Importantly, in physiological aging, chronic low-grade inflammation and progressive immune remodeling drive age-associated changes in host immune surveillance, which may consequently impair the efficiency of senescent-cell clearance[38,39]. In addition, senescent-cell immune-evasion mechanisms, such as HLA-E-mediated inhibition of NK- and CD8+ T-cell cytotoxicity[7], represent a distinct mechanism. Impaired immune surveillance can accelerate senescent-cell accumulation in vivo[25].
3.2 Inhibition of phagocytic clearance: How senescent cells signal “don’t eat me”
The next critical step following immune recognition is phagocytic removal. However, even after immune recognition has occurred, the effective elimination of senescent cells critically depends on the efficiency of macrophage-mediated phagocytosis and efferocytosis. Unlike the mechanisms of inhibition of NK cells, senescent cells suppress macrophages primarily through the upregulation of surface-associated “don’t eat me” signals via two key mechanisms.
The major pathway is the CD47-SIRPα signaling axis. Senescent cells upregulate CD47 together with its modifying enzymes glutaminyl-peptide cyclotransferase/glutaminyl-peptide cyclotransferase-like (QPCT/QPCTL), thereby promoting a senescence-associated efferocytosis suppression phenotype[19]. Elevated CD47 inhibits macrophage-mediated clearance via activation of the SIRPα-SHP-1 signaling axis, which triggers phosphorylation of immunoreceptor tyrosine-based inhibitory motif (ITIM) and immunoreceptor tyrosine-based switch motif (ITSM) within SIRPα, recruitment of SHP-1/2 phosphatases, and attenuation of pro-phagocytic signaling cascades[40,41]. The alternative pathway is the CD24-Siglec-10 signaling axis. In senescent human epithelial cells, this additional inhibitory pathway manifests as upregulation of CD24, which binds to Siglec-10 receptors on macrophages and similarly delivers a “don't eat me” signal. Notably, when the CD47 pathway is genetically ablated, these cells promptly engage the CD24 pathway as a compensatory mechanism to evade clearance[19]. This redundancy highlights the sophisticated and resilient nature of immune evasion strategies employed by senescent cells.
3.3 Resistance to apoptosis: Why senescent cells are difficult to eliminate
The execution phase of immune-mediated killing ultimately depends on the induction of target cell apoptosis. Although cellular senescence and apoptosis can be triggered by overlapping stressors, they represent fundamentally distinct cellular outcomes. Crucially, senescent cells are characteristically resistant to apoptosis, reflecting extensive rewiring of survival pathways that increases the threshold for cell death induction[42].
Senescent cells have been reported to downregulate pro-apoptotic proteins such as BCL-2 homologous antagonist/killer (BAK) and BCL-2-associated X protein (BAX) while upregulating anti-apoptotic BCL-2 family members including B-cell lymphoma 2 (BCL-2), BCL-2-like protein 1 (BCL-xL), and BCL-2-like protein 2 (BCL-W), thereby stabilizing mitochondrial integrity and elevating the intrinsic apoptotic threshold[43]. The BCL-2 homology 3 (BH3) mimetic navitoclax (ABT-263), which targets BCL-2, BCL-XL, and BCL-W, selectively induces apoptosis in multiple types of senescent cells, supporting the concept that senescent cells rely on anti-apoptotic BCL-2 family proteins for persistence[44].
Beyond modulating the intrinsic pathway, senescent cells can also interfere with extracellular death signals to counteract extrinsic apoptotic pathways. In senescent renal tubular epithelial cells, decoy receptor 2 (DcR2) is markedly upregulated and functions as a “decoy receptor” that competitively binds death ligands such as TNF-related apoptosis-inducing ligand (TRAIL) without transmitting apoptotic signals. Moreover, DcR2 effectively blocks downstream signaling of the death receptor pathway by upregulating FLICE-like inhibitory protein (FLIP), an inhibitor of caspase-8, thereby reducing caspase-8 activity[45]. Additionally, DcR2 interacts with glucose-regulated protein 78 (GRP78), further activating the anti-apoptotic protein kinase B (Akt) signaling pathway[43].
In addition to these canonical apoptotic pathways, senescent cells employ non-canonical survival mechanisms. Senescent cells downregulate the inner mitochondrial membrane peptidase subunit 2 (IMMP2L), blocking the processing of glycerol-3-phosphate dehydrogenase (GPD2) and preventing the activation of apoptosis-inducing factor (AIF). This dual inhibition reprograms phospholipid metabolism and suppresses caspase-independent cell death, thereby ensuring senescent cell survival under oxidative stress[46]. Furthermore, oxidative stress-induced senescent cells activate protective autophagy via the SIRT1/AMP-activated protein kinase (AMPK)/mechanistic target of rapamycin (mTOR) pathway, which confers resistance to oxidative stress-induced apoptosis[47].
3.4 SASP-driven immune and microenvironmental remodeling: From transient signaling to persistent tissue burden
The SASP influences the immune clearance cascade at multiple levels, from immune cell recruitment to effector activation and tissue remodeling. This multifaceted impact is driven by a dynamic secretory phenotype that includes pro-inflammatory cytokines, chemokines, growth factors, and matrix-remodeling enzymes, all of which collectively remodel the tissue microenvironment[4,5]. Its composition is regulated at transcriptional, epigenetic, and signaling levels, and varies by cell type. Upstream innate immune sensing pathways have been implicated in linking intracellular damage to inflammatory signaling outputs. Specifically, cytoplasmic chromatin fragments (CCFs), arising from nuclear instability in senescent cells, have been shown to activate the cyclic guanosine monophosphate (GMP)-adenosine monophosphate (AMP) synthase-stimulator of interferon genes (cGAS-STING) pathway, thereby promoting type I interferon responses and reinforcing inflammatory signaling programs[48]. Similarly, endogenous retroviral elements (ERVs) or retrotransposable elements (TEs) reactivation induces a viral mimicry state characterized by double-stranded DNA (dsDNA) accumulation and engagement of innate immune sensors, further contributing to interferon-associated signaling[49,50]. These upstream sensing mechanisms may act in concert to shape SASP composition and magnitude, providing a mechanistic link between genomic instability and secretory phenotypes.
In physiological or transient contexts, SASP factors participate in tissue remodeling and microenvironmental communication, integrating senescent cells into tissue repair programs. However, when senescent cells persist and SASP signaling becomes chronic, sustained secretion of inflammatory and matrix-modifying factors contributes to tissue dysfunction and pathological remodeling[51-53]. Prolonged activation of upstream innate sensing pathways further reinforces this chronic inflammatory state, coupling SASP persistence to sustained upstream signaling[48,54].
Critically, the chronic SASP contributes to immune evasion by senescent cells. Persistent secretion of inflammatory cytokines can create an immunosuppressive environment that dampens effective anti-senescent immune responses. Moreover, SASP-mediated matrix remodeling and extracellular matrix accumulation may physically shield senescent cells from immune infiltration and surveillance[52,55-57]. Evidence from musculoskeletal models shows that senescent cells impair matrix remodeling and alter tissue architecture, which may impede immune cell access[57]. Thus, beyond its well-recognized roles in tissue dysfunction and age-related pathology, chronic SASP actively promotes immune evasion, thereby enabling senescent cell accumulation and persistence.
3.5 Immune checkpoints and exhaustion axes: Inhibitory synapses that restrain the execution of senescence clearance
At the immune activation step, inhibitory checkpoints serve as critical gatekeepers that senescent cells exploit to attenuate cytotoxic responses. In therapy-induced senescence (TIS) or chronically inflamed and aged tissues, senescent cells are not devoid of immunogenic features; rather, they upregulate inhibitory immune checkpoint ligands that attenuate effector cell cytotoxicity at the immune synapse, thereby promoting immune evasion[7,58,59].
The programmed cell death protein 1 (PD-1)/programmed death-ligand 1 (PD-L1) axis is the most extensively characterized checkpoint mechanism regulating senescent cell immune clearance. Senescent cells are known to express high levels of PD-L1, which interacts with PD-1 on immune cells such as cytotoxic CD8+ T cells and NK cells, leading to the suppression of their cytotoxic functions and promoting immune evasion[58]. PD-L1+ senescent cells accumulate with age and resist immune clearance, whereas PD-L1- counterparts remain susceptible despite retaining SASP activity[58]. Mechanistically, p16-mediated inhibition of CDK4/6 enhances PD-L1 protein stability by downregulating its ubiquitin-dependent proteasomal degradation, and p16+ senescent alveolar macrophages display elevated PD-L1 expression associated with a local immunosuppressive environment[59]. Importantly, Fcγ receptor-activating anti-PD-L1 antibodies facilitate clearance of PD-L1+/p16+ cells, confirming a functional role of this checkpoint axis in limiting immune elimination[59].
Beyond PD-1/PD-L1, the NKG2A/HLA-E axis constitutes an additional inhibitory pathway linking senescent target cells to cytotoxic lymphocytes. Senescent human dermal fibroblasts have been shown to upregulate the non-classical MHC molecule HLA-E, which engages the inhibitory receptor NKG2A on NK cells and highly differentiated CD8+ T cells, thereby suppressing cytotoxic responses[7]. Blockade of HLA-E/NKG2A interactions enhances NK and CD8+ T cell degranulation and cytotoxic activity, indicating that this inhibitory checkpoint directly reduces the likelihood of senescent cell clearance[7,60].
Critically, these checkpoint-mediated evasion mechanisms operate within an aging-associated immune environment predisposed to functional exhaustion, as evidenced by increased expression of inhibitory receptors and heightened sensitivity to the action of checkpoint ligands on senescent cells[23,61,62]. Thus, the expression of checkpoint ligands by senescent cells does not merely dampen acute cytotoxic signaling; rather, it functions within this exhausted milieu to stabilize senescent cell persistence and reinforce immune evasion[23,58,59].
3.6 Spatial/structural immune evasion: When tissue architecture prevents clearance
Beyond molecular recognition and execution, effective immune clearance also requires physical access to target cells within the tissue architecture. Senescent cells actively remodel their surroundings by driving fibrosis and excessive ECM deposition, which not only alter tissue architecture and mechanical properties but also physically impede immune cell migration, infiltration, and stable engagement with target cells[23,24]. Consequently, immune cells may infiltrate the lesion yet remain excluded from its fibrotic core, resulting in an “immune-present but functionally ineffective” state that severely compromises productive clearance.
Critically, the ECM is not a passive byproduct but an active mediator of immune evasion. Senescent cells and their SASP factors encompass not only soluble inflammatory mediators but also ECM components and ECM-remodeling enzymes. These matrix-associated SASP factors contribute to alterations in ECM composition and organization, which, in certain pathological contexts, progress toward fibrosis and matrix stiffening, thereby reinforcing a structurally restrictive microenvironment[56,62-64]. In chronic lesions such as atherosclerotic plaques, ECM proteins and soluble mediators collectively shape the local biomechanical and biochemical landscape, modulating inflammatory signaling and cellular behavior[65-67].
Taken together, these findings suggest that matrix remodeling and architectural reorganization constitute upstream spatial constraints, promoting senescent cell persistence by restricting immune access and effector engagement. As such, the senescent ECM constitutes a physical barrier driving senescence-associated immune evasion.
3.7 Host factors: Immunosenescence and inflammaging as the permissive background
Superimposed on cell-intrinsic evasion mechanisms, immunosenescence and inflammaging impair immune clearance and synergize with senescent cells’ intrinsic programs to drive their persistence in aged hosts.
Immunosenescence, characterized by age-related thymic involution that both reduces the naïve T-cell pool and narrows the T-cell receptor (TCR) repertoire, weakens sustained immune surveillance[68]. It directly amplifies the impact of PD-L1 upregulation by senescent cells (Section 3.5), compounded by a diminished and less diverse T-cell pool that renders the inhibitory effect of PD-1/PD-L1 checkpoint engagement proportionally more potent[58,59,69]. Age-associated NK-cell dysfunction and the senescence-associated evasion programs of NKG2D-ligand shedding[14,70] and HLA-E upregulation[7] (Section 3.1) are concurrent, mutually reinforcing features of immunosenescence that collectively lower the barrier for senescent cells to evade phagocytic clearance via “don’t-eat-me” signals[19] (Section 3.2). Concurrently, inflammaging establishes a chronic inflammatory milieu that promotes immunosuppressive circuitry and drives PD-1/PD-L1 checkpoint pathways, with senescent cells further enhancing immune resistance through increased PD-L1 stability[6,59,71,72]. Inflammatory cytokines further reinforce evasion of NK cell- and T cell-mediated clearance, creating a bidirectional amplification loop: inflammaging promotes evasion, and the SASP from persisting senescent cells sustains inflammaging, a self-reinforcing cycle that is negligible in young tissues. Together, they provide the essential physiological context that renders the evasion mechanisms in Section 3.1, Section 3.2, Section 3.3, Section 3.4, Section 3.5, and Section 3.6 pathologically relevant in the aged host, forming a permissive background for progressive clearance failure and accelerated tissue aging and pathology.
Ultimately, the immune evasion of senescent cells should not be attributed to a single molecular defect but rather viewed as a result of a complex, multilayered regulatory network in which multiple distinct mechanisms, ranging from cell-intrinsic resistance and inhibitory reprogramming to host-level decline, are intertwined. The outcome of these coupled systems underscores that effective therapeutic targeting will likely require combinatorial rather than monotherapeutic strategies.
4. Diseases Resulting from the Immune Evasion of Senescent Cells
Under physiological conditions, senescent cells exist transiently as an adaptive response and are efficiently cleared by the innate immune system. However, once senescent cells acquire immune-evasive properties, this precise clearance mechanism fails, allowing senescent cells to persist long-term and progressively accumulate in tissues[15]. Beyond occupying tissue space, their active SASP continuously releases pro-inflammatory factors, chemokines, proteases, and growth factors into the microenvironment, converting a beneficial senescence response into a chronic, self-perpetuating pathological state[72], which contributes directly to the development and progression of a broad spectrum of age-related diseases, including cardiovascular diseases, cancers, idiopathic pulmonary fibrosis, as well as other tissue pathology (Figure 2).
Figure 2. Diseases associated with senescent-cell immune evasion. Immune evasion enables the accumulation of senescent cells and sustained SASP activity, leading to chronic inflammation, impaired immune clearance, and tissue dysfunction. These processes contribute to the development and progression of multiple age-related diseases across organ systems, including CVDs, cancers, IPF, liver diseases, metabolic disorders, and osteosarcopenia. Senescent cells employ shared immune evasion mechanisms, including CD47-SIRPα “don’t-eat-me” signaling, PD-L1/PD-1 checkpoint engagement, HLA-E-NKG2A inhibitory signaling, and SASP/ECM remodeling, alongside disease-specific mechanisms, such as the STAT1-STING axis in CVDs, PGE2/TGF-β-Treg signaling in IPF, and altered antigen visibility/T-cell exhaustion in cancers. Created in BioRender. Wang, L. (2026) https://www.biorender.com/kzwyf16. PD-L1: programmed death-ligand 1; PD-1: programmed cell death protein 1; HLA-E: human leukocyte antigen E; NKG2A: natural killer group 2 member A; SASP: senescence-associated secretory phenotype; IPF: idiopathic pulmonary fibrosis; ECs: endothelial cells; VSMCs: vascular smooth muscle cells; NK: natural killer; CAFs: cancer-associated fibroblasts; AMs: alveolar macrophages; PGE2: prostaglandin E2; CVDs: cardiovascular diseases; SIRPα: signal regulatory protein α; MMPs: metalloproteinases; ECM: extracellular matrix; TNF-α: tumor necrosis factor alpha; IL: interleukin; AECs: alveolar epithelial cells; QPCT/QPCTL: glutaminyl-peptide cyclotransferase/glutaminyl-peptide cyclotransferase-like; TGF-β: transforming growth factor-β; VEGF: vascular endothelial growth factor; CD47: cluster of differentiation 47; Treg: regulatory T cell.
4.1 Cardiovascular diseases (CVDs)
CVDs represent the leading cause of mortality and are among the foremost causes of disability globally. These disorders encompass a range of heart and vascular diseases and are associated with the biological process of aging[73]. In aging cardiovascular tissues, multiple cell types, including endothelial cells (ECs), vascular smooth muscle cells (VSMCs), foamy macrophages, and cardiomyocytes, undergo senescence and evade immune clearance through distinct mechanisms, thereby leading to their persistent accumulation and progressive tissue dysfunction.
In atherosclerosis, senescent ECs are present within plaque[74] and establish a pro-inflammatory environment through the secretion of SASP factors, including interleukin (IL)-1α, IL-6, IL-8, and chemokine (C-C motif) ligand 2 (CCL2) [75], which promote monocyte adhesion[76] and may increase endothelial permeability, creating a recruitment-biased inflammatory niche rather than an efficient clearance response. Within this lesional niche, CD47 is overexpressed on multiple cell types, delivering a “don’t-eat-me” signal that prevents macrophage-mediated clearance of diseased vascular cells and promotes necrotic core expansion[77,78]. This phagocytosis-resistant phenotype is mechanistically reinforced by the CD47-QPCT/L axis, through which senescent cells actively suppress macrophage-mediated removal[19]. Meanwhile, senescent VSMCs aggravate the inflammatory burden by secreting a pro-inflammatory SASP profile[79]. In addition to these vascular wall-resident cells, senescent foamy macrophages, beyond exhibiting impaired phagocytic function and resistance to apoptosis[80], further undermine immune surveillance by upregulating PD-L1, which engages PD-1 on infiltrating T cells to suppress cytotoxic clearance[59]. By evading immune clearance through these converging mechanisms, senescent ECs, VSMCs, and foamy macrophages persist within the atherosclerotic plaque. Their sustained SASP output then perpetuates local inflammation and necrotic core expansion, directly linking immune evasion to atherosclerotic progression[19,78].
In heart failure, particularly heart failure with preserved ejection fraction (HFpEF), senescent cardiomyocytes and cardiac fibroblasts accumulate. Senescent cardiomyocytes employ the CD47-SIRPα “don’t-eat-me” axis to resist macrophage-mediated phagocytosis[81], and their senescent phenotype is further consolidated by the STAT1-STING axis, in which interferon (IFN)-γ-driven STAT1 phosphorylation upregulates STING to establish a pro-inflammatory SASP that reinforces immune resistance[82]. Additionally, senescent cardiomyocytes impair post-infarction repair by inducing paracrine senescence in neighboring cells[83]. In parallel, senescent cardiac fibroblasts contribute to immune evasion primarily through spatial niche remodeling. Specifically, the SASP secreted by senescent cardiac fibroblasts promotes collagen deposition and activates neighboring fibroblasts, creating a self-reinforcing fibrotic cycle that remodels the extracellular matrix and ultimately drives ventricular stiffness and diastolic dysfunction, hallmark features of the failing aging heart[84]. Together, these strategies enable senescent cardiomyocytes to escape phagocytosis and drive fibroblasts to create an immune-excluded microenvironment, allowing their sustained accumulation and the progressive functional decline seen in aged failing hearts.
Thus, immune evasion is not merely a correlate of CVD pathology but a causal mechanism: it permits senescent cells to escape clearance, and their continued presence directly drives the vascular and cardiac dysfunction observed during cardiovascular aging. Therapeutic strategies targeting immune evasion of senescent cells represent a promising avenue for the treatment of cardiovascular disease.
4.2 Cancers
Cancers are often recognized as age-associated diseases, in which genomic instability, epigenetic alterations, and chronic inflammation associated with advancing age collectively facilitate tumorigenesis. Cellular senescence serves as an intrinsic antitumor barrier by enforcing stable cell-cycle arrest in premalignant or damaged cells[4,5]. However, senescent cells within the tumor microenvironment (TME), including cancer cells, immune cells, and stromal cells, link senescent-cell accumulation to immune evasion and tumor progression.
Senescent cancer cells induced by therapeutic stress initially exhibit strong immunogenicity. This is driven by the release of alarmins and SASP, which collectively enhance antigen presentation to DCs and promote robust activation of both CD4+ and CD8+ T cells, thereby favoring immune-mediated clearance[9,37]. However, when senescent cells persist within the TME over extended periods without effective clearance, their function shifts from “immune activation” to “immune suppression”. Persistent senescent tumor cells can engage checkpoint and recognition-evasion pathways, including PD-L1 upregulation, altered antigen visibility, and HLA-E/NKG2A-mediated inhibition of NK and CD8+ T-cell cytotoxicity[35]. Sustained activation of inflammatory signaling pathways, such as nuclear factor kappa B (NF-κB) and cGAS-STING, not only maintains SASP expression but also reshapes its biological properties, creating a temporal switch from immunogenicity to immune evasion[48,85,86].
Notably, immune cells and stromal cells within the TME can also undergo senescence, further compromising antitumor therapy. Senescent T cells are often defined by cluster of differentiation 27/28 (CD27/28) downregulation and cluster of differentiation 57 (CD57)/killer-cell lectin-like receptor G1 (KLRG-1) upregulation[87]. These cells exhibit low proliferative activity and impaired telomerase induction upon T-cell receptor activation[88,89]. Nevertheless, they retain cytotoxic activity and secrete substantial amounts of proinflammatory cytokines, contributing to SASP[87,90]. Accumulating evidence indicates that senescent T cells serve as critical mediators of immune suppression and actively promote tumor development and progression[91-93]. Metabolic interventions, particularly those targeting lipid metabolism, have shown promise in preventing T cell senescence and enhancing tumor immunotherapy[94].
Senescent macrophages polarize toward an M2-like phenotype with impaired phagocytosis and antigen presentation capacities, thereby limiting adaptive immune activation. Senescent NK cells display reduced killing capacity and impaired immune surveillance[95], and these defects are further exacerbated by myeloid-derived suppressor cell (MDSC) infiltration[96,97]. Meanwhile, senescent cancer-associated fibroblasts (CAFs) have been shown to produce a robust SASP and suppress NK-cell cytotoxicity, promoting tumor progression and recurrence[55,98-100]. Senescent endothelial cells alter vascular function and secrete SASP factors, such as C-X-C motif chemokine ligand 12 (CXCL12), thereby facilitating tumor cell migration and metastasis[98].
This multilayered immune-evasion strategy permits senescent cells to withstand immune surveillance and persist within the TME. Their accumulated presence fosters an immune-resistant niche, which in turn amplifies a self-reinforcing immunosuppressive loop that impairs residual effector cell function. Consequently, this cascade drives therapeutic resistance, facilitates tumor relapse, and portends poor clinical prognosis.
4.3 Idiopathic pulmonary fibrosis (IPF)
IPF is a progressive, fatal lung disease characterized by aberrant wound healing and excessive ECM deposition, with cellular senescence emerging as a central pathogenic driver[56]. In IPF lungs, multiple cell types, including type II alveolar epithelial cells (AECs), fibroblasts, and endothelial cells, exhibit hallmark features of senescence, accumulating in a microenvironment permissive for immune evasion-driven disease progression[56].
Senescent AECs are overproducers of prostaglandin E2 (PGE2) within the aged lung, which impairs the proliferation of alveolar macrophages (AMs)[101], thereby creating an immunosuppressive alveolar microenvironment that protects senescent AECs from immune clearance. Given that cellular senescence of AECs is a primordial driver and independent risk factor for IPF progression[102-104], this PGE2-driven immune evasion mechanism likely represents a key pathway by which senescent AECs persist in the IPF lung. Additionally, senescent lung epithelial cells upregulate CD47, the “don’t eat me” signal to block macrophage-mediated clearance, allowing the persistence of apoptotic and senescent cells[105]. The failure to clear these cells, compounded by age-related immune dysfunction, establishes a vicious cycle that makes them refractory to elimination, fuels persistent inflammation and fibroblast activation, directly driving fibrotic progression.
Beyond epithelial cells, senescent fibroblasts in IPF lungs employ distinct immune-evasion strategies that further perpetuate fibrosis. Specifically, they selectively express HLA-E, the high-affinity ligand for the NK cell inhibitory receptor NKG2A, which engages NKG2A+ NK cells and suppresses their granzyme B-mediated cytotoxicity[60]. Concurrently, IPF fibroblast subpopulations upregulate PD-L1 and CD47, which cooperate to inhibit T cell activation and block macrophage clearance, respectively[106]. These immune-evasive fibroblasts also secrete transforming growth factor-β (TGF-β), which promotes the accumulation of Tregs within the fibrotic niche while simultaneously suppressing effector T cell function, thereby reinforcing a broadly immunosuppressive microenvironment that protects both senescent AECs and fibroblasts from immune-mediated clearance[107,108]. In addition, the stiff fibrotic ECM in IPF, driven by crosslinked collagen, elastin, and proteoglycans[109], may create a physical barrier that further impedes immune cell infiltration into fibrotic foci.
Thus, senescent AECs and fibroblasts in IPF exploit both molecular (PGE2, CD47, HLA-E/NKG2A, PD-L1, TGF-β/Treg) and structural (stiff ECM) immune-evasion mechanisms to evade elimination. This immune evasion enables the uncontrolled persistence of senescent cells, which in turn sustains a feed-forward loop of inflammation, TGF-β-mediated fibroblast activation, and progressive ECM deposition, ultimately driving the relentless fibrotic remodeling that defines IPF pathogenesis.
4.4 Other diseases
Beyond CVDs, cancers, and IPF, several additional age-related disorders show persistent senescent-cell accumulation and impaired clearance, but their immune-evasion mechanisms have not been sufficiently studied.
Chronic liver diseases, spanning metabolic dysfunction-associated steatotic liver disease (MASLD), liver fibrosis, cirrhosis, and hepatocellular carcinoma (HCC), represent a spectrum of pathologies in which cellular senescence is increasingly recognized as an intertwined driver of disease progression. Multiple hepatic cell types, such as hepatocytes, hepatic stellate cells (HSCs), liver sinusoidal endothelial cells (LSECs), and Kupffer cells, become senescent under metabolic stress, lipotoxicity, and DNA damage[110,111]. In MASLD, failed clearance of senescent hepatocytes amplifies metabolic inflammation and promotes progression to steatohepatitis[112,113]. In fibrosis, senescent cells secrete a pro-inflammatory SASP that activate HSCs, driving excessive ECM deposition, while senescent HSCs themselves resist clearance and further amplify fibrogenesis[114,115]. In cirrhosis, persistent senescent cells contribute to hepatocellular dysfunction, portal hypertension, and progressive scar tissue replacement[116,117]. Critically, in HCC, the accumulation of senescent cells fosters a chronically inflamed, immunosuppressive microenvironment that promotes immune evasion and malignant transformation[118], with failed immune clearance of senescent hepatocytes under chronic injury serving as a key link between chronic liver disease and HCC[5,117].
In adipose-centered metabolic disease, senescent adipocytes and adipose progenitor cells secrete IL-6, TNF-α, and MCP-1, promoting macrophage infiltration and chronic inflammatory recruitment[119,120]. These SASP factors not only directly interfere with insulin signaling pathways (e.g., by upregulating suppressor of cytokine signaling 1/3 (SOCS1/3) to promote ubiquitination and degradation of insulin receptor substrate 1/2 (IRS1/2))[121], but also suppress the adipogenic capacity of neighboring non-senescent adipose progenitor cells in a paracrine manner[122]. Notably, senescent cells suppress the differentiation potential of adipose progenitor cells and reduce the replenishment of functional adipocytes, forcing existing adipocytes to undergo compensatory hypertrophy[123-125]. These hypertrophic adipocytes, coupled with senescence-related reduction in vascular density, collectively contribute to adipose tissue hypoxia[126], which further activates HIF-1α signaling, promoting ECM deposition and fibrosis, while SASP synergizes with hypoxia to form a vicious cycle, ultimately leading to adipose tissue endocrine dysfunction, insulin resistance, and systemic metabolic disorders[120,127].
Osteoporosis and sarcopenia are two common age-related degenerative diseases, characterized by bone loss, destruction of bone microarchitecture, and decline in skeletal muscle mass and function, respectively, often co-occurring as “osteosarcopenia”, which together significantly increase the risk of falls, fractures, and disability in older adults[128]. In osteoporosis, multiple cell types exhibit senescence phenotypes with aging, including osteocytes, osteoblasts, osteoclasts, and bone marrow mesenchymal stem cells (BMSCs). Senescent osteoblasts and osteocytes continuously secrete IL-6, TNF-α, receptor activator of nuclear factor-kappa B ligand (RANKL), and matrix MMPs to generate a chronic low-grade inflammatory microenvironment, ultimately leading to bone loss, destruction of bone microarchitecture, and an increased risk of fractures[129]. A recent study has revealed that targeting a ganglioside-based immune checkpoint immunotherapy decreases age-related bone remodeling associated with osteoarthritis (OA) disease[16]. In sarcopenia, the major senescent cell populations, including muscle stem cells (MuSCs), fibro-adipogenic progenitors (FAPs), macrophages (M1 and M2), ECs, smooth muscle cells (SMCs), and Schwann cells (SWCs), collectively establish an intricate cellular network through their specific senescent characteristics and SASP[130]. Notably, post-mitotic myofibers also acquire senescence-like features, including p21 upregulation and increased IL-6 secretion, creating an additional source of pro-inflammatory signaling[131]. In both conditions, immune evasion is not merely a bystander phenomenon but a causal mechanism: it permits senescent cells to escape clearance, and their continued presence directly drives the tissue degeneration characteristic of aging bone and muscle.
5. Intervention Strategy Targeting the Immune Evasion of Senescent Cells
The persistence of senescent cells is not merely a consequence of increased senescence induction but reflects multilayered immune evasion that operates at multiple levels, including impaired recognition by immune effectors, defective execution of immune-mediated clearance, enhanced survival signaling within senescent cells, and the immunosuppressive tissue niches, which collectively promote chronic low-grade inflammation (inflammaging), pathological tissue remodeling, and progressive multi-organ dysfunction. Consequently, therapeutic strategies aimed at counteracting senescent cell immune evasion, rather than merely reducing senescent cell burden, are essential for restoring immune-dependent homeostatic surveillance and promoting healthy aging (Figure 3).
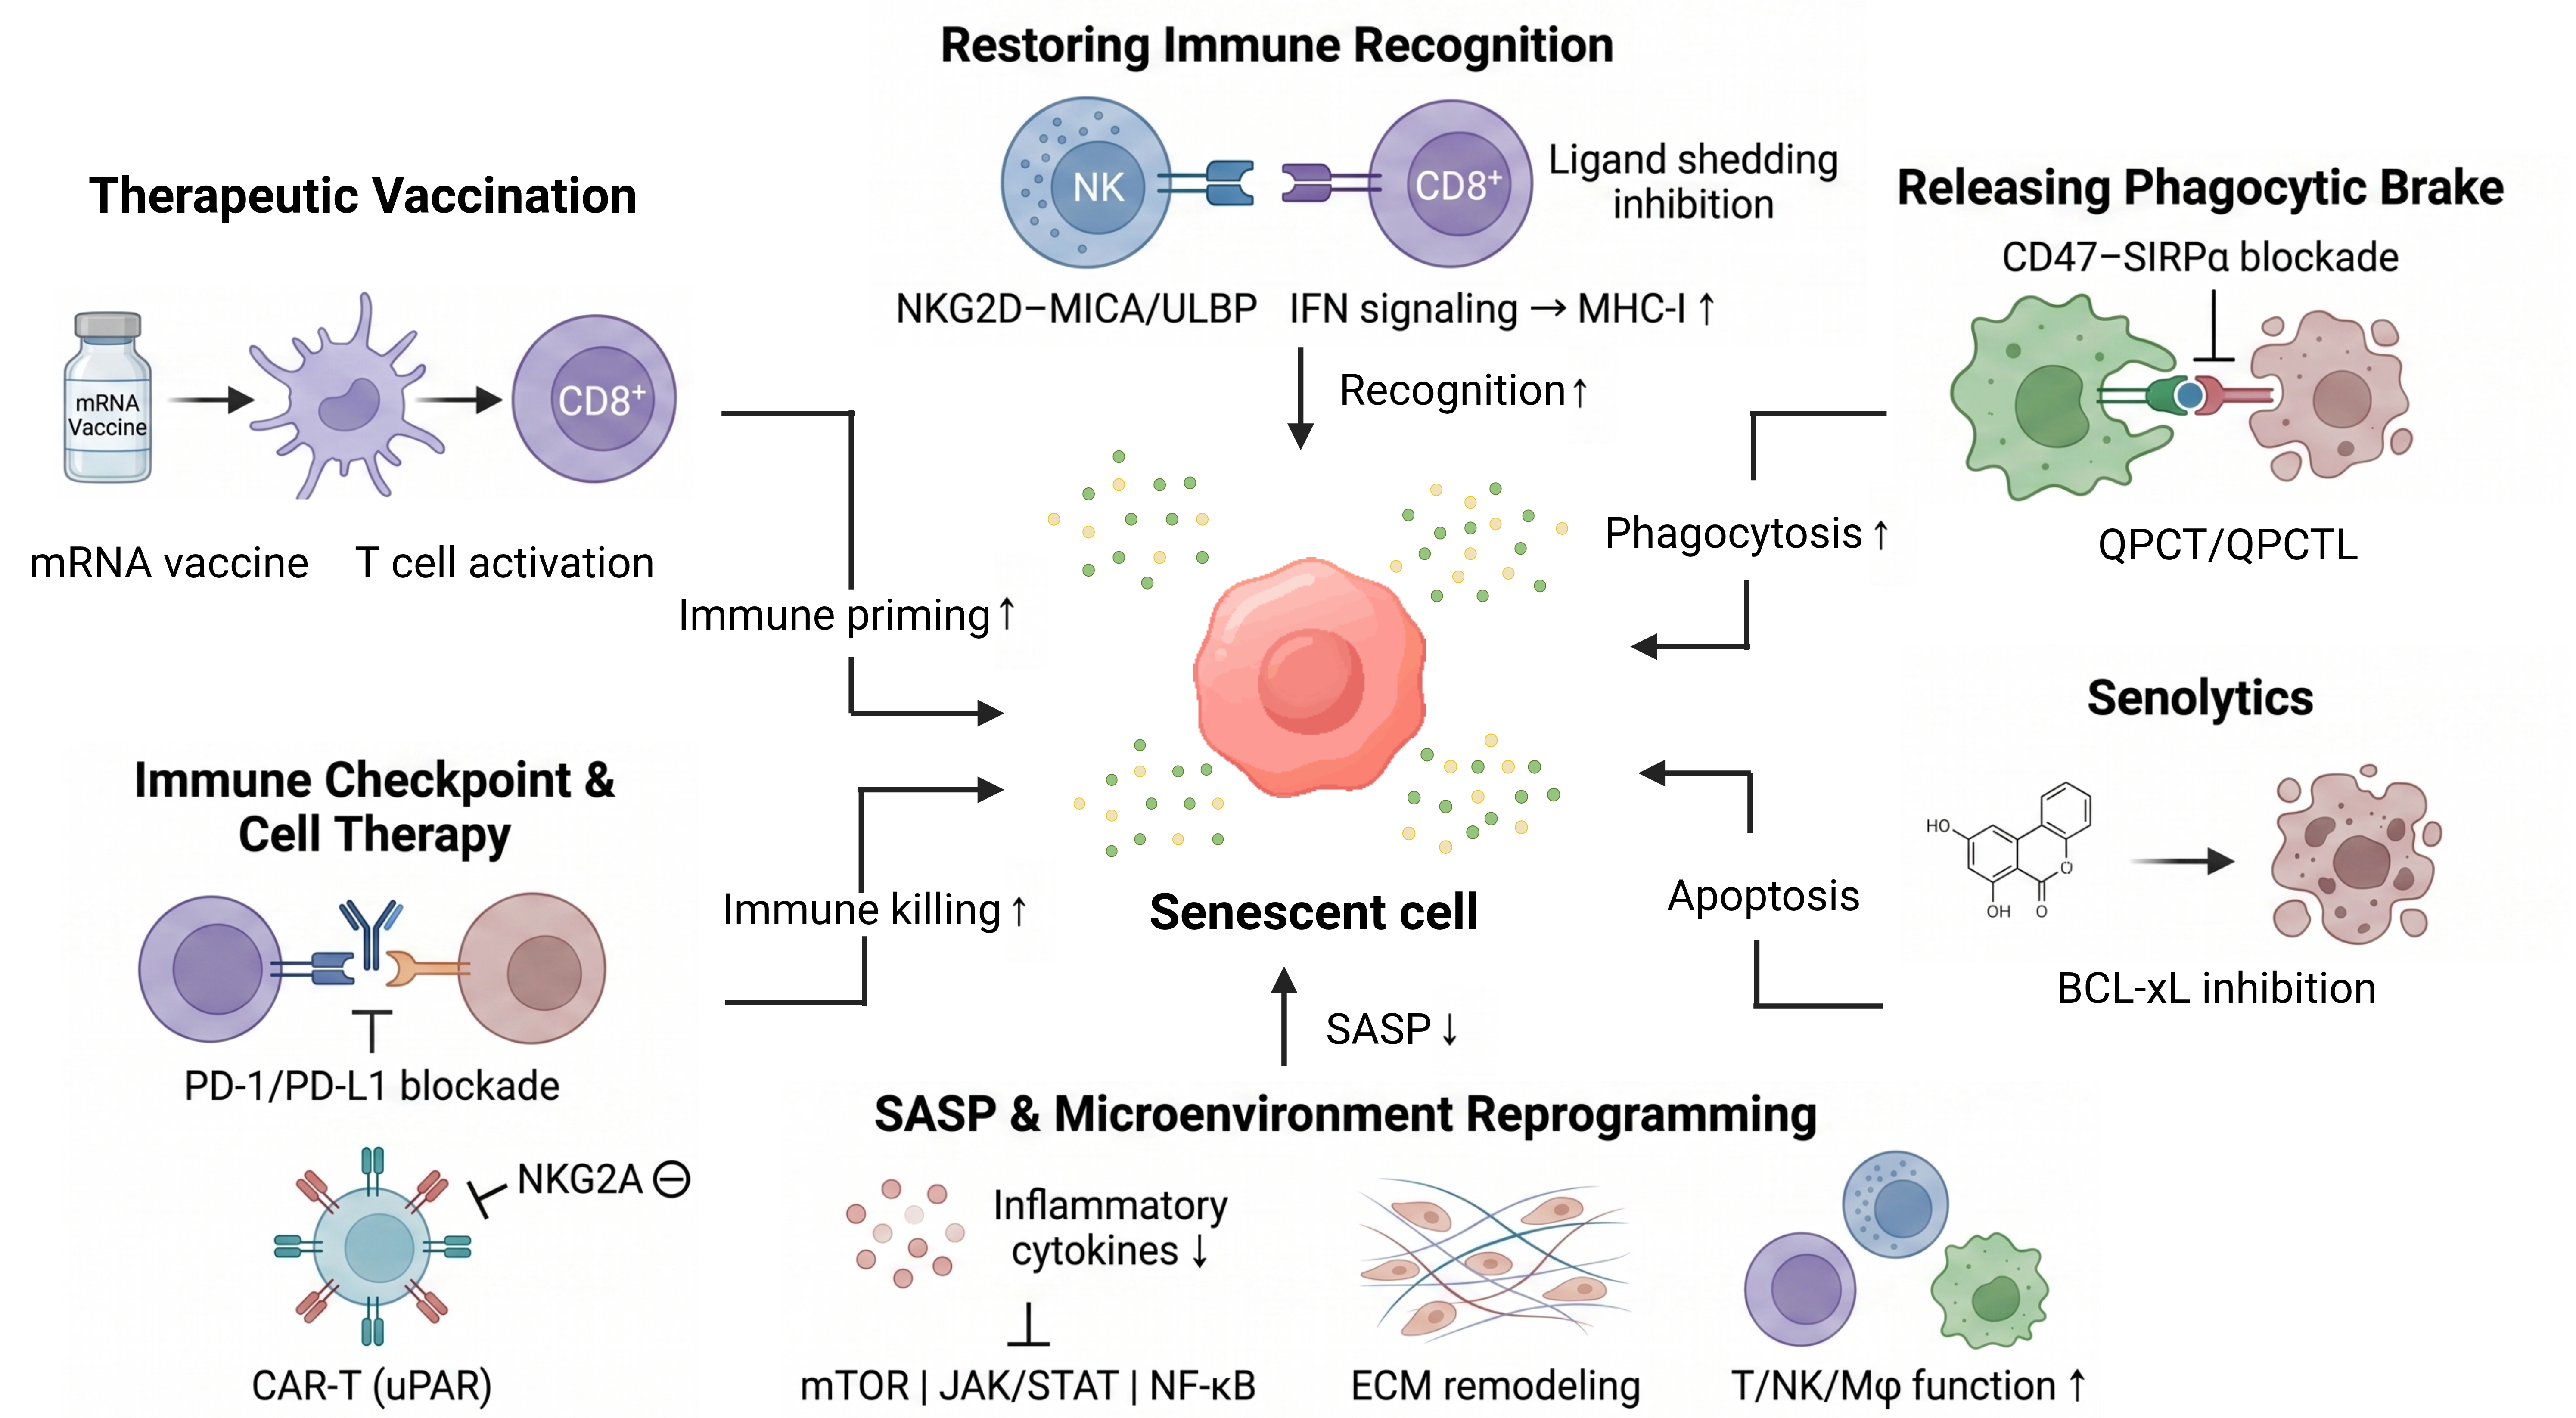
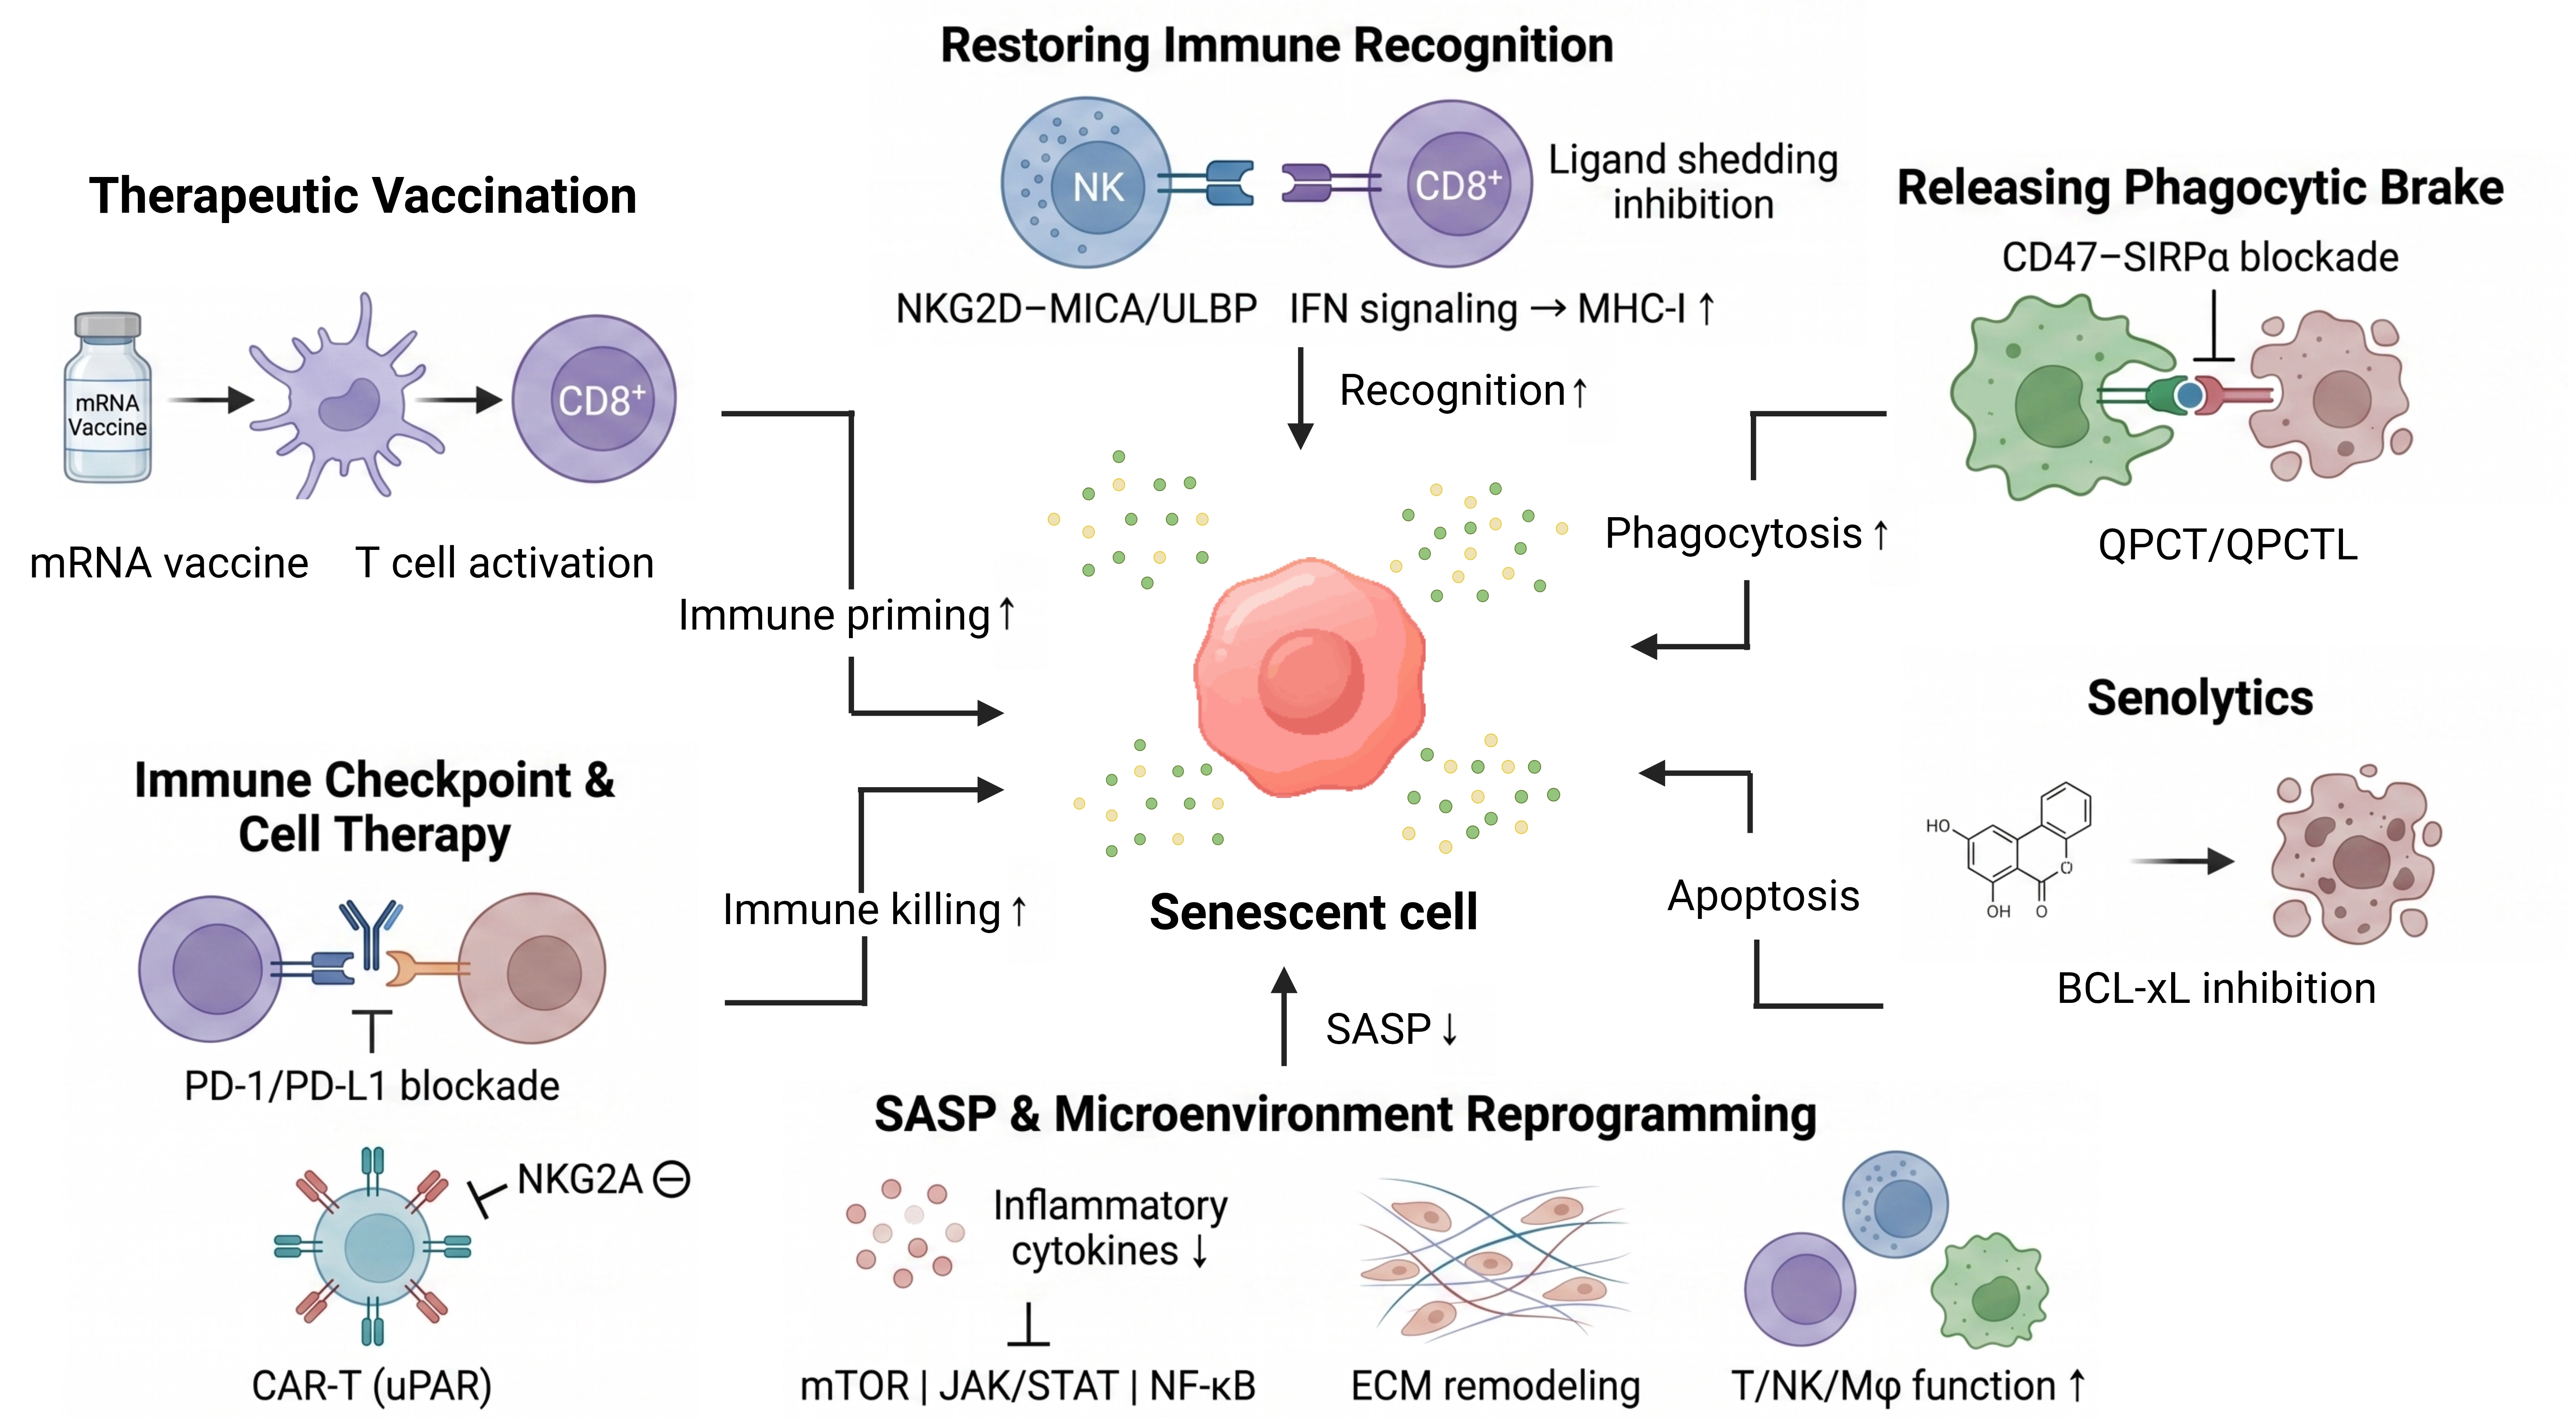
Figure 3. Therapeutic strategies targeting senescent-cell immune evasion. Interventions aimed at eliminating senescent cells or restoring immune-mediated clearance include enhancing immune recognition, releasing phagocytic inhibition, inducing apoptosis through senolytics, reprogramming the SASP, and applying immune checkpoint or cell-based therapies. In addition, therapeutic vaccination and modulation of the immune microenvironment may further improve senescent-cell clearance. Created in BioRender. Wang, L. (2026) https://www.biorender.com/xnjfmmv. NK: natural killer; CAR-T: chimeric antigen receptor T cell; PD-1: programmed cell death protein 1; PD-L1: programmed death-ligand 1; SASP: senescence-associated secretory phenotype; ECM: extracellular matrix; NKG2A: natural killer group 2 member A; SIRPα: signal regulatory protein α; MICA: MHC class I polypeptide-related sequence A; ULBP: UL16-binding protein; IFN: interferon; QPCT/QPCTL: glutaminyl-peptide cyclotransferase/glutaminyl-peptide cyclotransferase-like; BCL-xL: BCL-2-like protein 1; NF-κB: nuclear factor kappa B; mTOR: mechanistic target of rapamycin; uPAR: urokinase-type plasminogen activator receptor; JAK/STAT: janus kinase/signal transducer and activator of transcription.
5.1 Restoring recognition: Increasing “visibility” and activation efficiency
Senescent cells are subject to immune-mediated detection and elimination when activating ligand-receptor pathways are effectively engaged. In particular, recruited NK cells recognize senescent cells through the activating receptor NKG2D, whose interaction with ligands such as MICA and ULBP2 initiates NK cytotoxicity via granule exocytosis[8,10]. Consistently, senescence induced by multiple stresses upregulates NKG2D ligands, which are required for efficient NK-mediated cytotoxicity against senescent fibroblasts[10]. These observations provide a mechanistic basis for therapeutic strategies aimed at enhancing immune-mediated clearance of senescent cells by boosting immune cell function or by improving the targeting of senescence-associated surface markers, conceptually aligning with established mechanisms of senescent-cell immunosurveillance[8,132].
However, senescent cells can actively reduce immune recognition, rendering the restoration of immune detection a key therapeutic objective that requires reversal of these evasive adaptations. Persistent senescent cells shed NKG2D ligands via metalloprotease-mediated cleavage, thereby reducing surface ligand availability and escaping NK cell recognition and cytotoxicity. Notably, inhibition of this shedding restores NK-dependent clearance in experimental model systems[8,26].
Beyond innate immune evasion, adaptive immune recognition can be strengthened by enhanced antigen presentation. Specifically, type I interferon signaling upregulates the MHC-I antigen-processing machinery in senescent cells. Given that senescence is associated with increased immunogenicity, elevated IFN signaling, and enhanced MHC-I antigen presentation, these changes can facilitate CD8+ T-cell-mediated killing under appropriate conditions[9].
5.2 Releasing the phagocytic brake: Targeting “don’t-eat-me” signaling and restoring efferocytosis
Macrophage-mediated clearance depends on the balance between pro-phagocytic signals and inhibitory checkpoints. When CD47-SIRPα signaling predominates, phagocytosis is suppressed, preventing efficient clearance of target cells[133,134]. It has been reported that senescent fibroblasts and epithelial cells not only resist efferocytosis but also impair macrophage-mediated clearance of neighboring apoptotic cells through contact-dependent mechanisms. This effect is driven by increased CD47 expression on senescent cells together with elevated levels of QPCT/QPCTL, which enhance functional CD47-SIRPα engagement and inhibitory signaling in macrophages[19].
Therapeutically, disrupting the CD47-SIRPα axis can reverse this suppression. Interference with SIRPα-CD47-SHP-1 signaling or inhibition of QPCT/QPCTL activity restores macrophage-mediated corpse removal in senescent-cell co-culture systems[19]. Modulation of this checkpoint has been shown to enhance phagocytosis in aging- and disease-associated contexts. However, systemic blockade of CD47-SIRPα carries a risk of hematologic toxicity, including anemia and thrombocytopenia[133,134]. Notably, CD47 upregulation represents a general stress-adaptive immune-evasion mechanism employed not only by senescent cells but also by mobilized hematopoietic stem cells and leukemic cells to evade phagocytosis[74]. Collectively, these findings underscore the necessity of targeted delivery strategies or context-specific therapeutic application.
5.3 Checkpoint-based and cell-based therapies: Applicable scenarios and boundaries
Senescent cells engage immune-checkpoint signaling to evade immune-mediated elimination. Specifically, p16-dependent programs enhance PD-L1 stability in senescent cells, and PD-L1 in turn functions as a brake on immune clearance. Accordingly, experimental PD-L1 blockade can promote senescent cell removal in vivo, demonstrating that checkpoint inhibition can restore immune surveillance[59]. The PD-1/PD-L1 axis represents an immunosuppressive pathway that intersects with senescence biology and age-related pathology. Its activation suppresses the cytotoxic functions of T cells and NK cells, thereby promoting senescent cell persistence and accumulation[15,58,71]. This mechanistic understanding supports the rationale for checkpoint-oriented interventions to enhance immune clearance of senescent cells, while also underscoring the need for context-specific evaluation outside traditional oncology settings[62]. Importantly, systemic immune checkpoint blockade carries potential risks, including autoimmunity and exacerbation of chronic inflammatory diseases such as atherosclerosis, highlighting the necessity for carefully controlled and context-dependent therapeutic application. Beyond the PD-1/PD-L1 axis, additional inhibitory pathways also suppress senescent cell clearance. For instance, the NKG2A receptor on NK cells negatively regulates cytotoxicity; activation of NKG2A suppresses both antitumor immunity and senescence-directed clearance, suggesting that targeting NKG2A may further enhance NK cell-dependent elimination of senescent cells[7,15,60].
As a complementary strategy to checkpoint blockade, senescence-targeted cell therapy offers a direct approach to enhance immune-mediated elimination. The urokinase-type plasminogen activator receptor (uPAR) is broadly induced during senescence, and uPAR-directed CAR-T cells selectively eliminate senescent cells and ameliorate senescence-associated tissue abnormalities[132]. This approach bypasses endogenous checkpoint suppression by engineering immune cells with intrinsic cytotoxic capacity, thereby achieving senescent cell clearance independently of native immune activation.
Collectively, these strategies, which include checkpoint blockade to relieve immunosuppressive brakes, NKG2A targeting to enhance innate cytotoxicity, and CAR-T cell therapy to directly eliminate senescent cells, represent an expanding arsenal for enhancing immune-mediated clearance of pathogenic senescent cells. However, each approach requires careful safety evaluation and context-specific application to avoid off-target toxicity or immune-related adverse events.
5.4 Therapeutic vaccine strategies
Therapeutic vaccination has emerged as a potential strategy for senescent cell clearance. In proof-of-concept studies, immunization against the seno-antigen glycoprotein nonmetastatic melanoma protein B (GPNMB) (an endogenous glycoprotein) reduced senescent-cell burden, improved age-related phenotypes, and extended lifespan in mouse models[135]. Likewise, vaccination targeting CD153 effectively cleared CD153+ senescent T cells and alleviated insulin resistance and glucose intolerance in mice fed a high-fat diet[136]. These observations provide direct evidence that vaccine-based approaches can facilitate senescent-cell elimination.
Currently, mRNA vaccine technology provides a particularly advantageous platform for this approach, as it enables rapid and scalable antigen design, supports efficient intracellular antigen expression, and promotes antigen presentation to both CD8+ cytotoxic T cells and CD4+ helper T cells through dendritic-cell activation[137,138]. These features position mRNA vaccines as a promising tool for eliciting adaptive immune responses against senescence-associated antigens. Recent studies have demonstrated that strengthening antigen presentation and CD8+ T cell activation against seno-antigens can enhance immune-mediated elimination of senescent cells[139]. Nevertheless, whether mRNA vaccination can effectively harness these mechanisms to achieve comparable senescent-cell elimination in vivo remains to be directly investigated.
Despite its promise, the development of senescence-targeted vaccines faces several key challenges. Identifying seno-antigens with sufficient specificity to senescent cells remains a primary hurdle in avoiding off-target elimination of healthy cells. Additionally, optimizing adjuvants, delivery systems, and overall immunogenicity is essential to maximize vaccine efficacy while minimizing potential adverse immune effects. Overcoming these hurdles is critical for translating this approach into a clinically viable strategy to enhance immune-mediated clearance of pathogenic senescent cells.
5.5 Targeting the host immune system and microenvironmental barriers to restore immune access
Immunosenescence progressively impairs both innate and adaptive immune functions, thereby reducing the ability to recognize and eliminate senescent cells. Age-associated immune declines include diminished naive T-cell output, altered NK cell cytotoxicity, impaired macrophage phagocytic function, and chronic low-grade inflammation, all of which contribute to defective senescent cell clearance[8,25]. Therapeutically, reversing or mitigating these age-related immune defects may restore endogenous senescent cell removal and complement approaches that directly target senescent cells. In this context, targeting immunosenescence itself represents a viable strategy to re-establish senescent cell clearance capacity[139].
Beyond declining immune function, age-related alterations in ECM further compromise immune-mediated clearance of senescent cells. Senescent cells actively remodel the ECM through the secretion of proteases and matrix components, thereby creating physical and biochemical barriers that limit immune surveillance efficiency[140]. Recent studies have revealed that elastin-derived ECM fragments circulate in the blood and act as “infectious agents of aging”, activating innate immune cells via specific receptors and thereby driving chronic inflammation that further accelerates senescence accumulation. Remarkably, pharmacological inhibition of the elastin fragment receptor extended natural mouse lifespan by 17% and ameliorated age-related phenotypes in both mice and pigs, demonstrating that targeting the senescent ECM is a viable therapeutic strategy[141].
Together, these findings support a combinatorial strategy that integrates immune rejuvenation with microenvironmental normalization to enhance senescent cell clearance. Restoring immune competence, for example through cytokine modulation, metabolic reprogramming, or checkpoint regulation, may improve the recognition phase of clearance. Concurrently, correcting ECM remodeling, for instance via matrix metalloproteinase inhibitors or anti-fibrotic agents, may enhance immune cell access to target cells. By addressing both the cellular and structural barriers to effective immune-mediated elimination of senescent cells, such dual-pronged approaches may achieve greater efficacy than either strategy alone.
5.6 Senolytics and senomorphics as indirect or immune-bypass strategies
Beyond direct immune evasion-targeting strategies, pharmacological modulation of senescent cell burden and its inflammatory milieu have yielded important therapeutic advances. Senolytics, such as BCL-2 family inhibitors (e.g., ABT-263) or the dasatinib plus quercetin (D+Q), effectively eliminate senescent cells by targeting intrinsic pro-survival pathways, thereby reducing the total pool of senescent cells and alleviating tissue dysfunction in aged and progeroid murine models[142,143]. Translational potential is supported by early clinical evidence showing D+Q reduces senescence markers in humans[144]. However, emerging evidence indicates that senolytic efficacy may be tissue-context dependent, as D+Q has been reported to induce oligodendrocyte dysfunction and demyelination in the corpus callosum in mice, highlighting the need for careful safety evaluation, particularly in the central nervous system[145]. In light of these limitations, alternative senolytics with broader applicability are under further investigation. Procyanidin C1 (PCC1), a polyphenolic component of grape seed extract (GSE), has been reported to selectively eliminate senescent cells at higher concentrations without the limitations of cell-type dependence, significant toxicity to non-senescent cells, or poor clearance efficiency. Furthermore, PCC1 effectively extends healthspan in aged mice and enhances chemotherapeutic tumor cytotoxicity[146]. Concurrently, senomorphics modulate key signaling pathways (e.g., mTOR and janus kinase/signal transducer and activator of transcription (JAK/STAT)) to reduce inflammatory mediators and SASP expression, thereby attenuating the chronic inflammatory environment driven by senescent cells and helping restore tissue homeostasis without eliminating senescent cells themselves[147,148]. By dampening the immunosuppressive milieu, senomorphics can enhance residual immune surveillance[8,148]. Thus, these interventions can create a tissue context more favorable for endogenous immune activity.
Nevertheless, neither approach directly corrects the underlying defects in immune recognition or elimination. They should be positioned as indirect or adjunctive strategies: senolytics bypass the immune system by directly triggering intrinsic apoptotic pathways, thereby reducing the overall senescent cell burden and indirectly alleviating the antigenic load that the immune system must manage; senomorphics dampen inflammatory and spatial barriers created by SASP but do not necessarily eliminate immune-evasive senescent cells. Each strategy thus carries inherent limitations: senolytics may cause off-target toxicity in vulnerable tissues such as the central nervous system[145], and their efficacy can be tissue-context dependent; senomorphics require sustained dosing to maintain SASP suppression[149], and do not actively eliminate senescent cells, leaving the root source of pathology intact.
These complementary strengths and distinct limitations suggest that combining direct immune evasion-targeting strategies with senolytic or senomorphic agents may offer synergistic therapeutic potential. Immune checkpoint blockade targeting senescence-associated upregulation of PD-L1 or engineered CAR-T cells directed against senescent cell surface antigens could provide the specificity and durable memory required for sustained immune surveillance, while senolytics reduce the senescent cell burden to relieve immune exhaustion, and senomorphics remodel the inflammatory microenvironment to enhance immune cell infiltration and function. Such combinatorial regimens could enable lower doses of each individual agent, potentially mitigating off-target toxicities while achieving more robust and durable control of senescence-related pathology. This integrated paradigm, which harnesses both pharmacological senescence modification and immune system engagement, may prove particularly advantageous in complex tissues or chronic disease settings where single-modality approaches fall short.
6. Discussion
Accumulating evidence indicates that the persistence of senescent cells is not merely a passive consequence of senescence induction but rather a multifactorial process involving impaired immune recognition, defective clearance, enhanced anti-apoptotic signaling, and tissue microenvironment remodeling. These interconnected processes enable senescent cells to accumulate and persist in tissues, where they continuously secrete SASP factors, thereby driving chronic inflammation, fibrosis, and progressive functional decline across multiple organ systems[150]. Consequently, therapeutic strategies aimed at restoring immune surveillance, enhancing phagocytic clearance, directly eliminating senescent cells using senolytics, or modulating their secretory phenotype with senomorphics have emerged as promising avenues for intervention[151].
Despite these advances, a central unresolved challenge persists: the absence of a unified, specific, and quantifiable framework for defining and assessing senescent cell burden in vivo. Current identification strategies rely on combinations of surrogate markers, including p16INK4a, p21CIP1/WAF1, SA-β-gal activity, DNA damage foci, lamin B1 (LMNB1) loss, and SASP components[3]. However, none of these markers is universally necessary or sufficient, and many are shared with other cellular states. Ogrodnik et al. stated that senescence is defined largely by consensus around a set of context-dependent markers rather than a clear biological function[152]. Consequently, senescence should not be viewed as a discrete and uniform cellular state, but rather as a context-dependent and dynamically evolving phenotype shaped by the inducing stimulus, cell type, and tissue environment. Emerging evidence further suggests that DNA damage may contribute to this heterogeneity not only through mutation accumulation or persistent DNA damage response (DDR) signaling, but also through heritable post-repair chromatin and transcriptional alterations; notably, repaired DNA double-strand breaks can leave durable molecular “scars” that reshape 3D genome organization and gene regulation, potentially reinforcing divergent senescent phenotypes across cell divisions[153,154]. This intrinsic heterogeneity complicates the precise delineation of senescent cells and limits the comparability of senescence burden across tissues, models, and disease contexts.
Critically, the heterogeneity of senescent cell populations poses a further, conceptually distinct challenge: distinguishing immune-evasive senescent cells from other senescent subpopulations that may be immunologically visible or even actively cleared. Recent studies have identified inhibitory ligands and multiple senescence immune checkpoints (SICs) of NKG2D signaling that are upregulated on a subset of senescent cells, including HLA-E, PD-L1, and GD3, which enable these cells to evade clearance by NK cells and cytotoxic T lymphocytes, while other senescent subpopulations remain susceptible to immune-mediated elimination[14-16,58]. This functional heterogeneity implies that immunotherapies or senolytic agents that rely on bulk senescence markers may inadvertently spare the very subpopulations most responsible for pathological persistence, namely, those equipped with immune evasion mechanisms. Furthermore, it remains unclear whether markers of immune evasion (e.g., GD3, PD-L1) correlate with, or are orthogonal to, conventional senescence markers such as p16 or SA-β-gal, making it difficult to stratify patients or evaluate therapeutic responses based on current biomarker panels. Thus, the absence of reliable tools to distinguish immune-evasive senescent cells from their immunogenic or clearance-susceptible counterparts represents a major obstacle to the rational design and accurate assessment of senescence-targeting immunotherapies.
This limitation has important implications for interpreting therapeutic outcomes. Accumulating preclinical and early clinical evidence indicates that targeting senescent cells can improve healthspan-associated phenotypes and confer functional benefits in age-related diseases. For example, senolytic interventions have ameliorated multiple age-associated pathologies in animal models, and early clinical studies, such as the use of dasatinib plus quercetin in idiopathic pulmonary fibrosis, have reported improvements in physical function[155,156]. However, in the absence of reliable baseline quantification and precise in vivo measurement tools, the extent to which these benefits are attributable to actual senescent cell elimination remains difficult to ascertain. Observed improvements may reflect reductions in inflammatory signaling, modulation of the immune microenvironment, attenuation of SASP, or broader restoration of tissue homeostasis, rather than a direct decrease in senescent cell burden[157]. It is challenging to determine whether any observed benefit in patients is due to senescent cell clearance.
More broadly, the lack of quantitative resolution constrains the establishment of robust therapeutic benchmarks in this field. Without accurate assessment of baseline senescent cell load, spatial distribution, and turnover dynamics, several fundamental questions remain unanswered: what proportion of senescent cells must be eliminated to achieve clinical benefit? Is partial clearance sufficient? Do threshold effects vary across tissues? And how rapidly do senescent cells re-accumulate following intervention? These challenges are particularly acute for immune-mediated senescent cell clearance. Given the pleiotropic nature of the immune system, immunomodulatory interventions inevitably affect both senescent and non-senescent cells, thereby blurring the distinction between direct targeting of senescence and general improvement of tissue homeostasis[157].
Taken together, these considerations suggest that the major bottleneck for advancing senescence-targeted therapies is the need for a robust and standardized framework to identify, stratify, and quantify senescent cells in vivo. Several initiatives, such as the Aging Biomarker Consortium (ABC) “Six Pillars and Three Primary Colors” framework and the National Institutes of Health Common Fund’s Cellular Senescence Network (SenNet) program, have begun establishing standardized frameworks for senescence assessment[158-161]. However, these efforts have not yet incorporated immune evasion signatures (e.g., GD3, PD-L1, HLA-E) into standardized biomarker panels. Integrating these immune checkpoint molecules into existing or future frameworks (e.g., extending the ABC’s “Six Pillars” to include immune evasion dimensions, or annotating immune-evasive subpopulations within SenNet’s multimodal datasets) would provide a crucial layer of resolution, enabling the field to move from bulk senescence assessment toward stratified identification of immune-evasive versus clearance-susceptible senescent cells, and thereby inform more precise therapeutic targeting.
Recently, single-cell fluorescence imaging studies have already revealed significant heterogeneity in SA-β-gal activity and identified distinct senescent cell subpopulations, highlighting the value of assessing cellular heterogeneity in senescence research[162]. To move beyond mere descriptive correlation, emerging high-resolution approaches, including but not limited to single-cell and spatial multi-omics (transcriptomics, epigenomics, proteomics), large language models (LLMs) and generative AI, virtual-cell-enabled precise screening and mechanistic inference, offer the potential to simultaneously profile the identified or novel senescence markers and immune evasion signatures within the same cells, enabling the identification and spatial mapping of immune-evasive senescent cells within tissue microenvironments. Such approaches could help establish whether immune-evasive subpopulations cluster in specific anatomical niches and whether their distribution correlates with local immune dysfunction or fibrotic remodeling, and such integration would enable a paradigm shift from correlative descriptions and marker-based identification toward context-aware, multiparameter definitions of senescence. Ultimately, improved resolution in distinguishing genuine senescent cell clearance from phenotypic modulation will be essential. It will render senescence-targeting strategies not only more rigorously testable and comparable across studies, but also ultimately more translatable into safe and effective clinical interventions.
Acknowledgements
AI tools (DeepSeek, ChatGPT) were employed solely for the purpose of language polishing during manuscript preparation. All research content, including study design, data analysis, interpretations, figures, and tables, is original and was not generated using AI tools.
Authors contribution
Ou Q: Writing-original draft.
Zhao J, Ge Y: Writing-review & editing.
Wu S: Conceptualization, writing-review & editing.
Conflicts of interest
Shu Wu is a Youth Editorial Board Member of Ageing and Cancer Research & Treatment. The other authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
This work was supported by grants from the National Natural Science Foundation of China (Grant Nos. 82271590 and 82230047); the National Key R&D Program of China (Grant No. 2024YFA0918701); the Guangdong Basic and Applied Basic Research Foundation (Grant No. 2024A1515010727); and the Fundamental Research Funds for the Central Universities (Grant No. 21625106).
Copyright
© The Author(s) 2026.
References
-
5. Kang TW, Yevsa T, Woller N, Hoenicke L, Wuestefeld T, Dauch D, et al. Senescence surveillance of pre-malignant hepatocytes limits liver cancer development. Nature. 2011;479(7374):547-551.[DOI]
-
7. Pereira BI, Devine OP, Vukmanovic-Stejic M, Chambers ES, Subramanian P, Patel N, et al. Senescent cells evade immune clearance via HLA-E-mediated NK and CD8+ T cell inhibition. Nat Commun. 2019;10(1):2387.[DOI]
-
8. Majewska J, Krizhanovsky V. Immune surveillance of senescent cells in aging and disease. Nat Aging. 2025;5(8):1415-1424.[DOI]
-
10. Sagiv A, Burton DGA, Moshayev Z, Vadai E, Wensveen F, Ben-Dor S, et al. NKG2D ligands mediate immunosurveillance of senescent cells. Aging. 2016;8(2):328-344.[DOI]
-
17. Zhou X, Yan Z, Hou J, Zhang L, Chen Z, Gao C, et al. The Hippo-YAP signaling pathway drives CD24-mediated immune evasion in esophageal squamous cell carcinoma via macrophage phagocytosis. Oncogene. 2024;43(7):495-510.[DOI]
-
18. Vachon E. CD44 is a phagocytic receptor. Blood. 2006;107(10):4149-4158.[DOI]
-
27. Seitz HM, Camenisch TD, Lemke G, Earp HS, Matsushima GK. Macrophages and dendritic cells use different axl/mertk/Tyro3 receptors in clearance of apoptotic cells. J Immunol. 2007;178(9):5635-5642.[DOI]
-
31. Soriani A, Zingoni A, Cerboni C, Iannitto ML, Ricciardi MR, Gialleonardo VD, et al. ATM-ATR-dependent up-regulation of DNAM-1 and NKG2D ligands on multiple myeloma cells by therapeutic agents results in enhanced NK-cell susceptibility and is associated with a senescent phenotype. Blood. 2009;113(15):3503-3511.
-
34. Liu D, Wang J, Wei Y, Wu H, Yuan S, Yang M, et al. Senescent cancer cells in immune surveillance and evasion: Mechanisms and therapeutic implications. J Leukoc Biol. 2025;117(9):qiaf125.[DOI]
-
36. Zhou L, Ma B, Ruscetti M. Cellular senescence offers distinct immunological vulnerabilities in cancer. Trends Cancer. 2025;11(4):334-350.[DOI]
-
41. Logtenberg MEW, Scheeren FA, Schumacher TN. The CD47-SIRPα immune checkpoint. Immunity. 2020;52(5):742-752.[DOI]
-
44. Zhu Y, Tchkonia T, Fuhrmann-Stroissnigg H, Dai HM, Ling Y, Stout MB, et al. Identification of a novel senolytic agent, navitoclax, targeting the Bcl-2 family of anti-apoptotic factors. Aging Cell. 2016;15(3):428-435.[DOI]
-
49. Liu X, Liu Z, Wu Z, Ren J, Fan Y, Sun L, et al. Resurrection of endogenous retroviruses during aging reinforces senescence. Cell. 2023;186(2):287-304.e26.[DOI]
-
51. Demaria M, Ohtani N, Youssef SA, Rodier F, Toussaint W, Mitchell JR, et al. An essential role for senescent cells in optimal wound healing through secretion of PDGF-AA. Dev Cell. 2014;31(6):722-733.[DOI]
-
52. Malaquin N, Martinez A, Rodier F. Keeping the senescence secretome under control: Molecular reins on the senescence-associated secretory phenotype. Exp Gerontol. 2016;82:39-49.[DOI]
-
53. Kirkland JL, Tchkonia T. Cellular senescence: A translational perspective. EBioMedicine. 2017;21:21-28.[DOI]
-
56. Schafer MJ, White TA, Iijima K, Haak AJ, Ligresti G, Atkinson EJ, et al. Cellular senescence mediates fibrotic pulmonary disease. Nat Commun. 2017;8:14532.[DOI]
-
57. Stowe EJ, Keller MR, Connizzo BK. Cellular senescence impairs tendon extracellular matrix remodeling in response to mechanical unloading. Aging Cell. 2024;23(11):e14278.[DOI]
-
65. Rohwedder I, Montanez E, Beckmann K, Bengtsson E, Dunér P, Nilsson J, et al. Plasma fibronectin deficiency impedes atherosclerosis progression and fibrous cap formation. EMBO Mol Med. 2012;4(7):564-576.[DOI]
-
84. Chang D, Wang J, Zhu S, Shentu Y, Wang Y, Zhu P, et al. Cellular senescence and cell therapy in cardiovascular diseases. Stem Cell Res Ther. 2025;16(1):613.[DOI]
-
86. Wang H, Yu Y, Li R, Zhang H, Chen ZS, Sun C, et al. Immunoregulatory mechanisms in the aging microenvironment: Targeting the senescence-associated secretory phenotype for cancer immunotherapy. Acta Pharm Sin B. 2025;15(9):4476-4496.[DOI]
-
87. Slaets H, Veeningen N, de Keizer PLJ, Hellings N, Hendrix S. Are immunosenescent T cells really senescent? Aging Cell. 2024;23(10):e14300.[DOI]
-
89. Henson SM, Lanna A, Riddell NE, Franzese O, MacAulay R, Griffiths SJ, et al. p38 signaling inhibits mTORC1-independent autophagy in senescent human CD8+ T cells. J Clin Invest. 2014;124(9):4004-4016.[DOI]
-
97. Lai P, Liu L, Bancaro N, Troiani M, Calì B, Li Y, et al. Mitochondrial DNA released by senescent tumor cells enhances PMN-MDSC-driven immunosuppression through the Cgas-STING pathway. Immunity. 2025;58(4):811-825.e7.[DOI]
-
109. Júnior C, Ulldemolins A, Narciso M, Almendros I, Farré R, Navajas D, et al. Multi-step extracellular matrix remodelling and stiffening in the development of idiopathic pulmonary fibrosis. Int J Mol Sci. 2023;24(2):1708.[DOI]
-
110. Ogrodnik M, Miwa S, Tchkonia T, Tiniakos D, Wilson CL, Lahat A, et al. Cellular senescence drives age-dependent hepatic steatosis. Nat Commun. 2017;8:15691.[DOI]
-
112. Aravinthan A, Scarpini C, Tachtatzis P, Verma S, Penrhyn-Lowe S, Harvey R, et al. Hepatocyte senescence predicts progression in non-alcohol-related fatty liver disease. J Hepatol. 2013;58(3):549-556.[DOI]
-
117. Umbaugh DS, Diehl AM, Du K. Redefining senescence through hepatocyte fate changes in liver diseases. Trends Endocrinol Metab. 2026;37(4):304-312.[DOI]
-
121. Rui L, Yuan M, Frantz D, Shoelson S, White MF. SOCS-1 and SOCS-3 block insulin signaling by ubiquitin-mediated degradation of IRS1 and IRS2. J Biol Chem. 2002;277(44):42394-42398.[DOI]
-
125. Auger C, Kajimura S. Adipose tissue remodeling in pathophysiology. Annu Rev Pathol Mech Dis. 2023;18(1):71-93.[DOI]
-
126. Villaret A, Galitzky J, Decaunes P, Estève D, Marques MA, Sengenès C, et al. Adipose tissue endothelial cells from obese human subjects: Differences among depots in angiogenic, metabolic, and inflammatory gene expression and cellular senescence. Diabetes. 2010;59(11):2755-2763.
-
127. Zoico E, Policastro G, Rizzatti V, Nori N, Darra E, Rossi AP, et al. Mechanisms of adipose tissue extracellular matrix alterations in an in vitro model of adipocytes hypoxia and aging. Mech Ageing Dev. 2020;192:111374.[DOI]
-
130. Lai Y, Ramírez-Pardo I, Isern J, An J, Perdiguero E, Serrano AL, et al. Multimodal cell atlas of the ageing human skeletal muscle. Nature. 2024;629(8010):154-164.[DOI]
-
134. Mutombo Menga A, Hong X, Zhu L. CD47 signaling in aging and age-related diseases: Mechanisms, challenges, and therapeutic opportunities. Biogerontology. 2025;27(1):27.[DOI]
-
137. Liu C, Shi Q, Huang X, Koo S, Kong N, Tao W. mRNA-based cancer therapeutics. Nat Rev Cancer. 2023;23(8):526-543.[DOI]
-
139. Tizazu AM, Tessema EA, Cexus ON. Targeting immunosenescence promotes clearance of senescent cells. Immun Ageing. 2025;22(1):35.[DOI]
-
140. Mavrogonatou E, Pratsinis H, Papadopoulou A, Karamanos NK, Kletsas D. Extracellular matrix alterations in senescent cells and their significance in tissue homeostasis. Matrix Biol. 2019;75:27-42.[DOI]
-
141. Yi J, Wang Y, Sui H, Chen Z, Ye T, Zhong Y, et al. Elastin-derived extracellular matrix fragments drive aging through innate immune activation. Nat Aging. 2025;5(12):2380-2398.[DOI]
-
145. Lombardo ER, Pijewski RS, Lustig JT, Dhari Z, Lahiri A, Papile LE, et al. Senolytic treatment induces oligodendrocyte dysfunction and demyelination in the corpus callosum. Proc Natl Acad Sci U S A. 2026;123(12):e2524897123.[DOI]
-
149. Sutanto H, Fetarayani D, Narendra MR, Nasution SA. The role of the senescence-associated secretory phenotype in cardiovascular disease among the elderly. Eur J Intern Med. 2025;141:106488.[DOI]
-
151. McHugh D, Durán I, Gil J. Senescence as a therapeutic target in cancer and age-related diseases. Nat Rev Drug Discov. 2025;24(1):57-71.[DOI]
-
153. Bantele S, Mordini I, Biran A, Alcaraz N, Zonderland G, Wenger A, et al. Repair of DNA double-strand breaks leaves heritable impairment to genome function. Science. 2025;390(6773):eadk6662.[DOI]
-
154. Salari H, Chen CL. Repair of DNA double-strand breaks leaves heritable molecular scars that might shape aging trajectories and cancer risk. Ageing Cancer Res Treat. 2026;3(3):202609.[DOI]
-
156. Justice JN, Nambiar AM, Tchkonia T, LeBrasseur NK, Pascual R, Hashmi SK, et al. Senolytics in idiopathic pulmonary fibrosis: Results from a first-in-human, open-label, pilot study. EBioMedicine. 2019;40:554-563.[DOI]
-
159. Wu Z, Qu J, Zhang W, Consortium AB, Liu GH. Biomarkers of ageing of humans and non-human primates. Nat Rev Mol Cell Biol. 2025;26(11):826-847.[DOI]
-
160. Suryadevara V, Hudgins AD, Rajesh A, Pappalardo A, Karpova A, Dey AK, et al. SenNet recommendations for detecting senescent cells in different tissues. Nat Rev Mol Cell Biol. 2024;25(12):1001-1023.[DOI]
-
161. Fan R. Single-cell and spatial omics for mapping cellular senescence in health, aging and disease. Innov Aging. 2023;7(Supplement_1):473.[DOI]
Copyright
© The Author(s) 2026. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Ou Q, Zhao J, Ge Y, Wu S. Immune evasion of senescent cells: Mechanisms, pathological significance, and targeted interventions. Ageing Cancer Res Treat. 2026;3:202617. https://doi.org/10.70401/acrt.2026.0034
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Immune Cells Mediating Senescence Surveillance
- 3. Multilevel Architecture of Senescent Cell Immune Evasion
- 4. Diseases Resulting from the Immune Evasion of Senescent Cells
- 5. Intervention Strategy Targeting the Immune Evasion of Senescent Cells
- 6. Discussion
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Ou Q, Zhao J, Ge Y, Wu S. Immune evasion of senescent cells: Mechanisms, pathological significance, and targeted interventions. Ageing Cancer Res Treat. 2026;3:202617. https://doi.org/10.70401/acrt.2026.0034
copy
Share Link
copy