Senescence-associated transcriptional reprogramming in the tumor immune microenvironment: Mechanistic layers and therapeutic opportunities

Xiao Yu
1
,
Jianlei Xing
1
,
Xudong Zhao
1,*
,
Qiang Shan
2,*

*Correspondence to:
Xudong Zhao, Shengjing Hospital of China Medical University, Shenyang 110004, Liaoning, China.
E-mail: donold@126.com
Qiang Shan, Suzhou Institute of Systems Medicine, Chinese Academy of Medical Sciences, Suzhou 215123, Jiangsu, China. E-mail: sq@ism.pumc.edu.cn
Qiang Shan, Suzhou Institute of Systems Medicine, Chinese Academy of Medical Sciences, Suzhou 215123, Jiangsu, China. E-mail: sq@ism.pumc.edu.cn
Ageing Cancer Res Treat. 2027;4:202626. 10.70401/acrt.2026.0040
Received: June 01, 2026Accepted: September 15, 2026Published: September 15, 2026
This article belongs to the Special lssue Immunosenescence and Cancer: From Mechanisms to Therapy
Abstract
The tumor immune microenvironment (TIME) is a principal determinant of tumor progression, metastatic dissemination, and therapeutic response. Cellular senescence, primarily through the senescence-associated secretory phenotype (SASP), progressively reshapes the TIME toward immunosuppressive and therapy-resistant states. Here, we propose an integrative framework of “senescence-associated transcriptional reprogramming” comprising three mechanistic layers: endogenous inflammation-driven signaling centered on the cGAS-STING-NF-κB-IFN hub; lineage-specific epigenetic lock-in in immune cells; and metabolic-epigenetic coupling. We further discuss mechanism-guided, temporally optimized senolytic and senomorphic strategies, particularly relevant to elderly cancer patients, to rationally reverse senescence-driven tumor immune tolerance and enhance current immunotherapies.
Keywords
Tumor immune microenvironment, cellular senescence, senescence-associated secretory phenotype, senescence-associated transcriptional reprogramming, senolytics/senomorphics
1. Introduction
The tumor immune microenvironment (TIME) is a principal determinant of tumor progression, metastatic dissemination, establishment of immunosuppressive niches, and maintenance of tumor stemness[1-4]. Among the myriad factors that reshape the TIME, cellular senescence has emerged as a pivotal contributor[1-4]. Senescent cells remodel the TIME predominantly through the senescence-associated secretory phenotype (SASP), a complex secretome of cytokines, chemokines, growth factors, proteases, and extracellular vesicles[1-8]. Via SASP-mediated paracrine and autocrine signaling, senescent cells impair immune effector function, remodel the extracellular matrix, and drive aberrant angiogenesis and metabolic reprogramming, thereby progressively biasing the TIME toward immunosuppressive and therapy-resistant states[5-12].
Recent evidence indicates that cellular senescence is accompanied by extensive non-mutational epigenetic reprogramming and transcriptional rewiring. Senescent cells acquire durable changes in DNA methylation, histone modifications, and chromatin accessibility, and have been proposed to undergo reorganization of three-dimensional genome architecture[13-16]. In parallel, direct epigenetic profiling of CD8+ T cells has shown that chronic antigen stimulation establishes a stable, exhaustion-associated chromatin state that limits reinvigoration by checkpoint blockade[17,18], while senescent stromal and myeloid compartments can establish an immunosuppressive microenvironment[19]. Whether these programs are causally integrated into a single hierarchy remains a proposed rather than an established model. A profound reciprocal interplay between metabolic reprogramming and epigenetic modifications further couples hypoxia and lactate accumulation to chromatin-modifying enzyme activity, thereby imprinting microenvironmental metabolic cues onto the epigenome of tumor and immune cells.
Despite rapid progress, three gaps continue to limit a mechanistic understanding of how senescence reshapes the TIME. First, the cyclic GMP-AMP synthase-stimulator of interferon genes-nuclear factor kappa B-interferon (cGAS-STING-NF-κB-IFN) axis is frequently depicted as a linear signaling cascade, which underrepresents its behavior as a self-amplifying inflammatory hub capable of sustaining chronic, low-grade immunosuppression. Second, senescence-associated immune dysfunction is often described at the phenotypic level, without addressing how these dysfunctional states become epigenetically fixed and heritable through cell division. Third, immunometabolism and epigenetics have largely developed in parallel, leaving the metabolic control of the chromatin landscape underexplored in the senescent TIME. To address these gaps, we organize this review around a three-layer hierarchy—inflammatory hubs, epigenetic lock-in, and metabolic-epigenetic coupling.
In contrast to previous reviews that have primarily focused on organismal aging, SASP biology, or isolated signaling pathways, the present article centers on “senescence-associated transcriptional reprogramming” as an integrative framework linking senescent-cell intrinsic epigenetic changes, immune-cell epigenetic lock-in, and metabolic-epigenetic coupling within the TIME. We first delineate endogenous inflammation-driven signaling centered on the cGAS-STING-NF-κB-IFN hub, then discuss lineage-specific epigenetic remodeling of immune cells and metabolite-driven chromatin reprogramming, and finally explore temporally optimized senolytic and senomorphic strategies, particularly in elderly cancer patients, to rationally reverse senescence-driven tumor immune tolerance and enhance current immunotherapies[13-16,20].
Accordingly, this review is structured into four parts: baseline organization of the TIME; senescence-driven immune consequences; a three-layer mechanistic framework of senescence-associated transcriptional reprogramming; and mechanism-guided therapeutic opportunities.
Box 1. An operational definition of senescence-associated transcriptional reprogramming.
We define senescence-associated transcriptional reprogramming as a stress-driven, stably inherited reconfiguration of the transcriptional landscape that is operationally distinguished by three criteria: (i) Trigger. It is initiated by bona fide senescence-inducing stressors, including oncogene activation, telomere attrition, genotoxic/replicative stress, and metabolic or mitochondrial dysfunction, or is propagated paracrinally by the SASP. (ii) Chromatin-level stabilization. It is consolidated at the chromatin and DNA-methylation level (SAHF, Lamin B1 loss, genome-wide H3K9me3/H3K27me3 redistribution, and LINE-1 derepression), rather than reflecting transient signaling. (iii) Non-cell-autonomous output. It is coupled to a pro-inflammatory secretory program (SASP) that propagates the reprogrammed state to neighboring cells. Unless otherwise stated, our discussion of the tumor immune microenvironment refers to the cell-extrinsic consequences of this program.
This definition distinguishes senescence-associated transcriptional reprogramming from several related but distinct processes. Unlike developmental lineage programming, it is stress-initiated rather than cue-driven; unlike quiescence, it is accompanied by an active secretory program rather than metabolic dormancy; unlike trained immunity, its persistence is coupled to a stable proliferative arrest; unlike pluripotency reprogramming, it does not restore developmental potency; and unlike antigen-driven T-cell exhaustion, it is not primarily a consequence of chronic receptor stimulation. Throughout this review, our discussion of the TIME refers to the cell-extrinsic reprogramming of bystander stromal and immune cells by the SASP, rather than to reprogramming within the senescent cell itself.
2. Composition, Spatial Organization, and Phenotypic Polarization of the TIME
Tumors constitute complex ecosystems in which malignant cells, immune cells, and stromal elements collectively determine whether local immunity is tumor-suppressive or tumor-permissive[20-22]. In this context, cellular senescence and senescence-associated transcriptional reprogramming progressively reshape the cellular composition, spatial architecture, and functional polarization of the TIME, thereby dictating immunosurveillance, immune escape, and responses to immunotherapy[1-8].
2.1 Composition: Balance between effector and immunoregulatory networks
The cellular compartment of the TIME can be broadly dichotomized into effector and immunoregulatory populations that exist in a dynamic equilibrium[20-22]. Effector immune cells, including CD8+ cytotoxic T lymphocytes (CTLs), natural killer (NK) cells, type 1 T helper (Th1) cells, natural killer T (NKT) cells, and M1-polarized macrophages, mediate immunosurveillance and tumor clearance by direct cytolysis and orchestration of pro-inflammatory cascades. CTLs and NK cells are the principal cytolytic effectors, eliminating tumor cells via perforin/granzyme release or FasL/TRAIL pathways and secreting IFN-γ to sustain local immune activation. CD4+ Th1 cells and NKT cells amplify these responses by rapidly producing IFN-γ upon antigen or glycolipid recognition, whereas M1-like macrophages provide phagocytic, antigen-presenting, and reactive oxygen species (ROS)-mediated cytotoxic functions. Mature dendritic cells (DCs) and selected B-cell subsets further support adaptive immunity by capturing and presenting tumor antigens.
In parallel, the TIME harbors an expansive immunoregulatory compartment composed of regulatory T cells (Tregs), myeloid-derived suppressor cells (MDSCs), M2-polarized tumor-associated macrophages (TAMs), tumor-associated neutrophils (TANs), and regulatory B cells (Bregs)[23-27]. Tregs and Bregs suppress effector T-cell proliferation and cytokine production through IL-10 and TGF-β, while MDSCs and TANs inhibit T-cell and NK-cell function via arginase, ROS, and other suppressive mediators[28-31]. Non-immune stromal cells, particularly cancer-associated fibroblasts (CAFs), together with metabolic perturbations such as lactate accumulation and exosomes, provide a structural and signaling scaffold that favors effector-cell attrition and immunosuppressive cell recruitment[32-34]. As intratumoral stress and senescent-cell burden increase, SASP-driven transcriptional programs amplify these immunoregulatory networks by recruiting Tregs and MDSCs, promoting M2-like TAM differentiation, and upregulating immune checkpoint ligands, thereby progressively displacing effector dominance within the TIME.
2.2 Spatial architecture: Determinants of cell-cell interaction and physical barriers
The spatial configuration of TIME components critically influences the probability and quality of productive immune-tumor cell interactions[35-38]. Spatial multi-omics and imaging studies have revealed that non-immune and immunosuppressive elements frequently reorganize the microenvironment to hinder effector-cell infiltration and synapse formation with tumor cells. CAFs secrete and remodel extracellular matrix (ECM) components, leading to focal ECM deposition and increased tissue stiffness that perturb mechanotransduction in immune cells and impair their activation. These ECM-rich regions frequently coincide with the spatial aggregation of specific TAM subpopulations at tumor-stroma interfaces, forming physical and functional barriers that exclude T cells from the tumor core and generate classical immune-excluded phenotypes, as exemplified in pancreatic ductal adenocarcinoma[38].
Conversely, when CD8+ T cells, DCs, and B cells successfully penetrate the tumor parenchyma and form close clusters with malignant cells, or organize into tertiary lymphoid structures (TLS), antigen presentation, clonal expansion, and cytolytic activity are efficiently initiated[39-41]. Senescence-associated transcriptional reprogramming intersects with these spatial patterns by promoting aberrant ECM deposition, cross-linking, and stromal stiffening through SASP components such as matrix metalloproteinases and pro-fibrotic cytokines, thereby imposing durable architectural constraints on immune infiltration[35-38]. Over time, this coupling of senescent-cell SASP output with spatial barrier formation disrupts the spatiotemporal axes of anti-tumor immunity and consolidates immune exclusion.
2.3 Phenotypic polarization: From microenvironmental landscape to immunotherapy response
Integrating cellular composition, spatial distribution, and functional states, the TIME can be broadly categorized into immune-inflamed, immune-excluded, and immune-desert phenotypes. Immune-inflamed TIMEs are characterized by abundant intratumoral CD8+ T cells, high expression of effector molecules, and efficient spatial colocalization of immune and tumor cells, and are generally associated with robust tumor-suppressive capacity and favorable responses to immune checkpoint blockade (ICB)[39-41]. By contrast, immune-excluded and immune-desert TIMEs display quantitative and qualitative deficits in effector immunity, including reduced effector-cell infiltration, expansion of Tregs and MDSCs, functional exhaustion of T cells, elevated checkpoint expression, and physical or metabolic exclusion barriers[37,38].
Accumulating evidence implicates senescence-associated transcriptional reprogramming as an important contributor to malignant TIME polarization toward these immunosuppressive archetypes[5-8]. In early tumorigenesis or acute injury, transient SASP production and acute activation of innate sensing pathways can recruit NK cells and macrophages, facilitating immunosurveillance and elimination of aberrant cells. However, as senescent cells accumulate and SASP transcriptional networks become epigenetically stabilized, the SASP undergoes a functional transition toward chronic, pro-tumorigenic programs that favor immune checkpoint upregulation, recruitment of suppressive cell subsets, and maintenance of stromal barriers[5,9-12]. We find it useful to consider these three archetypes not as static categories but as reference points along a conceptual, heuristic continuum of immunosuppression, as summarized in Figure 1. Current evidence indicates that senescence and the SASP can contribute to this immunosuppressive remodeling; it does not, however, establish that individual tumors traverse these states in a fixed or unidirectional order. Depending on tumor type, senescence burden, and secretome composition, tumors may enter, stall at, bypass, or combine these phenotypes, and transitions between them are likely to be bidirectional rather than obligatory. Within this framework, chronic engagement of endogenous inflammatory signaling, immune-cell epigenetic lock-in, and metabolic-epigenetic coupling can bias an immune-inflamed TIME toward immune-excluded or immune-desert configurations, characterized, respectively, by SASP-driven checkpoints, ECM, and angiogenic barriers erected by senescent tumor cells and CAFs, and by dominance of senescent myeloid cells and MDSCs with minimal effector infiltration (Figure 1), a shift that tends to parallel a decline in immunotherapy responsiveness. We present this axis as a heuristic map to organize the mechanistic dissection that follows, rather than as an experimentally validated sequence. In the following sections, we therefore interpret TIME polarization through the lens of senescence-associated transcriptional reprogramming and its three-layer mechanistic hierarchy.
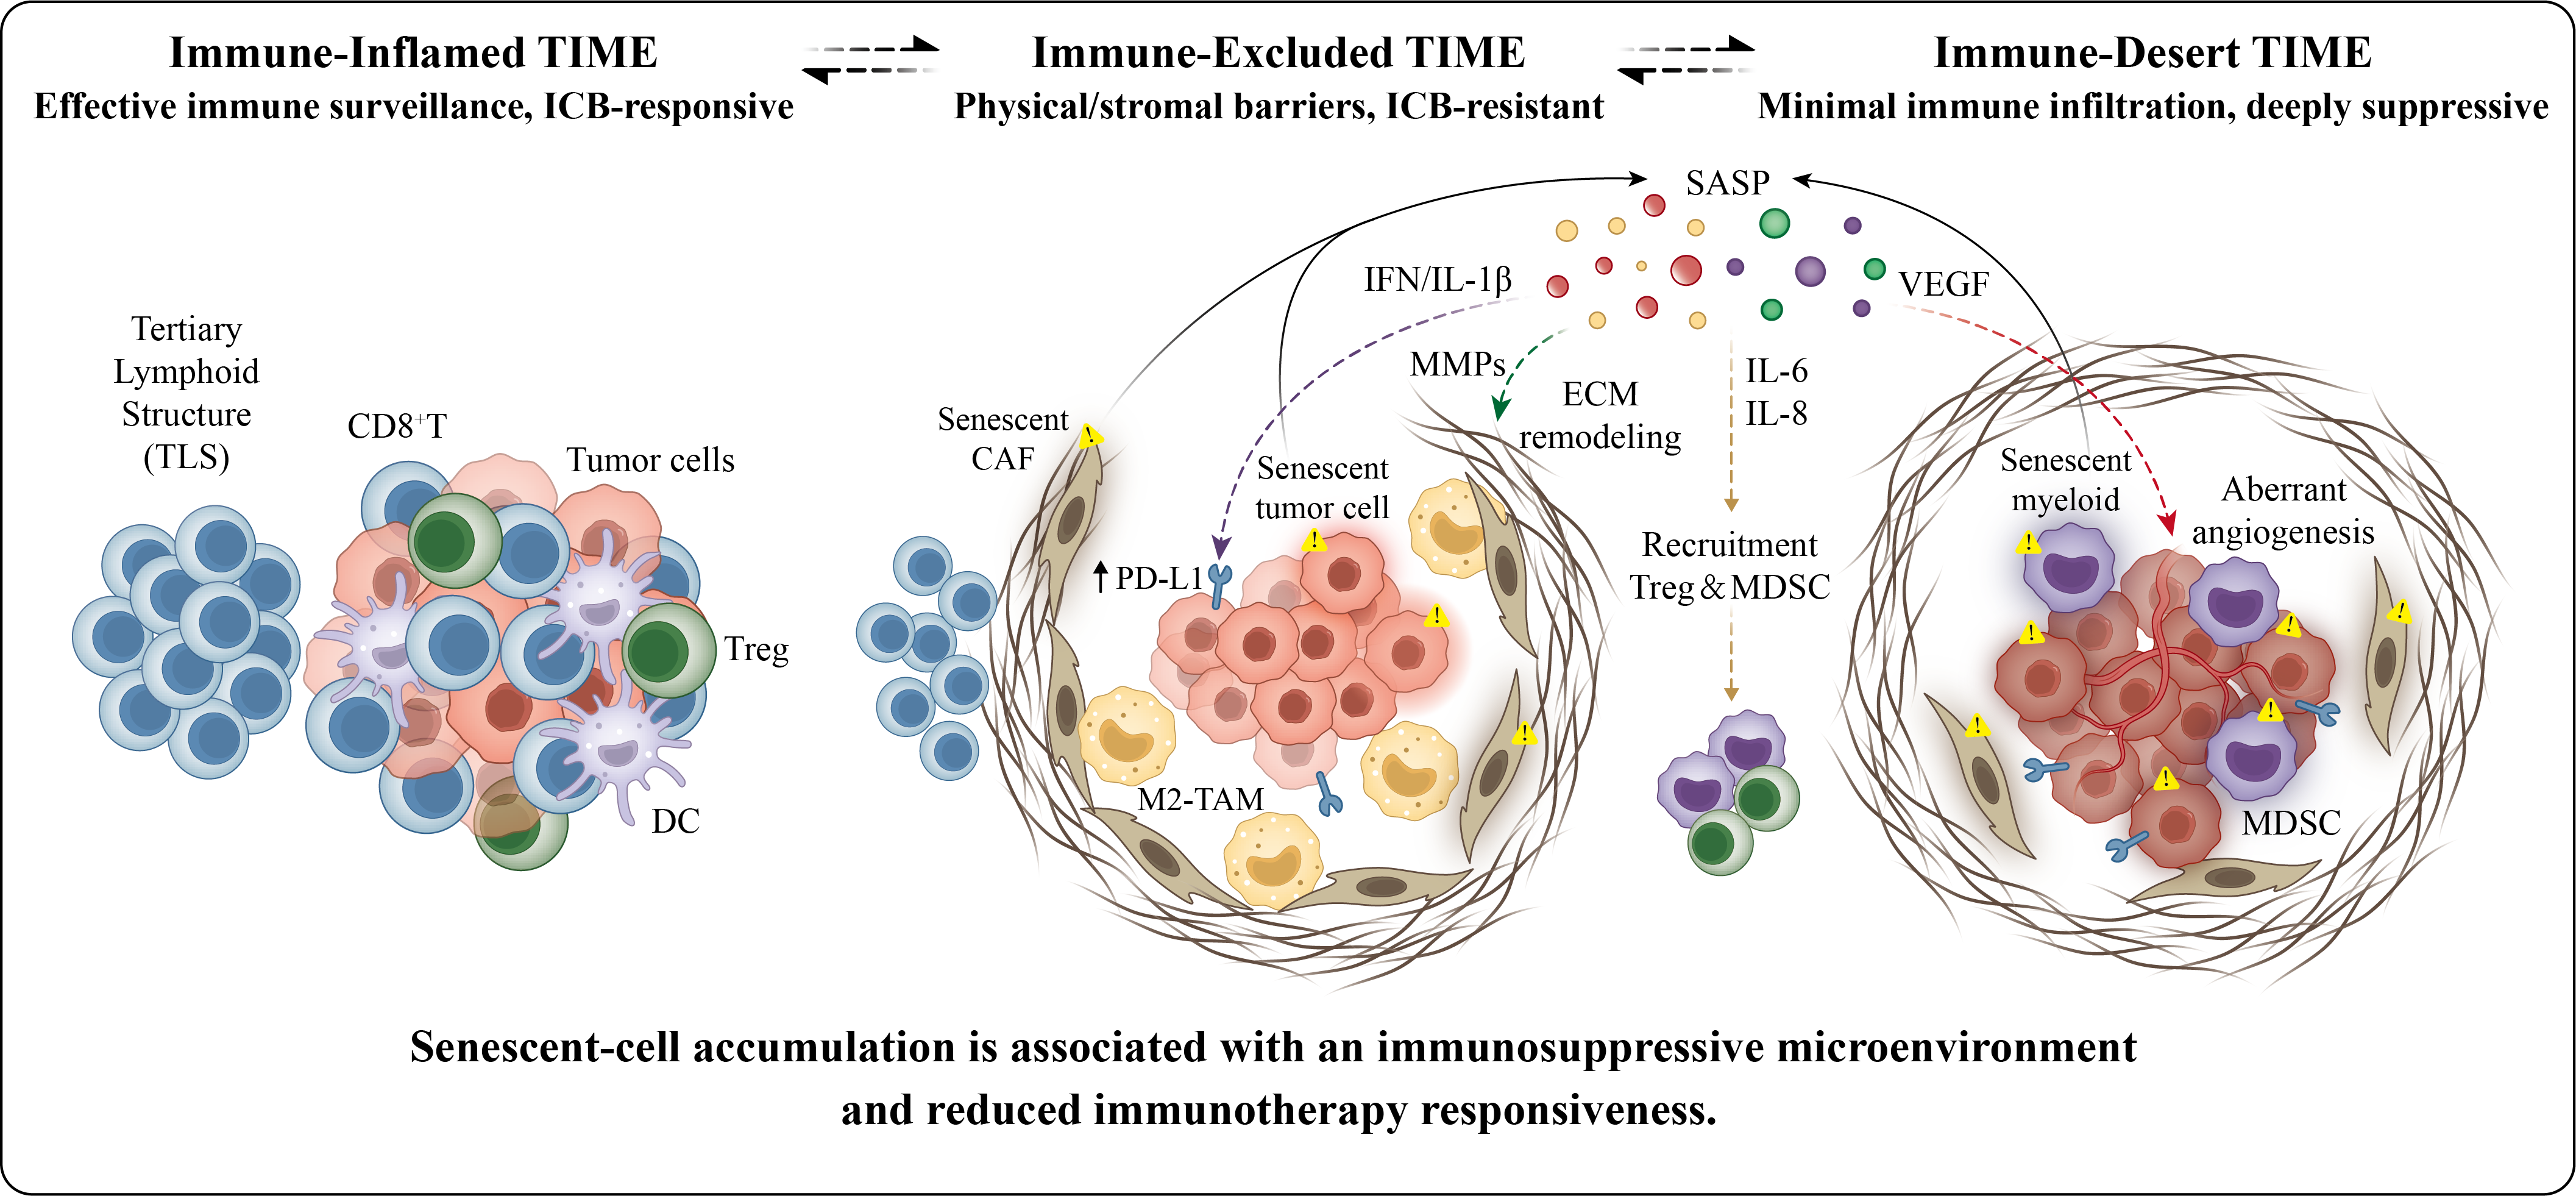
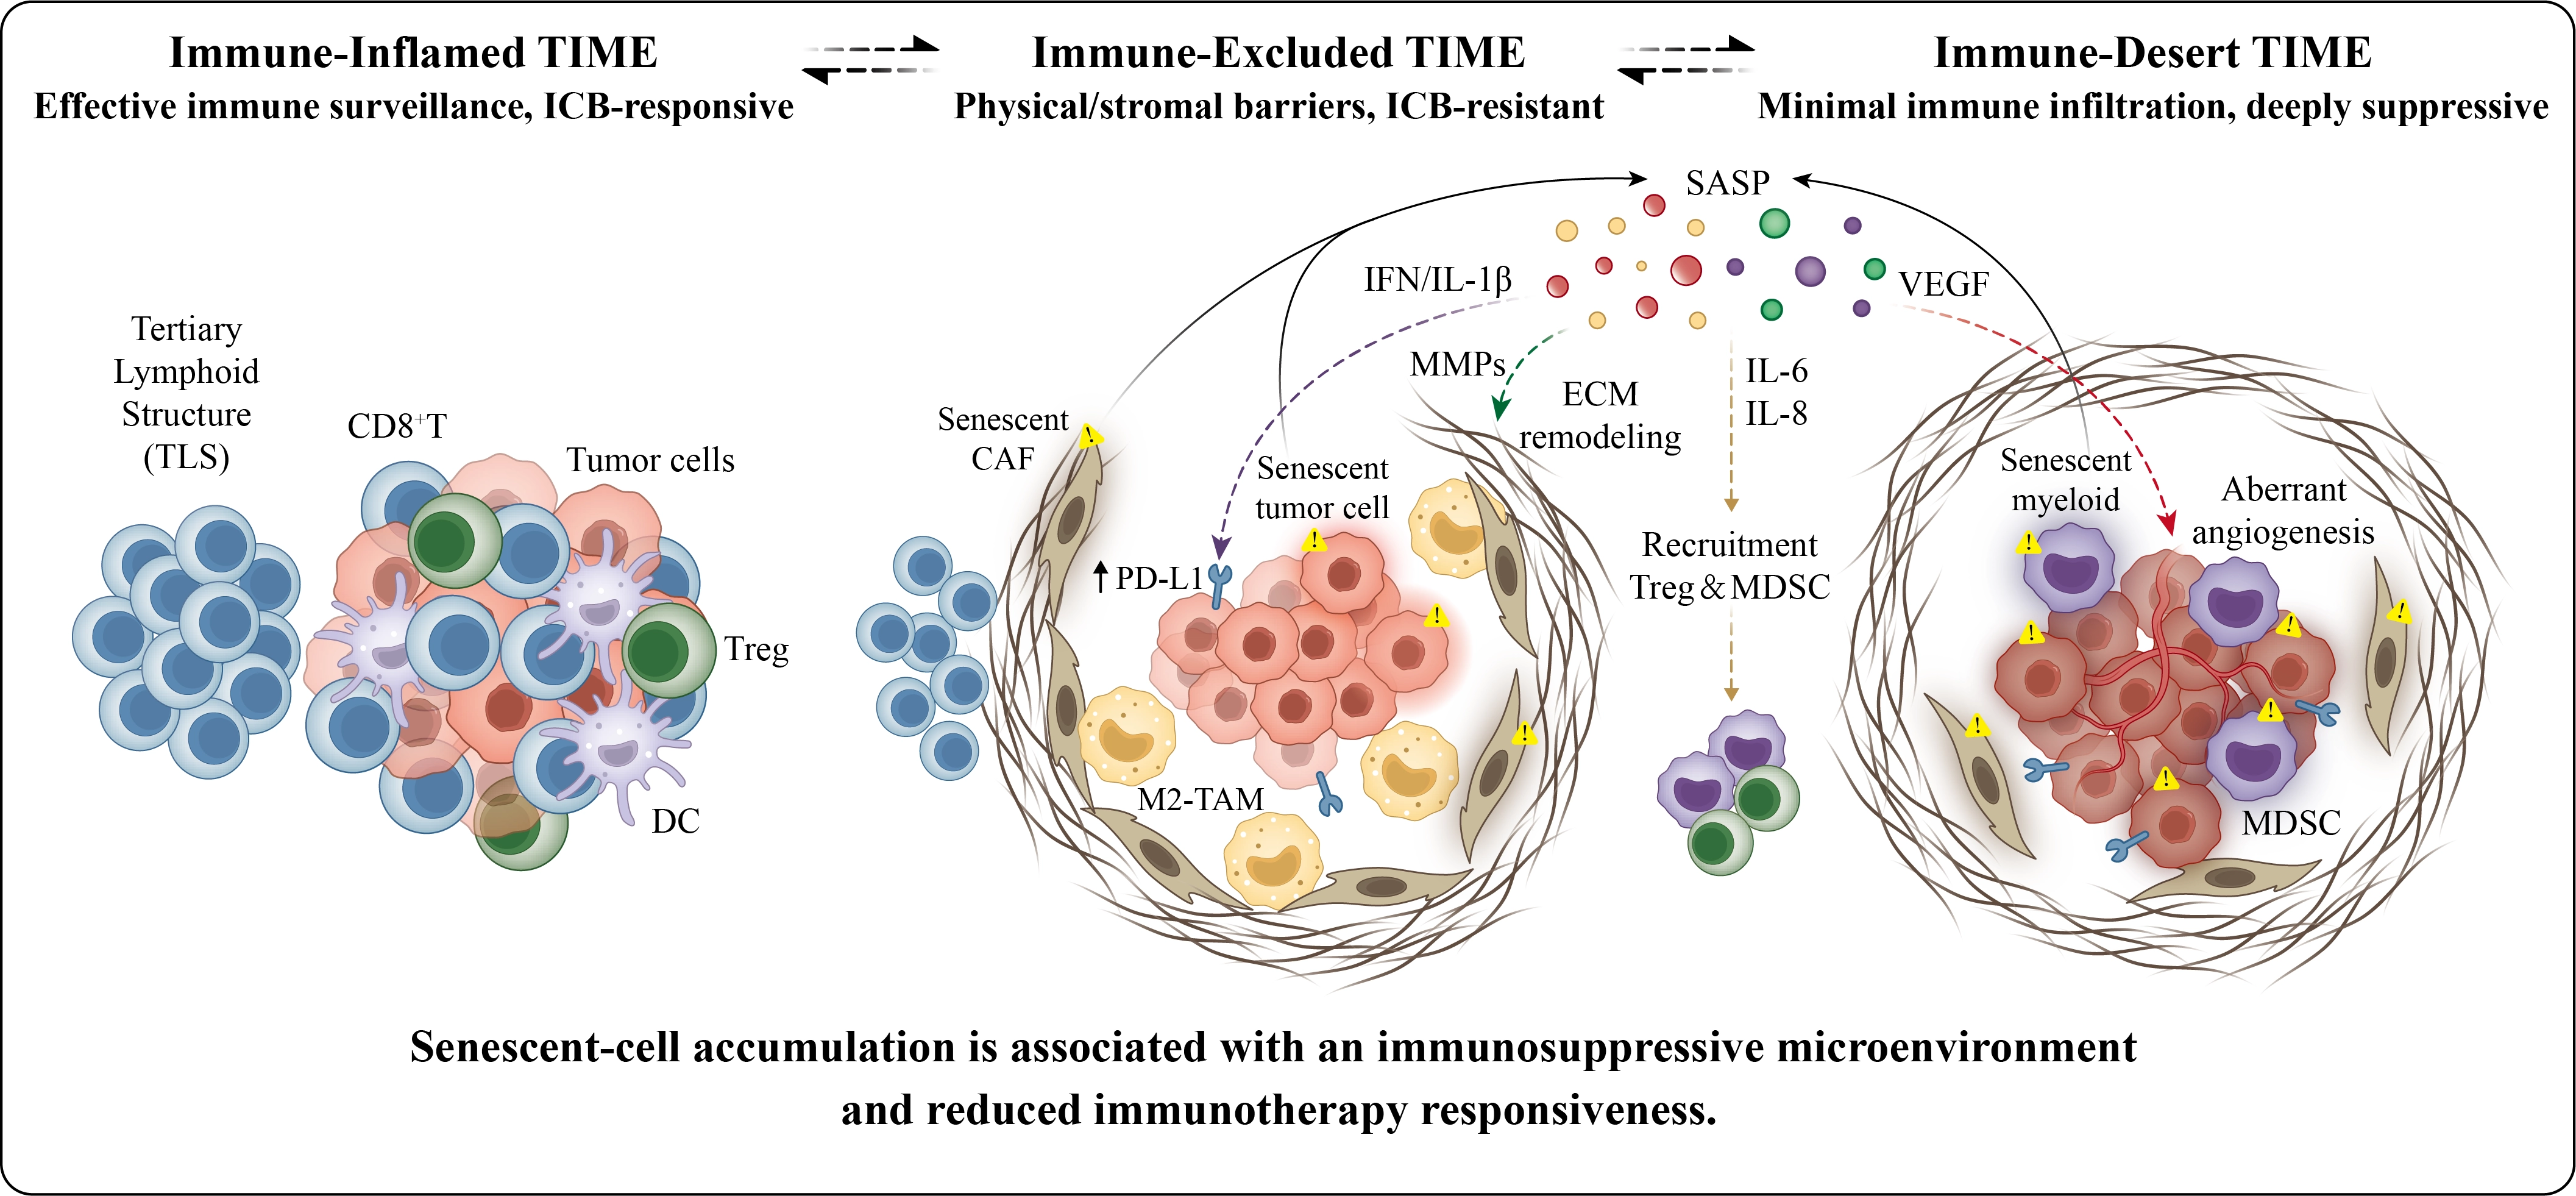
Figure 1. Three-layer framework of senescence-associated transcriptional reprogramming in the tumor immune microenvironment. Senescence-associated transcriptional reprogramming reshapes the tumor immune microenvironment through three interconnected mechanistic layers. The inflammatory-hub layer is driven by the SASP, which recruits myeloid-derived suppressor cells and M2-like macrophages while excluding effector T cells. The epigenetic-lock-in layer stabilizes immunosuppressive transcriptional states through chromatin modifications, including histone Kac and Kla. The metabolic-epigenetic layer links altered tumor metabolism, such as lactate accumulation and acidification, to the epigenetic changes that reinforce immune dysfunction. Together, these layers illustrate how senescent-cell burden is associated with an immunosuppressive microenvironment and reduced immunotherapy responsiveness. SASP: senescence-associated secretory phenotype; Kac: acetylation; Kla: lactylation; TIME: tumor immune microenvironment; ICB: immune checkpoint blockade; TLS: tertiary lymphoid structures; Treg: regulatory T cell; DC: dendritic cell; CAF: cancer-associated fibroblast; TAM: tumor-associated macrophage; MMPs: matrix metalloproteinases; ECM: extracellular matrix; MDSC: myeloid-derived suppressor cells; IFN: interferon.
3. Senescence-Driven Immune Consequences in the TIME
Cellular senescence reshapes the TIME by driving a progressive transition from transient immune activation to persistent immune suppression[42-47]. This process is characterized by a decline in effector-cell fitness, expansion of immunoregulatory populations, accumulation of stromal and metabolic barriers, and reinforcement of immune checkpoint signaling. These changes do not result from SASP secretion in isolation, but from a broader program of senescence-associated transcriptional reprogramming that stabilizes chronic inflammatory signaling and incrementally edits the TIME into an immune-tolerant state.
3.1 Early immunosurveillance versus chronic immune suppression
Senescence exerts biphasic effects on tumor immunity. In early tumorigenesis or acute injury, transient SASP production and innate sensing activation recruit NK cells and macrophages, facilitating immunosurveillance and clearance of aberrant cells[46]. However, as senescent cells accumulate and their transcriptional programs become epigenetically stabilized, this initially immunostimulatory output is reshaped into a chronic, pro-tumorigenic secretome that fosters durable immune suppression[48-50]. This temporal shift represents a key conceptual axis for understanding both spontaneous tumor progression and therapy-induced senescence (TIS) outcomes.
3.2 Effector attrition and expansion of immunoregulatory networks
A central immune consequence of senescence within the TIME is the coupled erosion of effector immunity and amplification of suppressive cellular networks[42-45]. Aging and chronic antigenic stimulation impair T-cell proliferative fitness, memory differentiation, and metabolic adaptability, while accelerating the acquisition of dysfunctional states marked by reduced responsiveness and increased expression of inhibitory receptors such as PD-1 and CTLA-4[42-44]. These defects directly compromise anti-tumor surveillance and diminish the capacity of effector lymphocytes to respond to immunotherapy.
At the same time, the senescent microenvironment favors expansion and recruitment of suppressive myeloid and lymphoid populations. Tregs accumulate and directly constrain effector T-cell function[23,24], while MDSCs suppress T-cell activation through ARG1, ROS, and additional inhibitory mediators[25-27]. TAMs are progressively skewed toward immunoregulatory phenotypes that promote tissue remodeling, angiogenesis, and cytokine-mediated suppression[7,8,28,29]. Thus, the net effect of senescence is not merely reduced immune activity, but an active rewiring of the TIME toward suppressive cellular dominance.
3.3 Stromal, checkpoint, and spatial consequences
Senescence also remodels the non-cellular and signaling landscape of the TIME. The SASP includes matrix metalloproteinases (MMPs), vascular endothelial growth factor (VEGF), inflammatory cytokines, and pro-fibrotic mediators, whose release drives extracellular matrix remodeling, aberrant neovascularization, and progressive stromal stiffening. Together with the spatial reorganization of the stromal compartment, these alterations reinforce physical barriers to immune-cell trafficking and contribute to spatial immune exclusion[35,37,38].
A further downstream consequence is the upregulation of immune checkpoint pathways[51-53]. Therapy-induced senescence directly increases PD-L1 in cancer cells through both transcriptional and post-translational mechanisms; the latter requires ribophorin 1 (RPN1), which promotes PD-L1 N-glycosylation, and RPN1 depletion lowers PD-L1 through an ER-lysosome-associated degradation pathway, increasing susceptibility to T-cell-mediated killing and suppressing recurrence in irradiated tumors[53]. On this background, at least three separable inputs further amplify checkpoint-ligand expression. First, in tumor-associated neutrophils, immune-cell-derived IFN-γ activates Janus kinase (JAK)/Signal Transducers and Activators of Transcription (STAT) 1, while tumor-derived lactate activates an MCT1/NF-κB/COX-2 axis; both induce PD-L1, and COX-2 inhibition with celecoxib reduces survival of lactate-stimulated PD-L1+ neutrophils and restores lenvatinib efficacy in hepatocellular carcinoma. Second, tumor-derived exosomes deliver HMGB1 to macrophages, where TLR2-MyD88-NF-κB signaling drives de novo PD-L1 synthesis together with a glycolytic shift. Third, SASP mediators such as IL-1β further amplify NF-κB-dependent checkpoint expression: macrophage-derived IL-1β upregulates PD-L1 on tumor cells, and IL-1β blockade synergizes with anti-PD-L1 therapy[54].
Each of these mechanisms was characterized in specific tumor models, and their relative contribution to checkpoint-inhibitor resistance in patients remains to be defined. Collectively, these stromal, spatial, and checkpoint changes define the macroscopic output of senescence-associated TIME remodeling, while the mechanistic basis of this transition resides in the layered transcriptional and epigenetic circuitry outlined in Section 4.
4. Mechanistic Layers of Senescence-Associated Transcriptional Reprogramming
The immune consequences outlined above are underpinned by a hierarchical and interconnected architecture of senescence-associated transcriptional reprogramming[13-16]. Conceptually, this architecture can be resolved into three mechanistic dimensions: endogenous inflammation-driven signaling, lineage-specific epigenetic lock-in of immune cells, and metabolic-epigenetic coupling. Together, these dimensions convert transient cellular stress into durable transcriptional states that sustain immune suppression, stromal remodeling, and therapeutic resistance within the TIME[55,56].
4.1 Endogenous inflammation-driven signaling
At the inflammatory signaling dimension, intracellular stress in senescent cells activates an endogenous transcriptional program centered on the cGAS-STING-NF-κB-IFN axis. Accumulation of cytoplasmic double-stranded DNA activates cyclic GMP-AMP synthase (cGAS), which generates 2’3’-cGAMP and thereby activates stimulator of interferon genes (STING)[57-59]. STING signaling bifurcates into a TBK1-IRF3 arm that induces type I interferons and an NF-κB arm that drives inflammatory transcription, together establishing a central node for SASP initiation and amplification[60-62]. This pathway is itself engaged during senescence: chronic cGAS-STING activation accompanies macrophage immunosenescence[63], T-cell senescence[64], and cellular senescence in age-related pathology[65], suggesting that senescent cells may sustain pathway activity through persistent cytosolic DNA exposure rather than acute damage alone. Notably, however, these senescence-cGAS/STING associations were established largely outside tumor models.
The role of this axis is context-dependent and dual, varying with the magnitude, duration, and cellular context of activation. Acute, robust activation promotes dendritic-cell maturation, enhances CD8+ T-cell priming, and supports an immune-stimulatory microenvironment; within senescent cells, strong STING signaling can additionally engage apoptotic and autophagy-dependent clearance programs and reinforce immune surveillance, thereby contributing to tumor suppression[66-68]. In senescent tissues and tumors, by contrast, chronic pathway activation sustains NF-κB-dependent transcription of IL-6, TNF-α, and other SASP mediators[69-71], and cancer cell-autonomous cGAS-STING signaling has been associated with drug resistance[72]. In tumor models, senescent stromal and myeloid cells establish an immunosuppressive niche that recruits MDSCs and impairs antitumor immunity[19,73].
These signals have also been associated with PD-L1 upregulation, Treg accumulation, and M2-like TAM polarization, although the evidence for each is distinct and the direct causal contribution of senescence to any of them remains to be fully defined. PD-L1 is upregulated on senescent cells in vitro and in aged tissues in vivo, where it restrains their clearance by cytotoxic lymphocytes; PD-1 blockade reduces the senescent-cell burden and ameliorates ageing-associated phenotypes in mice, in a CD8+ T-cell-dependent manner. Foxp3+ regulatory T cells accumulate in hypoxic, senescence-rich tumors, and hypoxia-driven, TET1-dependent repression of cGAS increases intratumoral Tregs while reducing effector CD8+ T cells[74]. SASP components have likewise been linked to immunosuppressive myeloid reprogramming: senescent stroma recruits granulocytic MDSCs and blunts CD8+ T-cell function[19], and cGAS-STING-NF-κB activation can license an M2-like polarization program in myeloid cells[75], although the latter was demonstrated in microglia after central nervous system injury rather than in tumor-associated macrophages.
In parallel, senescent-cell-derived lactate and other SASP components further skew tumor-associated macrophages toward an immunosuppressive M2-like phenotype[76], reinforcing the niche established by senescent stromal and myeloid cells. Importantly, the evidence underlying all three immune features is largely correlative and derives from models in which senescence coexists with hypoxia, lactate accumulation, and other metabolic stressors; no senescence-specific in vivo loss-of-function experiment has yet established that senescent cells are necessary or sufficient for any of them. The inference that senolytic or senomorphic therapy would reverse these features simultaneously therefore remains provisional. This duality carries direct therapeutic implications, since interventions targeting the pathway must preserve its protective, surveillance-promoting functions while curbing its chronic pro-inflammatory output[77]. This inflammatory dimension therefore explains how senescent cells convert damage sensing into durable immunoregulatory output.
4.2 Epigenetic lock-in of immune lineages
A second mechanistic dimension involves lineage-specific transcriptional and epigenetic reprogramming in immune cells exposed to persistent antigenic, inflammatory, and metabolic stress. In CD8+ T cells, chronic stimulation promotes the establishment of stable exhaustion-associated chromatin states, marked by progressive accumulation of repressive histone modifications and consolidation of DNA methylation programs that constrain functional recovery even after immune checkpoint blockade[78-80]. Sustained inflammatory pressure within the senescent TIME may therefore not simply induce transient dysfunction but drive an epigenetic lock-in that stabilizes T-cell exhaustion; these chromatin states, however, have been defined largely in chronic infection and tumor models that were not specifically characterized for senescence, and their persistence within a senescent TIME has not been demonstrated directly.
By contrast, myeloid populations retain greater plasticity yet are nonetheless subject to sustained transcriptional reprogramming[81-84]. Hypoxia and inflammatory signaling through HIF-1α and NF-κB skew TAMs toward immunosuppressive states characterized by elevated ARG1 and IL-10 expression. In specific contexts, hypoxic TAMs may also exhibit alternative epigenetic states, including DNA hypomethylation and secretion of CXCL9/10, indicating that their terminal phenotype reflects real-time integration of local cues rather than a fixed binary state.
Similar principles apply to DCs and NK cells. Hypoxia perturbs DC subset balance by reducing cDC1 abundance and favoring dysfunctional accumulation of cDC2 populations, thereby weakening antigen cross-presentation and CD8+ T-cell priming[85,86]. In NK cells, hypoxia and metabolic stress disrupt mitochondrial homeostasis and constrain the metabolic programs required for effector function, limiting NK-cell infiltration and antitumor cytotoxicity within the tumor microenvironment[87,88]. Hypoxia additionally drives CD39/CD73-dependent adenosine accumulation, and silencing CD73 restores antitumor immunity, indicating that adenosinergic signaling is a dominant brake on NK-cell activity in hypoxic tumors[89]. Hypoxia also reduces surface expression of the activating receptor NKG2D and of intracellular perforin and granzyme B, an effect partially reversed by IL-2 activation. By contrast, surface expression of the inhibitory receptor NKG2A is not altered by acute hypoxia; upregulation of NKG2A, TIGIT, and PD-1 is better attributed to chronic tumor-microenvironment-driven NK-cell exhaustion. Independently of oxygen tension, lactate accumulation blunts NK-cell immunosurveillance: LDHA-dependent lactic acid production prevents NFAT upregulation in T and NK cells, diminishing IFN-γ production and permitting tumor immune escape in melanoma models. Thus, distinct immune lineages acquire different forms of epigenetic and transcriptional constraint, but all converge on reduced antitumor effector function.
4.3 Metabolic-epigenetic coupling
The third mechanistic dimension is metabolic-epigenetic coupling, through which microenvironmental metabolic perturbations are translated into stable chromatin and transcriptional states[13,14,90-92]. Hypoxia, lactate accumulation, oxidative stress, and altered nutrient availability directly modulate the activity of chromatin-modifying enzymes and thereby shape the epigenetic landscape of tumor, stromal, and immune cells, with cGAS-STING signaling itself subject to metabolic regulation within the tumor microenvironment[93]. In hypoxic tumor cells, HIF-1α induces TET1, which upregulates miR-25 and miR-93; these microRNAs repress cGAS and thereby dampen cytosolic DNA-driven type I interferon responses, suppressing innate immune initiation. This axis is functionally consequential in vivo: inhibiting miR-25/93 restored effector CD8+ T-cell infiltration, reduced intratumoral Tregs, and delayed tumor growth in an immune-dependent manner, since the effect was lost in immunodeficient mice[74]. Because the mechanism was characterized primarily in breast cancer cell lines and xenograft models, whether senescent tumor cells converge on the same TET1-miR-25/93 node, and whether this is a generalizable feature of senescence-associated reprogramming, remains to be determined.
Lactate represents another major node in this dimension. Beyond supporting histone acetylation through increased acetyl-CoA availability, lactate serves as a substrate for histone lysine lactylation, in which lactate-derived lactyl-CoA is deposited on histone lysine residues; the best-characterized mark, H3K18la, links a high-lactate microenvironment to transcriptional activation and has been associated with an immunosuppressive, M2-like polarization of tumor-associated macrophages[94]. Because lactylation and acetylation modify overlapping lysine residues, the relative abundance of the two marks may report on the metabolic state of the microenvironment, although whether they compete directly at specific residues remains incompletely defined. Separately, lactate-rich, acidic microenvironments are associated with upregulation of PD-L1 on tumor and myeloid cells[51]; whether lactate drives PD-L1 directly through histone modification, however, remains to be established, and we present these as correlated rather than causally linked observations. This process is reinforced by intracellular oxidative stress in senescent cells, where ROS accumulation triggers mitochondrial DNA leakage and further activates innate sensing pathways, thereby amplifying SASP secretion and inflammatory transcription[91]. In this way, extrinsic metabolites and intrinsic metabolic damage cooperate to convert transient metabolic stress into self-reinforcing epigenetic and transcriptional programs of immune suppression.
Importantly, this metabolic-epigenetic dimension provides a mechanistic bridge between microenvironmental physiology and therapeutic intervention: because metabolic cues can stabilize immunosuppressive gene expression through chromatin remodeling, targeted disruption of metabolic-epigenetic coupling nodes, including combinations such as HDAC and PI3K inhibition[92], offers a rational strategy to destabilize the senescence-associated transcriptional state and restore immune responsiveness, although such combinations have not yet been shown to reverse senescence-associated transcriptional states specifically.
4.4 An integrated three-dimensional framework
Taken together, senescence-associated transcriptional reprogramming within the TIME can be understood as a three-dimensional framework in which endogenous inflammatory signaling initiates chronic transcriptional activation, lineage-specific epigenetic lock-in stabilizes dysfunctional immune states, and metabolic-epigenetic coupling entrenches these programs in a self-reinforcing manner[5,13-16]. As depicted in Figure 2, these three dimensions do not operate in isolation but are interconnected through reciprocal crosstalk: inflammatory signaling through the cGAS-STING-NF-κB axis amplifies SASP output and PD-L1 expression; lineage-specific epigenetic lock-in stabilizes dysfunctional states across CD8+ T cells, TAMs, DCs, and NK cells; and metabolic inputs such as ROS/mtDNA leakage, hypoxia/HIF-α/TET1, and lactate-driven histone modifications feed back onto both inflammatory and epigenetic layers (Figure 2). Together, they form a self-reinforcing loop that converts transient stress into stable, hard-to-reverse functional exhaustion. This framework explains how the immune consequences described in Section 3 emerge from intracellular and intercellular regulatory circuits rather than from SASP abundance alone. It also provides a mechanistic basis for therapeutic design, as distinct interventions can be aligned with specific dimensions of this hierarchy, including inflammatory hubs, immune-cell epigenetic states, or metabolically driven chromatin remodeling[63-65,76,77,92].
Figure 2. Integrated three-dimensional framework illustrating how senescence-associated transcriptional reprogramming reshapes the TIME. Dimension ①: Inflammation-driven signaling (top-left) centers on the cGAS-STING axis, transducing through NF-κB and TBK1/IRF3 to drive Type I IFN, SASP amplification, PD-L1 upregulation, and immunosuppressive cell recruitment. Dimension ②: Epigenetic lock-in (bottom) stabilizes dysfunctional states across immune lineages, including TOX/DNMT/H3K27me3-mediated CD8+T-cell exhaustion, HIF-1α/NF-κB-driven M2 reprogramming, cDC1 loss with cDC2 dysfunction, and CD73/NKG2A-mediated NK suppression. Dimension ③: Metabolic-epigenetic coupling (top-right) integrates ROS/mtDNA leakage, hypoxia/HIF-α/TET1, and lactate-driven histone acetylation/lactylation into chromatin states. The three dimensions form a self-reinforcing loop via reciprocal crosstalk (outer arrows), collectively producing stable, hard-to-reverse functional exhaustion and loss of effector capacity. TIME: tumor immune microenvironment; cGAS: cyclic GMP-AMP synthase; STING: stimulator of interferon genes; SASP: senescence-associated secretory phenotype; DC: dendritic cell; ROS: reactive oxygen species; MDSC: myeloid-derived suppressor cells; Treg: regulatory T cells; TAM: tumor-associated macrophages; NK: natural killer; NF-κB: nuclear factor kappa B; IFN: interferon.
5. Mechanism-Guided Therapeutic Opportunities to Reverse Senescence-Associated Immunosuppression
The hierarchical model outlined above suggests that durable immunosuppression in the TIME arises from senescent-cell accumulation, chronic activation of endogenous inflammatory hubs, epigenetic lock-in of immune cells, and metabolic-epigenetic coupling[5,13-16]. Therapeutic strategies to reverse senescence-associated immunosuppression must therefore operate at multiple levels, including direct modulation of senescent-cell burden, targeted reprogramming of transcriptional and epigenetic circuits, and temporally optimized combinatorial regimens with immunotherapy, particularly in elderly patients.
5.1 Foundational strategy: senolysis and senescence-phenotype remodeling
Direct intervention against senescent cells within the TIME represents a foundational approach to alleviating systemic immunosuppression[95-99]. Senolytics selectively induce apoptosis of senescent cells by targeting senescent cell anti-apoptotic pathways (SCAPs), including BCL-2 family members, PI3K/AKT signaling, and FOXO-p53 interactions[100-102]. Preclinical models demonstrate that genetic or pharmacological clearance of p16^INK4a+ senescent macrophages delays tumor growth in KRAS-driven lung cancer[95,102], and that combining senolytics with checkpoint blockade reduces tumor burden and prolongs survival in several syngeneic and genetically defined tumor models[96]. Because such clearance eliminates senescent stromal and myeloid cells that sustain an immunosuppressive niche—senescent stroma, for instance, recruits granulocytic MDSCs through IL-6 and blunts CD8+ T-cell function[19]—senolytic approaches may relieve local suppression of CD8+ T cells, although direct evidence that senolysis restores CD8+ T-cell proliferation within tumors remains limited and this inference is largely extrapolated from stromal-senescence models. Combinations such as dasatinib plus quercetin or BCL-2 family inhibitors (e.g. navitoclax) reduce senescent-cell burden and improve responses to immunotherapy in experimental settings[96,100], and senolytic-based regimens have now entered clinical testing[96].
However, TIS exemplifies the biphasic nature of senescence in tumor control. In early phases, TIS can enhance immunosurveillance by increasing tumor immunogenicity and promoting SASP-mediated recruitment of effector cells[46,103,104]. At later stages, persistent TIS and epigenetically stabilized SASP programs promote chronic inflammation, immunosuppressive cell recruitment, and checkpoint upregulation, thereby fostering relapse and resistance[53,73,105]. Indiscriminate or premature senolysis may therefore abrogate beneficial early effects of senescence, whereas delayed intervention risks acting on a microenvironment that has already entered an epigenetically constrained, irreversibly suppressive state.
These limitations underscore the appeal of senomorphic strategies that remodel, rather than eradicate, senescent cells. Senomorphics aim to preserve beneficial features, such as T-cell recruitment and tumor antigenicity, while selectively attenuating deleterious SASP components and immunosuppressive transcriptional programs[97,98,103,106]. For example, concurrent modulation of p16 and PD-L1 expression can enhance tumor immunogenicity[97], while targeting epigenetic effectors such as KDM4 suppresses pro-tumorigenic SASP factors in stromal cells and promotes cancer-cell apoptosis[98]. By acting at the level of transcriptional and epigenetic circuitry rather than bulk senescent-cell burden alone, these approaches are theoretically better suited to maintaining the TIME in a controlled, anti-tumor state[13-16,54,98].
5.2 Targeting key nodes in the transcriptional and epigenetic circuitry
Building on the three-layer framework outlined in Section 4, therapeutic interventions can be conceptualized as targeting inflammatory hubs, immune-cell epigenetic states, and metabolic-epigenetic coupling nodes[13-16]. Table 1 summarizes this mechanism-aligned strategy, mapping the key molecular nodes, their immunological consequences, and representative therapeutic agents onto each dimension of the hierarchy. In the following, we discuss these axes in turn.
Table 1. Mechanism-aligned therapeutic strategies for senescence-driven TIME reprogramming.
| Agent | Mechanistic layer | Molecular target | Effect/immunological consequence |
| Ruxolitinib | Inflammatory hub | JAK1/2 | Reduces SASP; decreases MDSC recruitment[103] |
| Vorinostat | Epigenetic lock-in | HDAC | Enhances antigen presentation; synergy with ICB[111] |
| Decitabine | Epigenetic lock-in | DNMT | Modulates T-cell exhaustion |
| JQ1 | Epigenetic lock-in | BET/BRD4 | Decreases immunosuppressive cytokines[109] |
| Tazemetostat | Epigenetic lock-in | EZH2 | Enhances immune surveillance[9] |
| AZD3965 | Metabolic-epigenetic | MCT1 | Reduces lactate-driven immunosuppression |
| CUDC-907 | Metabolic-epigenetic | HDAC + PI3K | Chromatin remodeling; proposed immunotherapy sensitization[92] |
| Dasatinib + Quercetin | Senescent-cell burden | Broad SCAP | Reduces senescent burden; restores CD8+ proliferation[96,121] |
| Navitoclax | Senescent-cell burden | BCL-2/BCL-xL | Reduces senescent burden[100] |
TIME: tumor immune microenvironment; JAK: Janus kinase; SASP: senescence-associated secretory phenotype; MDSC: myeloid-derived suppressor cells; HDAC: histone deacetylase; ICB: immune checkpoint blockade; DNMT: DNA methyltransferase; BET: bromodomain and extraterminal; SCAP: senescent cell anti-apoptotic pathway.
At the transcriptional level, inhibition of the JAK/STAT pathway has emerged as a strategy to optimize SASP composition and mitigate deleterious chronic inflammation. Pharmacological JAK2/STAT3 blockade reduces expression of pro-tumorigenic SASP factors, diminishes MDSC accumulation, and enhances the immunogenicity of senescent cells, thereby potentiating responses to ICB in preclinical models[103,107]. Ruxolitinib and related JAK inhibitors exemplify senomorphic agents that suppress SASP output without necessarily eliminating senescent cells, and attenuate senescence-associated inflammation in non-malignant settings. At the same time, their broad impact on cytokine signaling and immune homeostasis demands careful dosing and patient selection to avoid systemic immune dysregulation.
At the epigenetic level, interventions targeting histone deacetylases (HDACs), DNA methyltransferases (DNMTs), and bromodomain and extraterminal (BET) proteins can remodel chromatin architecture and transcriptional accessibility[108-110]. HDAC inhibition enhances T-cell infiltration and synergizes with ICB[111], and additionally upregulates tumor PD-L1 expression[108], suggesting that combined HDAC and checkpoint inhibition may exploit this dual transcriptional effect. A mechanistic basis for the latter is provided by breast cancer cells, in which HDAC4 and the acetyltransferase NAT10 form a self-reinforcing loop that activates NF-κB and drives PD-L1 transcription, such that disrupting the axis reduces PD-L1 and restores antitumor immunity. Combined targeting of the JAK/STAT and HDAC pathways has been proposed as a means of simultaneously modulating inflammatory transcription and chromatin state; this dual-targeting strategy nevertheless remains hypothetical in the oncological setting, as the JAK/HDAC dual inhibitors reported to date were developed for non-malignant inflammatory disease, and evaluation in therapy-induced senescence or high senescence burden is still awaited[112]. BET inhibitors targeting BRD4 and associated super-enhancer networks engage host immune responses and regulate immune checkpoint ligand expression, and have been proposed to dampen pro-tumorigenic SASP programs, although their broad transcriptional impact necessitates careful timing and combination design.
Metabolic-epigenetic coupling nodes offer additional opportunities for intervention. Hypoxia is a shared feature of senescent and tumor microenvironments and broadly constrains effector immunity: it drives Treg- and type-2 conventional dendritic cell-dependent immunosuppression in hepatocellular carcinoma[85] and suppresses the pro-stimulatory phenotype of human dendritic cells, which local oxygenation can restore[86], while NK-cell infiltration and function are constrained by metabolic and mitochondrial dynamics within the TME[87]. At the epigenetic level, hypoxia promotes NF-κB- and TET2-dependent macrophage reprogramming that can override TME-driven immunosuppression[83], and the epigenetic landscape of tumor-associated macrophages is itself a determinant of immune evasion[84]. Lactate accumulation[113] and hypoxia[114] have also been shown to suppress effector immune function through chromatin-level mechanisms: hypoxia drives HIF1α-dependent, HDAC1- and PRC2-mediated silencing of effector genes in T and NK cells, conferring resistance to PD-1 blockade[114], whereas lactate and its metabolic intermediates alter histone acetylation and lactylation[94,115]. Whether such cues directly upregulate PD-L1 in senescent cells remains provisional: acetylation-dependent NF-κB activation does drive PD-L1 transcription in breast cancer cells[55], but the equivalent mechanism has not been demonstrated in senescent tumor cells. Combined HDAC and PI3K inhibition, exemplified by fimepinostat, has been explored preclinically and impairs NF-κB and PI3K/AKT signaling[92]; extending this to re-sensitize tumors to immunotherapy remains a proposal. Because these agents act at the third layer of the hierarchy, they may be particularly suited to reversing entrenched transcriptional states in chronically senescent TIMEs[116].
5.3 Combinatorial and temporally optimized strategies to overcome immune tolerance
Given the multilevel nature of senescence-associated TIME remodeling, single-agent interventions are unlikely to fully reverse immunosuppression. Multi-mechanistic combination strategies that integrate senescence-targeted therapies with ICB or cell-based immunotherapies are therefore gaining traction[73,113,115,117]. One emerging paradigm involves using senolytics or senomorphics as “microenvironmental primers” to reduce senescent-cell burden, remodel SASP composition, or relax epigenetic constraints, followed by or combined with ICB to capitalize on a temporarily more permissive immune landscape. For instance, senolytic depletion of senescent myeloid populations prior to ICB has been proposed as a means to enhance response, although this sequencing remains to be validated in controlled studies[19].
Targeting the cGAS-STING-NF-κB-IFN hub offers another axis for combination therapy[72,74,75,93]. STING agonists are being clinically evaluated in combination with PD-1/PD-L1 blockade, with the goal of converting immune-desert or immune-excluded tumors into immune-inflamed phenotypes through enhanced dendritic-cell activation and T-cell priming[62,118]. However, given the context-dependent duality of STING signaling, immunostimulatory when transiently activated, yet potentially immunosuppressive under chronic activation, these strategies must be carefully timed and dosed[61], particularly in senescent or TIS-rich microenvironments. Concepts such as combined TLR-STING agonist adjuvants, or integration of STING modulation with metabolic-epigenetic interventions[90], exemplify attempts to precisely steer this axis toward durable immune activation.
5.4 Mechanisms of senescence-associated resistance to immunotherapy
Senescence can reinforce resistance to checkpoint blockade through several converging mechanisms that map onto the three-layer framework, although the strength of the underlying evidence varies across mechanisms. First, the SASP recruits immunosuppressive myeloid cells that suppress effector lymphocyte function: stromal IL-6 drives granulocytic MDSC accumulation and blunts CD8+ T-cell responsiveness in senescent stroma[19], whereas in established hepatocellular carcinoma immature CCR2+ myeloid cells act through NK-cell inhibition to accelerate tumour growth[73]. Whether these populations also restrict effector T cells by spatial exclusion within the tumour parenchyma remains to be shown directly. Second, senescent cells heterogeneously express PD-L1 and thereby evade CD8+ T-cell surveillance, a state that tracks with a higher SASP burden[119]; this has been demonstrated in aged and injured non-malignant tissues, and whether an equivalent PD-L1-high senescent subpopulation dominates within tumours is not yet established. A contribution of histone lactylation to this state remains a mechanistic hypothesis rather than an established pathway[94]. Third, senescence-associated signalling is thought to converge with T-cell exhaustion programs and with depletion of the stem-like T-cell factor 1 (TCF1)+ precursor pool required for durable responses[120]; consistent with this, poor response to neoadjuvant chemoimmunotherapy in head and neck squamous cell carcinoma is associated with reduced CCR7+CD4+ naive T cells and a higher immunosenescence gene signature[96], although whether senescence causally drives this depletion has not been directly demonstrated. Fourth, metabolic competition and acidification within the tumour microenvironment impair effector T- and NK-cell function, principally through tumour-derived lactic acid[113]; although this mechanism is well established in tumours generally, the specific contribution of senescent cells remains to be defined. Fifth, sustained type I interferon signalling can lead to interferon desensitisation that blunts responsiveness to immunotherapy[117], an association that has not yet been causally linked to senescence. Finally, epigenetic stability of exhausted T cells limits the durability of reinvigoration achievable with checkpoint inhibitors[121], a principle established in exhausted CD8+ T cells and extended here to the senescent context. Taken together, these mechanisms provide a rationale for combining senescence-directed agents with immunotherapy; this rationale is now supported by early clinical data showing that neoadjuvant dasatinib plus quercetin with anti-PD-1 therapy achieved a major pathological response rate of 33.3% with grade 3-4 adverse events in only 4.2% of patients with resectable head and neck squamous cell carcinoma[96], although this was a single-arm study and direct causal demonstration that senescence mediates resistance in individual tumours remains an important gap for future studies.
5.5 Translational limitations, selectivity, and tolerability in older patients
Several considerations temper this therapeutic outlook. Current clinical evidence for senescence-targeting agents in oncology remains of low to very low certainty and is largely derived from small or early-phase studies. Most agents also have limited selectivity for senescent over non-senescent cells; navitoclax, for example, targets the broadly expressed anti-apoptotic proteins BCL-2 and BCL-xL, and its use is constrained by dose-limiting thrombocytopenia. The primary target population, elderly and frail patients, is precisely the group in whom tolerability is poorest and safety data are scarcest, so the favorable therapeutic index observed in young preclinical models may not translate. In addition, the heterogeneity of senescence phenotypes across tissues and stimuli complicates the identification of reliable biomarkers for patient stratification, and senescence also serves protective functions, including tumor suppression and tissue repair, so its indiscriminate disruption carries a risk of unintended harm. We therefore propose, as a hypothesis to be tested rather than an established treatment paradigm, that biomarker-guided, context-specific strategies may be preferable to broad application. This framework remains speculative and will require prospective validation before it can inform clinical decision-making.
From a clinical translation perspective, these combinatorial strategies may be particularly relevant for patients with a high systemic senescence burden, a state that is more common, but not universal, in older individuals and that can coexist with immunosenescence and reduced tolerance to high-dose chemo-radiotherapy[4,12,42]. We emphasize that chronological age is not a reliable surrogate for local senescence burden, and stratification should therefore be guided by directly measured senescence markers rather than by age. On this basis, we propose the following as a testable hypothesis rather than an established treatment strategy: patients with a lower measured senescence burden might be evaluated for transient senomorphic modulation with early integration of ICB, whereas those with a high measured senescence burden might be candidates for phased regimens combining senolytics or senomorphics, epigenetic reprogramming agents, and carefully titrated ICB or cell therapy[94-98]. Each of these proposals would require validated senescence biomarkers for patient selection and prospective clinical evaluation before it could inform practice. Achieving this will depend on the development of robust biomarkers, including SASP profiles, senescence-associated transcriptional signatures, epigenetic clocks, and spatial senescence maps, to define local TIME senescence states and identify optimal therapeutic windows[5,13-16]. By aligning therapeutic design with the three-layer hierarchy of senescence-associated transcriptional reprogramming and by incorporating biomarker-defined senescence-burden and phenotype-based stratification, with chronological age considered separately as a tolerability variable, it may become possible to transform senescence from a barrier into a tractable therapeutic axis, thereby improving the durability and breadth of responses to existing immunotherapies. This integrated translational logic is summarized in Figure 3, which links each mechanistic dimension to its corresponding drug classes—JAK/STAT, STING, and NF-κB modulators for inflammatory hubs; HDAC, DNMT, BET, and KDM4 inhibitors for epigenetic states; and HDAC+PI3K combinations, MCT1 blockade, and hypoxia-targeting agents for metabolic-epigenetic nodes—while positioning senolytics and senomorphics as cross-cutting interventions that simultaneously reduce upstream drivers and remodel downstream TIME outputs (Figure 3). Crucially, the clinical translation layer integrates biomarker-defined senescence-burden and phenotype-based stratification, identification of therapeutic time windows that distinguish early immune-activating TIS from chronic immunosuppressive senescence, and rational combination with ICB, CAR-T, or DC vaccines, with all routes converging on the restoration of TIME immunocompetence and enhanced durability of immunotherapy.
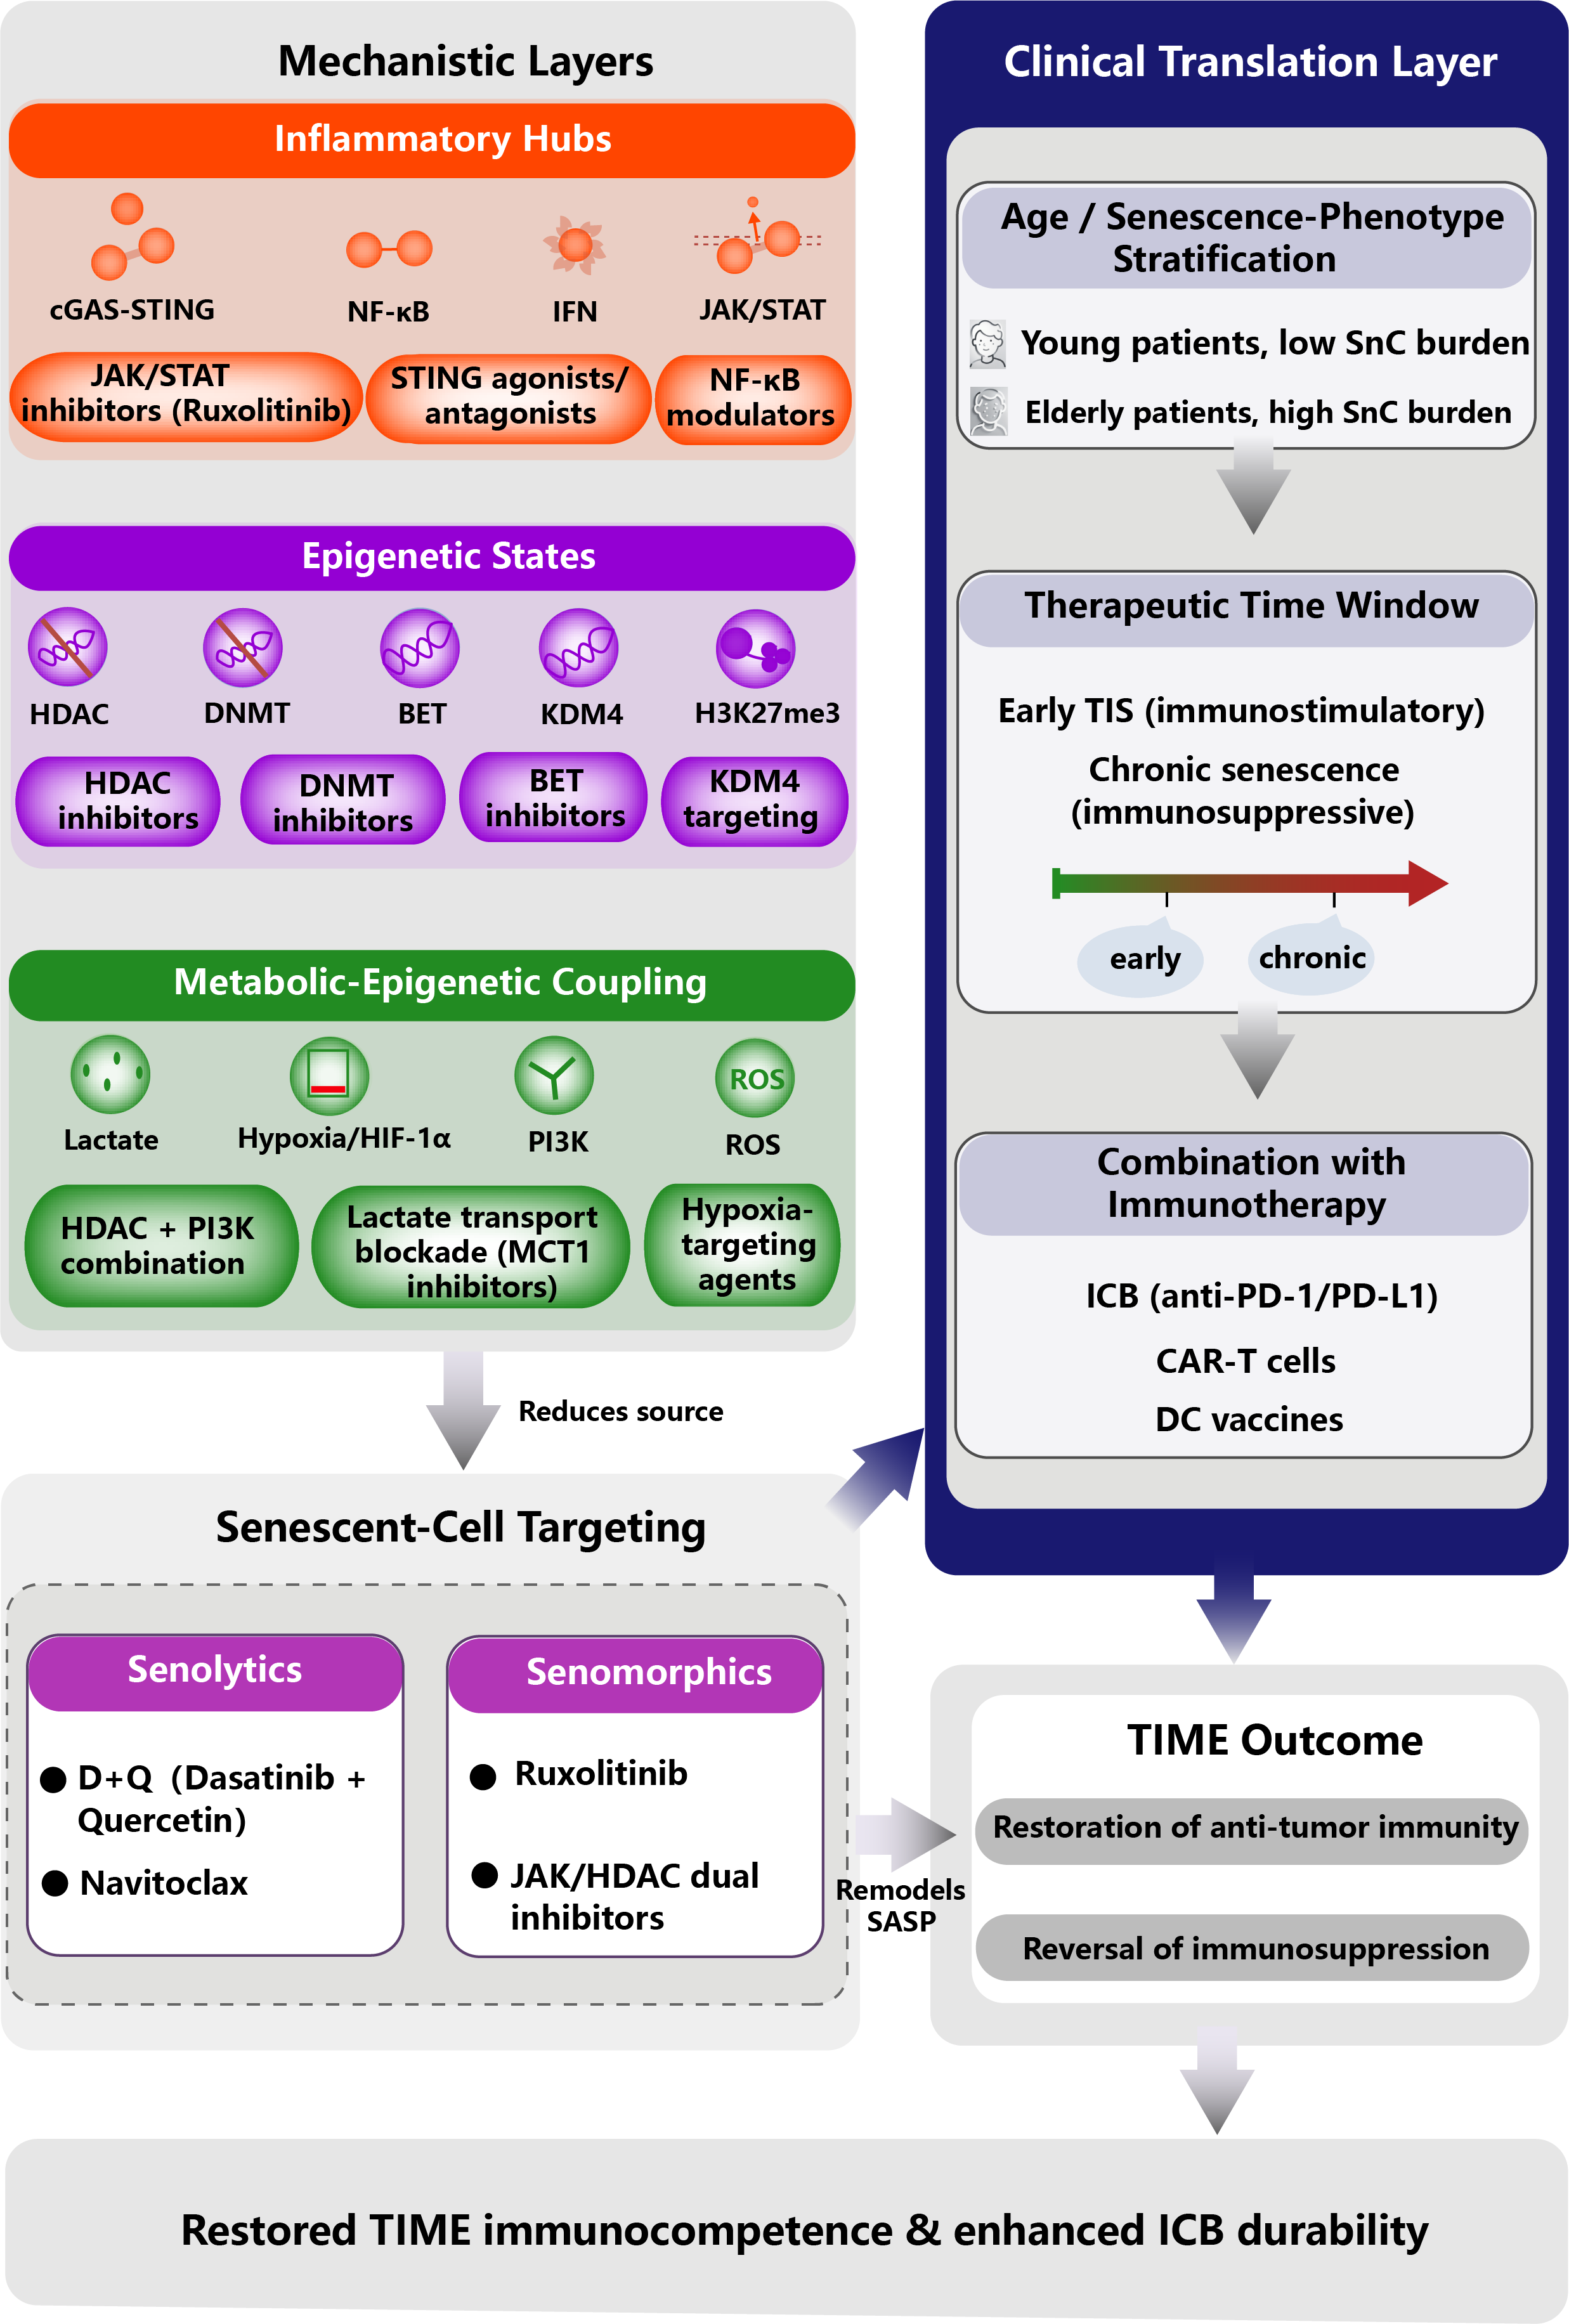
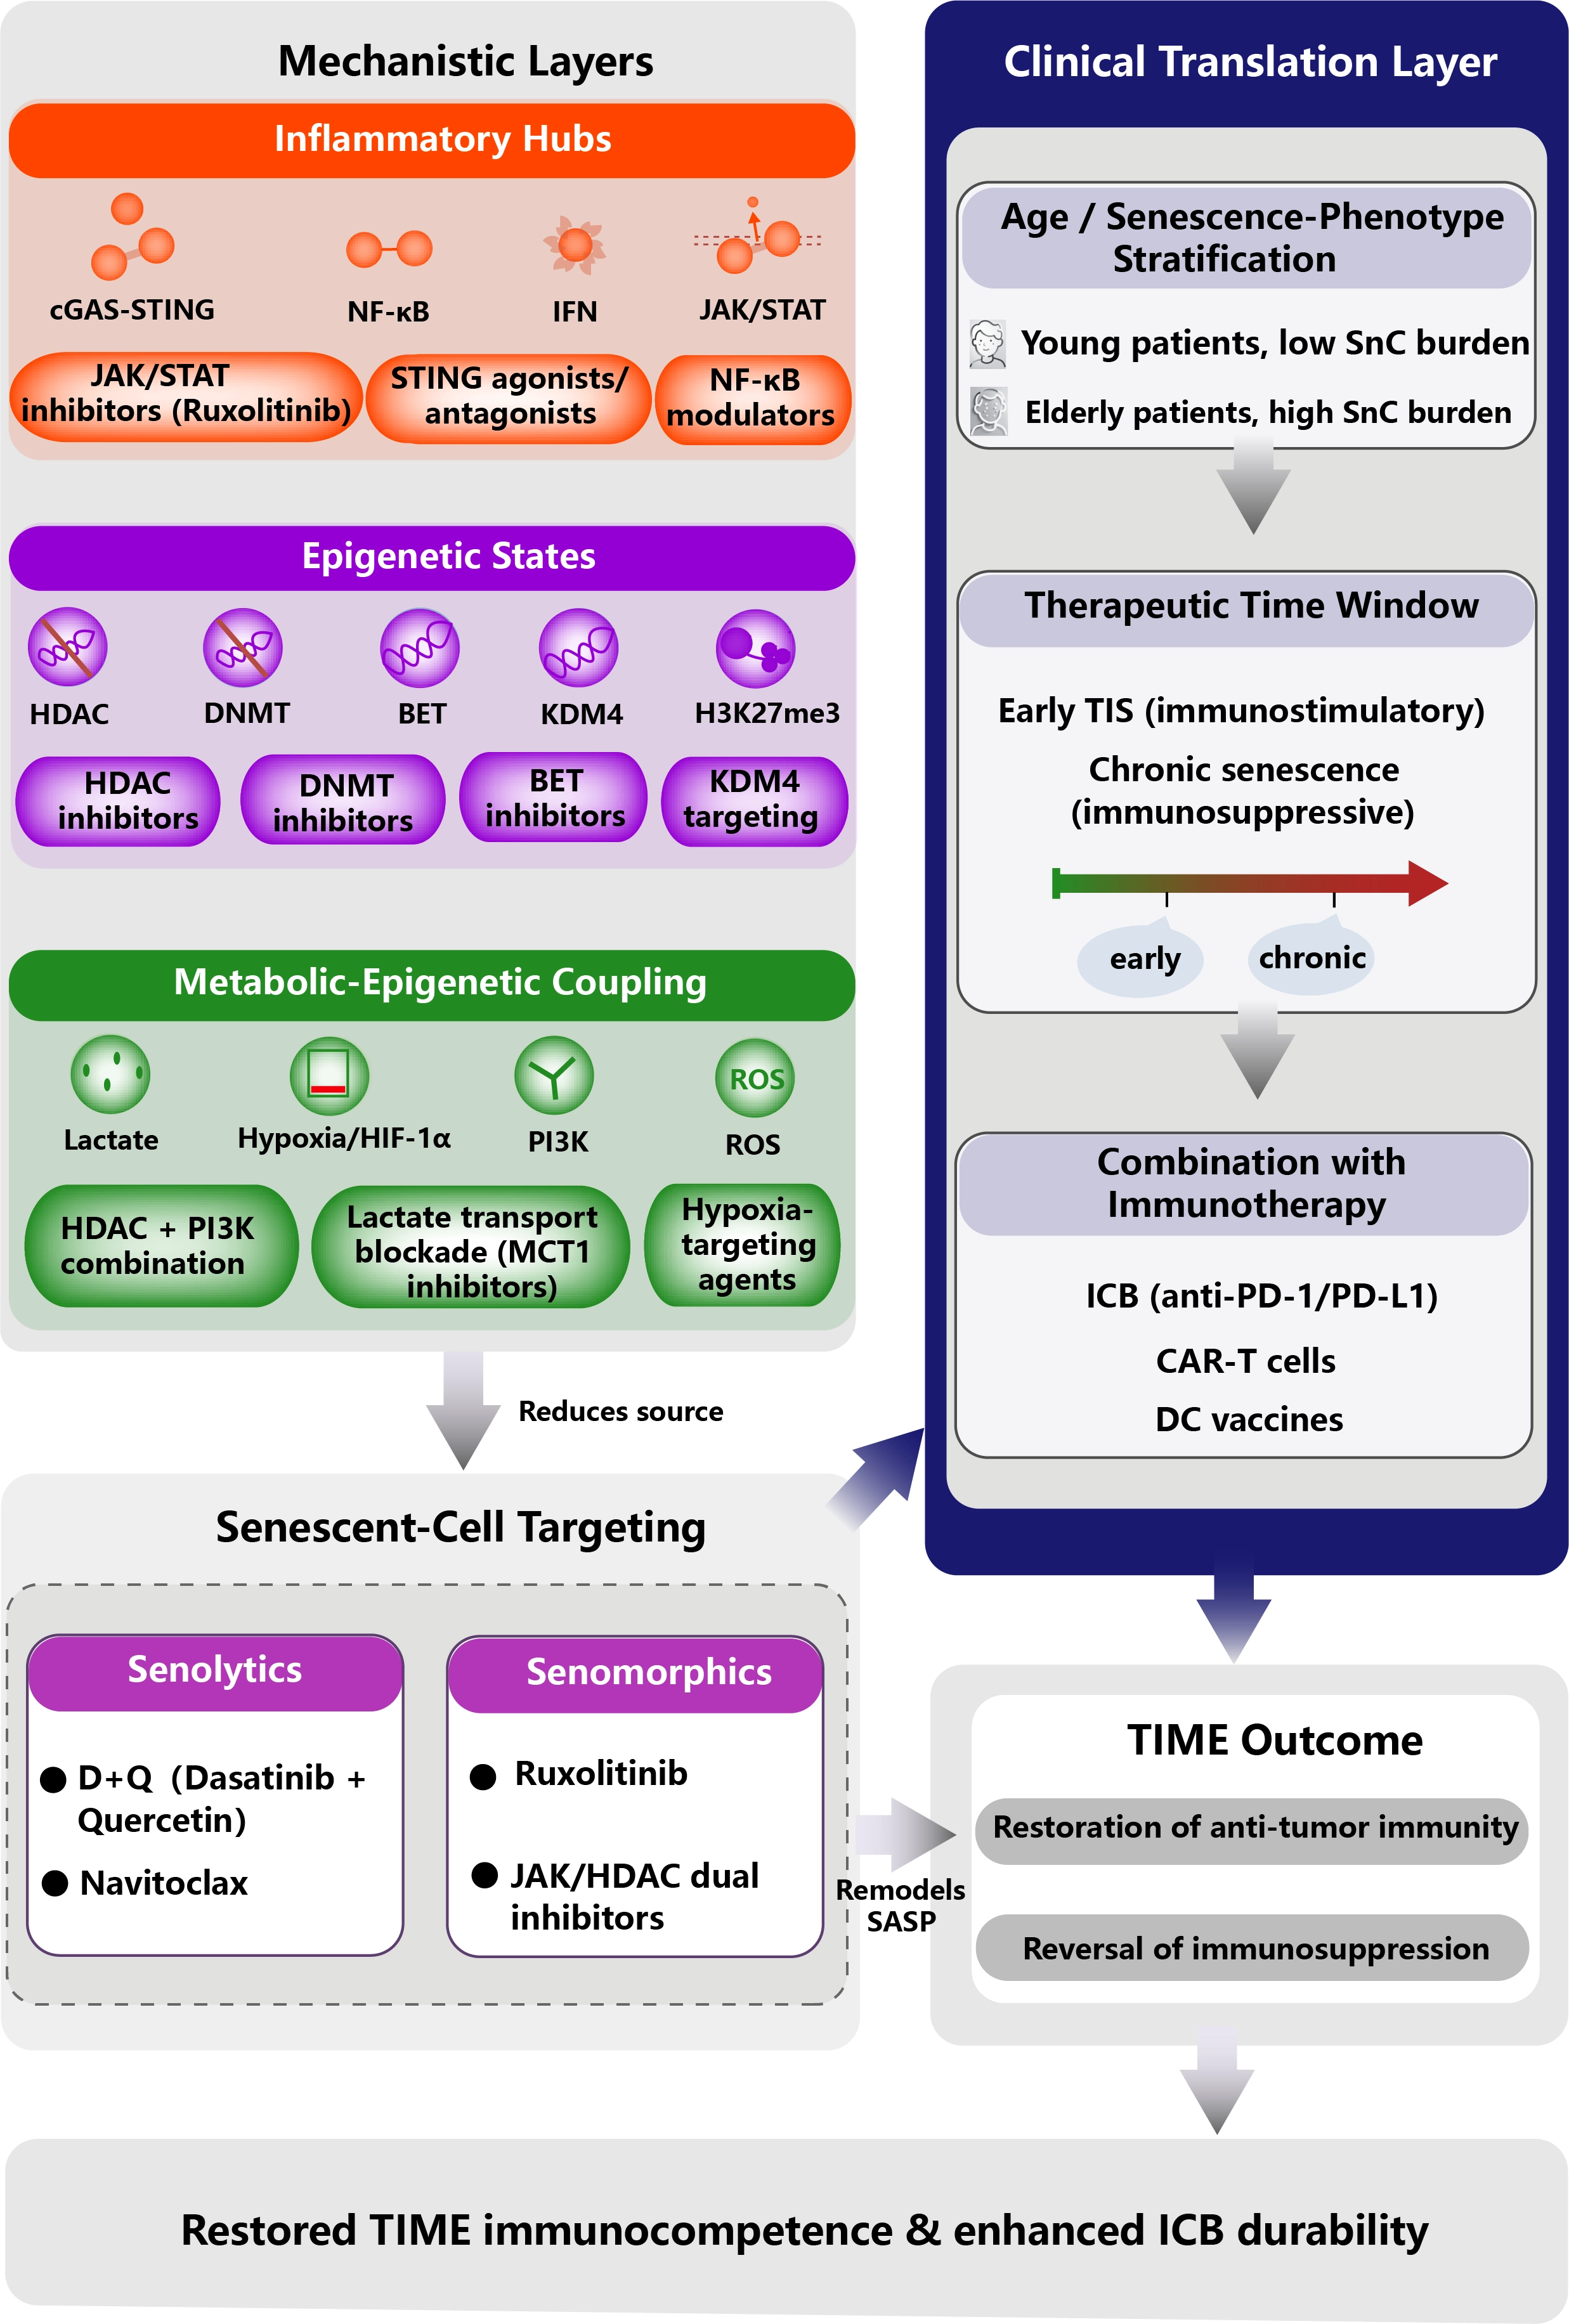
Figure 3. Translational framework linking mechanistic dimensions to therapeutic strategies. The mechanistic layer (left) maps each of the three dimensions to specific drug classes: inflammatory hubs (JAK/STAT inhibitors, STING modulators, NF-κB inhibitors), epigenetic states (HDAC/DNMT/BET/KDM4 inhibitors), and metabolic-epigenetic nodes (HDAC+PI3K combinations, MCT1 blockade, hypoxia-targeting agents). Senescent-cell targeting (bottom-left) acts as a cross-cutting hub: senolytics (D+Q, navitoclax) eliminate senescent cells, while senomorphics (ruxolitinib, JAK/HDAC dual inhibitors) suppress SASP, simultaneously reducing upstream drivers and remodeling TIME outputs. The clinical translation layer (right) integrates three decision modules: biomarker-defined senescence-burden and phenotype-based patient stratification, with chronological age considered separately as a tolerability variable, identification of therapeutic time windows distinguishing early TIS (immune-activating) from chronic senescence (immune-suppressive), and combination with ICB, CAR-T or DC vaccines. All routes converge on restoring TIME immunocompetence and enhancing ICB durability. STING: stimulator of interferon genes; HDAC: histone deacetylase; DNMT: DNA methyltransferase; BET: bromodomain and extraterminal; SASP: senescence-associated secretory phenotype; TIME: tumor immune microenvironment; TIS: therapy-induced senescence; ICB: immune checkpoint blockade; DC: dendritic cell; cGAS: cyclic GMP-AMP synthase; ROS: reactive oxygen species; JAK: Janus kinase; NF-κB: nuclear factor kappa B; IFN: interferon.
6. Conclusion and Future Perspectives
In summary, the intricate crosstalk between senescence-associated transcriptional reprogramming and the TIME constitutes a systemic process of immune editing driven by chronic cellular stress. By integrating endogenous inflammatory hubs, lineage-specific epigenetic lock-in, and metabolic-epigenetic coupling, senescent cells sustain SASP production and stabilize transcriptional programs that progressively convert an initially immunostimulatory, cytotoxic TIME into a highly tolerant, immunosuppressive one. Within this three-layer hierarchy, senescence acts not merely as a static cellular fate, but as a dynamic regulatory axis that continuously reshapes immune composition, spatial architecture, and functional phenotypes of the TIME.
Despite growing mechanistic insight, several critical gaps continue to hinder clinical translation. First, in vivo phenotyping of senescent cells remains insufficiently granular; most current markers capture bulk senescence burden rather than the transcriptional and epigenetic heterogeneity of specific senescent subpopulations across tumor, immune, and stromal compartments. It will be essential to leverage single-cell transcriptomics, spatial multi-omics, and chromatin accessibility profiling to define senescence-associated transcriptional signatures and to map their spatial distribution within the TIME. Second, the spatiotemporal dynamics of the SASP remain poorly defined. The temporal and dose-dependent properties of the SASP, including the concentration thresholds and temporal inflection points at which SASP signaling shifts from immune activation to immune suppression, represent a key mechanistic bottleneck that constrains precise intervention and rational scheduling of senescence-targeted therapies. Importantly, a causal relationship between cellular senescence and any fixed, sequential evolution of the TIME has not yet been established. Testing it will require longitudinal single-cell and spatial profiling of defined tumor models, combined with interventional studies that selectively modulate senescence burden and track the resulting changes in immune contexture over time.
These mechanistic uncertainties directly translate into therapeutic dilemmas. Determining the optimal therapeutic window for senolytics is particularly challenging: premature intervention risks disrupting physiological tissue repair and abrogating the early immunogenic benefits of senescence, whereas delayed intervention may encounter a microenvironment already locked into an epigenetically entrenched immunosuppressive state. Senomorphic strategies, while conceptually attractive, often target broad pathways such as NF-κB or JAK/STAT and therefore carry an inherent risk of systemic off-target effects and immune dysregulation. More critically, there is a paucity of robust biomarkers that accurately reflect the local senescence state and transcriptional configuration of the TIME, rendering biomarker-defined senescence-burden and phenotype-based patient stratification difficult to operationalize in clinical practice.
To overcome these barriers, future efforts will need to combine multidimensional therapeutic strategies with deep technological integration. From a treatment design perspective, temporally optimized regimens that deploy senolytics or senomorphics to transiently relax physical barriers and epigenetic constraints within the TIME, followed by or combined with immune checkpoint blockade or cell therapy, are expected to re-establish durable anti-tumor immune responses, particularly in elderly patients with high senescence burden. From a technological standpoint, AI-assisted integration of multi-omics data, including single-cell, spatial, epigenomic, and metabolomic layers, will enable the construction of computational models that predict microenvironmental evolution, senescence dynamics, and drug response under different intervention scenarios. Such models will accelerate the identification of actionable senescence-associated targets and support the rational design of combination therapies aligned with the three-layer hierarchy of senescence-associated transcriptional reprogramming. Ultimately, a deeper understanding of how senescence-driven transcriptional and epigenetic circuits orchestrate TIME evolution will provide a robust conceptual and translational framework for reversing tumor immune evasion and improving the durability and breadth of responses to existing immunotherapeutic modalities.
Acknowledgements
The authors declare that Claude-Opus-4.8 was used solely for language polishing during the manuscript preparation process. All research content, including the conceptual framework, mechanistic interpretations, selection and verification of references, figures, and tables, is original and was not generated using AI tools. The authors independently developed, verified, and take full responsibility for the integrity, originality, and accuracy of all scientific claims, interpretations, references, figures, and conclusions.
Authors contribution
Yu X: Writing-original draft.
Xing J: Writing-review & editing.
Zhao X, Shan Q: Conceptualization, writing-review & editing.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
None.
Copyright
© The Author(s) 2026.
References
-
3. Liu Y, Feng Y, Cheng L, Xu Y, Wu A, Cheng P. Profiling with senescence-associated secretory phenotype score identifies GDC-0879 as a small molecule sensitizing glioblastoma to anti-PD1. Cell Death Dis. 2025;16:602.[DOI]
-
4. Santos-Sousa DC, da Rosa S, Filippi-Chiela E. Molecular signatures of cellular senescence in cancer: A critical review of prognostic implications and therapeutic opportunities. Mech Ageing Dev. 2025;225:112052.[DOI]
-
7. Jiang SL, Wang D, Zou C, Zhu ZW, Luo C, Wang ZB. Macrophages at the crossroads of cellular senescence and cancer development and progression: Therapeutic opportunities and challenges. Pharmacol Ther. 2025;274:108906.[DOI]
-
12. Zhang J, Guan X, Zhong X. Immunosenescence in digestive system cancers: Mechanisms, research advances, and therapeutic strategies. Semin Cancer Biol. 2024;106-107:234-250.[DOI]
-
13. Ma L, He X, Fu Y, Ge S, Yang Z. Senescent endothelial cells promote liver metastasis of uveal melanoma in single-cell resolution. J Transl Med. 2024;22(1):605.[DOI]
-
14. Gu M, Liu Y, Zheng W, Jing Z, Li X, Guo W, et al. Combined targeting of senescent cells and senescent macrophages: A new idea for integrated treatment of lung cancer. Semin Cancer Biol. 2024;106-107:43-57.[DOI]
-
16. Zhang ZH, Yin JZ, Li W, Xiao H, Wang D, Yang MH. Multiomics analysis reveals that senescent CXCL16+ macrophages promote lung adenocarcinoma progression through TGF-β signalling. J Transl Med. 2026;24(1):306.[DOI]
-
17. Pauken KE, Sammons MA, Odorizzi PM, Manne S, Godec J, Khan O, et al. Epigenetic stability of exhausted T cells limits durability of reinvigoration by PD-1 blockade. Science. 2016;354(6316):1160-1165.[DOI]
-
19. Ruhland MK, Loza AJ, Capietto AH, Luo X, Knolhoff BL, Flanagan KC, et al. Stromal senescence establishes an immunosuppressive microenvironment that drives tumorigenesis. Nat Commun. 2016;7:11762.[DOI]
-
20. Chen DS, Mellman I. Elements of cancer immunity and the cancer-immune set point. Nature. 2017;541(7637):321-330.[DOI]
-
21. Binnewies M, Roberts EW, Kersten K, Chan V, Fearon DF, Merad M, et al. Understanding the tumor immune microenvironment (TIME) for effective therapy. Nat Med. 2018;24(5):541-550.[DOI]
-
22. Joyce JA, Fearon DT. T cell exclusion, immune privilege, and the tumor microenvironment. Science. 2015;348(6230):74-80.[DOI]
-
23. Scott EN, Gocher AM, Workman CJ, Vignali DAA. Regulatory T cells: Barriers of immune infiltration into the tumor microenvironment. Front Immunol. 2021;12:702726.[DOI]
-
24. Kalim KW, Yang JQ, Wunderlich M, Modur V, Nguyen P, Li Y, et al. Targeting of Cdc42 GTPase in regulatory T cells unleashes antitumor T-cell immunity. J Immunother Cancer. 2022;10(11):e004806.[DOI]
-
25. Pramanik A, Bhattacharyya S. Myeloid derived suppressor cells and innate immune system interaction in tumor microenvironment. Life Sci. 2022;305:120755.[DOI]
-
26. Lu J, Luo Y, Rao D, Wang T, Lei Z, Chen X, et al. Myeloid-derived suppressor cells in cancer: Therapeutic targets to overcome tumor immune evasion. Exp Hematol Oncol. 2024;13(1):39.[DOI]
-
27. Yazdimamaghani M, Kolupaev OV, Lim C, Hwang D, Laurie SJ, Perou CM, et al. Tumor microenvironment immunomodulation by nanoformulated TLR 7/8 agonist and PI3k delta inhibitor enhances therapeutic benefits of radiotherapy. Biomaterials. 2025;314:122831.[DOI]
-
28. Kim H, Park HJ, Chang HW, Back JH, Lee SJ, Park YE, et al. Exosome-guided direct reprogramming of tumor-associated macrophages from protumorigenic to antitumorigenic to fight cancer. Bioact Mater. 2023;25:527-540.[DOI]
-
31. Liu J, Bai Y, Li Y, Li X, Luo K. Reprogramming the immunosuppressive tumor microenvironment through nanomedicine: An immunometabolism perspective. eBioMedicine. 2024;107:105301.[DOI]
-
32. Li S, Zhang Y, Tong H, Sun H, Liao H, Li Q, et al. Metabolic regulation of immunity in the tumor microenvironment. Cell Rep. 2025;44(11):116463.[DOI]
-
33. Melese ES, Franks E, Cederberg RA, Harbourne BT, Shi R, Wadsworth BJ, et al. CCL5 production in lung cancer cells leads to an altered immune microenvironment and promotes tumor development. OncoImmunology. 2022;11(1):2010905.[DOI]
-
35. Xu M, Zhang T, Xia R, Wei Y, Wei X. Targeting the tumor stroma for cancer therapy. Mol Cancer. 2022;21(1):208.[DOI]
-
36. Kumari S, Advani D, Sharma S, Ambasta RK, Kumar P. Combinatorial therapy in tumor microenvironment: Where do we stand? Biochim Biophys Acta Rev Cancer. 2021;1876(2):188585.[DOI]
-
37. Xun Z, Ding X, Zhang Y, Zhang B, Lai S, Zou D, et al. Reconstruction of the tumor spatial microenvironment along the malignant-boundary-nonmalignant axis. Nat Commun. 2023;14:933.[DOI]
-
38. Bräutigam K, Skok K, Szymonski K, Rift CV, Karamitopoulou E. Tumor immune microenvironment in pancreatic ductal adenocarcinoma revisited-Exploring the “Space”. Cancer Lett. 2025;622:217699.[DOI]
-
39. Hou D, Wan H, Katz JL, Wang S, Castro BA, Vazquez-Cervantes GI, et al. Antigen-presenting B cells promote TCF-1+ PD1- stem-like CD8+ T-cell proliferation in glioblastoma. Front Immunol. 2024;14:1295218.[DOI]
-
40. Zhu CY, Zhai TT, Su M, Pan HC, Tang Q, Huang BH, et al. EZH2 elicits CD8+ T-cell desert in esophageal squamous cell carcinoma via suppressing CXCL9 and dendritic cells. Commun Biol. 2024;7:1645.[DOI]
-
41. Koti M, Bivalacqua T, Black PC, Cathomen T, Galsky MD, Gulley JL, et al. Adaptive immunity in genitourinary cancers. Eur Urol Oncol. 2023;6(3):263-272.[DOI]
-
42. Zhou H, Zheng Z, Fan C, Zhou Z. Mechanisms and strategies of immunosenescence effects on non-small cell lung cancer (NSCLC) treatment: A comprehensive analysis and future directions. Semin Cancer Biol. 2025;109:44-66.[DOI]
-
44. Chen ACY, Jaiswal S, Martinez D, Yerinde C, Ji K, Miranda V, et al. The aged tumor microenvironment limits T cell control of cancer. Nat Immunol. 2024;25(6):1033-1045.[DOI]
-
46. Chibaya L, Snyder J, Ruscetti M. Senescence and the tumor-immune landscape: Implications for cancer immunotherapy. Semin Cancer Biol. 2022;86:827-845.[DOI]
-
48. Wang N, Fang Y, Hou Y, Cheng D, Dressler EV, Wang H, et al. Senescent cells promote breast cancer cells motility by secreting GM-CSF and bFGF that activate the JNK signaling pathway. Cell Commun Signal. 2024;22(1):478.[DOI]
-
50. Chen Y, Yang L. Cellular senescence in renal ischemia-reperfusion injury. Chin Med J. 2025;138(15):1794-1806.[DOI]
-
53. Hwang HJ, Kang D, Shin J, Jung J, Ko S, Jung KH, et al. Therapy-induced senescent cancer cells contribute to cancer progression by promoting ribophorin 1-dependent PD-L1 upregulation. Nat Commun. 2025;16:353.[DOI]
-
54. Xu C, Xia Y, Zhang BW, Drokow EK, Li HY, Xu S, et al. Macrophages facilitate tumor cell PD-L1 expression via an IL-1β-centered loop to attenuate immune checkpoint blockade. MedComm. 2023;4(2):e242.[DOI]
-
55. Ma X, Jin S, Zhang X, Zhao L, Wang H, Liu S, et al. Targeting the NAT10-HDAC4 positive feedback loop counteracts immunosuppression in breast cancer. J Exp Clin Cancer Res. 2026;45:35.[DOI]
-
57. Alipour-Khezri E, Moqadami A, Zununi Vahed S, Barzegari A. Cytosolic DNA sensing pathway in senescence and aging: Underlying mechanisms and targeted interventions. Biomed Pharmacother. 2025;193:118790.[DOI]
-
58. Cancado de Faria R, Silva LND, Teodoro-Castro B, McCommis KS, Shashkova EV, Gonzalo S. A noncanonical cGAS-STING pathway drives cellular and organismal aging. Proc Natl Acad Sci USA. 2025;122(28):e2424666122.[DOI]
-
59. Kumar V, Bauer C, Stewart JH. Targeting cGAS/STING signaling-mediated myeloid immune cell dysfunction in TIME. J Biomed Sci. 2023;30(1):48.[DOI]
-
60. Zhang BC, Pedersen A, Reinert LS, Li Y, Narita R, Idorn M, et al. STING signals to NF-κB from late endolysosomal compartments using IRF3 as an adaptor. Nat Immunol. 2025;26(11):1916-1930.[DOI]
-
62. Vasiyani H, Wadhwa B, Singh R. Regulation of cGAS-STING signalling in cancer: Approach for combination therapy. Biochim Biophys Acta Rev Cancer. 2023;1878(3):188896.[DOI]
-
64. Xu G, Su J, Hong Y, Zhang E, Zheng Z, Li J, et al. Bu-Fei decoction ameliorates naïve CD4+ T cell senescence and attenuates age-related COPD by regulating the C1qbp-cGAS-STING signaling pathway. Phytomedicine. 2025;149:157513.[DOI]
-
65. Hou Y, Wei Y, Lautrup S, Yang B, Wang Y, Cordonnier S, et al. NAD+ supplementation reduces neuroinflammation and cell senescence in a transgenic mouse model of Alzheimer’s disease via cGAS-STING. Proc Natl Acad Sci USA. 2021;118(37):e2011226118.[DOI]
-
66. Tong Z, Zou JP, Wang SY, Luo WW, Wang YY. Activation of the cGAS-STING-IRF3 axis by type I and II interferons contributes to host defense. Adv Sci. 2024;11(35):2308890.[DOI]
-
69. Chen LY, Pang XY, Chen C, Xu HG. NF-κB regulates the expression of STING via alternative promoter usage. Life Sci. 2023;314:121336.[DOI]
-
70. Schmitz CRR, Grun LK, Makiyama BK, Piazza LS, Padoin AV, Mottin CC, et al. cGAS-STING signaling is blunted in senescent macrophages and monocytes in obesity. Mech Ageing Dev. 2026;229:112140.[DOI]
-
71. Zhao M, Wang T, Gleber-Netto FO, Chen Z, McGrail DJ, Gomez JA, et al. Mutant p53 gains oncogenic functions through a chromosomal instability-induced cytosolic DNA response. Nat Commun. 2024;15:180.[DOI]
-
72. Lv QM, Lei HM, Wang SY, Zhang KR, Tang YB, Shen Y, et al. Cancer cell-autonomous cGAS-STING response confers drug resistance. Cell Chem Biol. 2023;30(6):591-605.e4.[DOI]
-
75. Fan Z, Jia M, Zhou J, Zhu Z, Wu Y, Lin X, et al. Pharmacological targeting cGAS/STING/NF-κB axis by tryptanthrin induces microglia polarization toward M2 phenotype and promotes functional recovery in a mouse model of spinal cord injury. Neural Regen Res. 2025;20(11):3287-3301.
-
76. Colegio OR, Chu NQ, Szabo AL, Chu T, Rhebergen AM, Jairam V, et al. Functional polarization of tumour-associated macrophages by tumour-derived lactic acid. Nature. 2014;513(7519):559-563.[DOI]
-
80. Pan X, Wang J, Zhang L, Li G, Huang B. Metabolic plasticity of T cell fate decision. Chin Med J. 2024;137(7):762-775.[DOI]
-
81. Yi FS, Qiao X, Dong SF, Chen QY, Wei RQ, Shao MM, et al. Complement C1q is a key player in tumor-associated macrophage-mediated CD8+ T cell and NK cell dysfunction in malignant pleural effusion. Int J Biol Sci. 2024;20(15):5979-5998.[DOI]
-
84. Liu X, Li H, Yuan M, Wan J, Guo J, Dong X, et al. The epigenetic landscape of tumor-associated macrophages: Orchestrating immune evasion in the tumor microenvironment. Cancer Lett. 2025;632:217972.[DOI]
-
85. Suthen S, Lim CJ, Nguyen PHD, Dutertre CA, Lai HLH, Wasser M, et al. Hypoxia-driven immunosuppression by Treg and type-2 conventional dendritic cells in HCC. Hepatology. 2022;76(5):1329-1344.[DOI]
-
87. Ghosh S, Dutta R, Goswami D, Ghatak D, De R. Mitochondrial dynamics and metabolic attributes regulate function of natural killer cell and infiltration in tumor microenvironment modulating disease progression. Biochim Biophys Acta Rev Cancer. 2025;1880(6):189471.[DOI]
-
89. Yuan CS, Teng Z, Yang S, He Z, Meng LY, Chen XG, et al. Reshaping hypoxia and silencing CD73 via biomimetic gelatin nanotherapeutics to boost immunotherapy. J Control Release. 2022;351:255-271.[DOI]
-
90. Li QR, Zhang X, Zhang C, Zhang Y, Niu MT, Chen Z, et al. Biomineralized engineered bacterial outer membrane vesicles as cGAS-STING nanoagonists synergize with lactate metabolism modulation to potentiate immunotherapy. J Am Chem Soc. 2025;147(28):24555-24572.[DOI]
-
91. Huang Y, Mao J, Li Z, Wang W, Ni Z, Cai F, et al. Signal converter-based therapy platform promoting ageing bone healing by improving permeability of the mitochondrial membrane. Adv Mater. 2025;37(27):2500156.[DOI]
-
94. Zhang D, Tang Z, Huang H, Zhou G, Cui C, Weng Y, et al. Metabolic regulation of gene expression by histone lactylation. Nature. 2019;574(7779):575-580.[DOI]
-
96. Liu N, Wu J, Deng E, Zhong J, Wei B, Cai T, et al. Immunotherapy and senolytics in head and neck squamous cell carcinoma: Phase 2 trial results. Nat Med. 2025;31(9):3047-3061.[DOI]
-
97. Zhao K, Yan Y, Dong BT, Pan SS, Zhang XZ. Senescence reprogramming unleashes tumor immune surveillance via coordinated gene modulation. Adv Mater. 2026;38(8):e16597.[DOI]
-
99. Feng T, Xie F, Lee LMY, Lin Z, Tu Y, Lyu Y, et al. Cellular senescence in cancer: From mechanism paradoxes to precision therapeutics. Mol Cancer. 2025;24(1):213.[DOI]
-
100. Zhu Y, Tchkonia T, Fuhrmann-Stroissnigg H, Dai HM, Ling YY, Stout MB, et al. Identification of a novel senolytic agent, navitoclax, targeting the Bcl-2 family of anti-apoptotic factors. Aging Cell. 2016;15(3):428-435.[DOI]
-
101. Baar MP, Brandt RMC, Putavet DA, Klein JDD, Derks KWJ, Bourgeois BRM, et al. Targeted apoptosis of senescent cells restores tissue homeostasis in response to chemotoxicity and aging. Cell. 2017;169(1):132-147.e16.[DOI]
-
102. Haston S, Gonzalez-Gualda E, Morsli S, Ge J, Reen V, Calderwood A, et al. Clearance of senescent macrophages ameliorates tumorigenesis in KRAS-driven lung cancer. Cancer Cell. 2023;41(7):1242-1260.e6.[DOI]
-
106. Xiong J, Dong L, Lv Q, Yin Y, Zhao J, Ke Y, et al. Targeting senescence-associated secretory phenotypes to remodel the tumour microenvironment and modulate tumour outcomes. Clin Transl Med. 2024;14(9):e1772.[DOI]
-
107. Xu M, Tchkonia T, Ding H, Ogrodnik M, Lubbers ER, Pirtskhalava T, et al. JAK inhibition alleviates the cellular senescence-associated secretory phenotype and frailty in old age. Proc Natl Acad Sci USA. 2015;112(46):E6301-E6310.[DOI]
-
109. Hogg SJ, Vervoort SJ, Deswal S, Ott CJ, Li J, Cluse LA, et al. BET-bromodomain inhibitors engage the host immune system and regulate expression of the immune checkpoint ligand PD-L1. Cell Rep. 2017;18(9):2162-2174.[DOI]
-
111. Zheng H, Zhao W, Yan C, Watson CC, Massengill M, Xie M, et al. HDAC inhibitors enhance T-cell chemokine expression and augment response to PD-1 immunotherapy in lung adenocarcinoma. Clin Cancer Res. 2016;22(16):4119-4132.[DOI]
-
112. Hu W, Shen J, Zhou C, Tai Z, Zhu Q, Chen Z, et al. Discovery of Janus kinase and histone deacetylase dual inhibitors as a new strategy to treat psoriasis. J Med Chem. 2024;67(21):19267-19281.[DOI]
-
113. Brand A, Singer K, Koehl GE, Kolitzus M, Schoenhammer G, Thiel A, et al. LDHA-associated lactic acid production blunts tumor immunosurveillance by T and NK cells. Cell Metab. 2016;24(5):657-671.[DOI]
-
114. Ma S, Zhao Y, Lee WC, Ong LT, Lee PL, Jiang Z, et al. Hypoxia induces HIF1α-dependent epigenetic vulnerability in triple negative breast cancer to confer immune effector dysfunction and resistance to anti-PD-1 immunotherapy. Nat Commun. 2022;13:4118.[DOI]
-
115. Wellen KE, Hatzivassiliou G, Sachdeva UM, Bui TV, Cross JR, Thompson CB. ATP-citrate lyase links cellular metabolism to histone acetylation. Science. 2009;324(5930):1076-1080.[DOI]
-
117. Benci JL, Xu B, Qiu Y, Wu TJ, Dada H, Twyman-Saint Victor C, et al. Tumor interferon signaling regulates a multigenic resistance program to immune checkpoint blockade. Cell. 2016;167(6):1540-1554.e12.[DOI]
-
118. Harrington KJ, Champiat S, Brody JD, Cho BC, Romano E, Golan T, et al. Phase I and II clinical studies of the STING agonist ulevostinag with and without pembrolizumab in participants with advanced or metastatic solid tumors or lymphomas. Clin Cancer Res. 2025;31(16):3400-3411.[DOI]
-
120. Siddiqui I, Schaeuble K, Chennupati V, Fuertes Marraco SAF, Calderon-Copete S, Pais Ferreira D, et al. Intratumoral Tcf1+PD-1+CD8+ T cells with stem-like properties promote tumor control in response to vaccination and checkpoint blockade immunotherapy. Immunity. 2019;50(1):195-211.e10.
-
121. Zhu Y, Tchkonia T, Pirtskhalava T, Gower AC, Ding H, Giorgadze N, et al. The Achilles’ heel of senescent cells: From transcriptome to senolytic drugs. Aging Cell. 2015;14(4):644-658.[DOI]
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Yu X, Xing J, Zhao X, Shan Q. Senescence-associated transcriptional reprogramming in the tumor immune microenvironment: Mechanistic layers and therapeutic opportunities. Ageing Cancer Res Treat. 2027;4:202626. https://doi.org/10.70401/acrt.2026.0040
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Composition, Spatial Organization, and Phenotypic Polarization of the TIME
- 3. Senescence-Driven Immune Consequences in the TIME
- 4. Mechanistic Layers of Senescence-Associated Transcriptional Reprogramming
- 5. Mechanism-Guided Therapeutic Opportunities to Reverse Senescence-Associated Immunosuppression
- 6. Conclusion and Future Perspectives
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Yu X, Xing J, Zhao X, Shan Q. Senescence-associated transcriptional reprogramming in the tumor immune microenvironment: Mechanistic layers and therapeutic opportunities. Ageing Cancer Res Treat. 2027;4:202626. https://doi.org/10.70401/acrt.2026.0040
copy
Share Link
copy