Advancements in carbon dots for targeted treatment of pancreatic cancer

Hao Zhou
Yifan Zhang
Yang Xi
*

*Correspondence to:
Yang Xi, Ningbo Key Laboratory of Malignant Tumor Immunodiagnosis and Immunotherapy, School of Basic Medical Sciences, Health Science Center, Ningbo University, Ningbo 315211, Zhejiang, China.
E-mail: xiyang@nbu.edu.cn
Ageing Cancer Res Treat. 2027;4:202611. 10.70401/acrt.2026.0043
Received: March 19, 2026Accepted: September 21, 2026Published: September 21, 2026
Abstract
Pancreatic cancer is a highly aggressive and lethal malignancy with an exceptionally poor prognosis. Its clinical management is severely hampered by insidious early symptoms, strong invasiveness, intrinsic chemoresistance, and limited efficacy of conventional therapies. Carbon dots (CDs) have shown great promise in precision cancer theranostics owing to their excellent optical properties, high biocompatibility, controlled drug loading and release capabilities and customizable targeting features. This review critically examines the major therapeutic barriers in pancreatic cancer management, systematically summarizes the applications of CDs in pancreatic cancer imaging, targeted drug delivery, hyperthermia and pH-responsive theranostics, analyzes the current limitations of CD-based nanosystems, and discusses future development directions. This work aims to provide a rigorous theoretical foundation for the rational design and development of novel CD-mediated precision intervention strategies for pancreatic cancer.
Keywords
Pancreatic cancer, carbon dots, targeted drug delivery, fluorescence imaging
1. Introduction
1.1 The clinical Burden of pancreatic cancer
Pancreatic cancer is one of the most aggressive malignant tumors worldwide, with pancreatic ductal adenocarcinoma (PDAC) accounting for over 90% of all pancreatic malignancies. In 2022, pancreatic cancer was the sixth most common cause of cancer-related mortality globally, with 510,556 new cases and 467,005 deaths. Over the next decade, it is predicted to become the second leading cause of cancer-related death in high-income countries[1,2]. The disease is characterized by insidious early symptoms, a highly invasive nature, and marked therapeutic resistance, which together lead to an extremely poor prognosis. At diagnosis, only 15%-20% of patients are candidates for radical surgical resection, and the postoperative recurrence rate remains extremely high[3]. Conventional treatment modalities, including surgery, chemotherapy, and radiotherapy, fail to achieve satisfactory outcomes, resulting in a persistently low 5-year survival rate[4]. The growing disease burden and unmet clinical needs necessitate the development of innovative treatment strategies for pancreatic cancer.
1.2 Tumor microenvironment of pancreatic cancer
The tumor microenvironment (TME) of PDAC is a complex heterogeneous system composed of both cellular and non-cellular elements. Features such as fibrosis, hypoxia, and acidity that chiefly distinguish PDAC from other solid tumors, are also major drivers of drug resistance. Compared with other solid tumors, components in the TME of pancreatic cancer account for approximately 80% of the overall tumor volume. This compartment includes immune cells, the dense extracellular matrix (ECM), cancer-associated fibroblasts (CAFs), and other constituents[5].
As the hallmark feature of TME in PDAC, fibrosis is driven primarily by CAFs. ECM components such as type I and type III collagen and hyaluronic acid (HA) secreted by CAFs are abnormally deposited to form dense stroma. Dense fibrosis not only constitutes a physical barrier, hindering the infiltration of drugs and immune cells, but also promotes epithelial-mesenchymal transition and invasion of tumor cells through integrin-mediated signaling pathways, while increasing interstitial fluid pressure and destroying vascular perfusion[6]. CAFs and tumor cells form a reciprocal regulatory loop through paracrine signaling loops that continuously maintains the fibrosis homeostasis[5]. The hypoxic microenvironment results from poor vascularization combined with dense fibrosis. PDAC exhibits low microvessel density, and the dense stroma impairs functional angiogenesis, leading to insufficient oxygen supply and stable expression of hypoxia-inducible factor 1α (HIF-1α)[7,8]. HIF1α activates downstream target genes, drives metabolic reprogramming of tumor cells to adapt to the hypoxic environment, induces epithelial-mesenchymal transition, enhances metastatic potential, and aggravates immunosuppression. Activation of autophagy in pancreatic stellate cells also provides metabolic support for tumor cells under hypoxic environment[9].
The acidic microenvironment of pancreatic cancer is largely attributable to the abnormal glycolysis metabolism of tumor cells, known as the Warburg effect[10]. Tumor and stromal cells continuously produce metabolites such as lactic acid under hypoxia, and the dysfunctional vascular system fails to clear them efficiently, ultimately lowering the pH of the tumor stroma to 6.2-6.5. This pH is significantly lower than that of normal pancreatic tissue (pH ≈ 7.4) and blood pH (7.35-7.45) and exhibits obvious regional heterogeneity. Because of insufficient oxygen supply, metabolic activity in the tumor core is more intense, and acidity is correspondingly higher than at the tumor periphery. This acidic gradient aggravates TME dysfunction and therapeutic resistance[5]. The acidic microenvironment not only inhibits immune cell function and promotes tumor invasion, but also reduces the stability and cellular uptake of chemotherapeutic drugs, thereby aggravating treatment resistance[11].
1.3 Available treatment options and limitations
Current treatment modalities for pancreatic cancer include surgery, radiotherapy and chemotherapy. Many patients develop recurrence after surgery, even with radical resection; outcomes remain disappointing, with a median survival of 15-20 months and a 5-year survival rate of only 8-15%[12]. Consequently, the overall cure rate remains low. Radiotherapy is widely used as a neoadjuvant method to shrink or delay pancreatic tumor growth before surgery. However, pancreatic cancer cells surviving at the treatment site after radiotherapy may trigger signaling mechanisms for tumor cell proliferation and metastasis. Accumulating evidence indicates that radiotherapy is closely associated with tumor recurrence at the irradiated site and at distant sites[13]. As for chemotherapy, modified FOLFIRINOX (mFOLFIRINOX, containing 5-fluorouracil, leucovorin, oxaliplatin, and irinotecan) and the combination of NAB-paclitaxel with gemcitabine have shown only modest survival benefits and considerable toxicity[14]. In addition, several novel targeted therapies (such as cetuximab, bevacizumab, axitinib and aflibercept) failed to effectively improve overall survival (OS), whereas the combination of erlotinib and gemcitabine demonstrated only marginal clinical benefit[15].
Gemcitabine, a first-line single-agent chemotherapy drug in PDAC, relies on the nucleoside transporter (hENT1) to enter the cancer cells. However, expression of hENT1 in PDAC is generally reduced, and the low vascular density of TME further reduces drug delivery, exacerbating drug resistance[4,5,16]. Although paclitaxel inhibits cancer cell division by stabilizing microtubules, its hydrophobicity results in poor solubility, and matrix metalloproteinases secreted by CAFs in the PDAC TME accelerate its degradation. Moreover, side effects such as neurotoxicity limit its clinical application[5,17]. Even combination chemotherapy regimens such as FOLFIRINOX achieve only modest improvements in efficacy; their limited TME penetration and markedly increased toxicity make them suitable only for patients with a good performance status[4]. These limitations indicate that conventional chemotherapy is difficult to use to overcome the three major challenges of TME penetration, targeted delivery, and efficacy monitoring, highlighting the urgent need for novel theranostic strategies that provide TME responsiveness, precise targeting, and real-time imaging.
2. Physicochemical Properties and Diagnostic Potential of Carbon Dots
Carbon dots (CDs) are zero-dimensional carbon-based nanomaterials, generally classified into three categories: graphene quantum dots (GQDs), carbon quantum dots (CQDs), and carbonized polymer dots (CPDs). CQDs are spherical nanoparticles that contain small amounts of stacked carbon frameworks with sp2 and sp3 hybridization and exhibit weak crystallinity, and are primarily used in biomedical applications. In this article, CDs refer primarily to CQDs. GQDs consist of single- or multi-layer graphene sheets with well-defined lattice structures and conjugated π domains, and are commonly used in the fabrication of sensors and photodetectors. CPDs possess a hybrid structure where organic polymer chains are cross-linked with a carbon core, and are widely applied in catalysis, energy storage, and optoelectronic conversion[18]. CDs typically have a particle size of less than 10 nm, excellent water solubility, high biocompatibility, low toxicity, and easy functionalization[19-21]. Their optical properties are tunable: in addition to tunable fluorescence emission, CDs exhibit special optical phenomena such as aggregation-induced luminescence and room-temperature phosphorescence. The near-infrared band light absorption and conversion ability can also be achieved through structural design[22,23]. A wide range of carbon precursors can be selected, and a variety of functional groups or doped heteroatoms can be introduced into the surface to lay the foundation for functional modification[24].
The above properties are not unique to CDs. Liposomes, polymer nanoparticles, and gold nanoparticles also possess these features. However, when applied to pancreatic cancer, CDs offer some practical advantages over these conventional vectors. Firstly, their size of less than 10 nm facilitates diffusion through a dense matrix barrier, which larger particles, typically 50-300 nm, generally cannot pass. Second, the intrinsic fluorescence of CDs makes the imaging label-free, thus avoiding the exogenous fluorophores required for most other nanocrystals. Third, the small volume facilitates renal clearance compared to the predominantly reticuloendothelial uptake of liposomes and polymers, thereby potentially reducing long-term tissue retention[25-27]. Compared with traditional semiconductor quantum dots (QDs), CDs can be synthesized from cheap precursors on a large scale, at a low cost and in an environmentally friendly manner, which is expected to overcome the problems of high cost, potential toxicity and environmental pollution of traditional QDs[28].
The physical and chemical properties of CDs give them excellent potential for the diagnosis and therapy of pancreatic cancer. The optical properties can directly support tumor fluorescence imaging, photoacoustic and other imaging requirements. The surface can be readily functionalized with targeting ligands to achieve active targeting of pancreatic cancer. Some CDs have high efficiency photothermal or photodynamic conversion capabilities, which can mediate tumor hyperthermia. Their surface physicochemical properties can respond to the acidic microenvironment of pancreatic cancer, enabling pH-sensitive drug release or fluorescence activation. In addition, CDs can load chemotherapeutic drugs through electrostatic and hydrophobic interactions, facilitating the construction of integrated targeted delivery systems for diagnosis and treatment[29].
3. Application of Carbon Dots in Pancreatic Cancer Imaging
3.1 Unimodal fluorescence imaging
CDs have attracted extensive attention in the field of tumor fluorescence imaging due to their excellent fluorescence stability, favorable biocompatibility, and tunable emission wavelengths[30]. Compared with conventional imaging probes, CDs exhibit clear advantages and inherent limitations. Traditional organic fluorescent dyes suffer from severe photobleaching and short circulation times. While heavy-metal-based QDs exhibit high quantum yields but pose potential long-term toxicity risks[22]. CDs, however, strike a balance between biocompatibility and optical stability, making them more suitable for long-term in vivo tracking.
For deep-seated pancreatic cancers, the commonly used blue- and green-emitting CDs are severely limited by tissue scattering and autofluorescence, resulting in shallow imaging depth and poor signal-to-noise ratio (SNR). In recent years, heteroatom doping, conjugated structure extension, and surface state regulation, have enabled the construction of red emission and near-infrared radiation (NIR) emission CDs. NIR light (650-1,700 nm) is an ideal light source for deep tissue imaging due to its deeper tissue penetration, lower scattering, and weaker autofluorescence compared with visible light[31]. For example, the NIR-emitting CDs reported by Ge et al. have been used for in vivo tumor imaging and showed a good SNR with favorable biocompatibility[32]. By modulating the conjugation structure, surface functional groups, and heteroatom doping ratio of CDs, the effective red shift of emission wavelengths to the red and NIR regions has been realized. Other studies have indicated that the degree of π-conjugation can be enhanced by introducing nitrogen, sulfur, or aromatic precursors, resulting in CDs with emission wavelengths in the range of 650-800 nm. This spectral range is recognized as the optical window of biological tissues, where hemoglobin and water exhibit low absorption, thus remarkably improving tissue penetration depth and imaging contrast[33,34].
With respect to pancreatic cancer specificity, Varghese et al. synthesized red-emitting CDs with an emission peak of 676 nm using 1,4,5,8-tetraaminoxantrone as the precursor, and achieved tumor-specific fluorescence imaging in a BALB/c pancreatic cancer model after targeted modification with erlotinib[35]. By covalently coupling the clinical NIR dye indocyanine green (ICG) to CDs, Cillari et al. obtained the NIR-I-emitting CDs-ICG-PEG probe and achieved time-dependent tumor accumulation and NIR-I fluorescence imaging in a PDAC xenograft mouse model[36]. The fluorescent CDs constructed by Shang et al. exhibited blue, green, and red fluorescence in an orthotopic pancreatic cancer model. Blue-green light was used to identify the tumor margin, and red light was used to reveal the depth of tumor invasion. This approach compensates for the insufficient imaging depth of blue-green light and enables accurate fluorescence navigation surgical resection[37]. These studies indicate that red- and NIR-emitting CDs have significant potential to improve deep-tissue imaging of pancreatic cancer. They overcome some limitations of blue-green CDs in deep tumor imaging, but their quantum yields are generally lower, and the fluorescence stability is easily disturbed by the complex pancreatic cancer TME. PEGylation or surface charge optimization can further prolong the blood circulation time of CDs and reduce clearance by the reticuloendothelial system (RES)[38,39]. Unimodal fluorescent CDs are ideal for preoperative tumor localization and intraoperative fluorescence navigation, but insufficient penetration depth restricts their application in large animals and clinical pancreatic cancer imaging (Figure 1A).
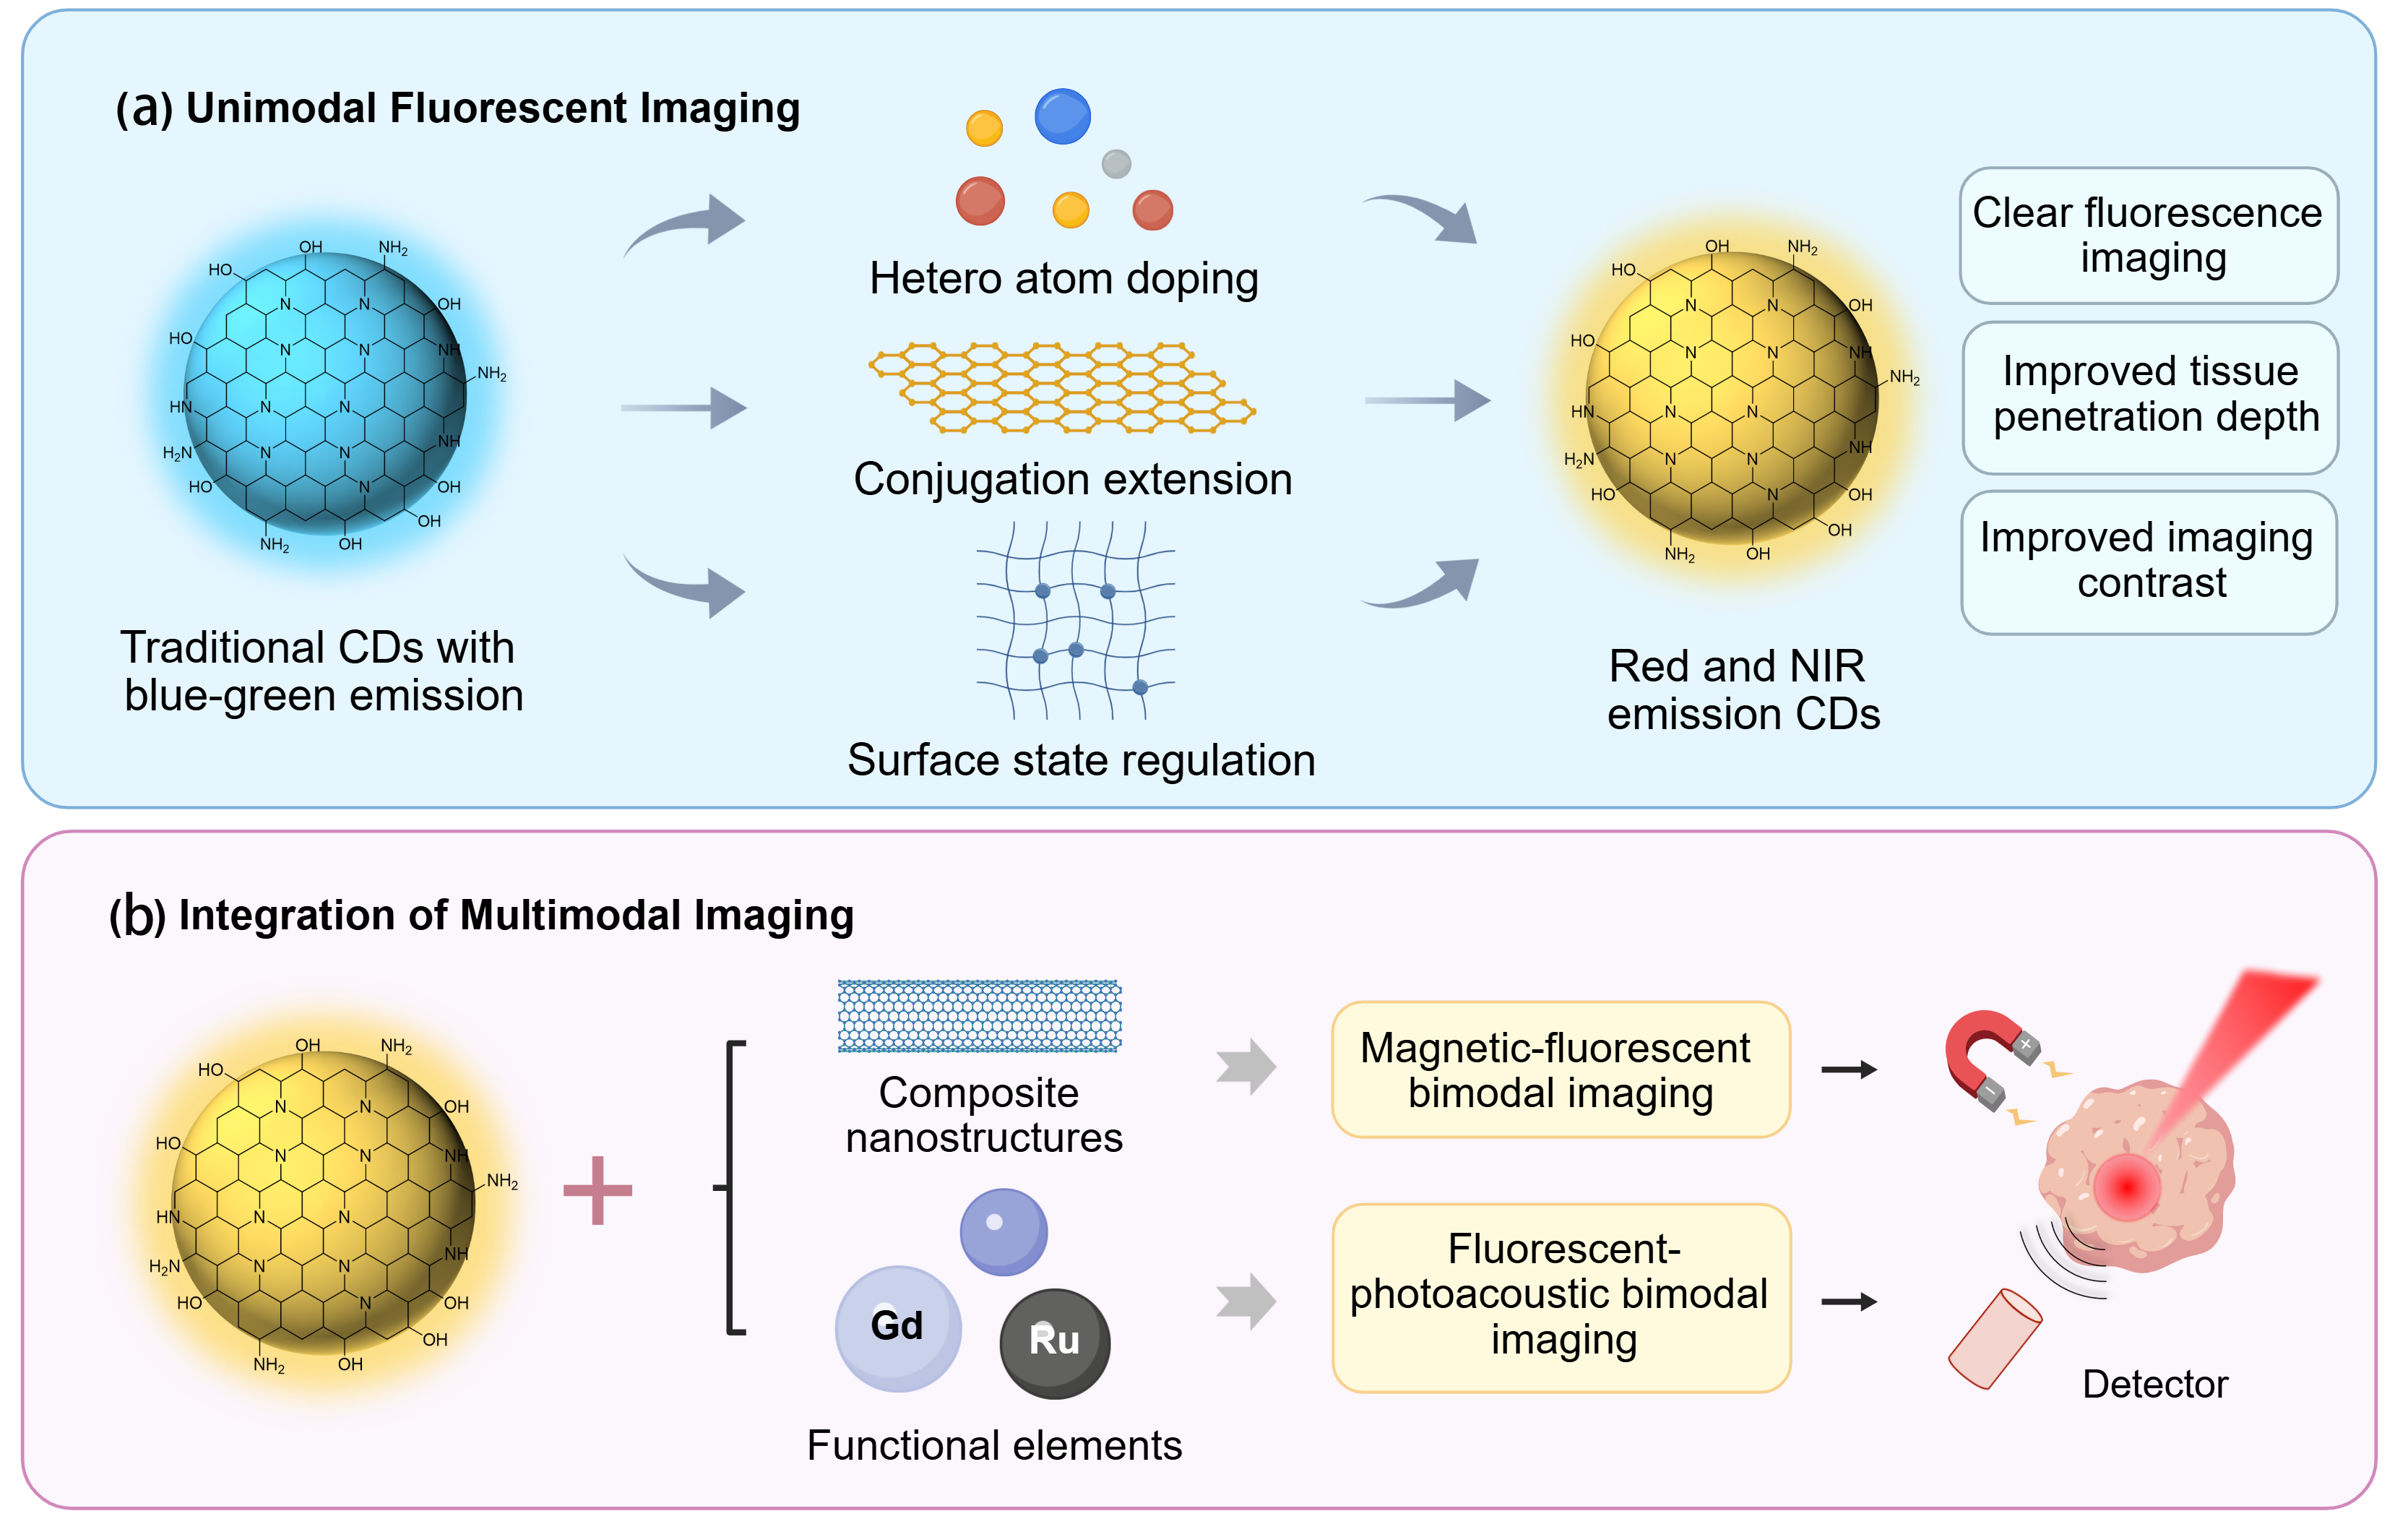
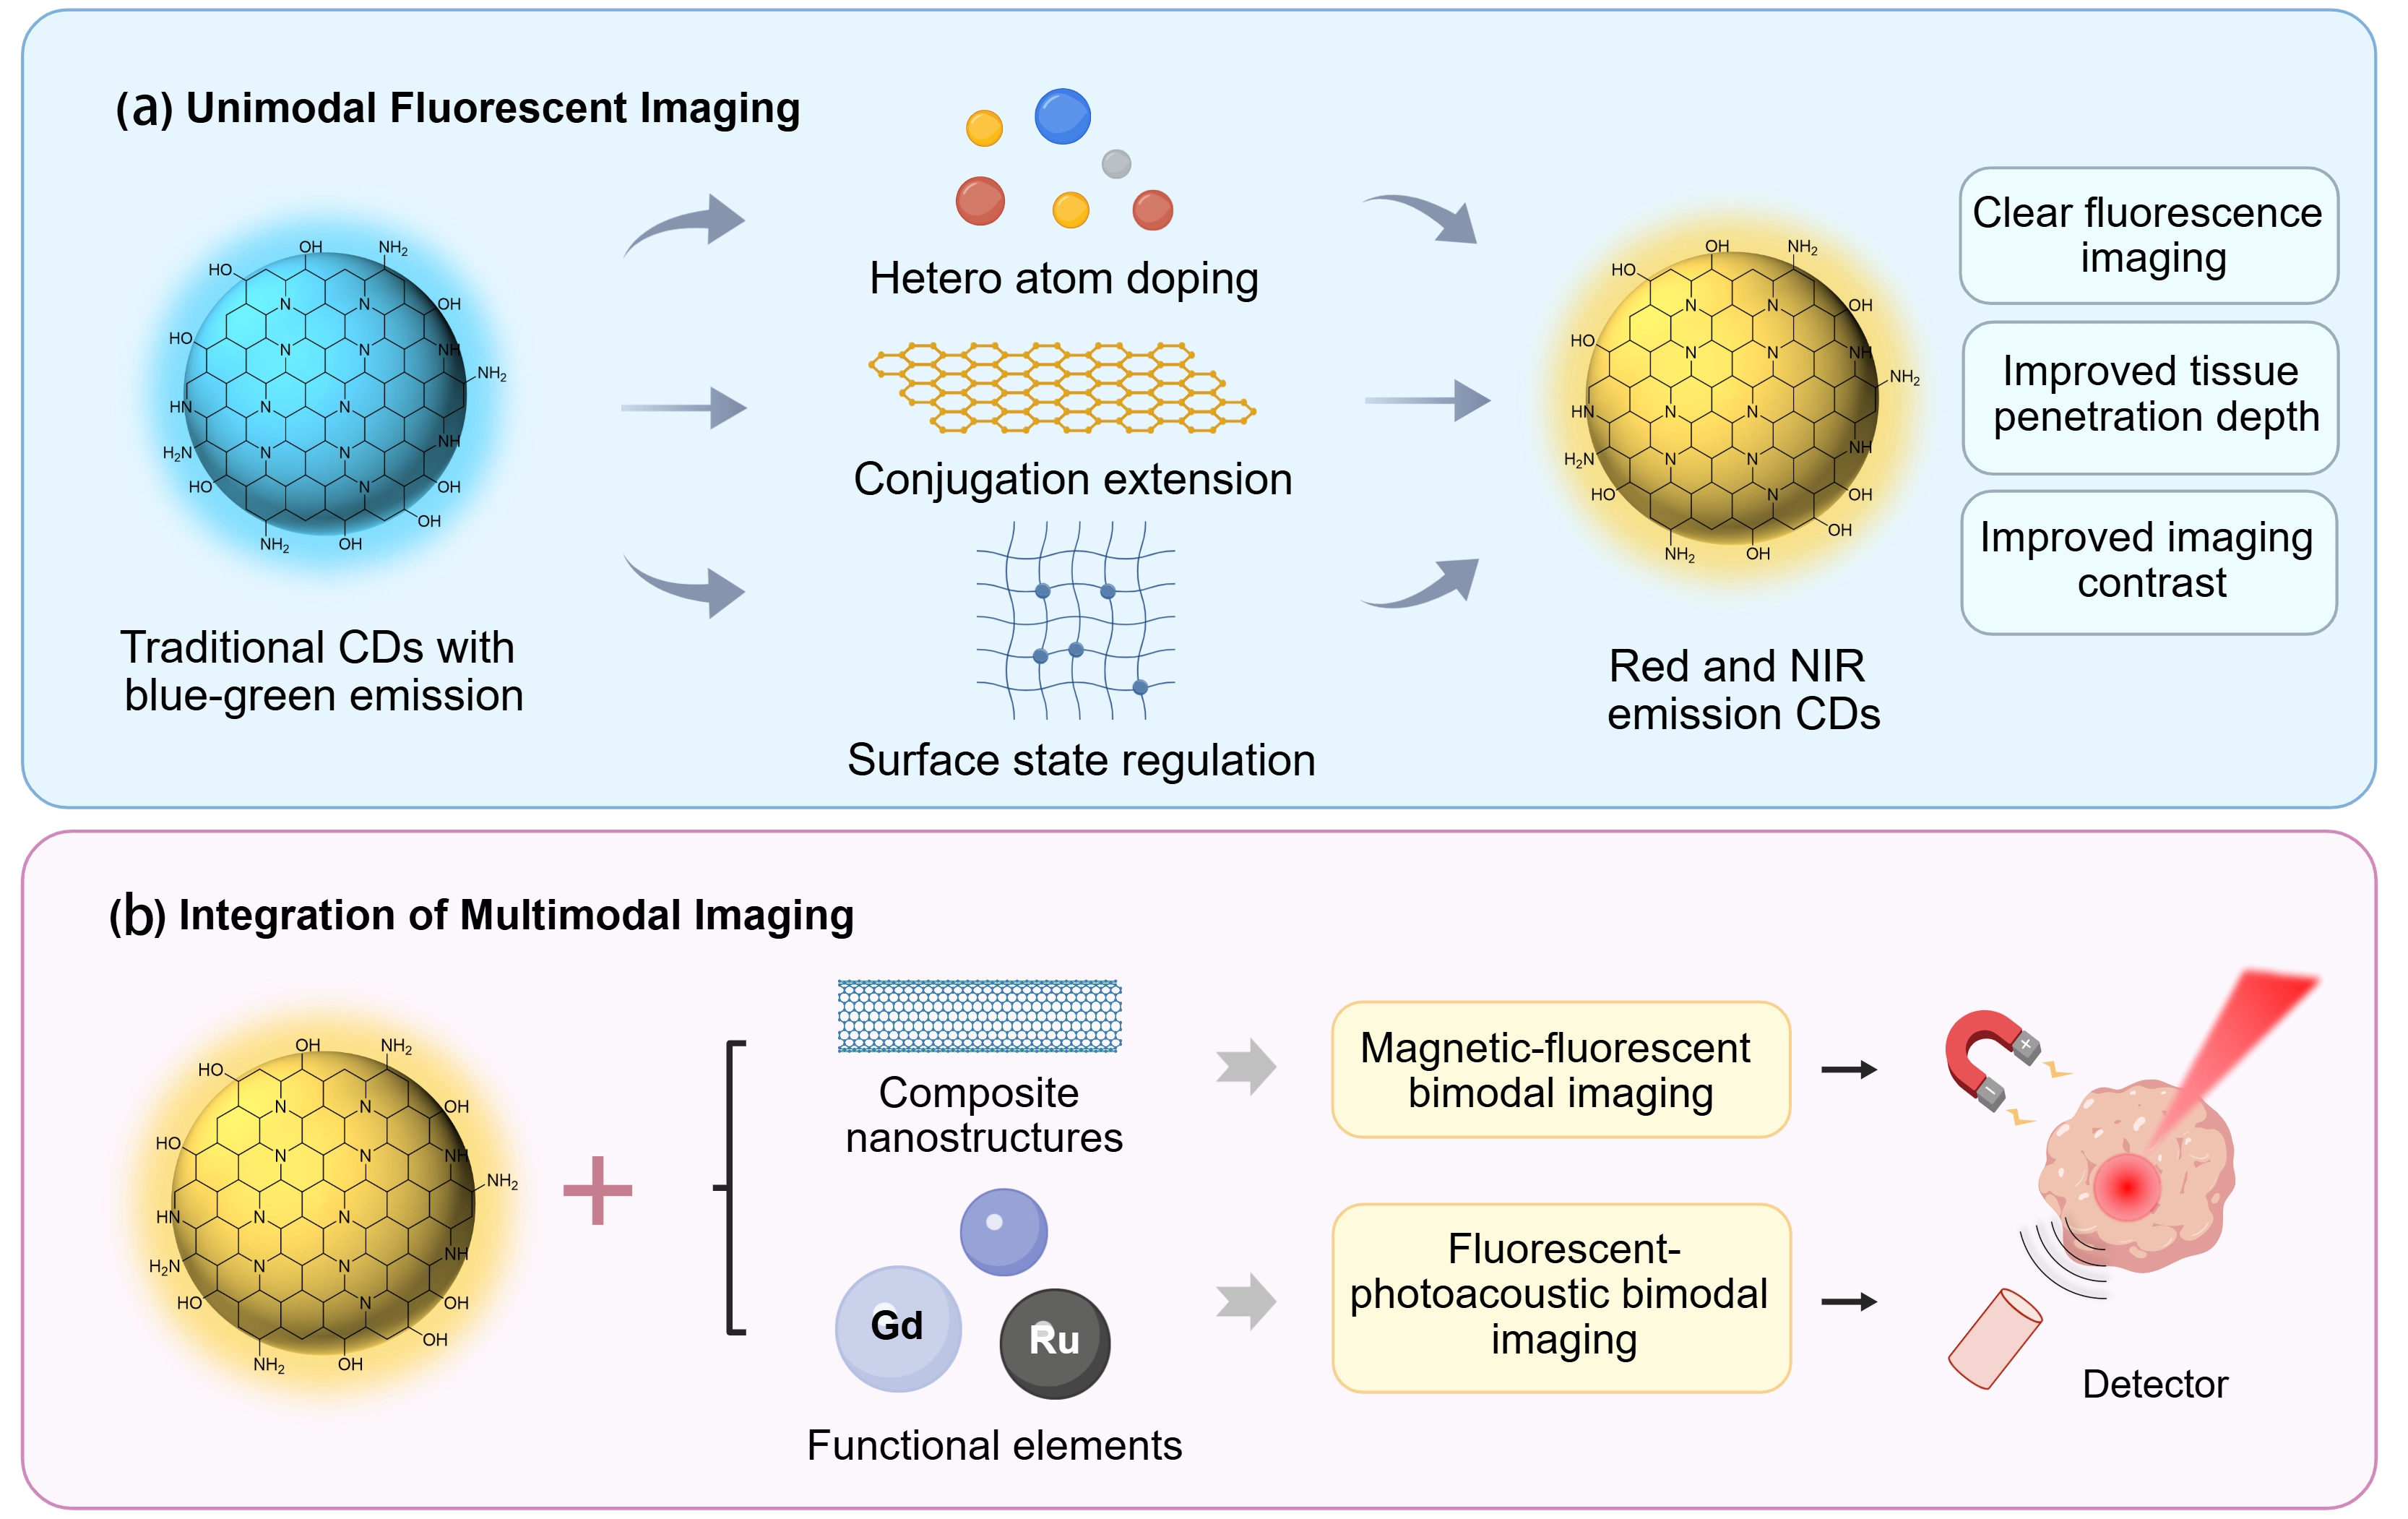
Figure 1. Application strategies of CDs for pancreatic cancer imaging: (a) Unimodal fluorescence imaging strategy. Through three key modification methods, including heteroatom doping, conjugated structure expansion, and surface state regulation, conventional blue-green emitting CDs are transformed into red/NIR-emitting CDs. This conversion enables robust fluorescence imaging, deeper tissue penetration, and improved imaging contrast, which is critical for visualizing deep-seated pancreatic tumors; (b) Multimodal imaging strategy: By constructing composite nanostructures or introducing functional elements, red/NIR-emitting CDs can be further engineered to generate two representative dual-mode imaging platforms: magnetic-fluorescence dual-mode imaging and fluorescence and laser-induced plasmonic dual-mode imaging. CDs: carbon dots; NIR: near-infrared radiation.
3.2 Integration of multimodal imaging
Despite the advantages of high sensitivity and real-time visualization, fluorescence imaging remains limited by insufficient penetration depth[40]. To overcome this drawback, multimodal imaging has emerged as a crucial research direction in the field of CDs in recent years.
By constructing composite nanostructures or introducing functional elements into CDs, fluorescence imaging can be integrated with techniques such as magnetic resonance imaging (MRI) and photoacoustic imaging (PAI), thereby enabling the synergistic acquisition of structural and molecular information[41]. For instance, doping paramagnetic ions such as Gd and Ru into the CD system can endow them with excellent MRI contrast enhancement, while preserving and optimizing their fluorescence properties, thus enabling dual-mode magnetic-optical imaging[42]. Such magnetic-fluorescent bimodal probes can achieve deep structural localization via MRI in vivo and cellular and molecular level visualization through fluorescence, thereby improving the localization accuracy of orthotopic pancreatic tumors. Compared with single contrast agents, multimodal platforms can reduce misdiagnosis and enhance diagnostic accuracy[43-45].
In addition, PAI relies on thermoacoustic signals generated after light absorption and offers a penetration depth of up to the centimeter scale[46]. By enhancing the NIR absorption capacity of CDs to endow them with both fluorescence emission and high photothermal conversion efficiency, fluorescence-photoacoustic bimodal imaging can be realized. Ultra-small CDs and high-purity, nucleus-targeted CDs with strong NIR absorption have been demonstrated to be useful for precise tumor localization via dual-mode fluorescence and photoacoustic imaging[47,48]. However, most of the above studies have been conducted using subcutaneous models, such as breast cancer xenografts, and the effect of dual-mode imaging in the orthotopic model of pancreatic cancer remains to be verified. Nevertheless, as an imaging modality, the principle of fluorescence-photoacoustic dual-mode imaging is generally applicable. CDs used for PAI usually have efficient NIR light absorption and photothermal conversion properties. Upon NIR irradiation, tissues enriched with CDs are heated, and the thermoelastic expansion of biomolecules generates sound waves that can be detected by PAI.
Multimodal integration offers potential advantages for the early detection and therapeutic evaluation of deep pancreatic tumors. It not only expands the dimensionality of imaging but also provides technical support for real-time monitoring during subsequent treatment processes, rendering CDs a promising candidate material for diagnostic and therapeutic platforms (Figure 1B).
4. Carbon Dot-Mediated Targeted Drug Delivery Systems for Pancreatic Cancer
4.1 Active targeting strategies
Pancreatic cancer is characterized by high invasiveness and a complex TME, with its cell surface expressing a variety of receptor molecules that can serve as targets, such as epidermal growth factor receptor (EGFR), integrin alpha-ν beta-3 (ανβ3), CD44, and carbohydrate antigen CA19-9[49-51]. Based on these molecular characteristics, constructing specific recognition units on the surface of CDs is an important strategy to enhance tumor accumulation capacity. Common active targeting strategies include antibody conjugation, peptide modification, and small-molecule ligand conjugation[52-54].
Antibody conjugation leverages the high affinity between antibodies and antigens to achieve highly specific targeted recognition. The abundant carboxyl or amino groups on the surface of CDs can form stable covalent bonds with antibodies through 1-ethyl-3-(3-dimethylaminopropyl)carbodiimide (EDC)/N-hydroxy-succinimide (NHS)-mediated amide condensation reactions. However, the application of this strategy in active targeting therapy for pancreatic cancer remains very limited. Existing studies are mostly focused on in vitro biosensing and immunoassay applications. For example, Alarfaj et al. conjugated CA19-9 monoclonal antibodies to CQDs/Au nanocomposites via EDC/NHS chemistry, establishing a fluorescence immunosensing method for the detection of the pancreatic cancer biomarker CA19-9. This method achieved sensitive detection of CA19-9 antigen over a linear range of 0.01-350 U/mL, with a detection limit as low as 0.007 U/mL, but this system was designed for diagnostic immunoassay rather than targeted drug delivery or therapy[55]. Direct studies using CDs as carriers for antibody conjugation via EDC/NHS for active targeted delivery in pancreatic cancer remain scarce. The large molecular size of antibodies (approximately 150 kDa) may compromise the ability of CDs to penetrate the dense fibrotic stroma of pancreatic cancer. Their Fc region may elicit immunogenic responses. Besides, large-scale production is costly. Therefore, antibody-modified CDs are currently more suitable for preclinical mechanistic validation and in vitro diagnostic scenarios, while their direct application in active targeted therapy for pancreatic cancer remains to be systematically established. Future research should achieve breakthroughs in conjugation chemistry precision, antibody miniaturization, and validation of in vivo targeting efficiency, in order to advance this strategy from detection towards therapeutic applications.
Peptide modification has recently attracted considerable attention in the field of active targeting for pancreatic cancer. Peptides possess small molecular weights (typically 1-5 kDa), low immunogenicity, and strong tissue penetration capabilities, making them more likely than antibodies to penetrate the dense tumor stroma of pancreatic cancer. Regarding conjugation strategies, in addition to the EDC/NHS method, maleimide-thiol coupling reactions can be employed for the oriented modification of thiol-containing peptides to optimize the spatial orientation and exposure efficiency of the functional groups. However, peptides exhibit poor metabolic stability in vivo and are susceptible to enzymatic degradation. Certain peptides, such as arginine-glycine-aspartic acid (RGD), are not pancreatic cancer-specific targets, as integrins are also expressed in normal tissues, potentially leading to non-specific uptake. Nevertheless, compared with antibody conjugation, peptide modification achieves a better balance between targeting specificity and tissue penetration, and therefore holds greater translational potential.
Compared with antibodies and peptides, small-molecule ligand conjugation offers several advantages, including facile synthesis, high chemical stability, and low cost, and represents the most widely reported strategy for CD targeting modification in the published literature. However, its binding affinity is generally weaker than that of antibodies and peptides, and targeting selectivity is relatively limited. Folic acid (FA) is one of the most extensively applied small-molecule targeting ligands, with folate receptors being overexpressed on the surface of pancreatic cancer and various other tumors. Pandey et al. utilized FA-conjugated cage-like CD nanostructures in a genetically induced pancreatic cancer model, validating their in vivo pharmacokinetics and tissue distribution[56]. HA, as another important small-molecule ligand, can specifically recognize CD44 receptors that are highly expressed on the surface of various tumor cells, including pancreatic cancer cells[57]. Recently, Varghese et al. covalently conjugated the EGFR-targeting ligand erlotinib to red-fluorescent CDs, achieving tumor-targeted fluorescence imaging in a BALB/c pancreatic cancer xenograft mouse model, thereby providing new insights into targeted drug delivery[35]. Nevertheless, folate receptors, CD44, EGFR, and other targets are also expressed in certain normal tissues, which may compromise targeting selectivity. Current studies have primarily focused on validating the difference in targeted CD uptake between cancer cells and normal pancreatic tissues, but have rarely assessed non-specific accumulation in other normal organs. Moreover, the binding affinity of small-molecule ligands is typically one to two orders of magnitude lower than that of antibodies, which may limit their targeting efficacy when receptor expression levels are low. At present, systematic validation of small-molecule ligand-modified CDs in pancreatic cancer remains insufficient, and this strategy may be more suitable for early-stage screening and proof-of-concept studies of CD-based carriers (Table 1).
Table 1. Comparison of active targeting modification strategies for carbon dots in pancreatic cancer.
| Representative ligands | Target receptors | Advantages | Limitations | Pancreatic cancer-related studies | Ref. | |
| Antibody conjugation | Anti-EGFR antibody, anti-CA19-9 antibody | EGFR, CA19-9 | High affinity and strong specificity | Large size (~150 kDa), high immunogenicity, and high production cost | Very limited: most remain at the mechanistic stage | [55] |
| Peptide modification | RGD, iRGD, GE11 | Integrin ανβ3, EGFR | Small size, low immunogenicity, and good tissue penetration | Poor metabolic stability, susceptibility to proteolysis, and non-specific binding for certain ligands | Very limited: RGD-modified carbon dots have been reported for photothermal therapy in general tumor models | [58,59] |
| Small-molecule ligand conjugation | Folic acid, hyaluronic acid, erlotinib | FRα, CD44, EGFR | Simple synthesis, low cost, and high chemical stability | Weak binding affinity (1-2 orders of magnitude lower than antibodies), and limited selectivity | Folic acid, hyaluronic acid, and erlotinib have all been investigated in pancreatic cancer models | [35,56,57,60] |
ανβ3: integrin alpha-ν beta-3; CA19-9: carbohydrate antigen 19-9; CD44: cluster of differentiation 44; EGFR: epidermal growth factor receptor; FRα, folate receptor alpha; GE11: a specific EGFR-targeting peptide; iRGD: internalizing arginine-glycine-aspartic acid; kDa: kilodalton; RGD: arginine-glycine-aspartic acid.
In summary, each of the three active targeting strategies has distinct applications. Antibody conjugation is suitable for mechanistic validation. Peptide modification achieves a favorable balance between targeting specificity and tissue penetration, making it the most promising candidate for clinical translation. Small-molecule ligands, owing to their simplicity and low cost, are well suited for early-stage screening. Overall, CD-mediated targeted drug delivery for pancreatic cancer remains at the exploratory stage. Future research should draw on the design principles of clinically advanced nanomedicines, incorporate the molecular expression profiles of specific pancreatic cancer subtypes, optimize the conjugation strategies for attaching targeting ligands to CDs, and facilitate systematic in vivo evaluation of actively targeted CD formulations in orthotopic pancreatic cancer models (Figure 2A).
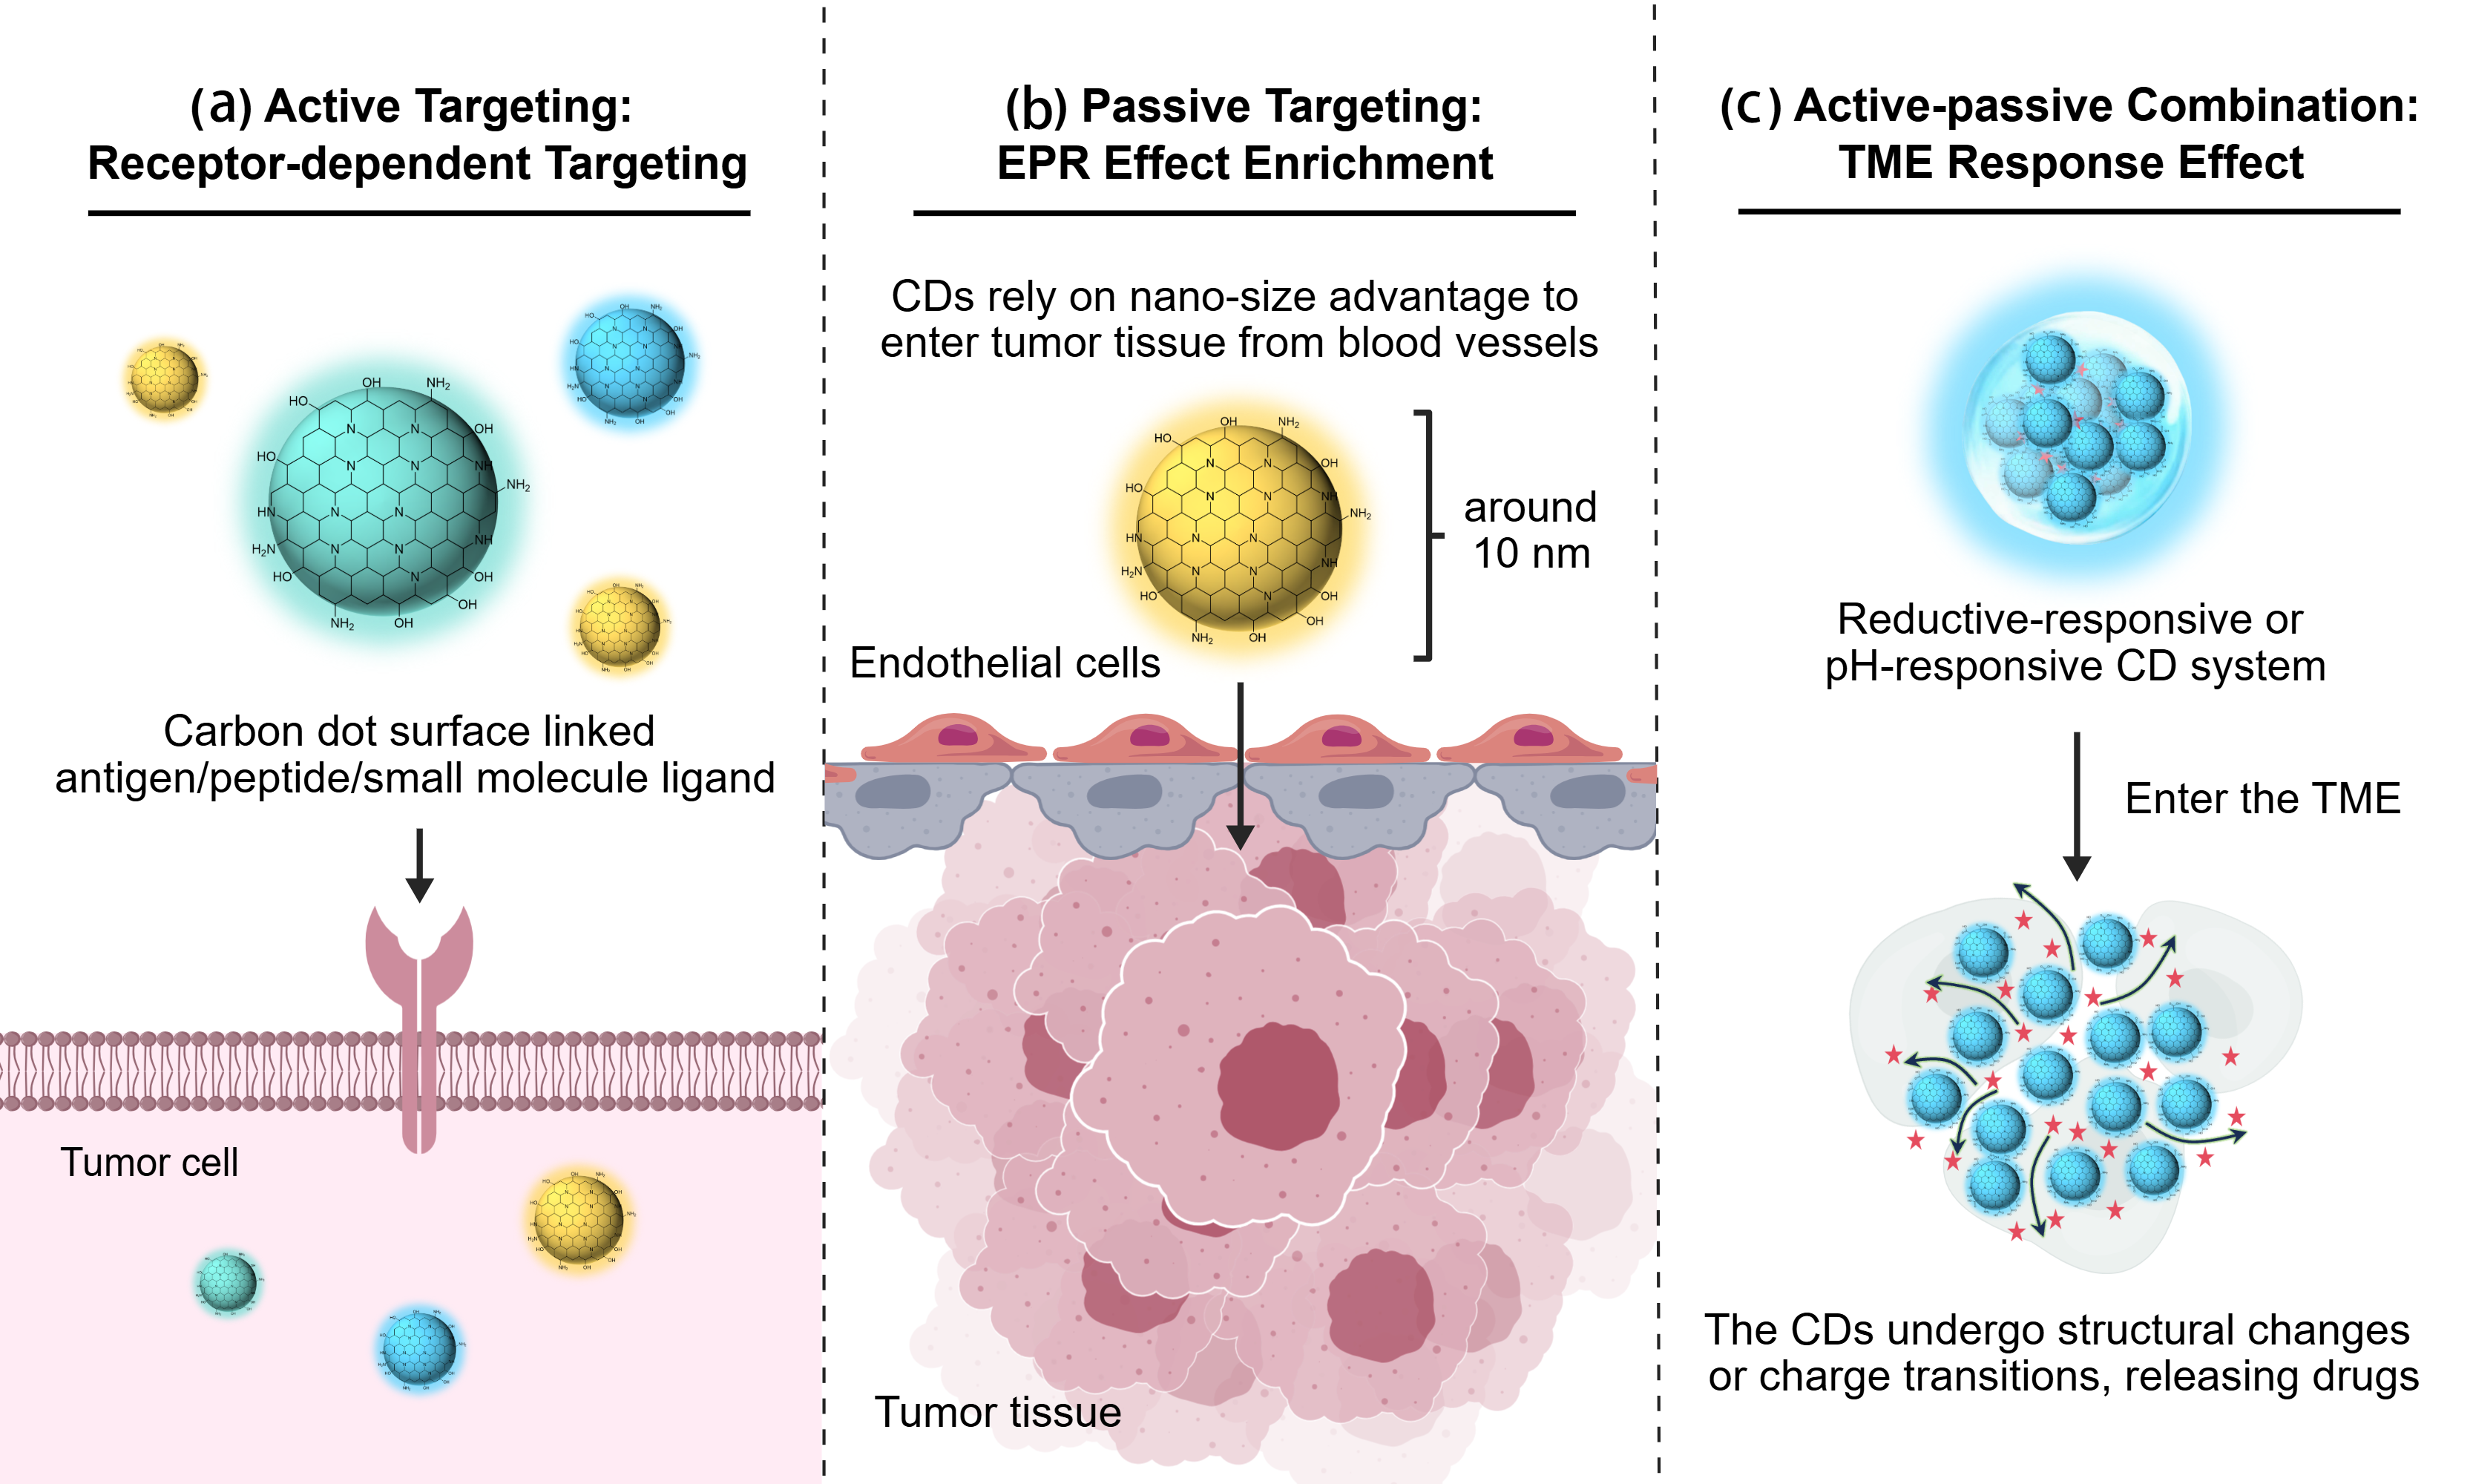
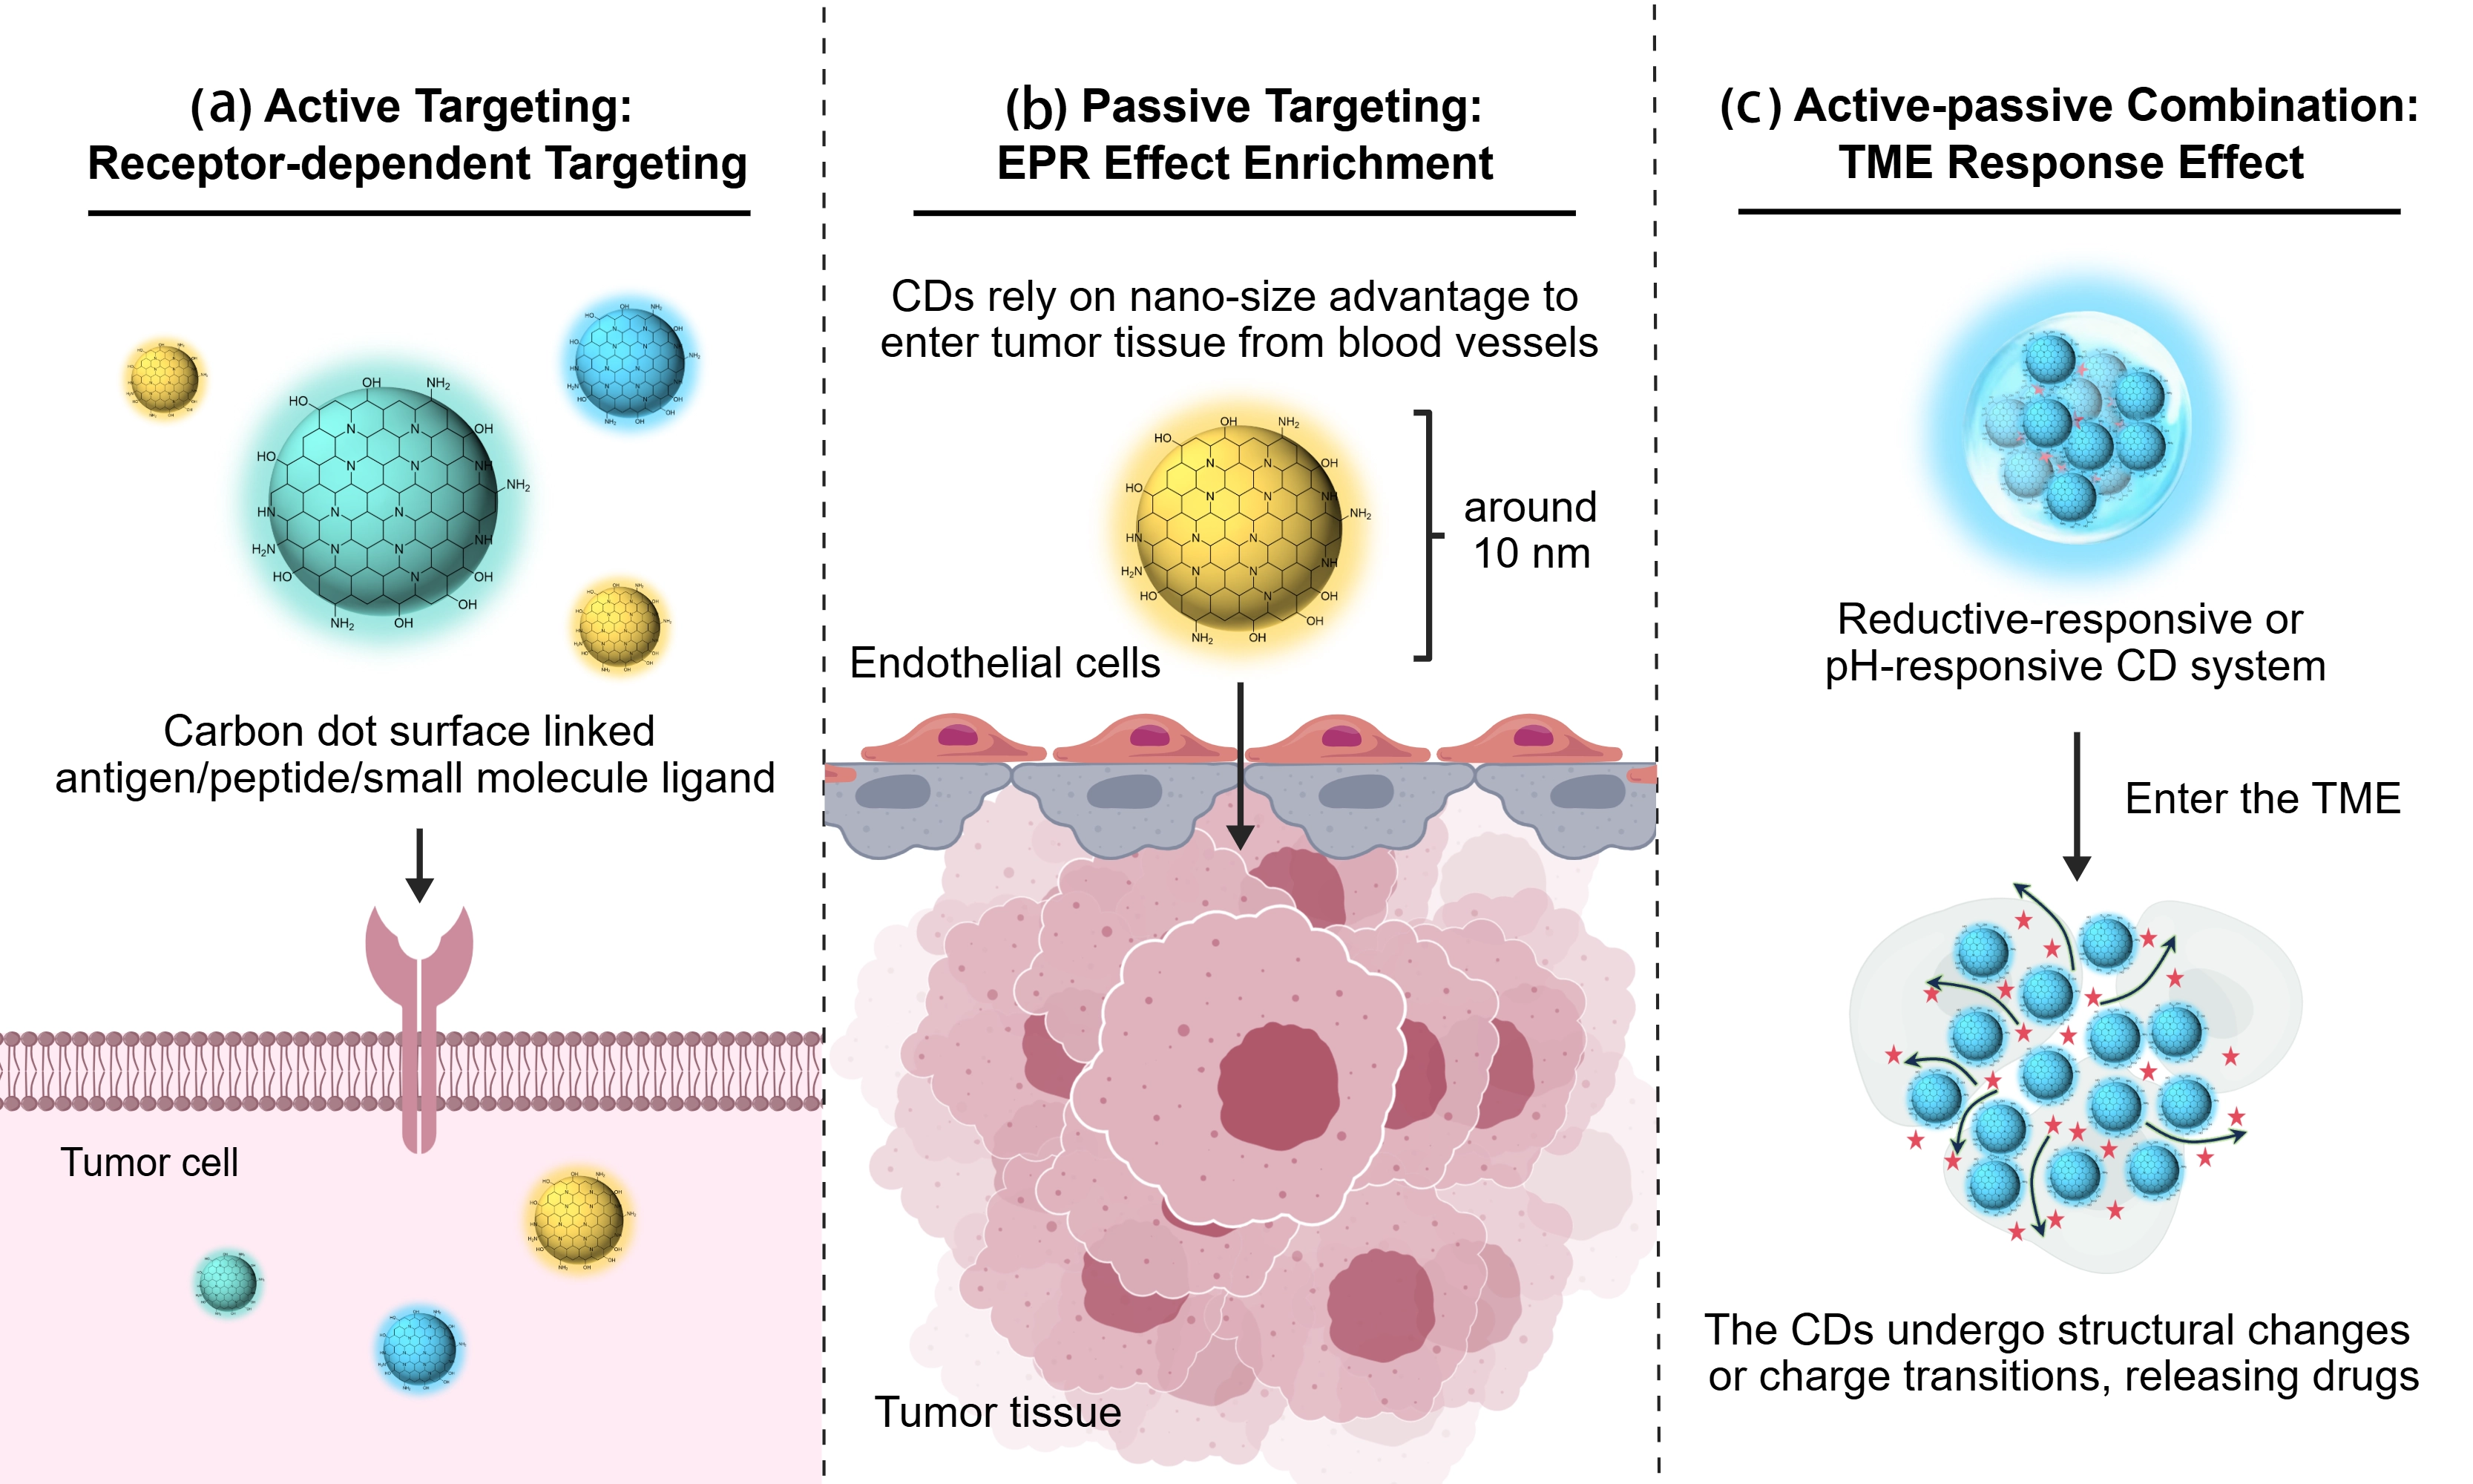
Figure 2. Schematic diagram of CDs-mediated targeted drug delivery system for pancreatic cancer: (a) Active targeting via receptor recognition: Using covalent linkage strategy, specific recognition units are functionalized onto the surface of the carrier. These modified carriers can specifically bind to receptors overexpressed on the membrane of pancreatic cancer cells, triggering receptor-mediated endocytosis and significantly enhancing the cellular uptake efficiency. This mechanism improves the tumor enrichment efficiency while minimizing the non-targeted accumulation in normal tissues; (b) Passive targeting via the EPR effect: Owing to their ultra-small nanoscale size, CDs can extravasate through the abnormal, leaky vasculature of pancreatic tumor tissues and accumulate in the tumor stroma by enhancing the EPR effect. This strategy achieves tumor targeting without requiring specific ligand modification, providing a basis for subsequent targeted delivery; (c) Combined active–passive targeting via TME responsiveness: An integrated strategy combining passive enrichment, active recognition, and TME responsiveness has been established for targeted delivery. Reductive responsive or pH-responsive CDs remain structurally stable in the neutral systemic circulation. Upon reaching the pancreatic cancer TME, these CDs undergo structural decomposition or surface charge reversal, thereby triggering rapid drug release and enhancing intracellular drug delivery. CDs: carbon dots; EPR: enhanced permeability and retention; TME: tumor microenvironment.
4.2 Passive targeting and tumor microenvironment responsiveness
Beyond their general nanocarrier properties, CDs possess several unique advantages that make them attractive for passive targeting. Compared with conventional nanocarriers such as liposomes, polymer nanoparticles, and gold nanoparticles, CDs generally exhibit ultra-small particle size (< 10 nm), intrinsic fluorescence, abundant surface functional groups, and potential for renal clearance. These features not only facilitate surface functionalization and the integration of diagnosis and therapy, but also enhance the ability of CDs to diffuse through the dense stroma of pancreatic cancer and reduce their long-term accumulation in the liver and spleen.
CDs can rely on the advantages of size to achieve passive targeting. Tumor tissues exhibit the enhanced permeability and retention (EPR) effect due to abnormal vascular structure and impaired lymphatic return[61]. CDs with a particle size of about 10 nm can enter the tumor stroma through the regions of abnormal vascular permeability and be relatively retained in the tumor tissue, thereby achieving a certain degree of passive enrichment (Figure 2B). However, there is increasing evidence that the EPR effect is highly heterogeneous across tumor types and is less pronounced in pancreatic cancer than in many other solid tumors. The dense desmoplastic matrix, low blood supply, and high interstitial fluid pressure severely limit nanoparticle extravasation and intratumoral transport. Therefore, passive accumulation mediated by EPR alone is not sufficient to achieve efficient drug delivery in pancreatic cancer.
In recent years, passive targeting has been increasingly integrated with microenvironment-responsive mechanisms. The pancreatic cancer microenvironment is characterized by mild acidity, redox imbalance, and elevated enzyme expression. The construction of pH-responsive or reduction-responsive CD systems enables structural changes or charge transitions in the tumor region, thereby enhancing cellular uptake and drug release efficiency[62]. For example, such systems maintain a stable structure in the neutral blood environment but undergo surface charge reversal or bond cleavage in the acidic TME, thereby triggering rapid drug release[63]. This multistage delivery strategy partially compensates for the limited EPR effect in PDAC by combining passive accumulation, deep stromal penetration, and tumor microenvironment-responsive drug release. Consequently, CDs can improve drug distribution throughout tumor tissues rather than relying solely on vascular permeability. For solid tumors such as pancreatic cancer, which are characterized by limited drug penetration and dense stroma, multi-stage targeting strategies are particularly important and may provide a more precise delivery platform for subsequent photothermal therapy or chemotherapy synergy (Figure 2C).
5. Applications of Carbon Dots in Hyperthermia Therapy for Pancreatic Cancer
5.1 Hyperthermia types and mechanisms of action
Owing to their unique physicochemical properties, CDs have enabled hyperthermia-based therapeutic strategies for pancreatic cancer, including photothermal therapy (PTT), photodynamic therapy (PDT), magnetic hyperthermia (MHT), and synergistic therapies[64].
In PTT, CDs serve as highly efficient light absorbers that convert light energy into heat upon NIR laser irradiation to elevate the local tumor temperature to the therapeutic window of 42-46 °C and thereby kill pancreatic cancer cells through protein denaturation and DNA strand breaks. Numerous studies have confirmed the excellent photothermal conversion performance of CDs in the NIR region. For example, the nitrogen-doped CDs achieved photothermal conversion efficiencies of 31.25% and 27.12% under 808 nm and 1,060 nm laser irradiation, respectively[65]. Sulfur and nitrogen codoped NIR CDs reached an efficiency of 59%[66]. Ganoderma-derived CDs were shown to generate synergistic PTT/PDT effects under NIR laser irradiation, effectively killing pancreatic cancer cells[67].
However, most of the above CD-based PTT systems have been validated primarily in prostate cancer, liver cancer, or other models. The Ganoderma-derived CDs are one of the few systems tested in pancreatic cancer cells, but only in vitro results have been reported. Their in vivo efficacy remains to be confirmed. The dense fibrotic stroma of pancreatic cancer may impair heat conduction efficiency, and heat-shock protein upregulation induced by hyperthermia can trigger tumor tolerance. Future studies should address these challenges and validate the true therapeutic efficacy of PTT in orthotopic pancreatic cancer models (Figure 3A).
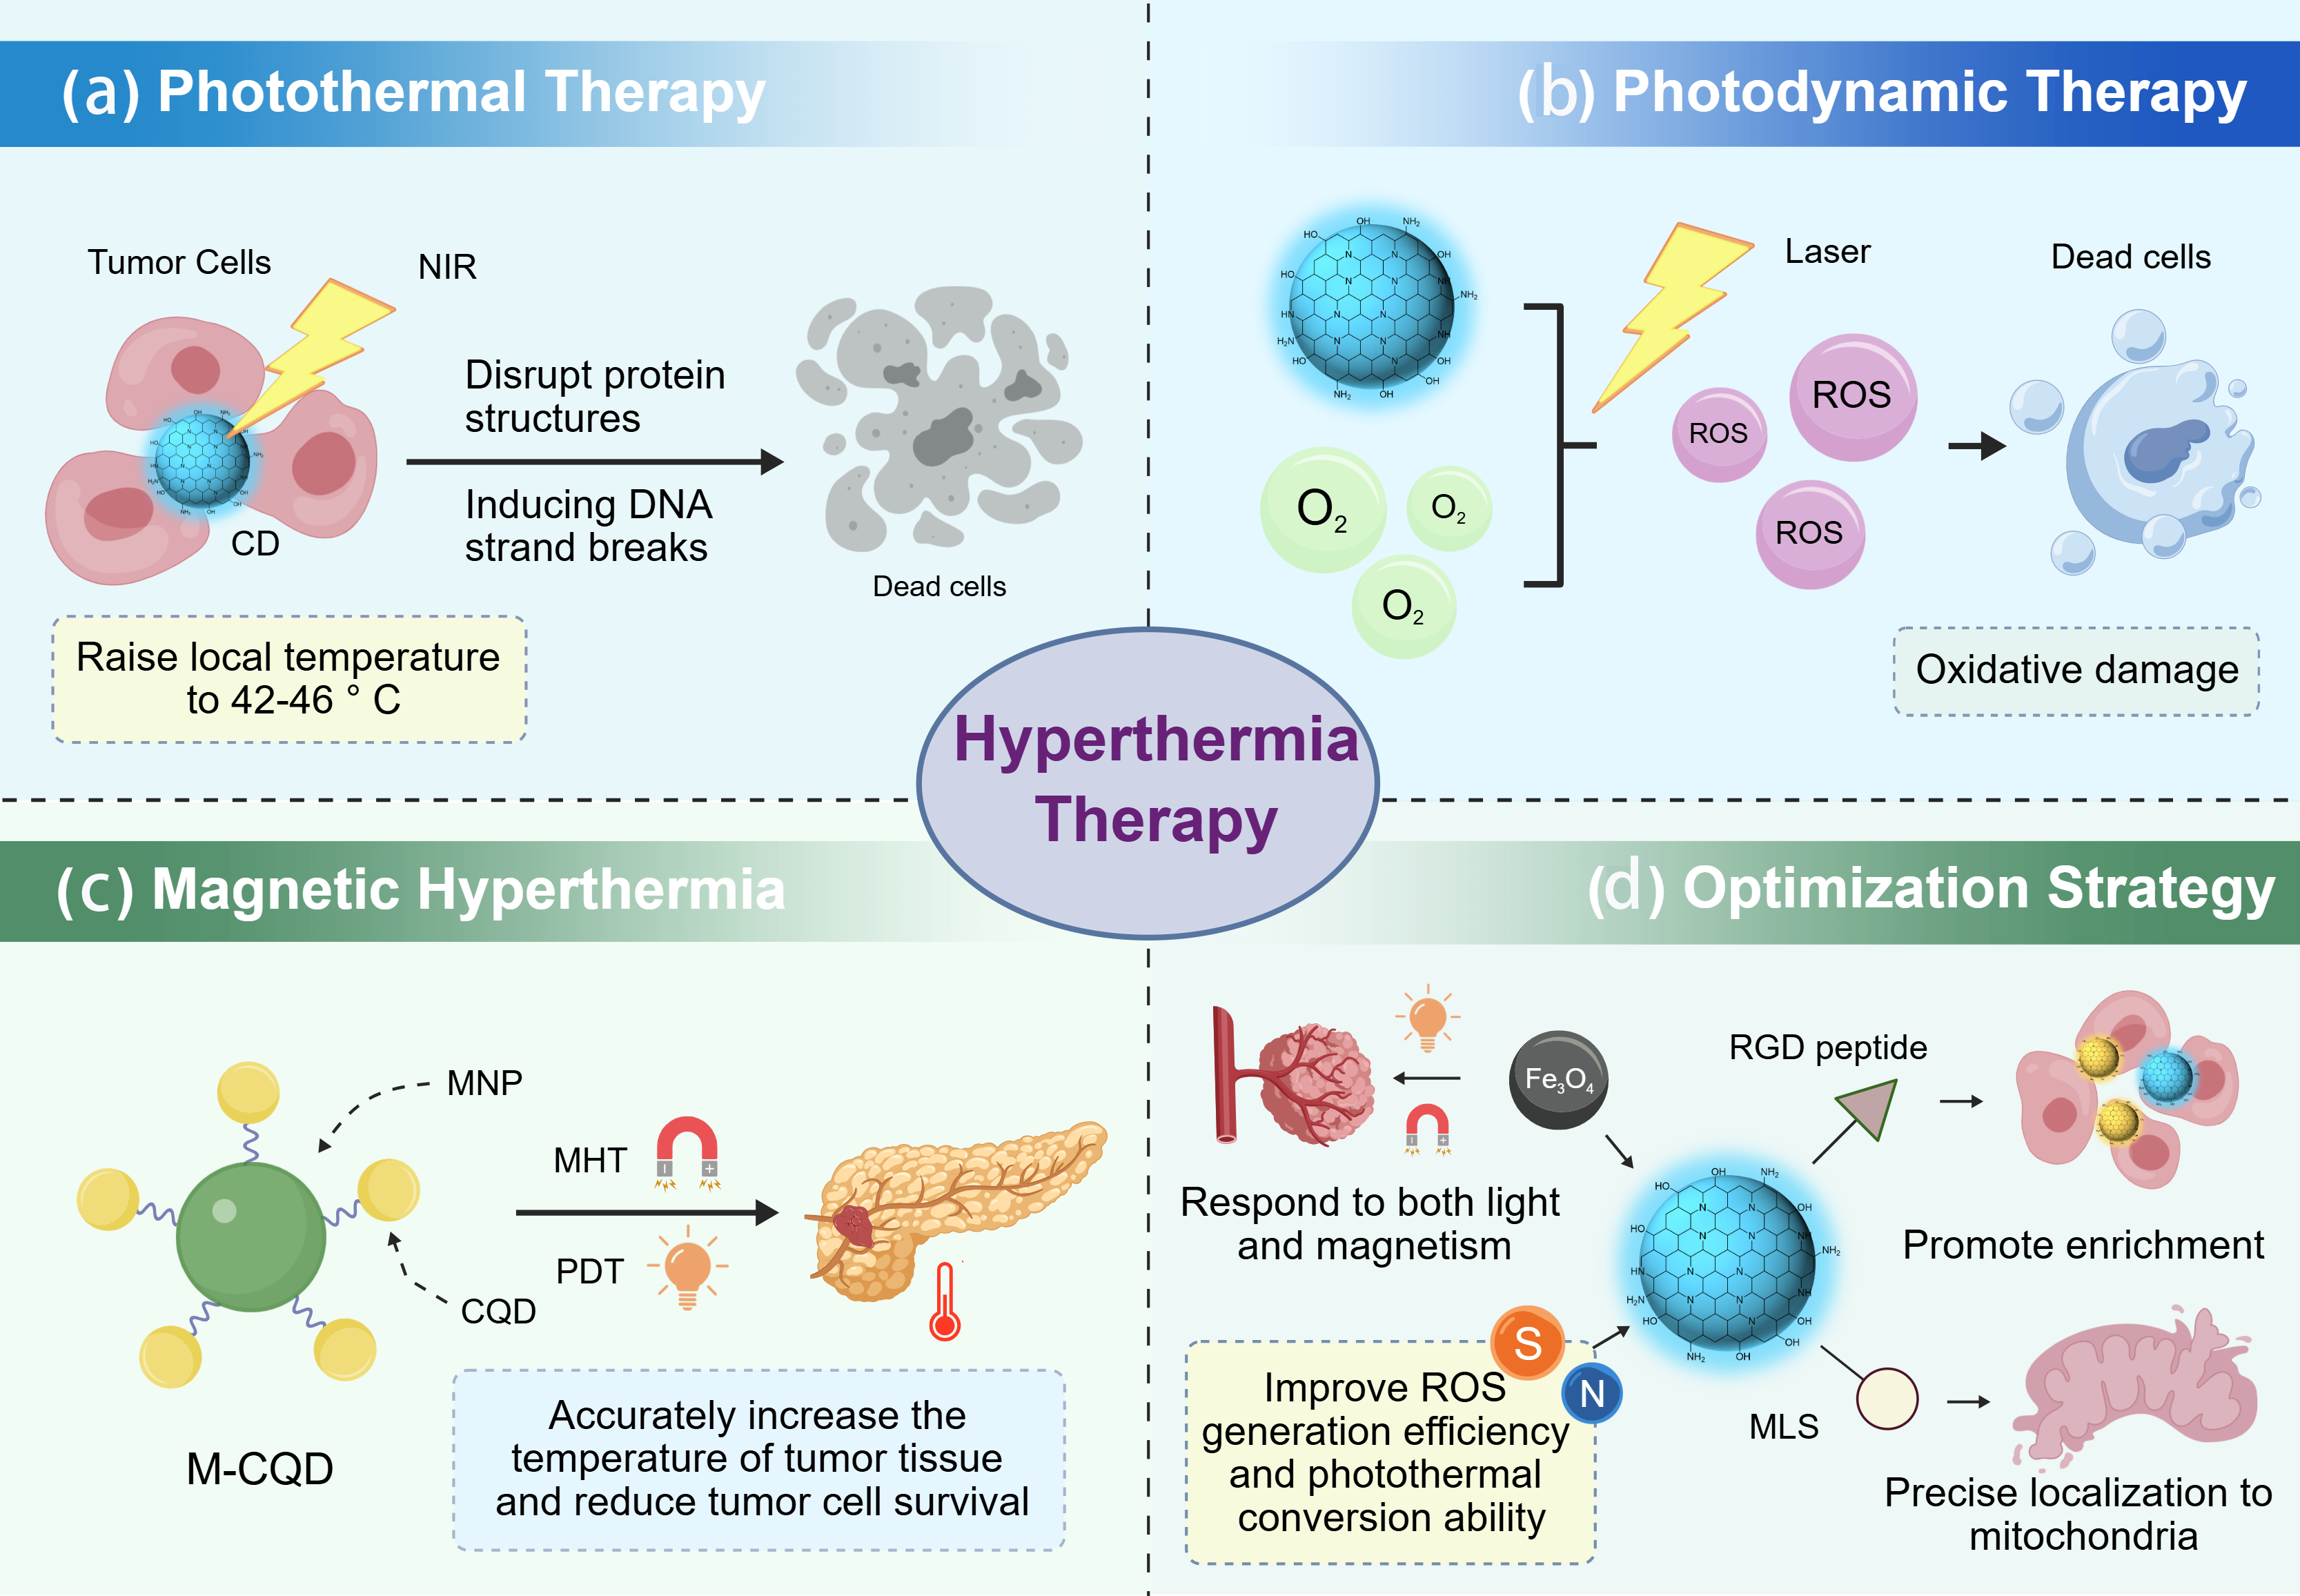
Figure 3. Schematic diagram of the synthesis and optimization mechanism of CDs for hyperthermia applications: (a) Photothermal therapy: CDs act as efficient NIR absorbers, converting light energy into localized heat that disrupts protein structures and induces DNA strand breaks, thereby killing pancreatic cancer cells; (b) Photodynamic therapy: CDs serve as photosensitizers that generate ROS upon laser irradiation. These ROS cause oxidative damage to the cell membranes and biomolecules of tumor cells, ultimately inducing apoptosis; (c) Magnetic hyperthermia: CDs can be combined with magnetic nanoparticles to form M-CQDs, which generate heat under an alternating magnetic field, precisely elevating the tumor temperature into the therapeutic window. The combination of photodynamic therapy and magnetic hyperthermia further enhances the antitumor effect; (d) Optimization strategy: Engineering modification of CDs, including heteroatom doping, surface functionalization, and conjugation with magnetic nanoparticles, can enhance the generation of ROS, photothermal conversion, tumor accumulation, and mitochondrial targeting, thereby improving the efficacy of hyperthermia therapy. CDs: carbon dots; NIR: near-infrared radiation; ROS: reactive oxygen species; M-CQDs: magnetic carbon quantum dots; MNP: magnetic nanoparticle; CQD: carbon quantum dot; MHT: magnetic hyperthermia; PDT: photodynamic therapy; RGD: arginine-glycine-aspartic acid; MLS: mitochondrial targeting peptides.
PDT offers the advantages of minimal invasiveness and low damage to normal tissues. In PDT, CDs act as photosensitizers that, upon excitation with light of specific wavelengths, react with oxygen in the TME to generate reactive oxygen species (e.g., 1O2), which oxidatively damage cell membranes and biomacromolecules. Researchers have constructed FA-targeted cage-like CDs (C-dotsCL) for the delivery of the anticancer drug methotrexate (MTX). This nanocomplex efficiently generates reactive oxygen species (ROS) upon NIR irradiation to achieve photodynamic therapy, while NIR irradiation also significantly accelerates MTX release in tumor tissues, enabling chemo-PDT synergy. In a genetically engineered pancreatic cancer model, C-dotsCL delivered high concentrations of MTX to the tumor site, significantly improving the pharmacokinetic parameters of MTX and enhancing its therapeutic efficacy[56]. However, the inherently hypoxic TME of pancreatic cancer may compromise the efficiency of ROS generation in PDT. Therefore, considerable hurdles remain to be overcome before CDs for PDT can be translated into clinical applications (Figure 3B).
For MHT, CDs can be covalently conjugated with magnetic nanoparticles (MNPs) to form composite systems (M-CQDs), which generate heat via Néel and Brownian relaxation under an alternating magnetic field (AMF). Studies have shown that M-CQDs exhibit a specific absorption rate (SAR) of up to 95.04 W/g at a frequency of 260.84 kHz, enabling stable maintenance of the temperature above 42 °C[68]. This approach offers deep tissue penetration without being limited by optical penetration depth, although it currently suffers from relatively low heating efficiency and requires large magnetic equipment. MHT-based combination therapy has become a research hotspot. One study demonstrated that M-CQDs-mediated combination of PDT and MHT reduced tumor cell viability to approximately 4%, significantly outperforming either monotherapy, providing a rationale for developing MHT-PDT synergistic CDs for pancreatic cancer[68]. Clinical studies have confirmed that the synergy between hyperthermia and chemoradiotherapy can improve the prognosis of pancreatic cancer patients. The median OS of the combined treatment group (11.7 months) is significantly longer than that of the chemoradiotherapy alone group (5.6 months), and the mechanism is related to the improvement of the hypoxic TME and enhanced drug delivery efficiency by hyperthermia[69] (Figure 3C).
5.2 Optimization of hyperthermia performance of carbon dots
The hyperthermia efficiency of CDs can be optimized through multiple strategies, including structural design and functional modification. Regarding the choice of carbon precursors, chitosan-derived amine-functionalized CDs and super carbon dots (SCDs) synthesized from citric acid and dicyandiamide both exhibit excellent photothermal conversion, with SCDs achieving an NIR photothermal conversion efficiency of up to 41.7%[70]. With respect to size control, CDs with diameters of 2-8 nm enhance light absorption via the quantum confinement effect, whereas pH-responsive SCDs self-assemble into 20-30 nm aggregates in the acidic TME (pH ≈ 6.5) of pancreatic cancer, significantly improving NIR absorption and thermal stability. M-CQDs, formed by conjugating 2-8 nm CDs with 10-20 nm MNPs, are engineered to a particle size of 20-30 nm, balancing stability and hyperthermia efficiency[68]. Surface modification and heteroatom doping are key strategies for performance optimization. For instance, in HepG2 liver cancer cells, RGD peptide modification has been shown to enhance the cancer cell-targeting ability of CDs to a limited extent. Furthermore, SCDs modified with mitochondrial targeting peptides (MLS) can precisely localize to the mitochondria of tumor cells, disrupting membrane potential and inducing protein disulfide bond cleavage[70]. Doping with heteroatoms such as sulfur and nitrogen can regulate the electronic structure of CDs, thereby improving ROS generation efficiency and photothermal conversion capacity[64]. After compounding with magnetic materials like Fe3O4, CDs can simultaneously respond to light and magnetic fields, enabling dual-mode hyperthermia. For example, M-CQDs maintain efficient heat production even at a low frequency of 260.84 kHz[68] (Figure 3D).
Research on CDs for pancreatic cancer hyperthermia is still in its early stages, but it has demonstrated promising therapeutic potential. Preclinical studies on lung cancer and breast cancer have shown that photodynamic therapy mediated by CD and modified with RGD can significantly inhibit tumor growth, while the combined use of M-CQD-mediated hyperthermia in mouse models led to a significant reduction in tumor size suggesting the proof-of-concept evidence for pancreatic cancer therapy[68]. Owing to an ultra-small particle size, CDs are theoretically capable of penetrating the dense fibrotic stroma of pancreatic cancer and overcoming the delivery bottleneck of conventional photothermal agents. However, this size-related advantage has not yet been directly verified in vitro or in vivo, and further targeted investigations are needed. Systematic reviews have confirmed that, for locally advanced or metastatic pancreatic cancer, patients receiving hyperthermia combined with chemoradiotherapy have significantly better objective response rates and median OS than those treated with chemoradiotherapy alone[69].
6. Research Progress on pH-Responsive Carbon Dots in Pancreatic Cancer Therapy
6.1 Synthesis and surface modification of pH-responsive carbon dots
For biomedical applications targeting the TME, pH-responsive CDs (pH-CDs) have been developed. The synthesis of pH-CDs typically employs green and straightforward methods, with a wide range of precursors, including small molecular compounds such as citric acid, urea, and amino acids, which are prepared via techniques like microwave-assisted synthesis and hydrothermal synthesis[21,71-73]. Their pH-responsive properties mainly rely on acid-base sensitive functional groups modified on the surface, such as carboxyl groups (-COOH), amino groups (-NH2), and imidazole groups. These groups undergo protonation or deprotonation under different pH conditions, triggering structural changes of CDs and thereby enabling controlled drug release[74] (Figure 4A).
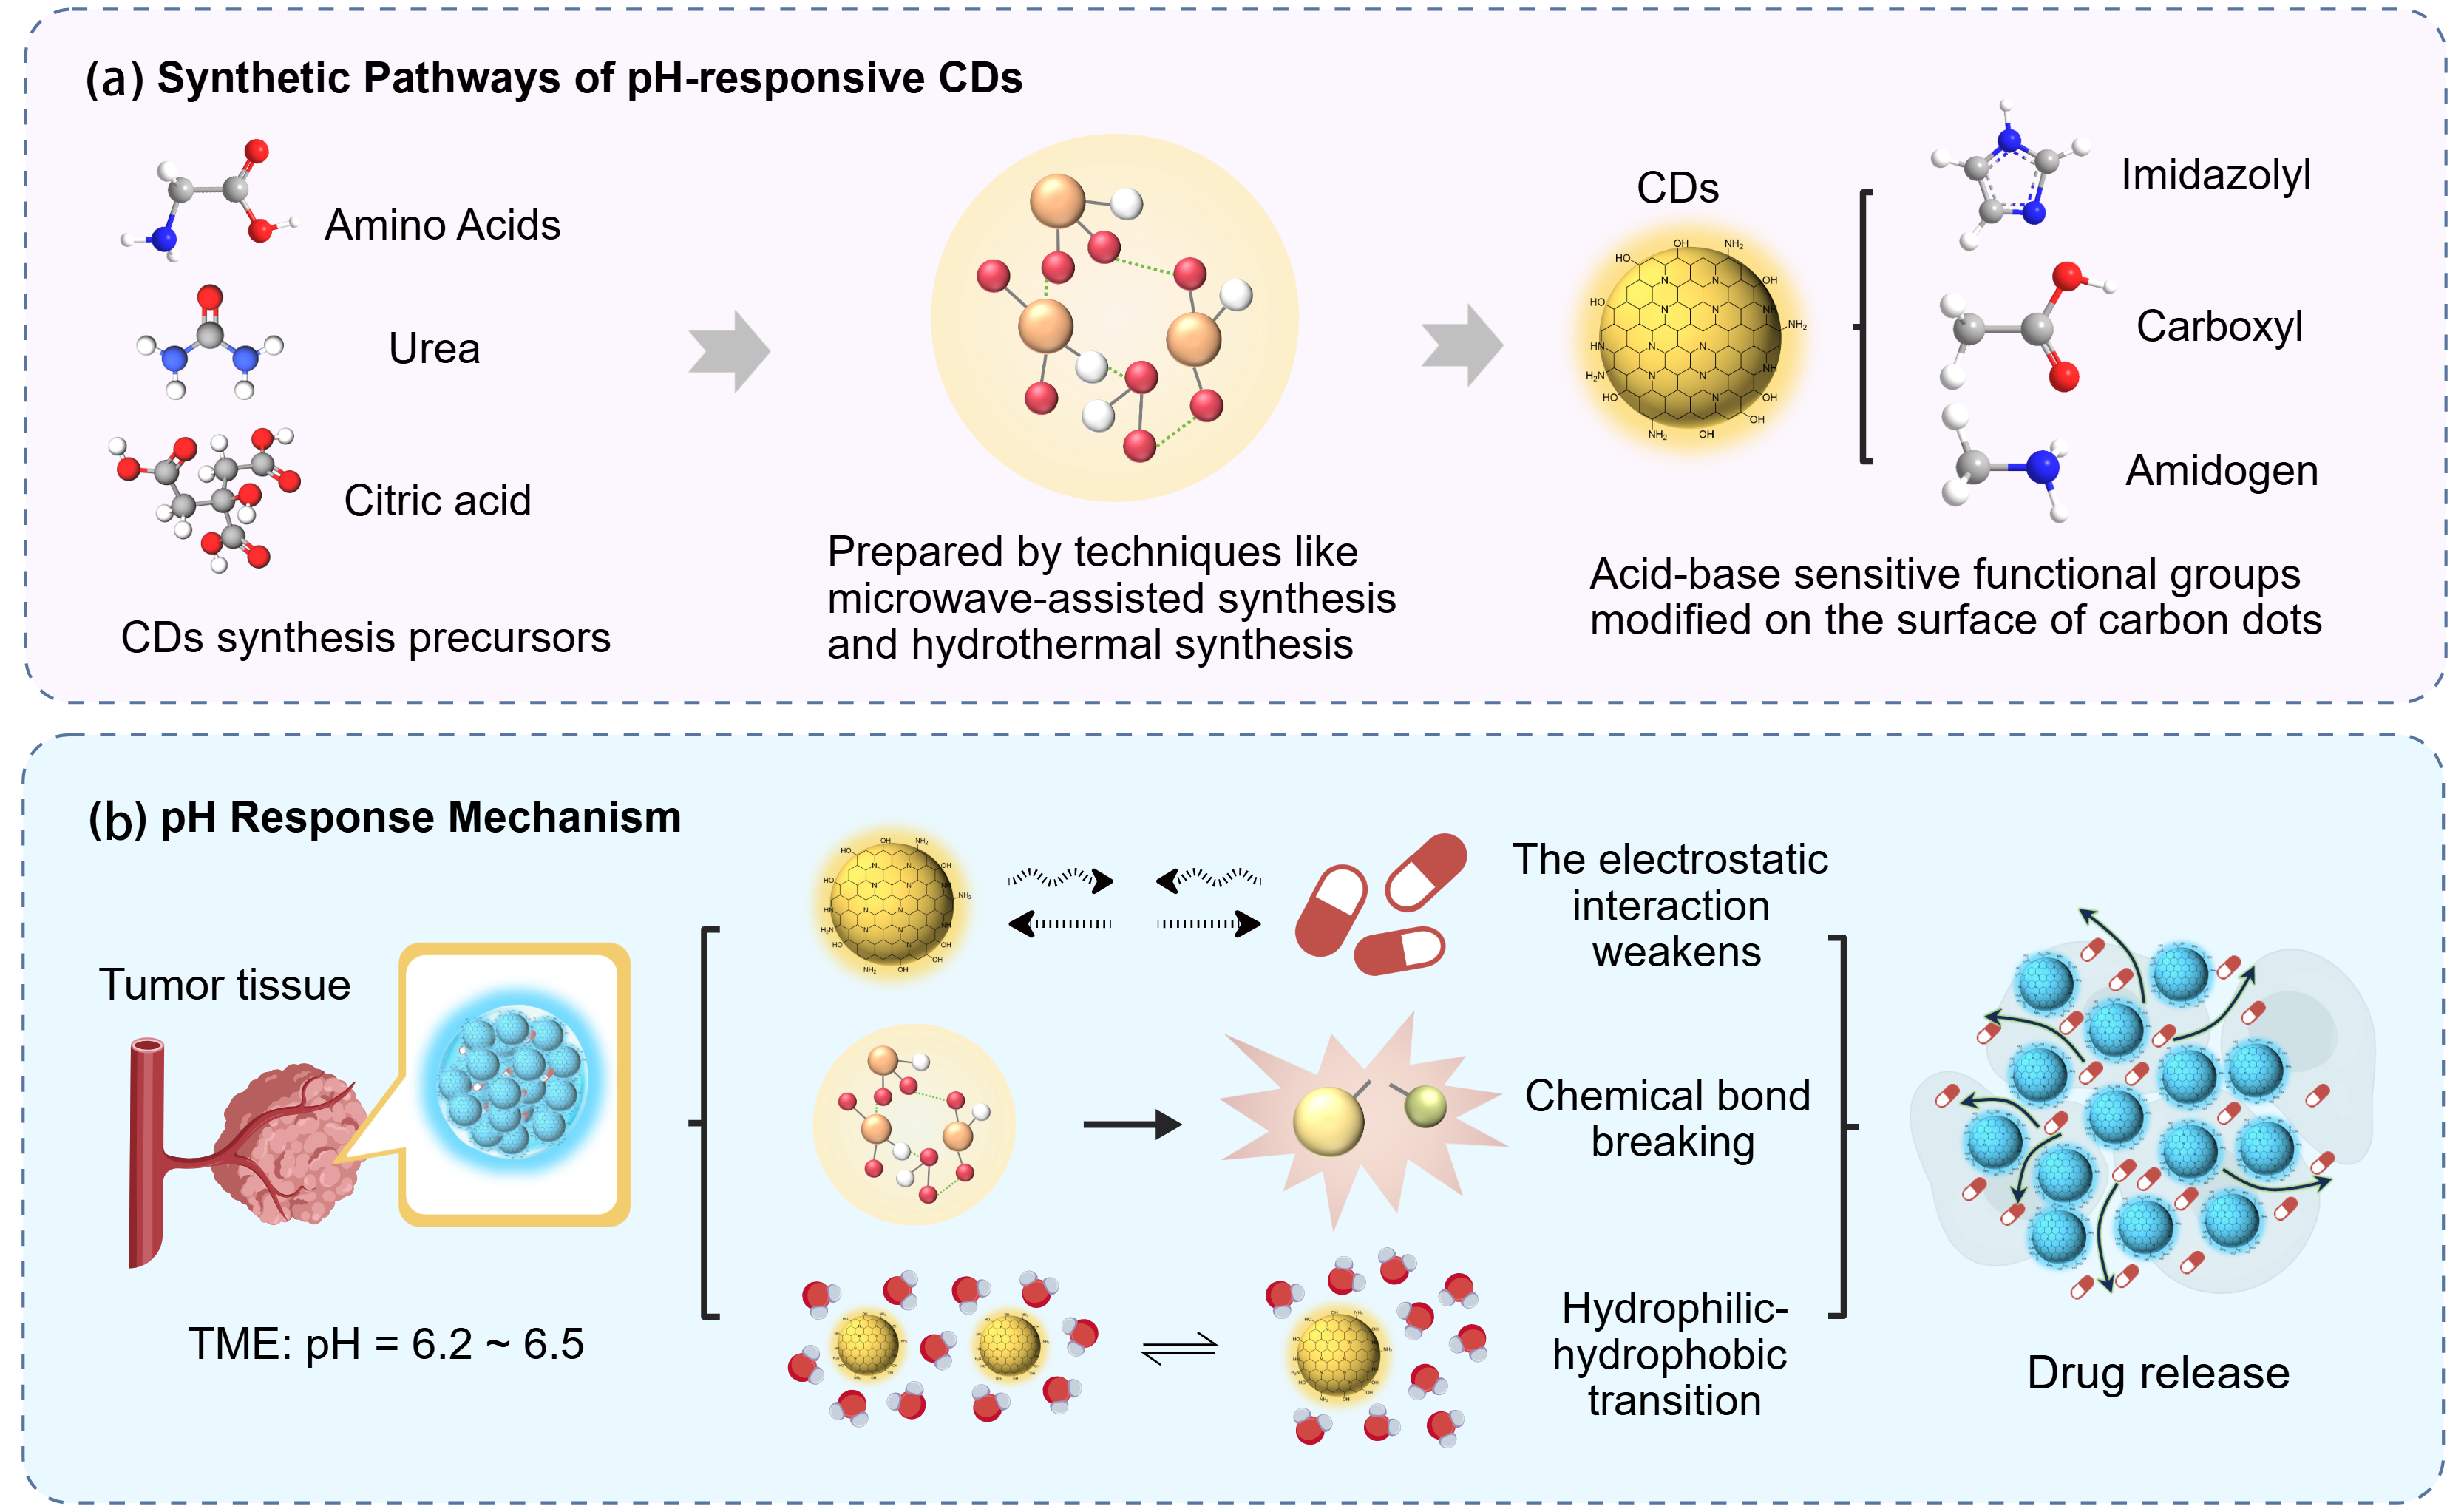
Figure 4. Schematic diagram of the synthesis pathway and drug release mechanism of pH-responsive CDs: (a) Synthesis of pH-responsive CDs: pH-responsive CDs are prepared by green synthesis technology using biocompatible precursors. Functional groups sensitive to acid-base conditions are modified on the surface of the CDs, enabling their response under different pH conditions; (b) pH response mechanism: In the acidic TME of pancreatic cancer, CDs trigger drug release through three main mechanisms: weakening the electrostatic interaction between the surface groups on CDs and drug molecules, chemical bond breaking and hydrophilic transformation of CD surface. These mechanisms enable spatiotemporally controlled drug release at the tumor site. CDs: carbon dots; TME: tumor microenvironment.
The application of pH-CDs in pancreatic cancer theranostics has attracted increasing attention. Seo et al. developed non-polymeric pH-sensitive carbon dots (pSCDs) from citric acid and 1-(3-aminopropyl) imidazole via a one-step rapid synthesis method. These CDs are rich in surface imidazole groups, enabling doxorubicin (DOX) loading through hydrophobic interactions with a loading efficiency of 78.55%. In the acidic TME (pH ≈ 6.5), protonation of the imidazole groups leads to depolymerization of the CD structure and an approximately 7-fold increase in DOX release compared to the control group, with therapeutic efficacy validated in the PANC-1 cell line[75]. Nevertheless, the mechanistic explanation of CD depolymerization in this study remains largely inferential, lacking direct comparative evidence from particle size distribution and transmission electron microscopy imaging before and after depolymerization. Moreover, DOX loading relies primarily on non-covalent hydrophobic interactions. Whether this loading mode remains stable in physiological environments containing serum, or whether premature drug leakage occurs, has not been evaluated. In addition, drug release experiments were conducted only in PBS buffer, without the introduction of serum proteins, hyaluronidase, or other factors present in vivo to simulate the real TME.
In another study, researchers constructed boron and nitrogen co-doped CDs as fluorescent nanocarriers for the hydrophobic anticancer drugs curcumin (CUR) and paclitaxel (PTX), demonstrating significant pH-dependent drug release behavior in pH 5.0 and pH 7.4 buffer media[76]. However, this study has not been validated in pancreatic cancer cell lines or animal models, leaving its applicability in the pancreatic cancer context unclear. Moreover, the study fails to elucidate the specific mechanism by which boron and nitrogen co-doping synergistically regulates pH responsiveness. The explanation that doping alters the surface chemical state remains qualitative, lacking systematic quantitative analysis of X-ray photoelectron spectroscopy (XPS) and zeta potential variations with pH.
Peanut shell-derived CDs, functionalized with amino groups and conjugated with DOX, exhibited a cumulative drug release rate of 81.4% at pH 6.5, significantly higher than the 55.4% observed at pH 7.4[77]. We consider the pH selectivity of this system to be suboptimal because it poses a risk of non-specific drug release. In addition, although agricultural waste as a carbon source offers cost advantages, the inherent batch-to-batch variability in chemical composition poses potential challenges to product standardization and reproducibility. Although this study has not yet been validated in pancreatic cancer models, the pH 6.5 condition is compatible with the pancreatic cancer TME, offering insights for the development of pH-CDs for pancreatic cancer therapy.
6.2 pH-responsive mechanisms and drug delivery strategies
The drug delivery mechanisms of pH-CDs are primarily triggered by the acidity of the TME and can be classified into three types.
The first involves regulation of electrostatic interactions[74]. Functional groups such as -COOH/-COO-, -OH, and -NH2 undergo ionization equilibria under different pH conditions, thereby regulating the binding affinity between CDs and drug molecules. Under neutral or mildly alkaline conditions (pH ≈ 7.4), carboxyl groups predominantly exist in their deprotonated form (-COO-), imparting an overall negative charge to the CDs and enabling strong electrostatic attraction with positively charged amine groups in anthracycline drugs such as DOX, resulting in stable CD-DOX complexes. In contrast, under acidic conditions (pH ≈ 5.0-6.5), carboxyl groups become progressively protonated (-COOH), reducing the negative charge density[78]. Meanwhile, the amine groups in DOX are more readily protonated to -NH3+, resulting in a redistribution of charges that weakens electrostatic interactions and facilitates drug release. This method is simple to design and offers high drug loading capacity, but it suffers from slow drug release kinetics and limited specificity.
The second mechanism is structural collapse-triggered release. CDs containing acid-base sensitive groups such as imidazole groups and hydrazone bonds undergo protonation or chemical bond cleavage under acidic conditions, resulting in collapse of the carrier structure and rapid drug release. For instance, in imidazole-functionalized systems, the pKa of the imidazole ring is typically in the range of 6.0-6.5. When the pH falls below this range, protonation of the imidazole nitrogen (from -N to -NH-) significantly increases the overall positive charge and alters intermolecular interactions, potentially leading to structural collapse or rearrangement[75]. This method enables rapid and thorough drug release, but it suffers from poor blood stability and is prone to premature leakage.
The third is the hydrophilic-hydrophobic transition. Under neutral conditions, carboxyl and hydroxyl groups confer strong hydrophilicity and a negative zeta potential (e.g., around -25 mV), which helps maintain colloidal stability via electrostatic repulsion. Upon the introduction of amine-rich polymers such as chitosan, the presence of protonated -NH3+ groups shifts the surface charge to positive values, thereby altering interparticle interactions and drug distribution within the carrier. Due to its aromatic and hydrophobic nature, DOX preferentially partitions into relatively hydrophobic domains and engages in π-π stacking interactions with CDs. Under acidic conditions, further protonation of amine groups enhances hydrophilicity while disrupting hydrophobic domains, leading to the loosening or reorganization of the ‘hydrophobic core-hydrophilic shell’ structure[79]. Concurrently, reduced electrostatic repulsion promotes particle aggregation or structural relaxation, collectively facilitating drug diffusion and release. This approach enables co-delivery of both hydrophilic and hydrophobic drugs, but the manufacturing process is complex and the associated cost is relatively high (Figure 4B).
In terms of drug selection, current research mainly focuses on optimizing the delivery of traditional chemotherapeutic drugs. Gemcitabine, a first-line chemotherapeutic drug for pancreatic cancer, has drug resistance mechanisms associated with downregulated nucleoside transporter expression and inhibited deoxycytidine kinase activity. pH-CDs can increase the concentration of gemcitabine at tumor sites through targeted delivery[4,75]. In addition, some studies have even achieved co-delivery of chemotherapeutic drugs and gene drugs, enhancing therapeutic efficacy through synergistic effects[29].
Overall, current research on pH-CDs for pancreatic cancer theranostics remains at an early exploratory stage. Most reports focus on in vitro release behavior and cellular-level validation, whereas critical data on in vivo pharmacokinetics, tumor-specific accumulation, and long-term biosafety are severely lacking. Furthermore, quantitative elucidation of pH-responsive mechanisms and evaluation of efficacy in orthotopic pancreatic cancer models remain urgent directions requiring breakthrough progress.
7. Integrated Imaging and Therapy Applications of Carbon Dots
An ideal theranostic platform requires that a single nanoparticle not only enable accurate tumor imaging and localization, but also exert simultaneous or sequential therapeutic effects. CDs show great potential for such dual function integration.
Based on their fluorescence emission wavelengths, CD imaging is primarily divided into blue-green imaging (400-550 nm) and NIR imaging (650-1,700 nm)[80]. Traditional blue-green CDs, such as pSCDs and Ag-GQDs, have been validated for in vitro imaging of pancreatic cancer cells and in vivo imaging in mouse tumor models, enabling direct visualization of drug distribution and accumulation through fluorescence signals. The pSCDs aforementioned achieved targeted and efficient release of DOX by surface modification with imidazole groups, demonstrating low cytotoxicity[75]. This study effectively simulated the acidic TME of pancreatic cancer in vitro, highlighting the potential of imidazole-modified CDs for pancreatic cancer therapy. However, in vivo experiments were limited to colon tumor-bearing mice. Due to the different anatomical location, blood supply, and interstitial characteristics, the drug delivery effect of pancreatic cancer is often significantly different from that in subcutaneous models, and therefore further experimental verification is required.
Nigam Joshi et al. designed Ag-GQD nanocomposites loaded with 5-FU, which inhibited PANC-1 cells by 72-78%. However, their study did not simulate the acidic TME, and the observation period was relatively short. In a rat pancreatic cancer model, Ag-GQDs significantly reduced the number of viable cells in tumor tissues without causing obvious damage to normal organs such as the liver, spleen, and kidneys[57]. It also confirmed that HA modification enhances the targeting efficiency of CDs, providing valuable insights for further optimization of CDs in pancreatic cancer treatment. Nevertheless, the potential long-term toxicity of doped silver ions has not been fully investigated.
Both blue-green emission CDs mentioned above are limited by inherent limitations, including shallow tissue penetration depth and strong tissue autofluorescence interference. Pancreatic cancer is located deep in the retroperitoneum, whereas the penetration depth of blue-green light in biological tissues is usually less than 1 mm. Moreover, endogenous substances such as collagen and NADH produce strong autofluorescence under blue-green light excitation, which severely reduces the imaging SNR. These limitations hinder the application of blue-green CDs for accurate imaging of deep pancreatic tissues and further underscore the need to develop red- and NIR-emitting CDs for the diagnosis and treatment of pancreatic cancer.
NIR-emitting CDs offer more options for the integration of diagnosis and treatment of pancreatic cancer. As mentioned above, the long-wavelength emission of the NIR CD allows it to penetrate deep tissues of pancreatic cancer and provide a fluorescent signal with a high signal-to-noise ratio. Some NIR CDs can also realize multimodal imaging to further improve the accuracy of tumor localization. However, the application of NIR CDs to integrated imaging and therapy of pancreatic cancer has not yet been investigated. In the context of lung cancer, citrate-derived CDs have been shown to efficiently load bergenin, which possesses the dual functions of targeted drug delivery and multimodal imaging, enabling accurate tumor localization and treatment guidance. This study provides a valuable reference for the development of NIR CDs for pancreatic cancer therapy[81] (Table 2).
Table 2. Summary of representative carbon dot platforms for pancreatic cancer theranostics.
| Carbon dot system | Main application | Precursors | Synthesis method | Size | Emission/absorption | Targeting strategy | In vivo model | Biocompatibility | Ref. |
| Er@TC-CQDs | Imaging and targeted drug release | Citric acid and 1,4,5,8-tetraaminoanthraquinone | Microwave-assisted (700 W, 5 min) | TEM: ~5 nm DLS: 47.4 nm (TC)/66.7 nm (after Er conjugation) | Red emission, ~676 nm | Active: covalent erlotinib conjugation (EGFR) | BALB/c mice (DMBA-induced pancreatic cancer) | LC50 ~162.87 µg/mL (PANC-1) | [35] |
| CDs-ICG-PEG | NIR-I imaging | Indocyanine green and PEG | Click chemistry, amide coupling, and PEGylation | AFM: ~6.8 nm (after PEGylation) | NIR-I emission 690-790 nm | Passive (EPR and PEG stealth) | BALB/c nude mice (BxPC3 subcutaneous xenograft) | IC50 > 500 µg/mL (multiple cell lines) | [36] |
| Multicolor fluorescent CDs | Multicolor fluorescence imaging | Glucose and aspartic acid | Hydrothermal (125 °C → 200 °C) | TEM: ~3.35 nm AFM: ~6.8 nm (after PEGylation) | Multicolor 400-700 nm, optimum ~525 nm | Passive (EPR and glucose metabolism theory) | In situ pancreatic cancer mouse model | Cell viability > 85% (PANC-1) | [37] |
| C-dotsCL-MTX-FA | Targeted chemotherapy and PTT/PDT | Citric acid, PEG-amine, and CTAB (template) | CTAB-templated hydrothermal (200 °C, 12 h) | TEM: 20-50 nm | Clathrate structure, NIR absorption (PTT/PDT) | Active: folic acid (folate receptor) | ICR nude mice | > 93% cell viability (BCSCs and Vero cells) | [56] |
| Ag-GQDs (HA-CMI) | Targeted drug delivery and imaging | Glutamine, silver nitrate, and sodium citrate | Pyrolysis (190-200 °C) and chemical reduction | TEM: 10-35 nm | Green fluorescence (~530 nm) | Active: hyaluronic acid (CD44) | Pancreatic cancer bearing Wistar rat model | CMI coating reduces Ag toxicity; HA formulation inhibits 72-78% of Panc-1 cells | [57] |
| Ganoderma lucidum CDs | Fluorescence imaging and PDT/PTT | Ganoderma lucidum extract, citric acid, and ethylenediamine hydrochloride | Hydrothermal (200 °C, 10 h) | TEM: 6.40 ± 1.31 nm | Blue-green fluorescence (~452 nm, ex 370 nm) NIR photothermal (808 nm) | Passive (EPR and potential tumor affinity) | BALB/c nude mice (BxPC-3 subcutaneous pancreatic model) | Normal cells (HPDE6-C7) > 90% viability (0-400 µg/mL) | [67] |
| pSCDs (DOX-loaded) | pH-responsive drug release | Citric acid and 1-(3-aminopropyl)imidazole | Microwave-assisted (700 W, 3 min) | TEM: 3-6 nm DLS: ~5 nm | Imidazole protonation triggers release at pH 6.5 | Passive (pH-responsive) | HCT-116 colon xenograft | No cytotoxicity at pH 7.4; enhanced release at pH 6.5 | [75] |
AFM: atomic force microscopy; Ag-GQDs: silver-doped graphene quantum dots; BxPC-3: biopsied xenotransplanted pancreatic cancer cell line 3; CQDs: carbon quantum dots; CTAB: cetyltrimethylammonium bromide; DLS: dynamic light scattering; DMBA, 7,12-dimethylbenz[a]anthracene; DOX: doxorubicin; EGFR: epidermal growth factor receptor; EPR: enhanced permeability and retention; FA: folic acid; GQDs: graphene quantum dots; HA: hyaluronic acid; IC50: half-maximal inhibitory concentration; LC50: half-maximal lethal concentration; MTX: methotrexate; NIR: near-infrared; PANC-1: pancreatic cancer cell line; PEG: polyethylene glycol; pSCDs: pH-sensitive carbon dots; PTT/PDT: photothermal therapy/photodynamic therapy; TEM: transmission electron microscopy.
8. Limitations of the Current Study
Although CDs have shown great potential in cancer theranostics, their application in the treatment of pancreatic cancer still faces a series of key challenges.
8.1 Inherent property limitations
The suboptimal physicochemical properties of CDs originate from immature synthetic control and unclear relationships between structures and performances, rather than isolated technical drawbacks. Most reported CDs exhibit predominant absorption in the blue-green light region, and achieving stable NIR emission remains difficult. This is attributed to the ambiguous luminescence mechanism of NIR-CDs and insufficient regulation of surface energy levels, leading to limited tissue penetration depth and unstable fluorescence in complex in vivo environments. Consequently, these limitations preclude adequate imaging of deep-seated pancreatic tumors[82].
For pH-responsive CDs, the response range (5.0-6.5) does not precisely match the weakly acidic TME of PDAC (pH ≈ 6.2-6.5). This non-specific response arises from imprecise control over the type, density, and spatial distribution of surface functional groups, causing premature drug leakage in normal weakly acidic tissues, such as inflammatory sites, and unavoidable off-target toxicity[74,75]. In addition, laboratory-scale synthesis methods, such as microwave-assisted and hydrothermal synthesis, often fail to achieve uniform particle size distribution and controllable surface functionalization, resulting in poor batch-to-batch reproducibility[29]. This poses a major obstacle to large-scale production and standardized preparation of CD materials.
8.2 Challenges of targeted delivery and the tumor microenvironment
Current CD-based targeted delivery systems generally rely on a single-ligand modification strategy, and their targeting efficiency is often compromised by the instability of these ligands in the PDAC microenvironment. Commonly used ligands include HA and RGD peptides. However, the heterogeneous expression of receptors such as CD44 and integrin ανβ3 in PDAC patients leads to inconsistent tumor accumulation and variable therapeutic responses[57]. In addition, ligand conjugation can introduce steric hindrance and alter surface charge, thereby reducing the fluorescence intensity of CDs and possibly triggering immunogenic responses[29]. This potential immunogenicity has been largely overlooked in existing studies.
Notably, the dense fibrous matrix of pancreatic cancer forms a physical barrier that limits the penetration of CDs into deep tumor regions. And it has been suggested that pancreatic lipases may degrade the structure of CDs, thereby reducing the delivery efficiency[83]. Furthermore, CD nanocarriers can only increase the local drug concentration, but still cannot reverse the intrinsic chemotherapy resistance of PDAC. These observations indicate that the current chemotherapeutic drug design only focuses on the targeting of tumor cells, but rarely takes into account the adaptive adjustment of the complex TME in reality; consequently, they cannot overcome the intrinsic chemoresistance of pancreatic cancer or break through the key biological barriers to effective treatment.
8.3 Inadequate biosafety evaluation system
Although CDs are generally considered to possess favorable biocompatibility, the current biosafety evaluation framework for CDs in pancreatic cancer remains incomplete. Most existing studies rely solely on short-term in vitro cytotoxicity assays and short-term in vivo pathological analysis of major organs as evaluation criteria[57,75]. These approaches fail to fully capture the complex in vivo dynamic behaviors and long-term biological effects of nanomaterials, resulting in a critical lack of data needed to support clinical translation. Accordingly, systematic and in-depth mechanistic research is urgently required to address the following biosafety risks.
First, the long-term in vivo metabolic destination of heteroatom-doped CDs is still unclear, particularly when CDs are doped with heavy metals, such as gadolinium or manganese for MRI, to enhance diagnostic functionality. Although doping can significantly improve the physical and chemical properties, the introduction of heavy metal elements may reintroduce toxicity risks similar to those of traditional QDs. Their long-term retention in the body and the potential release of toxic metal ions are also safety concerns that cannot be ignored. For example, it has been shown that among different metal-doped CDs, silver-doped CDs are the most toxic, causing approximately 85% bacterial death and 100% mammalian cell death at a concentration of 10 μg/mL[84].
Second, the distribution and accumulation risk of CDs in the vital organs, particularly the liver, kidney, and spleen, have not been fully evaluated. At present, the in vivo toxicity assessment in most studies is limited to histopathological examination of organ tissue sections, making it difficult to detect obvious lesions within such short observation periods[85]. In a lung cancer study, serological tests revealed increased serum lactate dehydrogenase activity and increased urea levels in some experimental mice, indicating that CDs have caused damage to the liver and kidney. Histopathological analysis further revealed mild renal tubular damage, as evidenced by morphological changes in epithelial cells, accompanied by an inflammatory response[86]. More importantly, repeated daily administration of CDs and their surface modifications (e.g., liposomes or polymers) may result in cumulative toxicity, leading to chronic inflammation or organ damage. Therefore, long-term in vivo toxicology studies are urgently needed.
Third, there has been insufficient attention to the potential immunogenicity of various surface-modified CDs. Currently, efficacy evaluations of CDs in pancreatic cancer and other malignancies are mostly limited to the measurement of tumor cell inhibition rate. Surface modifications such as functional groups, surface charge, and coating materials can fundamentally alter how the immune system recognizes and responds to CDs. For example, cationic polyamino-CDs can be recognized by macrophage scavenger receptors, leading to decreased cell viability and the secretion of proinflammatory cytokines[87]. Although some carbon-based nanomaterials are generally considered to have low immunogenicity, prolonged administration may still induce inflammatory responses, liver and kidney damage, and adverse immune reactions. Given the diversity of surface properties of CDs, immunotoxicity assessment should be performed for each specific formulation. A general conclusion that CDs are universally safe is not warranted.
The current CD biosafety evaluation system in CDs in pancreatic cancer theranostics remains insufficient to support clinical translation. Future studies should include comprehensive long-term in vivo evaluations, including systematic distribution monitoring in major organs, chronic toxicity tests with extended observation periods, and rigorous immunogenicity analysis of different surface modifications. Establishing a standardized biosafety assessment system is essential to bridge the gap between excellent preclinical results and safe clinical translation.
8.4 Technical bottlenecks in clinical translation
At present, the application of CDs in the diagnosis and therapy of pancreatic cancer is still in the preclinical stage. Although existing studies have shown encouraging preclinical results, the clinical translation of CDs still faces multiple systemic obstacles. This challenge is not unique to pancreatic cancer-related CDs; it is a long-standing issue shared by CDs and other nanomaterials in general.
Poor batch-to-batch reproducibility in CD synthesis is the primary technical bottleneck restricting clinical translation. Variations in synthesis methods, including precursor selection, reaction conditions, and post-treatment processes, can result in substantial inconsistencies in the physicochemical and optical properties of different batches of products. Even subtle differences in synthesis conditions can dramatically alter CD performance[88]. This variability not only impedes the accumulation of reliable basic research data but also fails to satisfy regulatory requirements for the consistency of nanomedicine batches. Moreover, inconsistent purification strategies, including dialysis, centrifugation, electrophoresis, and size-exclusion chromatography, further exacerbate batch-to-batch variability[89].
The transformation of the laboratory synthesis process to good manufacturing practice (GMP) scale production faces multiple engineering challenges. The obstacles to large-scale production of CDs, and indeed all nanomaterials, include poor reproducibility of synthesis, high purification cost, energy-intensive, and unresolved regulatory issues[90]. At present, the reported large-scale preparation methods mainly include top-down approaches (laser ablation, electrochemical oxidation, and chemical oxidation) and bottom-up approaches (pyrolysis, hydrothermal/solvothermal synthesis, microwave-assisted synthesis, and template-based synthesis). However, each method has inherent limitations when scaled up[91]. From a GMP perspective, the production of CDs as a novel nano-drug needs to meet a series of stringent requirements, such as the traceability of the source of raw materials, the strict control of key process parameters, the online monitoring of intermediates, and the total quality release of final products. However, the vast majority of CD studies remain at the laboratory synthesis stage and lack systematic investigation of critical quality attributes during process scale-up.
Currently, no CD-based formulation specifically for pancreatic cancer theranostics has entered clinical trials, highlighting a pronounced transition gap between preclinical and clinical stages. To our knowledge, no clinical trial of CD preparation for pancreatic cancer has been reported in the literature. This gap underscores that the path from laboratory discovery to clinical application for CDs remains long and challenging. The intrinsic heterogeneity of pancreatic cancer, the complex TME, and the dense interstitial barrier further increase the difficulty of clinical translation.
In response to the above challenges, future research should focus on the following directions. First, unified synthesis and purification standards should be established. A standardized preparation process would improve data comparability across different laboratories. Second, controllable and scalable production technologies, such as continuous-flow synthesis or process optimization, need to be developed. Third, CD-specific quality control standards should be formulated, which will define acceptable methods and criteria for critical quality attributes including particle size distribution, surface charge, quantum yield, and emission stability[89]. Furthermore, artificial intelligence, particularly machine learning, could be employed to optimize CD design and synthesis, thereby improving product consistency and controllability.
In conclusion, bridging the gap between laboratory research and clinical application requires multidisciplinary collaboration. By systematically addressing these challenges, CDs hold great potential for future clinical translation and biomedical innovation.
9. Summary and Prospect
CDs have demonstrated considerable application potential in pancreatic cancer diagnosis and therapy, owing to their tunable fluorescence properties, favorable biocompatibility, and ease of surface functionalization. This review systematically summarizes the research progress of CDs in pancreatic cancer theranostics. Current studies have shown that CDs can achieve fluorescence imaging of tumor tissues, receptor-mediated active targeting delivery, and pH-triggered drug release both in vitro and in animal models, preliminarily validating their potential to improve the imaging signal-to-noise ratio, enhance tumor accumulation of drugs, and overcome chemotherapy resistance.
Despite these encouraging advances, the practical application of CDs in pancreatic cancer theranostics still faces several fundamental challenges. At the material level, the response windows of existing pH-responsive CDs are generally too broad (pH 4.0-8.0) to precisely match the subtle acidity of the pancreatic cancer microenvironment (pH 6.2-6.8). In addition, although surface modification strategies have enriched the functionality of CDs, the comprehensive effects of multi-ligand modification on particle size, fluorescence performance, and in vivo distribution behavior remain to be systematically evaluated. At the biological level, CD penetration into the dense stroma of pancreatic cancer is limited. Most studies have only validated targeting effects in subcutaneous xenograft models without adequate verification in orthotopic pancreatic cancer models, whose delivery efficiency is often much lower than that of subcutaneous models due to differences in anatomical location, blood supply, and stromal characteristics. From a safety perspective, existing toxicity evaluations are predominantly based on short-term observations, with particularly insufficient data on the long-term accumulation in organs such as the liver and spleen, metabolic fate, and potential immunogenicity of CDs. From a translational perspective, batch-to-batch reproducibility, scalable preparation processes, and quality control standards for CDs have not yet been established, leaving a substantial gap relative to GMP requirements.
In response to the above bottlenecks, future research should prioritize the following directions. First, it is necessary to develop pH-responsive systems with narrower response windows or to introduce multi-responsive mechanisms such as enzyme or temperature responsiveness, thereby improving the activation specificity of CDs in the pancreatic cancer microenvironment. Second, the delivery efficiency and therapeutic efficacy of CDs should be systematically evaluated in orthotopic pancreatic cancer models rather than relying solely on subcutaneous models. Third, long-term in vivo metabolism and immunogenicity evaluation protocols should be established to clarify the organ accumulation and clearance kinetics of CDs. Finally, efforts should be made to promote the standardization and scale-up of CD synthesis processes, laying the groundwork for subsequent clinical translation. Advancing these directions will require multidisciplinary collaboration across materials science, tumor biology, and pharmaceutical engineering. Only by fully recognizing these limitations and systematically accumulating data can CDs be expected to transition from laboratory research to clinical evaluation in pancreatic cancer theranostics.
Acknowledgements
Language editing was helped by ChatGPT-5.4 and Deepseek-V4. Photos are edited by BioGDP. After using this tool/service, the authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
Authors contribution
Zhou H, Zhang Y: Conceptualization, investigation, writing-original draft.
Xi Y: Writing-reviewing & editing, validation, supervision.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
This work was supported by Ningbo Natural Science Foundation (2025J181) and the Keynote Research Project of Ningbo City (2023Z171).
Copyright
© The Author(s) 2026.
References
-
1. Bray F, Laversanne M, Sung H, Ferlay J, Siegel RL, Soerjomataram I, et al. Global cancer statistics 2022: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J Clin. 2024;74(3):229-263.[DOI]
-
3. Stoop TF, Javed AA, Oba A, Koerkamp BG, Seufferlein T, Wilmink JW, et al. Pancreatic cancer. Lancet. 2025;405(10485):1182-1202.[DOI]
-
4. Zeng S, Pöttler M, Lan B, Grützmann R, Pilarsky C, Yang H. Chemoresistance in pancreatic cancer. Int J Mol Sci. 2019;20(18):4504.[DOI]
-
7. Koong AC, Mehta VK, Le QT, Fisher GA, Terris DJ, Brown JM, et al. Pancreatic tumors show high levels of hypoxia. Int J Radiat Oncol. 2000;48(4):919-922.[DOI]
-
17. Silli EK, Li M, Shao Y, Zhang Y, Hou G, Du J, et al. Liposomal nanostructures for Gemcitabine and Paclitaxel delivery in pancreatic cancer. Eur J Pharm Biopharm. 2023;192:13-24.[DOI]
-
21. Behi M, Gholami L, Naficy S, Palomba S, Dehghani F. Carbon dots: A novel platform for biomedical applications. Nanoscale Adv. 2022;4(2):353-376.[DOI]
-
22. Huang W, Zhang J, Xiao J, Zeng L, Li C, Zhou L, et al. Facile synthesis of broadband red-emitting hydrophilic carbon dots for zebrafish imaging application. J Mol Struct. 2025;1335:141991.[DOI]
-
24. Ru Y, Waterhouse GIN, Lu S. Aggregation in carbon dots. Aggregate. 2022;3(6):e269.[DOI]
-
26. Sun X, Xiang T, Xie L, Ren Q, Chang J, Jiang W, et al. Recent advances in fluorescent nanomaterials designed for biomarker detection and imaging. Mater Today Bio. 2025;32:101763.[DOI]
-
27. Gao P, Hui H, Guo C, Liu Y, Su Y, Huang X, et al. Renal clearing carbon dots-based near-infrared fluorescent super-small nanoprobe for renal imaging. Carbon. 2023;201:805-814.[DOI]
-
28. Das A, Snee PT. Synthetic developments of nontoxic quantum dots. ChemPhysChem. 2016;17(5):598-617.[DOI]
-
30. Sun YP, Zhou B, Lin Y, Wang W, Fernando KAS, Pathak P, et al. Quantum-sized carbon dots for bright and colorful photoluminescence. J Am Chem Soc. 2006;128(24):7756-7757.[DOI]
-
31. Liu Y, Wang H, Qu S. Review on near-infrared absorbing/emissive carbon dots: From preparation to multi-functional application. Chin Chemical Lett. 2025;36(5):110618.[DOI]
-
35. Varghese S, Abraham MK, Indongo G, Rajeevan G, Kala ABK, Lekshman A, et al. In vivo imaging of pancreatic cancer in BALB/c mice using erlotinib-conjugated carbon quantum dots derived from 1,4,5,8-tetraminoanthraquinone. Bioconjugate Chem. 2025;36(6):1329-1339.[DOI]
-
36. Cillari R, Riccardi F, Terracina F, Busato D, Canil G, Corona G, et al. NIR-I imaging of indocyanine green-functionalized carbon nanodots in pancreatic adenocarcinoma: Biodistribution, protein corona, and prospects for theranostics. Mater Today Adv. 2026;30:100836.[DOI]
-
44. Angelovski G. What we can really do with bioresponsive MRI contrast agents. Angew Chem Int Ed. 2016;55(25):7038-7046.[DOI]
-
49. Rahmatulla A, Bi X, Wang P, Wang X, Li S, Zhang X, et al. Review of design strategies for active targeted drug delivery systems for pancreatic cancer. Eur J Pharm Biopharm. 2026;218:114915.[DOI]
-
56. Pandey S, Gedda GR, Thakur M, Bhaisare ML, Talib A, Khan MS, et al. Theranostic carbon dots ‘clathrate-like’ nanostructures for targeted photo-chemotherapy and bioimaging of cancer. J Ind Eng Chem. 2017;56:62-73.[DOI]
-
59. Wang H, Tian T, Xu S, Yin Y, Shi H. Targeted multifunctional nano-engineered carbon dots with enhanced synergistic photothermal/photodynamic performance for precision tumor therapy. J Colloid Interface Sci. 2025;700:138351.[DOI]
-
60. Anjali Devi JS, Aparna RS, Anjana RR, Madanan Anju S, George S. Erlotinib conjugated nitrogen doped carbon nanodots for targeted fluorescence imaging of human pancreatic cancer cells. ChemistrySelect. 2020;5(29):9269-9276.[DOI]
-
61. Khan MS, Alqahtani T, Al Shmrany H, Gupta G, Goh KW, Sahebkar A, et al. Enhanced permeability and retention (EPR) effect: Advances in nanomedicine for improved tumor targeting. Biomater Adv. 2026;181:214636.[DOI]
-
63. Girma WM, Mekuria SL, Gedda G, Xiangyang S, Park YJ, Pang MG. Carbon dot-based nanohybrids for tumor microenvironment-activated cancer theranostics. Coord Chem Rev. 2026;548:217236.[DOI]
-
66. Bao X, Yuan Y, Chen J, Zhang B, Li D, Zhou D, et al. In vivo theranostics with near-infrared-emitting carbon dots: Highly efficient photothermal therapy based on passive targeting after intravenous administration. Light Sci Appl. 2018;7(1):91.[DOI]
-
67. Yu H, Luo KS, Zhu Y, Chen T, Chen ZY, Feng TT, et al. Preparation of Chinese medicine Ganoderma lucidum carbon dots and their application photodynamic/photothermal therapy for pancreatic cancer in vitro. Acta Pharmaceutica Sinica. 2025;60(11):3518-3526.[DOI]
-
69. van der Horst A, Versteijne E, Besselink MGH, Daams JG, Bulle EB, Bijlsma MF, et al. The clinical benefit of hyperthermia in pancreatic cancer: A systematic review. Int J Hyperth. 2018;34(7):969-979.[DOI]
-
70. Shen Y, Zhang X, Liang L, Yue J, Huang D, Xu W, et al. Mitochondria-targeting supra-carbon dots: Enhanced photothermal therapy selective to cancer cells and their hyperthermia molecular actions. Carbon. 2020;156:558-567.[DOI]
-
71. Dong Y, Shao J, Chen C, Li H, Wang R, Chi Y, et al. Blue luminescent graphene quantum dots and graphene oxide prepared by tuning the carbonization degree of citric acid. Carbon. 2012;50(12):4738-4743.[DOI]
-
73. Namdari P, Negahdari B, Eatemadi A. Synthesis, properties and biomedical applications of carbon-based quantum dots: An updated review. Biomed Pharmacother. 2017;87:209-222.[DOI]
-
75. Seo J, Lee J, Bin Lee C, Bae SK, Kun N. Nonpolymeric pH-sensitive carbon dots for treatment of tumor. Bioconjugate Chem. 2019;30(3):621-632.[DOI]
-
77. Kirubanithy K, Santhanam A. A pH-responsive nanocarrier of peanut shell carbon quantum dots as a promising delivery of doxorubicin for cancer therapy. Sci Rep. 2025;15(1):33885.[DOI]
-
78. Cillari R, Sciortino A, Scirè S, Cannas M, Messina F, Mauro N. Fluorescence switching in pH-responsive poly(amidoamine) hydrogel networks containing gold nanoparticles and carbon nanodots for potential real-time tumor pH monitoring. ACS Appl Opt Mater. 2025;3(7):1628-1636.[DOI]
-
81. Li J, Feng X, Jiang H, Mo X, Liu C, Liu X, et al. Near-infrared and pH-responsive carbon dots/bergenin for biological imaging and chemo-photothermal synergistic tumor therapy. J Colloid Interface Sci. 2025;694:137679.[DOI]
-
83. Srivastava I, Sar D, Mukherjee P, Schwartz-Duval AS, Huang Z, Jaramillo C, et al. Enzyme-catalysed biodegradation of carbon dots follows sequential oxidation in a time dependent manner. Nanoscale. 2019;11(17):8226-8236.[DOI]
-
84. Mishra J, Suryawanshi T, Redkar N, Kumar Das R, Saxena S, Majumder A, et al. Toxicological effects of metal-doped carbon quantum dots. ChemSusChem. 2025;18(10):e202402056.[DOI]
-
85. Zhang S, Pei X, Xue Y, Xiong J, Wang J. Bio-safety assessment of carbon quantum dots, N-doped and folic acid modified carbon quantum dots: A systemic comparison. Chin Chem Lett. 2020;31(6):1654-1659.[DOI]
-
88. Jing HH, Adnan M, Patel M, Sasidharan S. Reproducibility roadblocks and standardization in carbon dot synthesis: A critical review of current practices, challenges, and future directions. Microchim Acta. 2025;192(12):835.[DOI]
-
89. Tumallah HM, Sasidharan S. Next-generation green carbon dots: Toward standardized synthesis and purification for translational nanomedicine—A comprehensive review. J Inorg Organomet Polym Mater. 2026.[DOI]
-
90. Bartkowski M, Calzaferri F, Giordani S. Toward clinical translation of carbon nanomaterials in anticancer drug delivery: The need for standardisation. Beilstein J Nanotechnol. 2025;16:2092-2104.[DOI]
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Zhou H, Zhang Y, Xi Y. Advancements in carbon dots for targeted treatment of pancreatic cancer. Ageing Cancer Res Treat. 2027;4:202611. https://doi.org/10.70401/acrt.2026.0043
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Physicochemical Properties and Diagnostic Potential of Carbon Dots
- 3. Application of Carbon Dots in Pancreatic Cancer Imaging
- 4. Carbon Dot-Mediated Targeted Drug Delivery Systems for Pancreatic Cancer
- 5. Applications of Carbon Dots in Hyperthermia Therapy for Pancreatic Cancer
- 6. Research Progress on pH-Responsive Carbon Dots in Pancreatic Cancer Therapy
- 7. Integrated Imaging and Therapy Applications of Carbon Dots
- 8. Limitations of the Current Study
- 9. Summary and Prospect
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Zhou H, Zhang Y, Xi Y. Advancements in carbon dots for targeted treatment of pancreatic cancer. Ageing Cancer Res Treat. 2027;4:202611. https://doi.org/10.70401/acrt.2026.0043
copy
Share Link
copy