Selective preservation of immune competence in human longevity: Youth-like cellular features and molecular support programs

Xia-Yan Wang
1,2,#
,
Fan-Qian Yin
1,#
,
Qing-Peng Kong
1,3,*

*Correspondence to:
Qing-Peng Kong, State Key Laboratory of Genetic Evolution and Animal Models, Key Laboratory of Healthy Aging Research of Yunnan Province, Kunming Key Laboratory of Healthy Aging Study, KIZ/CUHK Joint Laboratory of Bioresources and Molecular Research, Kunming Institute of Zoology, Chinese Academy of Sciences, Kunming 650201, Yunnan, China; CAS Center for Excellence in Animal Evolution and Genetics, Chinese Academy of Sciences, Kunming 650201, Yunnan, China.
E-mail: kongqp@mail.kiz.ac.cn
Ageing Cancer Res Treat. 2027;4:202632. 10.70401/acrt.2026.0044
Received: July 01, 2026Accepted: September 24, 2026Published: September 29, 2026
Abstract
Advanced age is associated with immune decline and remodeling, including loss of adaptive reserve, impaired host defense, and chronic low-grade inflammation. Yet the immune phenotype of long-lived individuals (LLIs), especially centenarians, shows that immune aging is not a uniform process. Rather than reflecting global rejuvenation, longevity-associated immunity is better understood as selective preservation of immune competence, with selected cellular features retaining youth-like characteristics under the constraints of extreme age. The most direct cellular evidence comes from innate effector functions, including preserved natural killer (NK)-cell cytotoxic surveillance and neutrophil chemotaxis, phagocytosis, and redox control. T-cell findings are more heterogeneous, including maintenance of a non-inverted CD4/CD8 ratio and partial naive CD4+ T-cell reserve, while T helper 17 cell (Th17)/regulatory T cell (Treg) data provide more limited support for preserved regulatory-inflammatory balance. Myeloid and antigen-presenting-cell programs may further support clearance and antigen handling, although direct functional evidence remains more limited. Molecular studies point to candidate support layers rather than proven causal mechanisms, including coordinated immune-cell states and communication, survival and apoptosis-regulatory programs, ribosome-inflammation balance, autophagy-lysosomal and mitochondrial quality control, and buffering of inflammatory and senescence-associated signals. Importantly, some immune changes reported in LLIs fall outside the youth-like frame: cytotoxic and effector-memory T-cell states and repertoire remodeling, humoral shifts, and complement changes are better interpreted as adaptive remodeling whose occurrence and significance depend on lifelong immunological experience. This framework places selective preservation of immune competence at the center of LLI immune biology while distinguishing it from experience-shaped adaptive remodeling.
Keywords
Centenarians, long-lived individuals, immunosenescence, youth-like immune features, inflammaging, immune remodeling, autophagy, single-cell transcriptomics
1. Introduction
Population aging has made the prevention of late-life multimorbidity, frailty, and functional decline a central challenge for modern medicine[1-3]. Chronological aging is a dominant driver of chronic disease burden and multimorbidity, which in turn contributes to disability and health-care utilization[4]. Exceptionally long-lived individuals (LLIs), including centenarians, therefore represent an informative exception to this trajectory. Rather than simply surviving with a heavy disease burden, LLIs appear to delay and compress morbidity and disability into later life: the Danish 1905 birth cohort showed lower hospitalization rates and shorter cumulative hospital stays among individuals who eventually reached 100 years[5], and successive cohorts of Danish centenarians have further exhibited improved activities of daily living[6]. Nationwide registry-based analyses in Sweden reported slower disease accumulation, fewer co-occurring conditions, and a more favorable distribution of age-related morbidity among centenarians[7,8]. Evidence from a Chinese oldest-old cohort further indicates that lifestyle and morbidity-related factors remain closely associated with survival at advanced ages[9].
The immune system is a plausible contributor to this exception because it coordinates host defense, immune surveillance, tissue repair, immune tolerance, and chronic inflammatory disease[10-12]. Classical frameworks of immunosenescence and inflammaging emphasize impaired responses to new antigens, reduced vaccine efficacy, diminished pathogen control, and chronic inflammatory tissue damage in old age[13-15]. These models help explain major components of late-life morbidity, including the high burden of respiratory infections and severe COVID-19 in advanced age[16,17]. Yet they do not fully account for the heterogeneity of immune outcomes among the oldest-old. LLIs remain vulnerable to severe infections, particularly in frail or multimorbid settings[18], but selected cohorts of nonagenarians, centenarians, and supercentenarians have shown mild or asymptomatic severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection, recovery after documented infection, detectable or robust neutralizing antibody responses after infection or vaccination, and, in one centenarian serological cohort, long-lived humoral memory to historical influenza exposure[19-21].
This heterogeneity suggests that LLI immunity is neither globally rejuvenated nor simply the oldest extension of conventional immune decline. Building on recent comprehensive overviews of centenarian immunity[22], the present Review focuses on how the available evidence should be interpreted. We distinguish youth-like maintenance from partial preservation, evidence-limited support, and non-youth-like adaptive remodeling, while considering the strength of the supporting evidence and the limits of mechanistic inference. This distinction matters because these patterns need not reflect the same underlying biology.
Within this framework, selective preservation of immune competence remains the central focus, with youth-like maintenance representing its most strongly supported form. The strongest evidence comes from preserved innate effector function, particularly natural killer (NK)-cell cytotoxic surveillance and neutrophil chemotaxis and phagocytosis. T-cell evidence is more heterogeneous, but supports maintenance of CD4/CD8 homeostatic balance and partial preservation of naive CD4+ T-cell reserve. Regulatory-inflammatory balance is also suggested, although direct evidence remains more limited. Adaptive remodeling is considered separately in the context of immunobiography because lifelong antigenic and environmental exposures can shape immune trajectories and contribute to the marked heterogeneity among LLIs. We then examine candidate molecular programs that may support these preserved functions, while distinguishing associative human findings and model-based evidence from mechanisms demonstrated directly in LLI immune cells.
2. Comparative Immune Landscape and Interpretive Framework
LLIs, including centenarians and supercentenarians, show mixed patterns of immune features: some immune functions remain close to young-adult states, some are only partly preserved, and others are clearly remodeled by lifelong antigen exposure. To provide a framework for the following sections, we summarize and organize these immune features in Figure 1 and Table 1 according to evidence strength and biological interpretation.
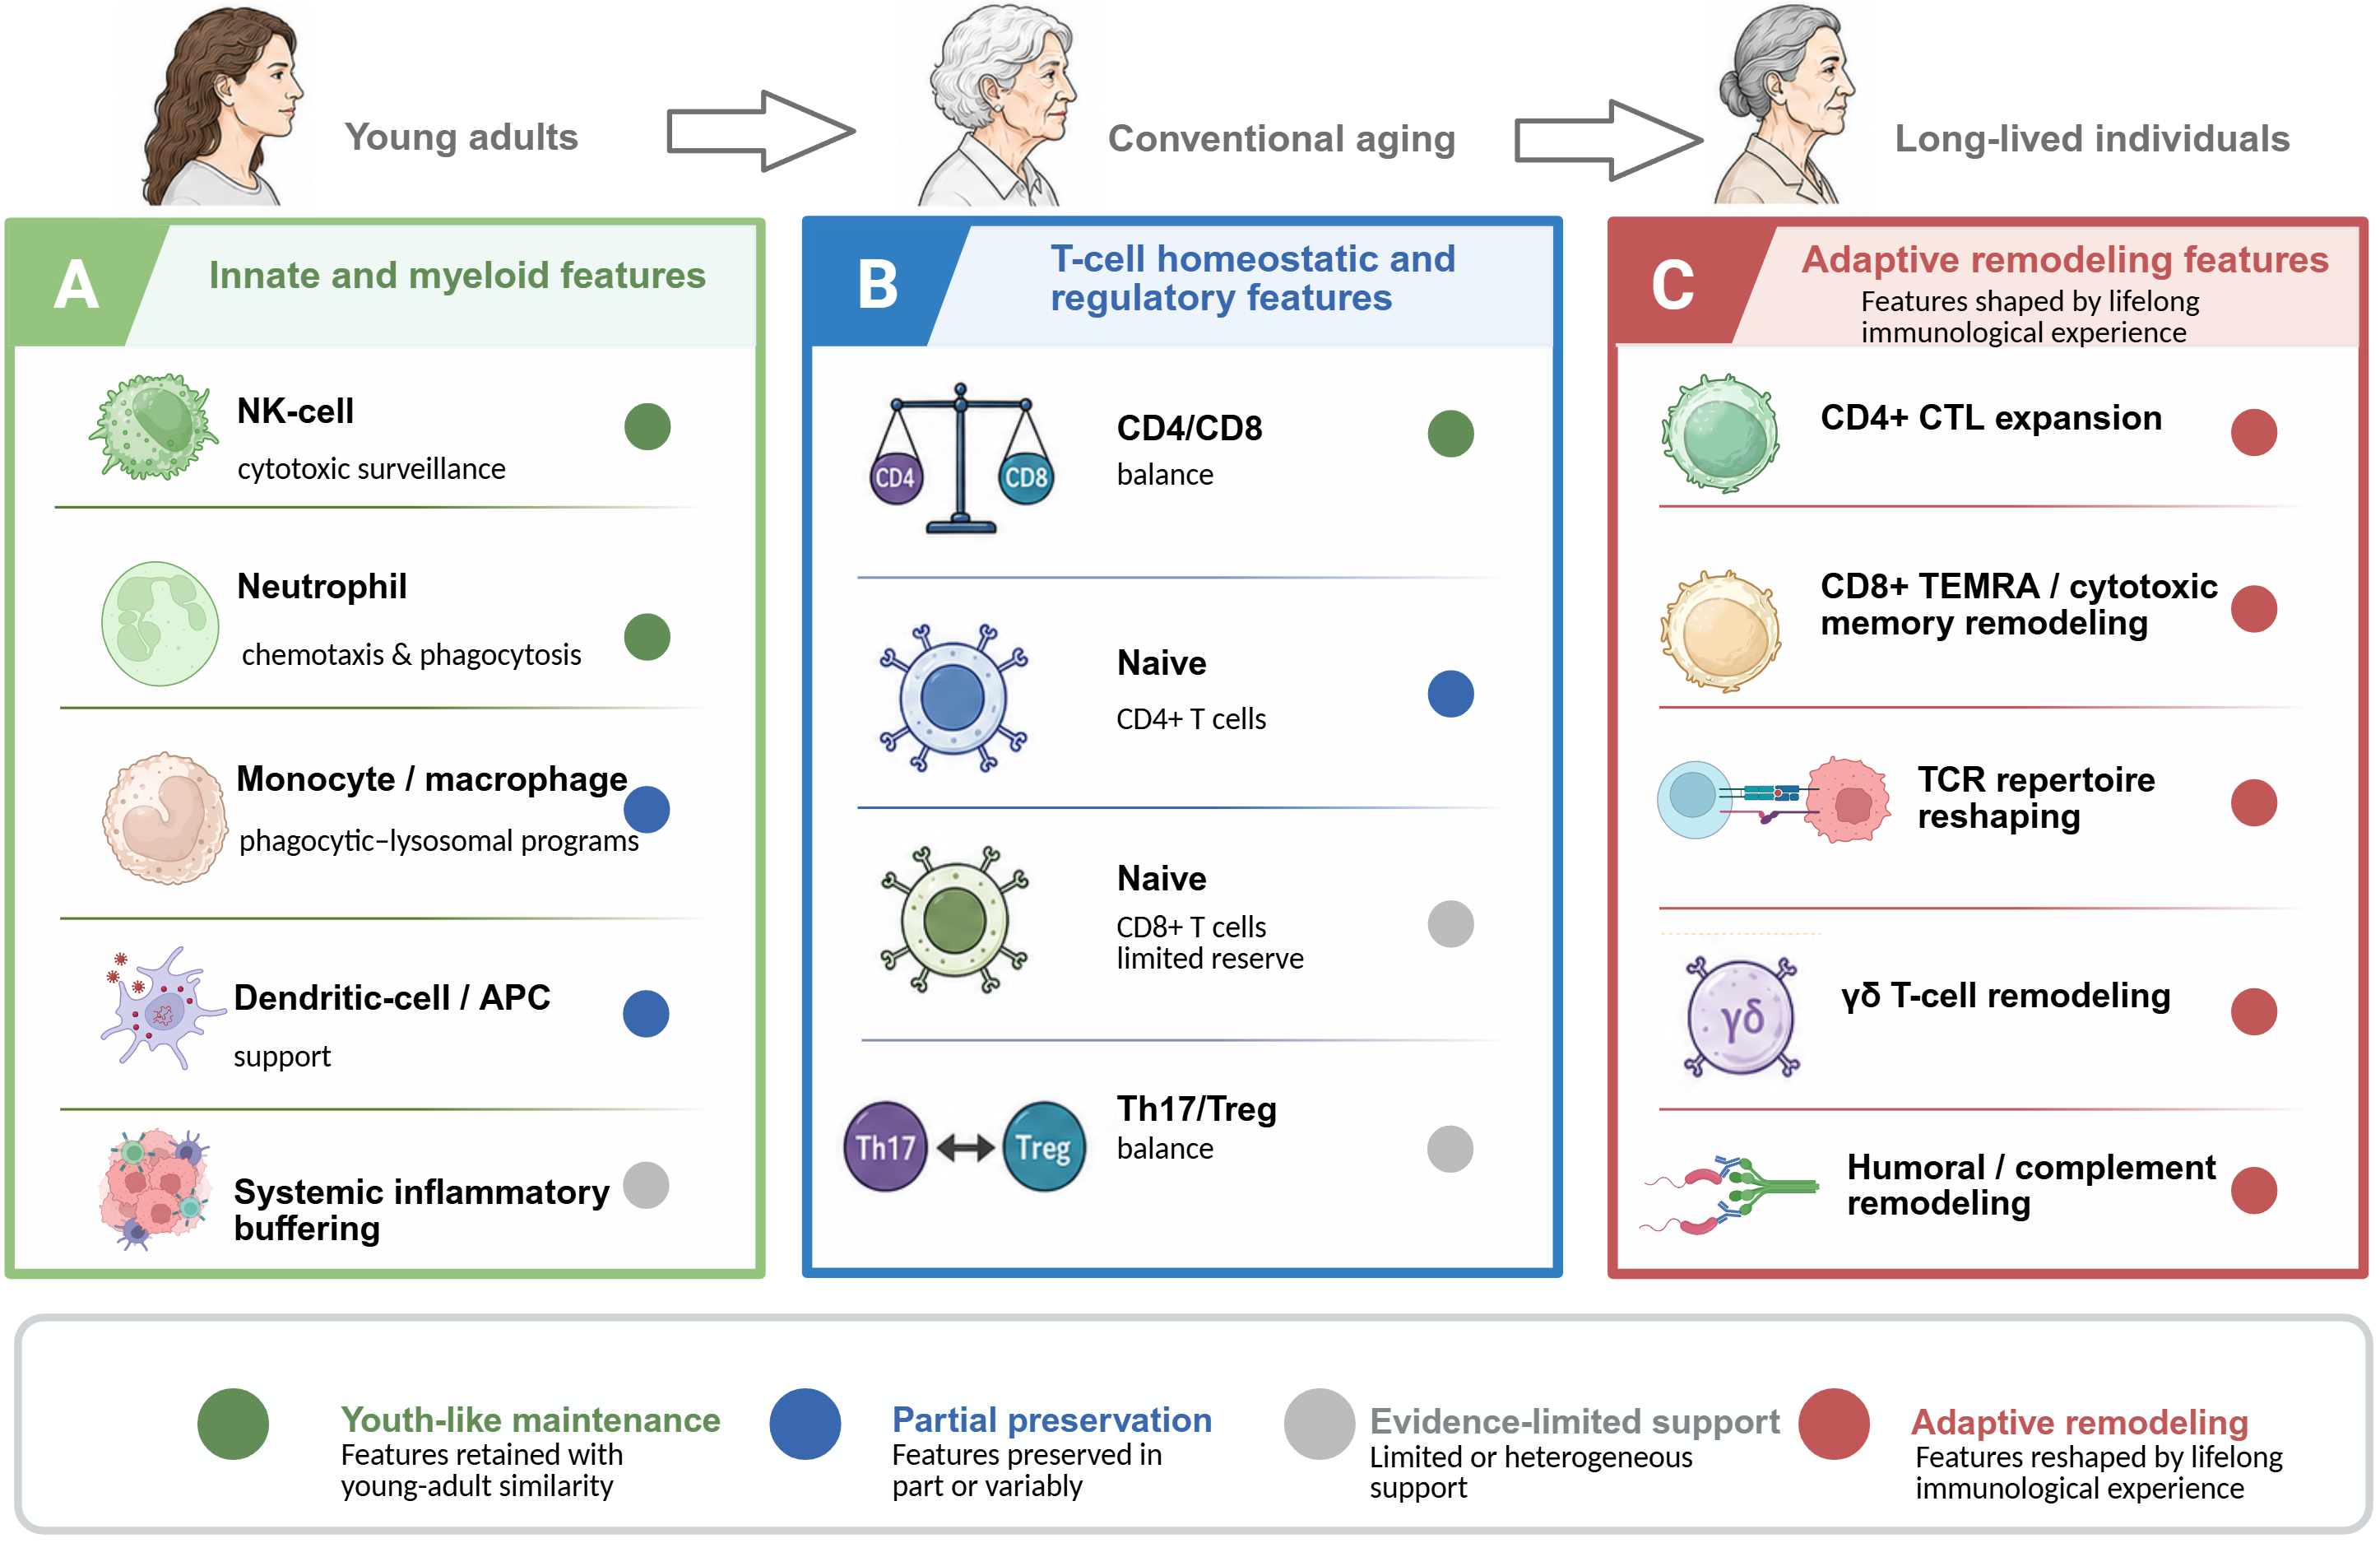
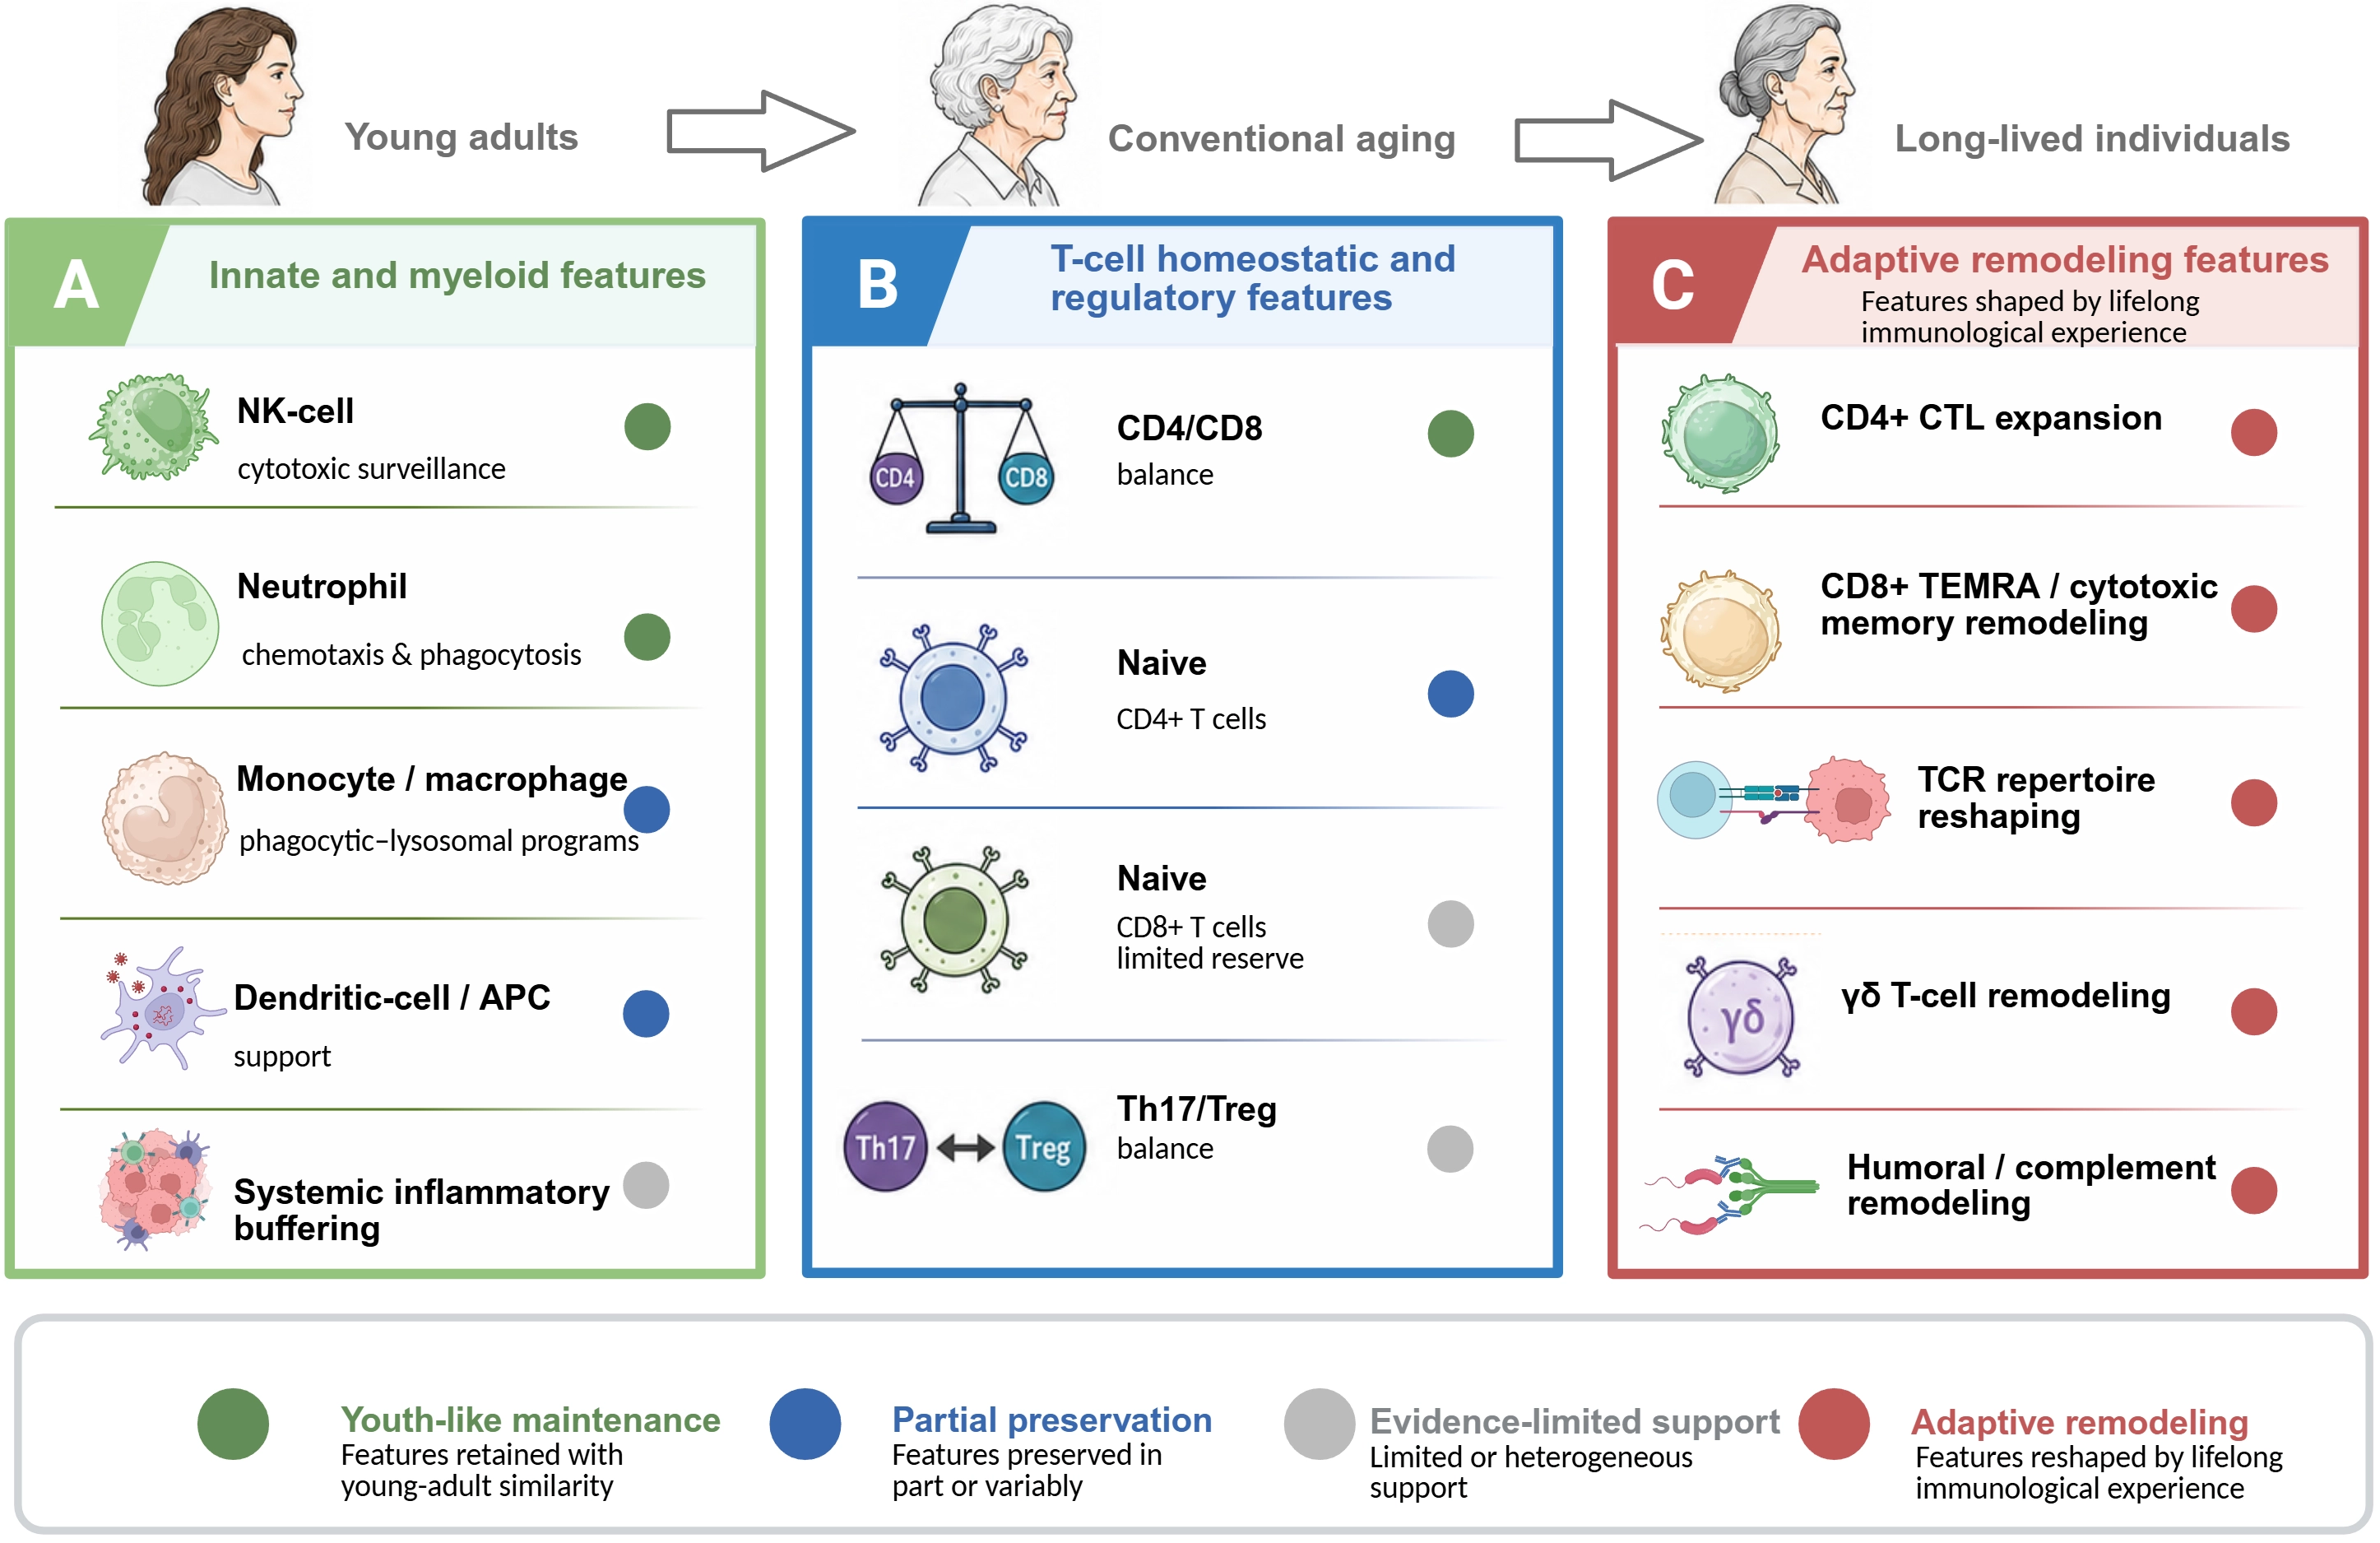
Figure 1. Comparative immune landscape and interpretive framework in human longevity. Representative immune-cell and functional features in LLIs are organized according to their relationship to young-adult immune patterns and the strength of the available evidence. Innate and myeloid features, T-cell homeostatic and regulatory features, and adaptive remodeling features are shown separately. Green indicates youth-like maintenance supported by comparatively consistent evidence; blue indicates partial preservation; gray indicates evidence-limited support based on limited, indirect, or heterogeneous findings; and red indicates adaptive remodeling shaped by lifelong immunological experience rather than preservation of a young-adult state. LLIs: long-lived individuals; APC: antigen-presenting cell; CTL: cytotoxic T lymphocyte; NK: natural killer; TCR: T-cell receptor; TEMRA: terminally differentiated effector memory T cell re-expressing CD45RA; Treg: regulatory T cell.
Table 1. Key immune features in LLIs: evidence strength, interpretation, and potential translational relevance
| Feature/program | Key LLI evidence | Interpretive boundary | Potential translational relevance |
| NK-cell cytotoxic surveillance | Preserved NK-cell cytotoxic activity has been reported in selected centenarian cohorts, together with increased NK-cell abundance/IFN-γ-producing capacity and relatively youth-like NK molecular signatures; reduced cell-intrinsic cytotoxicity has also been observed in one cohort[23-27]. | Youth-like maintenance—convergent functional and molecular evidence, but not uniform across cohorts. | Antiviral and antitumor surveillance; clearance of damaged or senescent cells. |
| Neutrophil chemotaxis and phagocytosis | Spanish centenarians showed youth-like chemotaxis, phagocytosis, and redox control, while a Japanese cohort showed enhanced granulocyte phagocytosis with reduced superoxide output[27,28]. | Youth-like maintenance—replicated direct functional evidence for chemotaxis, phagocytosis, and redox control. | Antimicrobial defense with limited oxidative tissue injury. |
| CD4/CD8 balance | Maintenance of a non-inverted CD4/CD8 ratio was associated with survival to extreme age; higher ratios also predicted lower mortality, although inversion remains present in a substantial subset of centenarians[29-32]. | Youth-like homeostatic maintenance—survival-associated but not universal; does not imply T-cell rejuvenation. | Immune-risk stratification and interpretation of late-life vaccine or immunotherapy responses. |
| Naive CD4+ T-cell reserve | Residual naive CD4+ populations remain detectable in centenarians despite marked contraction, with depletion less severe than that of naive CD8+ T cells[33-35]. | Partial preservation—incomplete maintenance in the naive CD4+ compartment, not thymic rejuvenation. | Immune reserve, B-cell help, CD8+ priming, and novel-antigen responses. |
| Naive CD8+ T-cell reserve | Severe depletion of circulating naive CD8+ T cells is common, whereas higher-than-expected frequencies relative to modeled aging trajectories occur in selected supercentenarians[33,35-37]. | Evidence-limited support—selected relative preservation against a background of marked naive-CD8 depletion. | Responses to novel viral or tumor antigens. |
| Th17/Treg regulatory-inflammatory balance | One Chinese cohort reported a lower Th17/Treg ratio and ex vivo secretory profiles consistent with inflammatory restraint[38]. | Evidence-limited support—direct cellular and ex vivo evidence derives from a small subset and lacks independent LLI replication. | Inflammatory restraint and regulatory-inflammatory balance. |
| Myeloid and APC support | Myeloid subset proportions show modest or inconsistent changes across LLI cohorts, whereas single-cell and multi-omic studies consistently identify HLA/MHC-II-associated, cytokine/antimicrobial, lysosomal, and phagocytosis-related molecular programs[25,39-41]. | Partial preservation—molecular evidence is stronger than cellular-composition or direct functional evidence. | Clearance, antigen handling, and coordination with lymphocyte responses. |
| CD4+ cytotoxic T-cell expansion | Clonally expanded granzyme/perforin-expressing CD4+ CTLs have been reported in supercentenarians and other centenarian cohorts[42-44]. | Adaptive remodeling—an antigen-experienced, non-youth-like T-cell state. | Potential late-life antiviral and antitumor surveillance; context dependent. |
| CD8+ cytotoxic memory/TEMRA and repertoire remodeling | Cytotoxic CD8+ states and increased TCR clonality occur in some cohorts, whereas naive/TEMRA distributions show marked inter-individual heterogeneity, including among CMV-seropositive LLIs[36,42]. | Adaptive remodeling—heterogeneous and strongly shaped by chronic antigen exposure and immunobiographic context. | Antigen-experienced surveillance, with possible costs to novel-antigen responses and inflammatory control. |
| B-cell and humoral remodeling | Altered B-cell composition coexists with persistent antibody responses to selected viral exposures, including SARS-CoV-2 and historical H1N1 influenza[19-22,25]. | Adaptive remodeling—preserved antigen-experienced humoral memory rather than broad maintenance of a youthful B-cell compartment. | Vaccine responsiveness and long-lived humoral memory. |
LLIs: long-lived individuals; NK: natural killer; IFN: interferon; CD4: cluster of differentiation 4; CD8: cluster of differentiation 8; Treg: regulatory T cell; APC: antigen-presenting cell; HLA: human leukocyte antigen; CTL: cytotoxic T lymphocyte; TEMRA: terminally differentiated effector memory T cell re-expressing CD45RA; TCR: T-cell receptor; SARS-CoV-2: severe acute respiratory syndrome coronavirus 2; H1N1: influenza A virus subtype H1N1; MHC-II, major histocompatibility complex class II; CMV: cytomegalovirus.
To clarify this classification, we considered both the extent to which individual immune features in LLIs resemble young-adult patterns and the consistency and directness of the supporting evidence. Relevant evidence included cellular abundance, phenotype, molecular signatures, and functional readouts, where available. Youth-like maintenance refers to features that remain comparatively close to young-adult states, whereas partial preservation denotes incomplete or compartment-specific maintenance. Evidence-limited support is used when preservation is suggested, but the available evidence remains too limited, indirect, or heterogeneous to support a stronger interpretation. Adaptive remodeling refers to non-youth-like immune configurations that are more consistent with lifelong antigen exposure, clonal selection, or compensatory adaptation. Figure 1 provides an overview of these categories, whereas Table 1 summarizes the key LLI evidence and interpretive boundaries underlying the classification of individual features.
Among the cellular features reviewed, youth-like maintenance is most consistently supported for innate effector functions, particularly neutrophil chemotaxis and phagocytosis and NK-cell cytotoxic surveillance, which are supported by direct functional evidence in selected cohorts and by later review-level syntheses[23,24,28]. Recent single-cell and cytometry-based studies further support youth-like NK transcriptional/protein signatures and RUNX3-associated cytotoxic programs[25], while increased NK-cell proportions may partially compensate for declining per-cell cytotoxicity in some cohorts[26]. T-cell findings are more heterogeneous: avoidance of CD4/CD8 inversion has been associated with survival to extreme age in longitudinal cohorts[29-31], although this pattern is not uniform across LLI populations[32], whereas true naive T-cell preservation is limited and compartment-specific, with centenarian studies showing severe overall naive T-cell contraction but residual naive-like CD4+ features in selected cohorts[33-35], and general aging studies providing mechanistic context for CD4+ naive T-cell homeostasis[45]. Regulatory-inflammatory balance is also suggested, although direct evidence remains more limited. Myeloid and antigen-presenting-cell (APC) programs[22,25], cytotoxic T-cell remodeling[42-44], B-cell shifts and repertoire changes, and complement regulation are also important, but these features are better interpreted as partial preservation or adaptive remodeling rather than straightforward youth-like maintenance[46].
A key interpretive boundary concerns adaptive remodeling, which may reflect cumulative immunological experience rather than preservation of a young-adult state. This life-course history, often termed immunobiography, includes the intensity and timing of antigenic exposures and is shaped by persistent infections, vaccination, and environmental or host-specific factors[47]. Cytomegalovirus (CMV) is particularly relevant to late-life T-cell differentiation, but operates within this broader exposure history.
Cytotoxic T-cell states and repertoire remodeling illustrate this point. A Chinese scRNA-seq and T-cell receptor (TCR)-sequencing study reported enrichment of granzyme B (GZMB+) and CMC1+ CD8+ T-cell states and increased TCR clonality in centenarians[42]. However, a cytometric study of semi- and supercentenarians showed marked inter-individual variation in naive and terminally differentiated effector memory T cell re-expressing CD45RA (TEMRA) CD8+ T-cell distributions, including among CMV-seropositive individuals[36], whereas a single-cell aging-clock analysis identified higher-than-expected naive CD8+ and lower-than-expected cytotoxic CD8+ T-cell proportions relative to model-predicted aging trajectories[37]. Late-differentiated CD8+ and TEMRA populations are also strongly associated with CMV exposure in older adults[48]. These observations support a heterogeneous, experience-shaped interpretation of CD8+ remodeling rather than a uniform phenotype of exceptional longevity.
Other adaptive features show similar dependence on immune history. Sicilian LLIs showed expansion of Vδ1+ TEMRA cells correlated with CD8+ TEMRA frequencies, although universal CMV seropositivity and the absence of subset-specific functional assays limit interpretation of this finding[49]. Humoral immunity likewise does not retain a uniformly youthful B-cell architecture, yet selected antigen-experienced responses can persist. Lower serum immunoglobulin M (IgM) was associated with increased mortality in Chinese centenarians[50], while antibody responses to previously encountered viral antigens, including historical H1N1 influenza and SARS-CoV-2, remained detectable in centenarian cohorts[19-21]. Complement-associated proteins have also been reported in LLI blood signatures[22,46], although their functional significance remains uncertain. The following section therefore focuses on cellular features for which the available evidence more directly supports selective preservation of immune competence.
3. Youth-Like Cellular Immune Features in Long-Lived Individuals
LLI immunity is not a preserved young-adult immune state. After a century of thymic involution, antigen exposure, clonal selection, tissue damage, and inflammatory stress, extensive immune aging is unavoidable. The key feature is that selected immune activities remain comparatively preserved at an age when conventional immunosenescence predicts broad functional erosion. In this Review, “youth-like” is used in this functional sense: a feature is considered youth-like when it remains closer to young-adult patterns than to the usual trajectory of older adults, or when its age-related decline appears delayed, buffered, or partially compensated. The strongest cellular evidence is concentrated in innate effector function and T-cell homeostatic balance. Regulatory-inflammatory findings remain evidence-limited, whereas myeloid and antigen-presenting-cell programs provide partial, predominantly molecular support.
3.1 Innate effector function: NK cells and neutrophils
Innate effector function provides a useful entry point for defining youth-like immune maintenance in LLIs. This is biologically significant: immediate defense against infected, malignant, and damaged cells remains useful even when thymic output and naive lymphocyte pools have declined. In conventional aging, innate immunity often becomes uncoupled—cell numbers may be preserved or increased while chemotaxis, cytotoxicity, phagocytosis, or redox control decline[51,52]. LLIs show a different pattern. Rather than simply displaying more innate immune cells, they appear to retain selected effector functions that are usually compromised in advanced age.
The relevant phenotype is not higher inflammatory activation. It is controlled effector function: preserved killing and clearance capacity with restrained inflammatory or oxidative toxicity. This distinction has direct implications for cancer immunosurveillance, as uncontrolled inflammatory activation can paradoxically promote tumor progression through chronic tissue damage and pro-tumorigenic cytokine environments[12,14].
NK-cell cytotoxic surveillance: NK cells provide cytotoxic surveillance against infected and malignant cells through perforin/granzyme-mediated killing, cytokine secretion, and crosstalk with other lymphocytes. Aging can increase total NK-cell numbers but reduce functional coordination through changes in subset composition, receptor balance, and killing efficiency[53-55]. NK-cell abundance alone is therefore not evidence of immune preservation. The key question is whether expanded or retained NK populations still perform surveillance functions without becoming part of a dysregulated inflammatory state. Several centenarian studies support this view. Earlier centenarian studies provided direct functional evidence that NK-cell cytotoxic activity against K562 target cells can remain preserved in selected cohorts[23]. Separately, Japanese centenarian data showed increased NK-cell abundance and higher proportions of interferon (IFN)-γ-producing NK and NKT cells, accompanied by higher circulating IFN-γ[27]. However, reduced cell-intrinsic NK cytotoxicity despite increased NK-cell proportions has also been reported in another centenarian cohort[26], indicating that preservation is not uniform across individuals or studies. Recent multi-cohort single-cell and cytometric studies provide complementary molecular and phenotypic support. A multi-cohort analysis integrating Chinese and Japanese centenarians identified increased NK-cell proportions, youth-like transcriptional and protein signatures, RUNX3-associated cytotoxic programs, and higher frequencies of stimulated granzyme B-positive NK cells[25]. The same work inferred stronger NK-T-cell communication through major histocompatibility complex class I (MHC-I), CD99, and macrophage migration inhibitory factor (MIF)-related pathways[25]. These findings are consistent with preserved NK cytotoxic competence, although they should be distinguished from direct target-cell-killing assays.
Neutrophil chemotaxis and phagocytosis: Neutrophils provide an equally important functional anchor. In conventional aging, neutrophil function often becomes dissociated: directional migration and phagocytosis decline, whereas adhesion, basal activation, and reactive oxygen species generation may increase[51,52]. This pattern weakens antimicrobial clearance while amplifying inflammatory tissue injury. Neutrophils from centenarian cohorts show a more favorable configuration. Japanese studies reported higher granulocyte numbers, enhanced phagocytic activity and cytokine production, and reduced superoxide generation in centenarians[27]. Spanish centenarians displayed chemotaxis and phagocytosis closer to young adults than to conventionally aged controls, together with preserved glutathione levels and high catalase activity[28]. These findings suggest that LLIs may retain an optimized first-line defense state: efficient recruitment and microbial uptake are preserved, while antioxidant buffering and restrained superoxide output reduce collateral damage.
The neutrophil phenotype should therefore be described as optimized effector function rather than generalized activation. It suggests that LLIs may preserve a form of innate immunity that clears microbes, damaged cells, and debris more efficiently while reducing secondary inflammatory amplification. When considered together, NK cells and neutrophils define a preserved innate effector axis in extreme longevity. Among all candidate youth-like cellular features, this axis has the strongest convergence of functional evidence, biological plausibility, and relevance to infection control and tumor surveillance.
3.2 T-cell homeostatic balance: CD4/CD8 ratio and partial preservation of naive CD4+ T cells
T cells show deeper remodeling than innate effectors. Thymic involution limits new T-cell output; chronic viral exposure drives memory and effector differentiation; and CMV can promote expansion of differentiated CD8+CD28- and CD57+ populations[30,48]. LLIs do not escape this process. Many have low thymic output, reduced recent thymic emigrants, and contracted naive T-cell pools[22,33,42]. The youth-like component of their T-cell system therefore lies less in broad T-cell rejuvenation than in preservation of homeostatic structure.
CD4/CD8 ratio: The CD4/CD8 ratio is a simple but informative system-level index. In very old individuals, an inverted CD4/CD8 ratio below one is a defining component of the immune-risk phenotype, together with high CD8+ T-cell percentages, low CD4+ T-cell percentages, impaired proliferative responses, and CMV seropositivity[29,30]. Swedish longitudinal studies linked this immune-risk profile to increased mortality, whereas individuals who reached 100 years often avoided it[29,31]. This pattern is not universal, however: nearly 40% of centenarians in a Cuban cohort had an inverted CD4/CD8 ratio, although a higher ratio was associated with lower mortality during subsequent follow-up[32]. Japanese extreme-longevity cohorts further support the broader link between inflammatory and immunosenescence-related profiles and survival, physical function, and cognition[22,56]. A non-inverted CD4/CD8 ratio should not be mistaken for a young T-cell system. It does not imply intact thymic output, broad naive T-cell preservation, or absence of clonal expansion. Its value is different: it indicates that the T-cell compartment has avoided collapse into a high-risk configuration. In this sense, CD4/CD8 balance captures a form of homeostatic youth-likeness. It integrates CD4+ maintenance, CD8+ expansion, chronic viral exposure, sex, inflammatory state, and survivor selection into a single architectural readout. For LLIs, maintaining this balance may be more important than retaining any single T-cell subset at young-adult levels.
Naive T-cell preservation: Naive CD4+ and CD8+ T cells both decline with age, but the kinetics differ. Naive CD4+ T cells also undergo marked age-related contraction, but their depletion is generally less severe than that of naive CD8+ T cells[33,35]. In centenarians, residual naive CD4+ populations therefore support partial rather than complete preservation of this compartment[33-35]. Residual naive CD4+ T cells may remain functionally meaningful by supporting B-cell help, CD8+ priming, and responses to new antigens. Naive CD8+ T cells are less robustly preserved. Fagnoni and colleagues showed severe age-related depletion of naive CD8+ T cells, with very low levels in the oldest individuals[35]. Nasi and colleagues reported that most centenarians had undetectable T-cell receptor excision circles and extremely low naive T-cell numbers, indicating minimal thymic output[33]. Some single-cell analyses reported higher-than-expected naive CD8+ T-cell frequencies in selected supercentenarians relative to model-predicted aging trajectories[37], whereas other LLI cohorts show pronounced cytotoxic, effector-memory, or TEMRA remodeling[22,36,42]. Rather than defining a single dominant CD8+ phenotype of extreme longevity, these contrasting observations indicate substantial inter-individual and cohort-level heterogeneity. Late-differentiated CD8+ states should therefore be interpreted in relation to chronic antigen exposure, CMV status, and broader immunobiographic context, while recognizing that their relative contributions cannot be disentangled in most LLI cohorts.
The T-cell phenotype of LLIs is therefore best viewed as heterogeneous rather than uniformly preserved or remodeled. Relative preservation is most evident at the level of homeostatic structure, particularly avoidance of CD4/CD8 inversion and partial maintenance of the naive CD4+ T-cell reserve, whereas CD8+ memory, cytotoxic, and repertoire states vary substantially across individuals and studies. Exceptional longevity may therefore coexist with different T-cell configurations rather than require a single CD8+ remodeling pattern.
3.3 Regulatory-inflammatory balance
Preserved immune competence is not limited to effector capacity; it also involves control of inflammatory tone. In late life, immune dysfunction arises not only from weak responses to pathogens or vaccines, but also from persistent low-grade inflammation that damages tissues, distorts hematopoiesis, and feeds back on immune-cell function. The T helper 17 cell (Th17)/regulatory T cell (Treg) axis provides a cellular entry point into this problem. Th17 cells promote inflammatory responses through interleukin (IL)-17A, IL-22, TNF, and related mediators, whereas Treg cells restrain effector activation and maintain tolerance through FOXP3-dependent programs and cytokines such as IL-10 and transforming growth factor beta (TGF-β)[57-59].
A Chinese centenarian study provides direct but limited evidence for altered Th17/Treg regulation. Plasma IL-17A, IL-1β, IL-23, and TGF-β levels in the larger cohort were closer to young-adult than older-adult patterns[38]. In a smaller cytometric and ex vivo subset (n = 8 per group), centenarians showed a lower Th17/Treg ratio, while polarization assays showed reduced pro-inflammatory cytokine secretion from Th17-polarized cells and higher IL-10 secretion with relatively maintained TGF-β under Treg-polarizing conditions[38]. This configuration suggests recalibrated inflammatory control rather than broad immunosuppression. Although Treg frequencies can rise during ordinary aging, excessive regulatory activity may compromise vaccine responses, pathogen clearance, or tumor surveillance[57,58,60].
This pattern may contribute to inflammatory restraint in extreme old age without implying broad immunosuppression. Within the present classification, however, the Th17/Treg findings provide evidence-limited support for preserved regulatory-inflammatory balance because direct cellular and ex vivo evidence derives from a small subset of one cohort and lacks independent validation across LLI populations.
3.4 Myeloid and antigen-presenting-cell support
Monocytes, macrophages, and dendritic cells connect pathogen sensing, phagocytosis, efferocytosis, antigen presentation, tissue repair, and resolution of inflammation[25,61]. Conventional aging often shifts myeloid cells toward inflammatory phenotypes, alters monocyte subset composition, and impairs phagocytosis or efferocytosis.
Data from LLI cohorts support partial maintenance of selected myeloid programs, although cellular composition and molecular activity should be distinguished. At the cellular level, changes in monocyte and dendritic-cell abundance are modest or inconsistent across cohorts. A three-cohort single-cell study found only small changes among myeloid subsets, including a lower proportion of myeloid dendritic cells in centenarians than in centenarian offspring[25], whereas another study reported a modest increase in CD14+ monocytes in centenarians relative to elderly controls[40]. At the transcriptomic level, centenarian myeloid cells show enrichment of cytokine/chemokine, antimicrobial, and antigen-presentation-related programs[25]. Complementary single-cell analysis further identified enhanced antigen-presenting activity of CD14+ monocytes in long-lived individuals[41]. Multi-cohort transcriptomic and epigenomic analyses further identified monocyte-enriched lysosomal and phagocytosis-related programs associated with insulin signaling and oxidative phosphorylation[39]. Together, these findings support partial preservation of myeloid molecular programs, while direct assays of phagocytosis, efferocytosis, or antigen presentation in primary LLI myeloid cells remain limited.
Dendritic-cell and APC evidence remains less complete. Aging can reduce dendritic-cell numbers and weaken TLR signaling, type I IFN responses, and antigen-specific priming[62-64]. In centenarian cohorts, antigen-presentation-related transcriptional programs appear preserved or enhanced in selected myeloid populations, but this has not been consistently accompanied by preservation of dendritic-cell abundance or by direct functional APC assays[22,25,40]. Thus, myeloid/APC support in LLIs is best interpreted as partial preservation, with stronger evidence for molecular programs associated with antigen handling than for preserved APC function per se. The relative distribution and evidential strength of these selectively preserved cellular immune features are summarized in Figure 2.
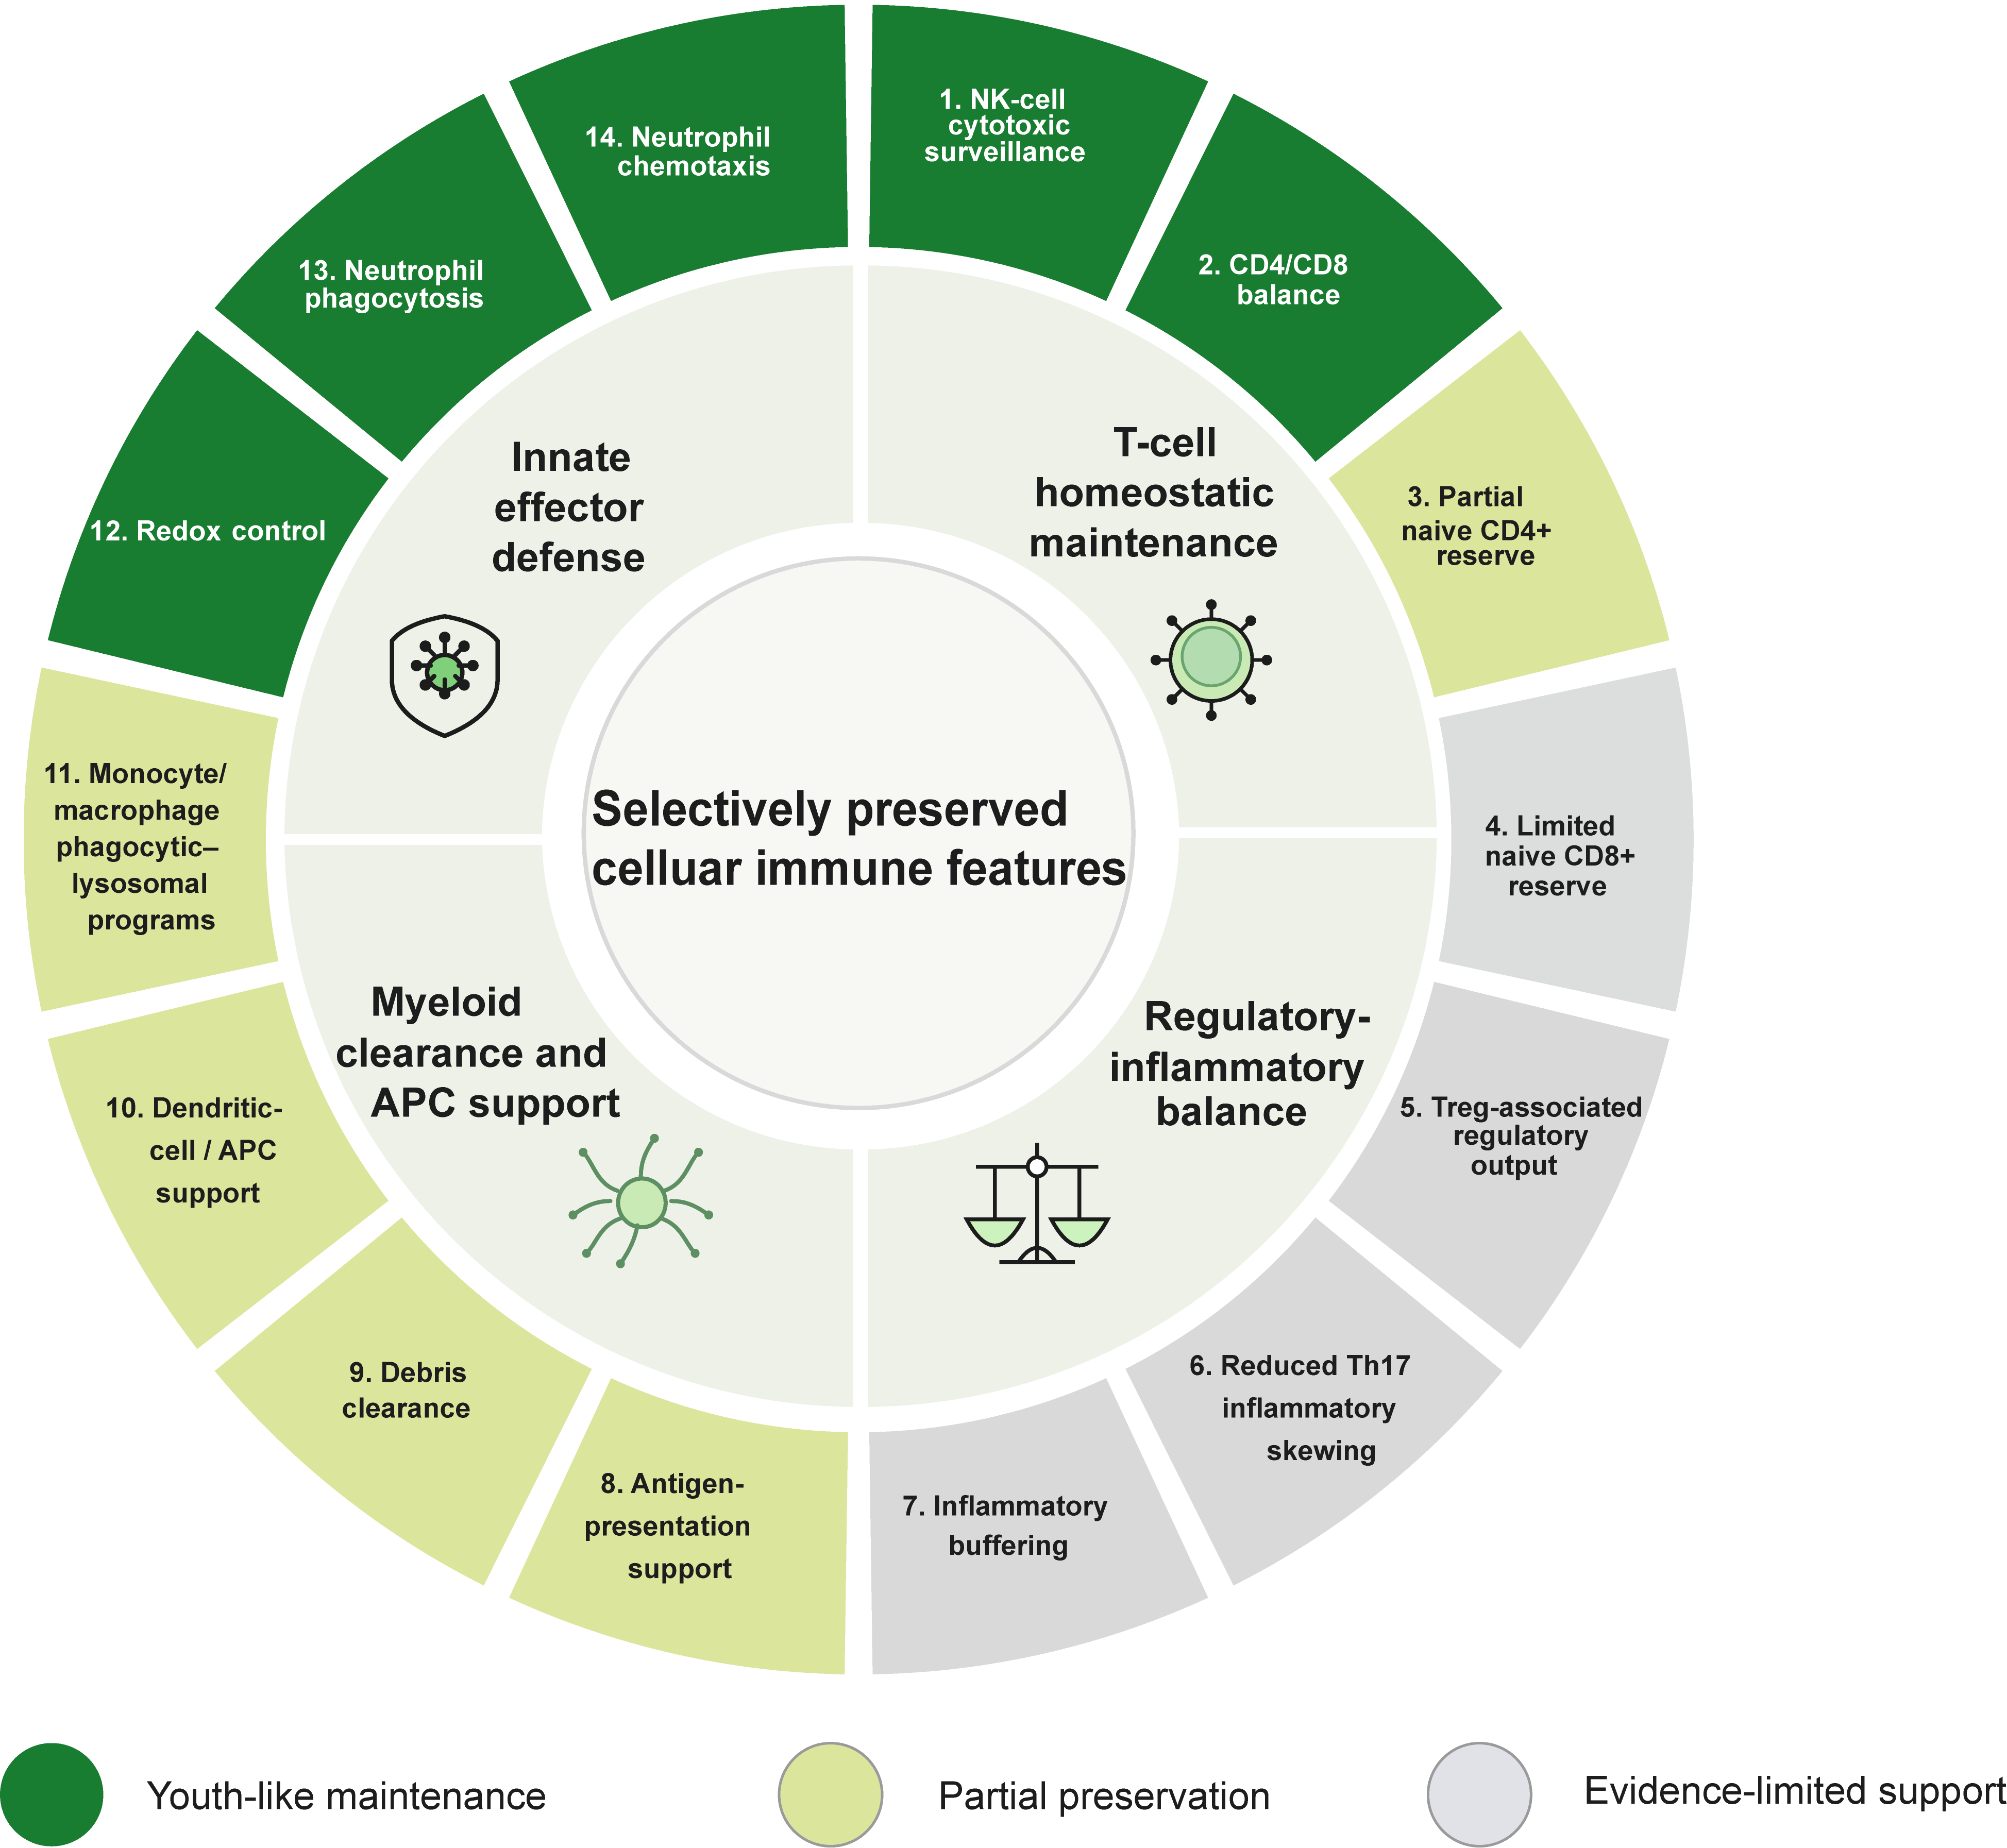
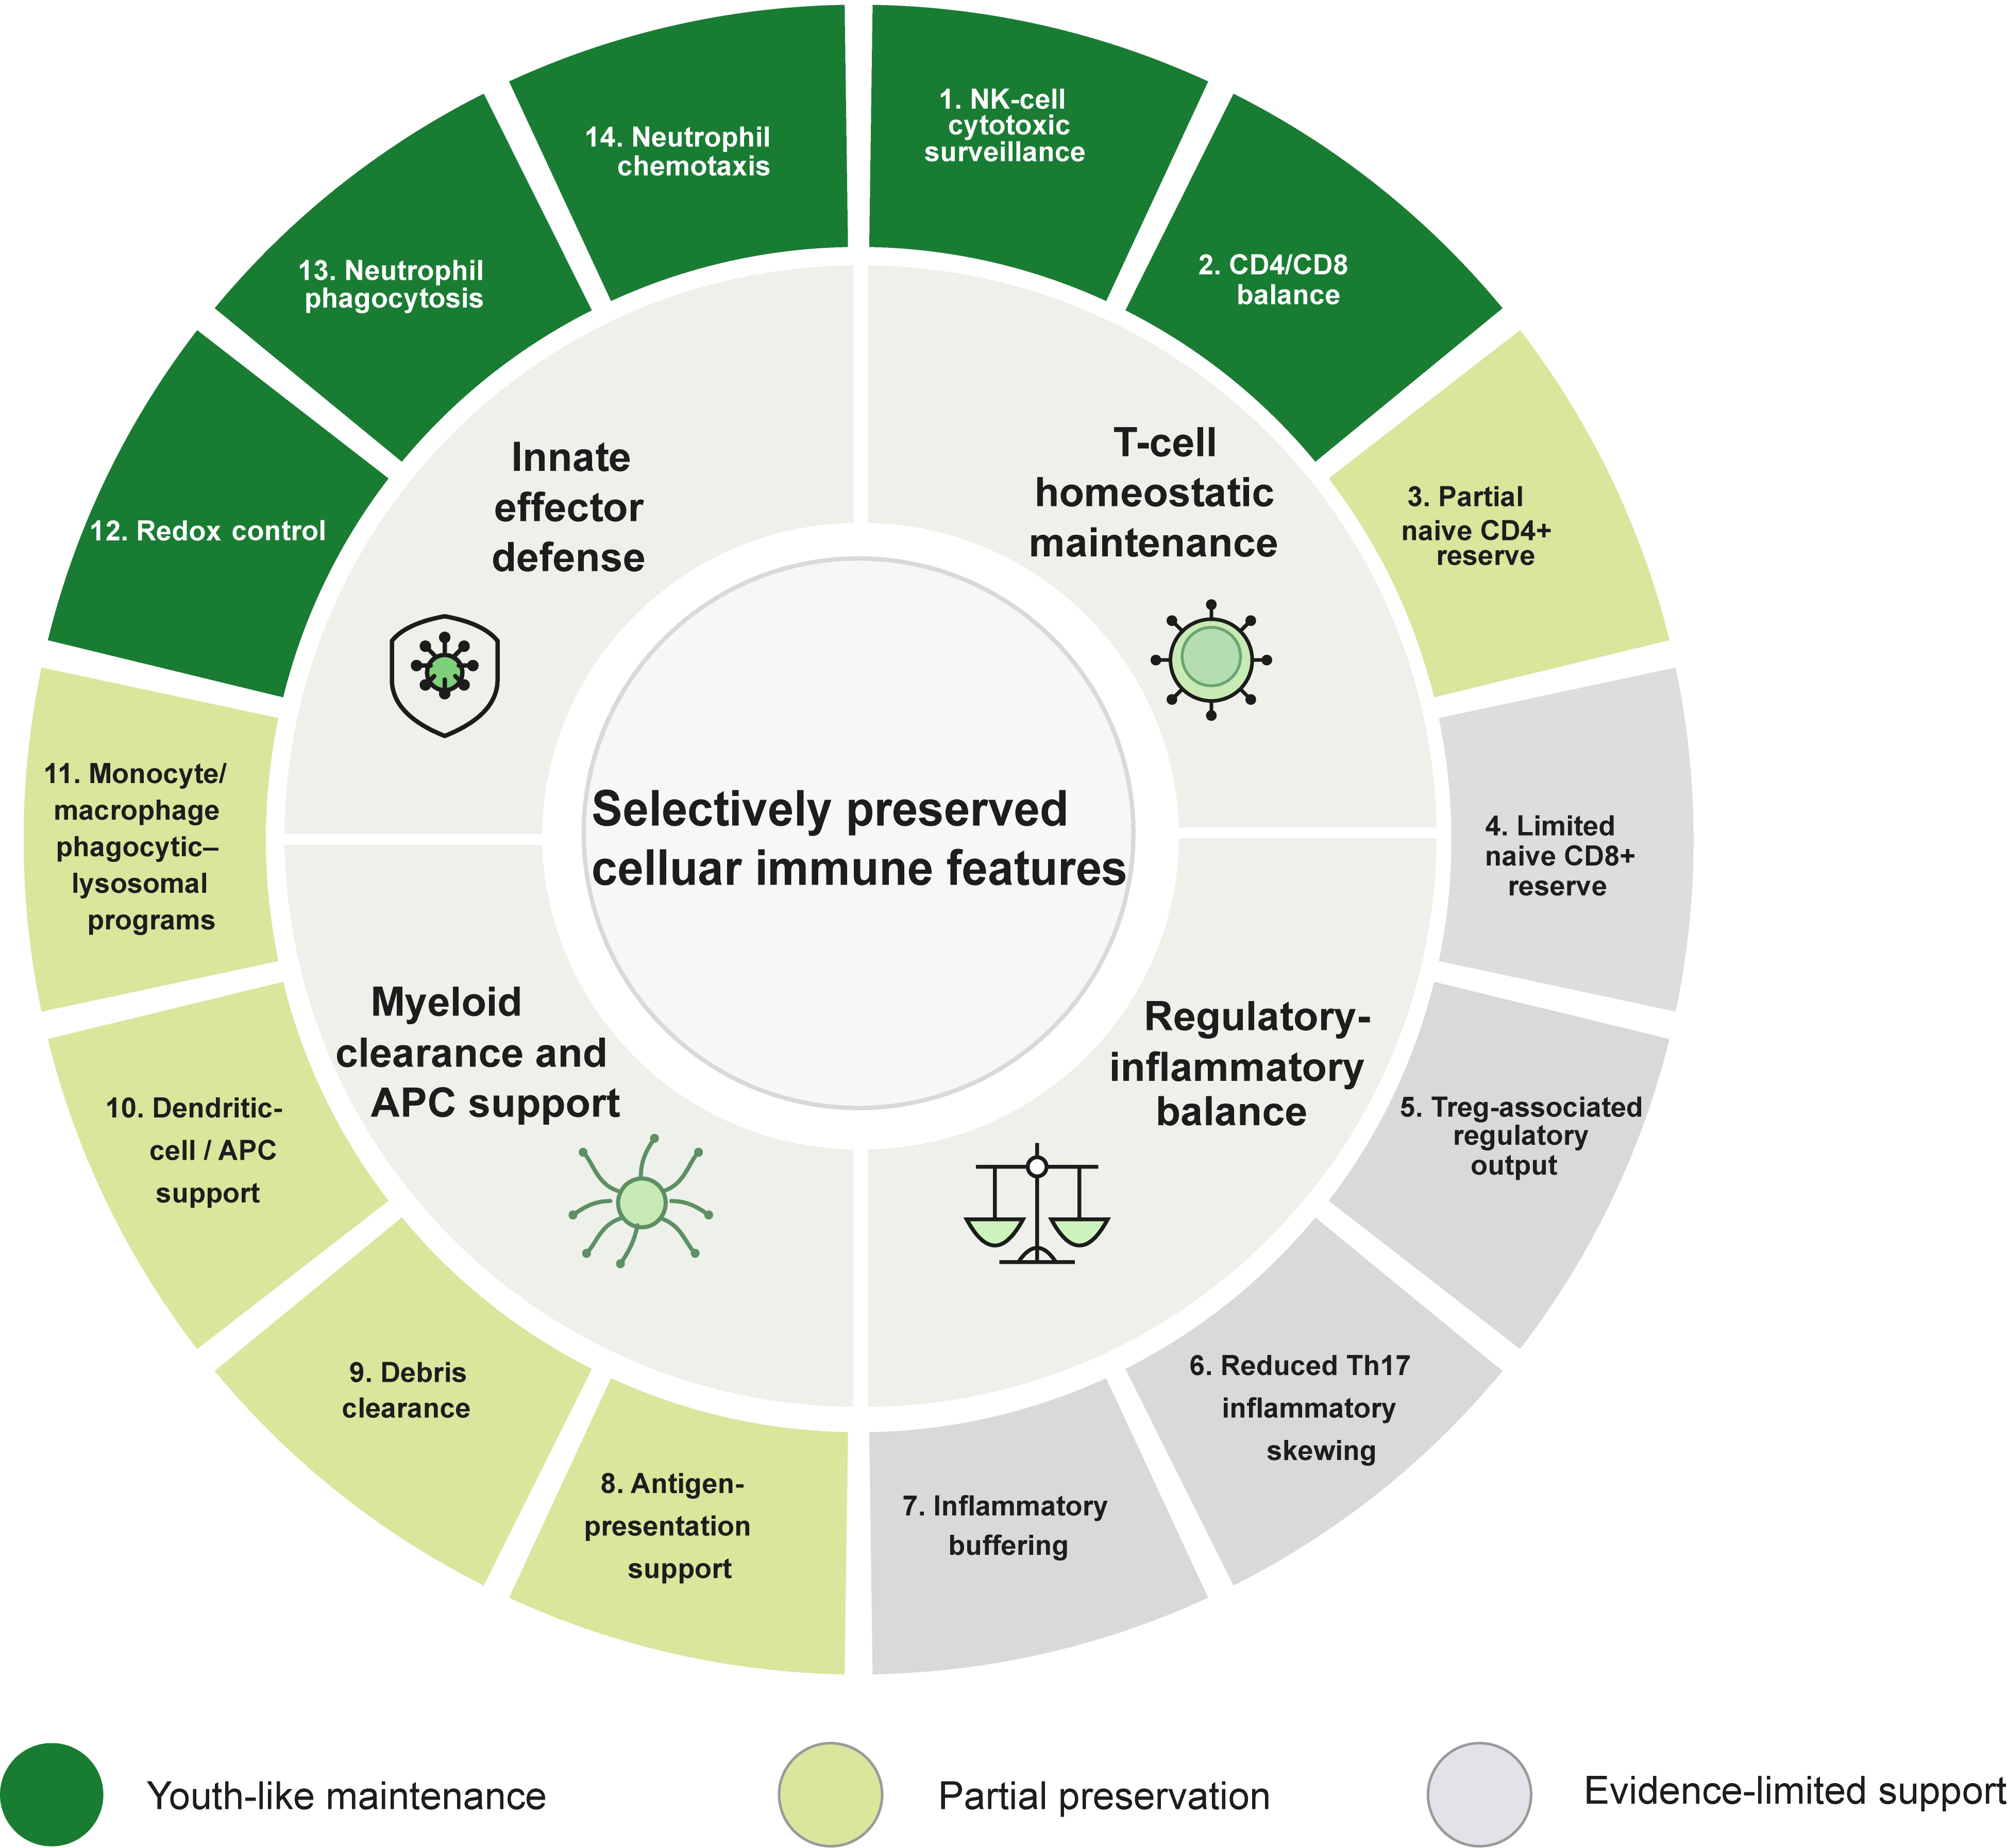
Figure 2. Distribution and evidential strength of selectively preserved cellular immune features in human longevity. Selected features in LLIs are organized into four functional domains: innate effector defense, T-cell homeostatic maintenance, regulatory-inflammatory balance, and myeloid clearance/APC support. Dark green, light green, and gray indicate youth-like maintenance, partial preservation, and evidence-limited support, respectively. LLIs: long-lived individuals; APC: antigen-presenting cell; Th17: T helper 17 cell; Treg: regulatory T cell; CD4: cluster of differentiation 4; CD8: cluster of differentiation 8; NK: natural killer.
4. Molecular Programs Supporting Selectively Preserved Immune Competence
The cellular features described above establish that selected immune functions in LLIs can remain closer to young-adult patterns than expected from chronological age. The molecular basis of this preservation is less directly resolved. Current studies mainly show that LLIs differ from conventionally aged older adults in coordinated transcriptional, proteostasis-related, mitochondrial, metabolic, and inflammatory states[25,37,65-67]. These patterns provide plausible support for preserved cytotoxicity, phagocytosis, T-cell homeostasis, antigen handling, and inflammatory restraint, even though direct pathway-to-function evidence in primary LLI immune cells remains limited. The available molecular evidence can be organized around three connected processes: immune-cell state coordination and communication, quality-control programs involving autophagy-lysosomal and mitochondrial regulation, and inflammatory buffering.
4.1 Cell-state coordination and immune-cell communication
Peripheral blood transcriptomes provide an important molecular entry point into selective immune maintenance. Their value is not in defining isolated markers, but in showing that immune cells from LLIs can occupy expression states that differ from conventional aging trajectories. Across available transcriptomic and single-cell studies, the recurring signal is not global molecular rejuvenation but coordinated preservation of selected cell states involved in survival, cytotoxic function, antigen handling, protein-synthesis capacity, and inflammatory control[25,37,40,42,65].
4.1.1 Transcriptional activation-survival and apoptosis-regulatory programs
Peripheral blood mononuclear cells (PBMCs) from Spanish centenarians showed transcriptional profiles distinct from those of septuagenarians and, for selected immune and signaling features, closer to those of young adults. Sub-network analyses highlighted IFNG-, IL32-, TGFB1-, TNF-, and T-cell receptor-associated regulatory networks[65]. These networks were linked to apoptosis- and survival-related genes, including BCL2L1, FAS, and FASL[65,68]. This pattern suggests that long-lived immune systems are not transcriptionally inactive. Instead, they may retain a regulated activation-survival program that supports immune responsiveness while limiting excessive cell loss or uncontrolled expansion.
BCL2L1, which encodes mitochondrial B-cell lymphoma-extra large (Bcl-xL), illustrates this balance. It was selectively upregulated in centenarians relative to septuagenarians, with validation showing levels comparable to young adults in an independent cohort[65]. In vitro, Bcl-xL overexpression in lymphocytes from older donors reduced senescence-associated markers, and a gain-of-function mutation in the Caenorhabditis elegans orthologue extended lifespan[65]. These findings do not identify Bcl-xL as an isolated driver of immune rejuvenation; rather, they suggest that survival-senescence regulation may help preserve competent immune cells when integrated with apoptotic control, mitochondrial fitness, and inflammatory restraint.
4.1.2 Cell-type-specific aging deceleration and inflammatory control
Single-cell studies show that youth-like immune maintenance in LLIs is cell-type specific rather than global. Human blood aging and frailty cohorts reveal divergent trajectories across naive, memory, exhausted, NK, B-cell, and monocyte populations[69], while supercentenarians also show adaptive remodeling, including clonal expansion of cytotoxic CD4+ T cells[43]. In a PBMC scRNA-seq aging-clock study, supercentenarians had transcriptome-based biological ages below their chronological ages, but this deceleration was uneven across immune populations. Relative to predicted aging trajectories, they retained higher-than-expected naive CD8+ T-cell frequencies and lower-than-expected frequencies of cytotoxic CD8+ T cells, memory CD4+ T cells, and megakaryocytes[37].
A key molecular signal was the ribosome-inflammation balance. Supercentenarians retained more high-ribosomal-expression cells, especially among inflammatory-prone myeloid populations, and this state was inversely associated with inflammatory gene-expression scores[37]. Bayesian network inference and translation inhibition in monocytes further suggested that reduced ribosomal activity can promote IL-6 and IL-8 induction in specific myeloid contexts. Thus, preserved ribosome-associated translation programs may contribute to delayed immune aging and inflammatory restraint, although this should be interpreted as a cell-type-specific candidate mechanism rather than a universal feature of longevity.
4.1.3 Immune-cell communication and antiviral signatures
Single-cell and cytometry-based studies also point to preserved communication among immune compartments. Chinese and Japanese centenarian cohorts showed youth-like NK-cell transcriptional and protein signatures, RUNX3-associated cytotoxic programs, increased granzyme B-positive NK cells, and inferred NK-T-cell communication through MHC-I, CD99, and MIF-related pathways[22,25]. These findings provide molecular support for the preserved NK-cell cytotoxic surveillance described in Section 2.
Single-cell studies of Chinese centenarians and supercentenarians identified enhanced myeloid transcriptional programs related to antigen presentation, human leukocyte antigen (HLA)/MHC-II expression, cytokine and chemokine signaling, and antimicrobial responses, while changes in myeloid-cell abundance were modest or inconsistent across cohorts[25,41]. These molecular signatures support partial preservation of selected myeloid/APC programs, but should not be interpreted as direct evidence of preserved antigen-presenting function.
Taken together, transcriptional and single-cell evidence supports a model in which preserved immune competence in LLIs is associated with coordinated cell states rather than isolated genes. These states combine survival-senescence balance, preserved protein-synthesis capacity, cytotoxic communication, antigen-presentation-related molecular programs, and restrained inflammatory drift. This layer provides the molecular context in which selected immune functions may remain preserved in extreme old age.
4.2 Quality-control programs: Autophagy-lysosomal and mitochondrial regulation
A second support layer involves cellular quality control. The youth-like immune functions described above are difficult to sustain without efficient protein turnover, lysosomal degradation, redox control, mitochondrial fitness, and metabolic coordination. NK-cell killing requires cytotoxic granule biogenesis and membrane trafficking; neutrophil chemotaxis and phagocytosis depend on cytoskeletal remodeling and oxidative control; T-cell survival and memory maintenance require proteostatic balance and mitochondrial integrity; and monocyte/macrophage clearance relies on lysosomal degradation, efferocytosis, antigen processing, and inflammasome restraint. Conventional aging weakens many of these processes. Loss of proteostasis, disabled macroautophagy, mitochondrial dysfunction, and chronic inflammatory signaling are core hallmarks of aging[14,70,71], and impaired autophagy in immune cells can compromise T-cell function, reduce stress tolerance, and increase inflammatory activation[70,71]. The relevant question in LLIs is therefore whether selected quality-control programs remain sufficient to support immune competence at very advanced age.
4.2.1 Autophagy-lysosomal programs
Human centenarian studies provide associative evidence implicating autophagy-lysosomal regulation in exceptional longevity. In Chinese centenarians, peripheral white blood cells showed upregulation of autophagy-lysosomal genes, including ATG4D, ATP6V0C, CTSB, and WIPI1[66]. In experimental models, overexpression of these genes in IMR-90 fibroblasts reduced senescence-associated markers and produced changes consistent with enhanced autophagic degradation, while overexpression of Atg18a, the Drosophila homolog of WIPI1, extended lifespan in transgenic flies[66]. Systemic biomarkers provide complementary but indirect evidence. Healthy Italian centenarians had higher circulating beclin 1 than young healthy controls[72]. By contrast, circulating acyl-CoA-binding protein (ACBP), an extracellular inhibitor of autophagy, was elevated in close-to-centenarians relative to young adults and increased further during acute health deterioration[73]. These circulating markers therefore indicate altered autophagy-related regulation in exceptional aging, but do not establish enhanced autophagic flux in LLI immune cells.
4.2.2 Lineage- and context-dependent evidence
Direct immune-cell evidence is more restricted. Activation-induced autophagy in CD4+ T cells was better maintained in offspring of exceptional-longevity families than in age-matched controls, whereas centenarians themselves showed activation-induced autophagy levels similar to those in the older control group, suggesting that the age-associated decline may be delayed rather than prevented in exceptional-longevity families[74]. Fas/FasL/sFas balance in centenarian lymphocytes may further contribute to apoptotic and survival equilibrium, although this evidence reflects apoptosis-related regulation rather than autophagy per se[68]. These findings argue against a model in which LLIs maintain globally youthful autophagy. A more plausible interpretation is lineage- and context-dependent support: quality-control and cell-fate regulatory programs may contribute to selected immune functions, but direct causal links in LLI immune cells remain to be established.
4.2.3 Mitochondrial and metabolic quality control
Centenarian PBMCs show evidence of altered mitochondrial and intrinsic-apoptotic regulation, including increased BCL2L1/Bcl-xL expression, higher mitochondrial membrane potential, and lower circulating cytochrome c than septuagenarians[65]. Experimental manipulation supports a role for Bcl-xL in cellular aging, but does not establish that Bcl-xL directly accounts for the mitochondrial phenotype observed in centenarian immune cells. More broadly in aging biology, mitochondrial dysfunction can increase reactive oxygen species (ROS) production and release mitochondrial damage-associated molecular patterns (DAMPs), including mitochondrial deoxyribonucleic acid (mtDNA), thereby activating inflammatory pathways such as NLR family pyrin domain containing 3 (NLRP3), cyclic GMP-AMP synthase (cGAS)-stimulator of interferon genes (STING), and nuclear factor kappa B (NF-κB) and amplifying inflammaging[12,75]. Mitophagy therefore represents a plausible bridge between autophagy-lysosomal maintenance and inflammatory buffering. Direct evidence for preserved mitophagy in primary centenarian immune subsets remains limited, but recent longevity transcriptomic data support the relevance of mitochondrial translation: in a large Chinese cohort of nonagenarians and centenarians, bulk RNA sequencing of peripheral white blood cells revealed younger-than-expected transcriptional ages and higher-than-expected expression of eight mitochondrial ribosomal protein genes relative to typical age-related trajectories[67]. Higher scores for the eight mitochondrial ribosomal protein gene signature (8-mRPG) were associated with lower aging- and senescence-related signatures and increased mitochondrial-function-related gene expression[67]. Together, these findings support a peripheral blood transcriptional state compatible with healthier immune aging, while not yet proving preserved mitochondrial function in specific immune subsets.
Overall, quality-control programs are best viewed as candidate support layers for preserved immune competence rather than as established mechanisms of exceptional longevity. Autophagy, lysosomal degradation, proteostasis, metabolic regulation, and mitochondrial maintenance may help explain how immune cells remain competent under chronic age-associated stress. The strongest current evidence comes from LLI-associated autophagy-lysosomal gene expression, systemic autophagy-related biomarkers, mitochondrial/apoptosis-related PBMC signatures, and model-system validation[65-67,72-74]. Future studies should test whether preserved quality control in NK cells, neutrophils, T cells, and monocytes directly predicts cytotoxicity, chemotaxis, phagocytosis, vaccine responsiveness, and inflammatory restraint.
4.3 Inflammatory buffering: Cytokines, NLRP3, senescence-associated secretory phenotype (SASP) and systemic tone
The third support layer concerns the cost of chronic inflammation. Inflammaging contributes to immunosenescence, frailty, cardiovascular disease, and multimorbidity[13,14,76]. LLIs often present an apparent paradox: inflammatory mediators may be detectable or even elevated, yet many individuals remain functionally preserved. The relevant feature is therefore not uniformly low inflammation, but the ability to buffer, redirect, or tolerate inflammatory signals so that immune activation does not become chronic tissue damage.
4.3.1 Cytokine networks and regulatory tone
Cohort studies support this interpretation, but also highlight marked heterogeneity. In a Chinese cohort, plasma IL-17A, IL-1β, and IL-23 levels in centenarians were closer to young-adult patterns, while a smaller cytometric subset showed a lower Th17/Treg ratio than older adults[38]. In Italian cohorts, a small targeted study reported higher circulating IL-22 in healthy centenarians[77], while a broader cytokine-network analysis found higher TNF-α, IL-6, IFN-α, IL-23, chemokines, and immune-related growth factors, but no significant increase in IFN-γ, IL-12p70, or IL-17 isoforms[78]. In Japanese semi-supercentenarians and supercentenarians, an inflammation score based on CMV titer, IL-6, TNF-α, and C-reactive protein (CRP) predicted survival, physical capability, and cognition, whereas associations with multimorbidity were weaker or inconsistent[56]. These findings suggest that cytokine abundance alone is an incomplete readout of inflammatory burden. Cytokine source, receptor availability, soluble receptor networks, cellular targets, and counter-regulatory pathways can reshape whether a cytokine profile becomes harmful[79].
The Th17/Treg axis provides a representative cellular and secretory example of this regulatory tone. Chinese centenarians showed a lower Th17/Treg ratio than older adults, with circulating IL-17A, IL-1β, and IL-23 closer to young-adult levels[38]. Ex vivo differentiation assays further suggested that centenarian-derived Th17-polarized cells secreted fewer pro-inflammatory cytokines, whereas Treg-polarized cells showed higher IL-10 secretion and relatively maintained TGF-β secretion compared with older-adult controls[38]. Cytokine-network studies also report remodeling of hemopoietic growth-factor responsiveness and cytokine production in healthy centenarians, while soluble cytokine and growth-factor receptors may further reshape downstream signaling[79,80]. Together, these observations suggest that inflammation in LLIs is organized through networks and counter-regulation rather than through a simple low-cytokine state.
4.3.2 Systemic inflammatory-aging readouts
Inflammatory clocks and circulating RNA/DNA-based readouts provide complementary evidence that LLIs may avoid accelerated inflammatory aging. The inflammatory aging clock (iAge) model identified C-X-C motif chemokine ligand 9 (CXCL9) as a major contributor to inflammatory aging and linked higher iAge to multimorbidity, immunosenescence, frailty, and cardiovascular aging; in a small Italian cohort, centenarians were enriched in a protective group with a low iAge index[81]. Circulating microRNA (miRNA) studies further suggest nonlinear inflammatory-aging trajectories: in Sicilian ultra-centenarians, miR-21-5p and miR-126-3p were lower than in adult or older-adult groups, whereas miR-146a-5p and miR-181a-5p showed greater heterogeneity[82]. Additional data indicate that miR-19a-3p/miR-19b-3p and related isomiR patterns may distinguish healthier from less healthy extreme aging and converge on FOXO-related stress-response pathways[83]. Cell-free DNA (cfDNA) profiling similarly suggests that healthy centenarians can resemble young individuals more closely than unhealthy centenarians in selected nucleosome and tissue-contribution patterns[84]. Together, these markers do not establish causality, but they support the view that LLI inflammatory biology differs from conventional aging at both signaling and damage-output levels.
4.3.3 Inflammasome restraint and SASP buffering
Human centenarian data provide limited direct transcript-level evidence linking healthier extreme aging to a lower NLRP3-associated inflammatory state. In stimulated T cells, high-performing centenarians showed lower NLRP3 and pro-inflammatory cytokine expression than low-performing centenarians and older controls, together with higher IL-10 expression[85]. These findings indicate an attenuated inflammatory transcriptional response but do not demonstrate reduced NLRP3 inflammasome activation or causality. In aged mice, Nlrp3 deficiency attenuates multiple age-related inflammatory and functional changes[86], providing mechanistic context for biological aging rather than direct evidence for exceptional human longevity. NLRP3 restraint should therefore be regarded as a candidate support program whose causal contribution to preserved immune competence in LLIs remains to be established.
SASP modulation extends this buffering framework. Senescent cells release heterogeneous mixtures of cytokines, chemokines, growth factors, proteases, lipids, and extracellular-vesicle-associated signals that can amplify local and systemic inflammaging[87]. Evidence from centenarian fibroblast studies implicating DNA-damage/RNASEH2C-related inflammatory restraint, together with the circulating RNA/DNA patterns described above, is compatible with altered senescence-associated inflammatory signaling in LLIs; however, these findings do not directly demonstrate reduced SASP production or activity in LLI immune cells[82-84,88]. Importantly, proteomic analysis from the New England Centenarian Study showed that centenarians retain aging-related serum protein signatures enriched for SASP-associated proteins[89], indicating that exceptional longevity does not require the absence of SASP-associated circulating signals. SASP buffering should therefore be regarded as a candidate support model in which the biological consequences of senescence-associated inflammatory signals may be better tolerated or counter-regulated, rather than as an established mechanism preserving specific immune functions in LLIs. These candidate molecular support layers and their proposed links to preserved immune functions are summarized in Figure 3.
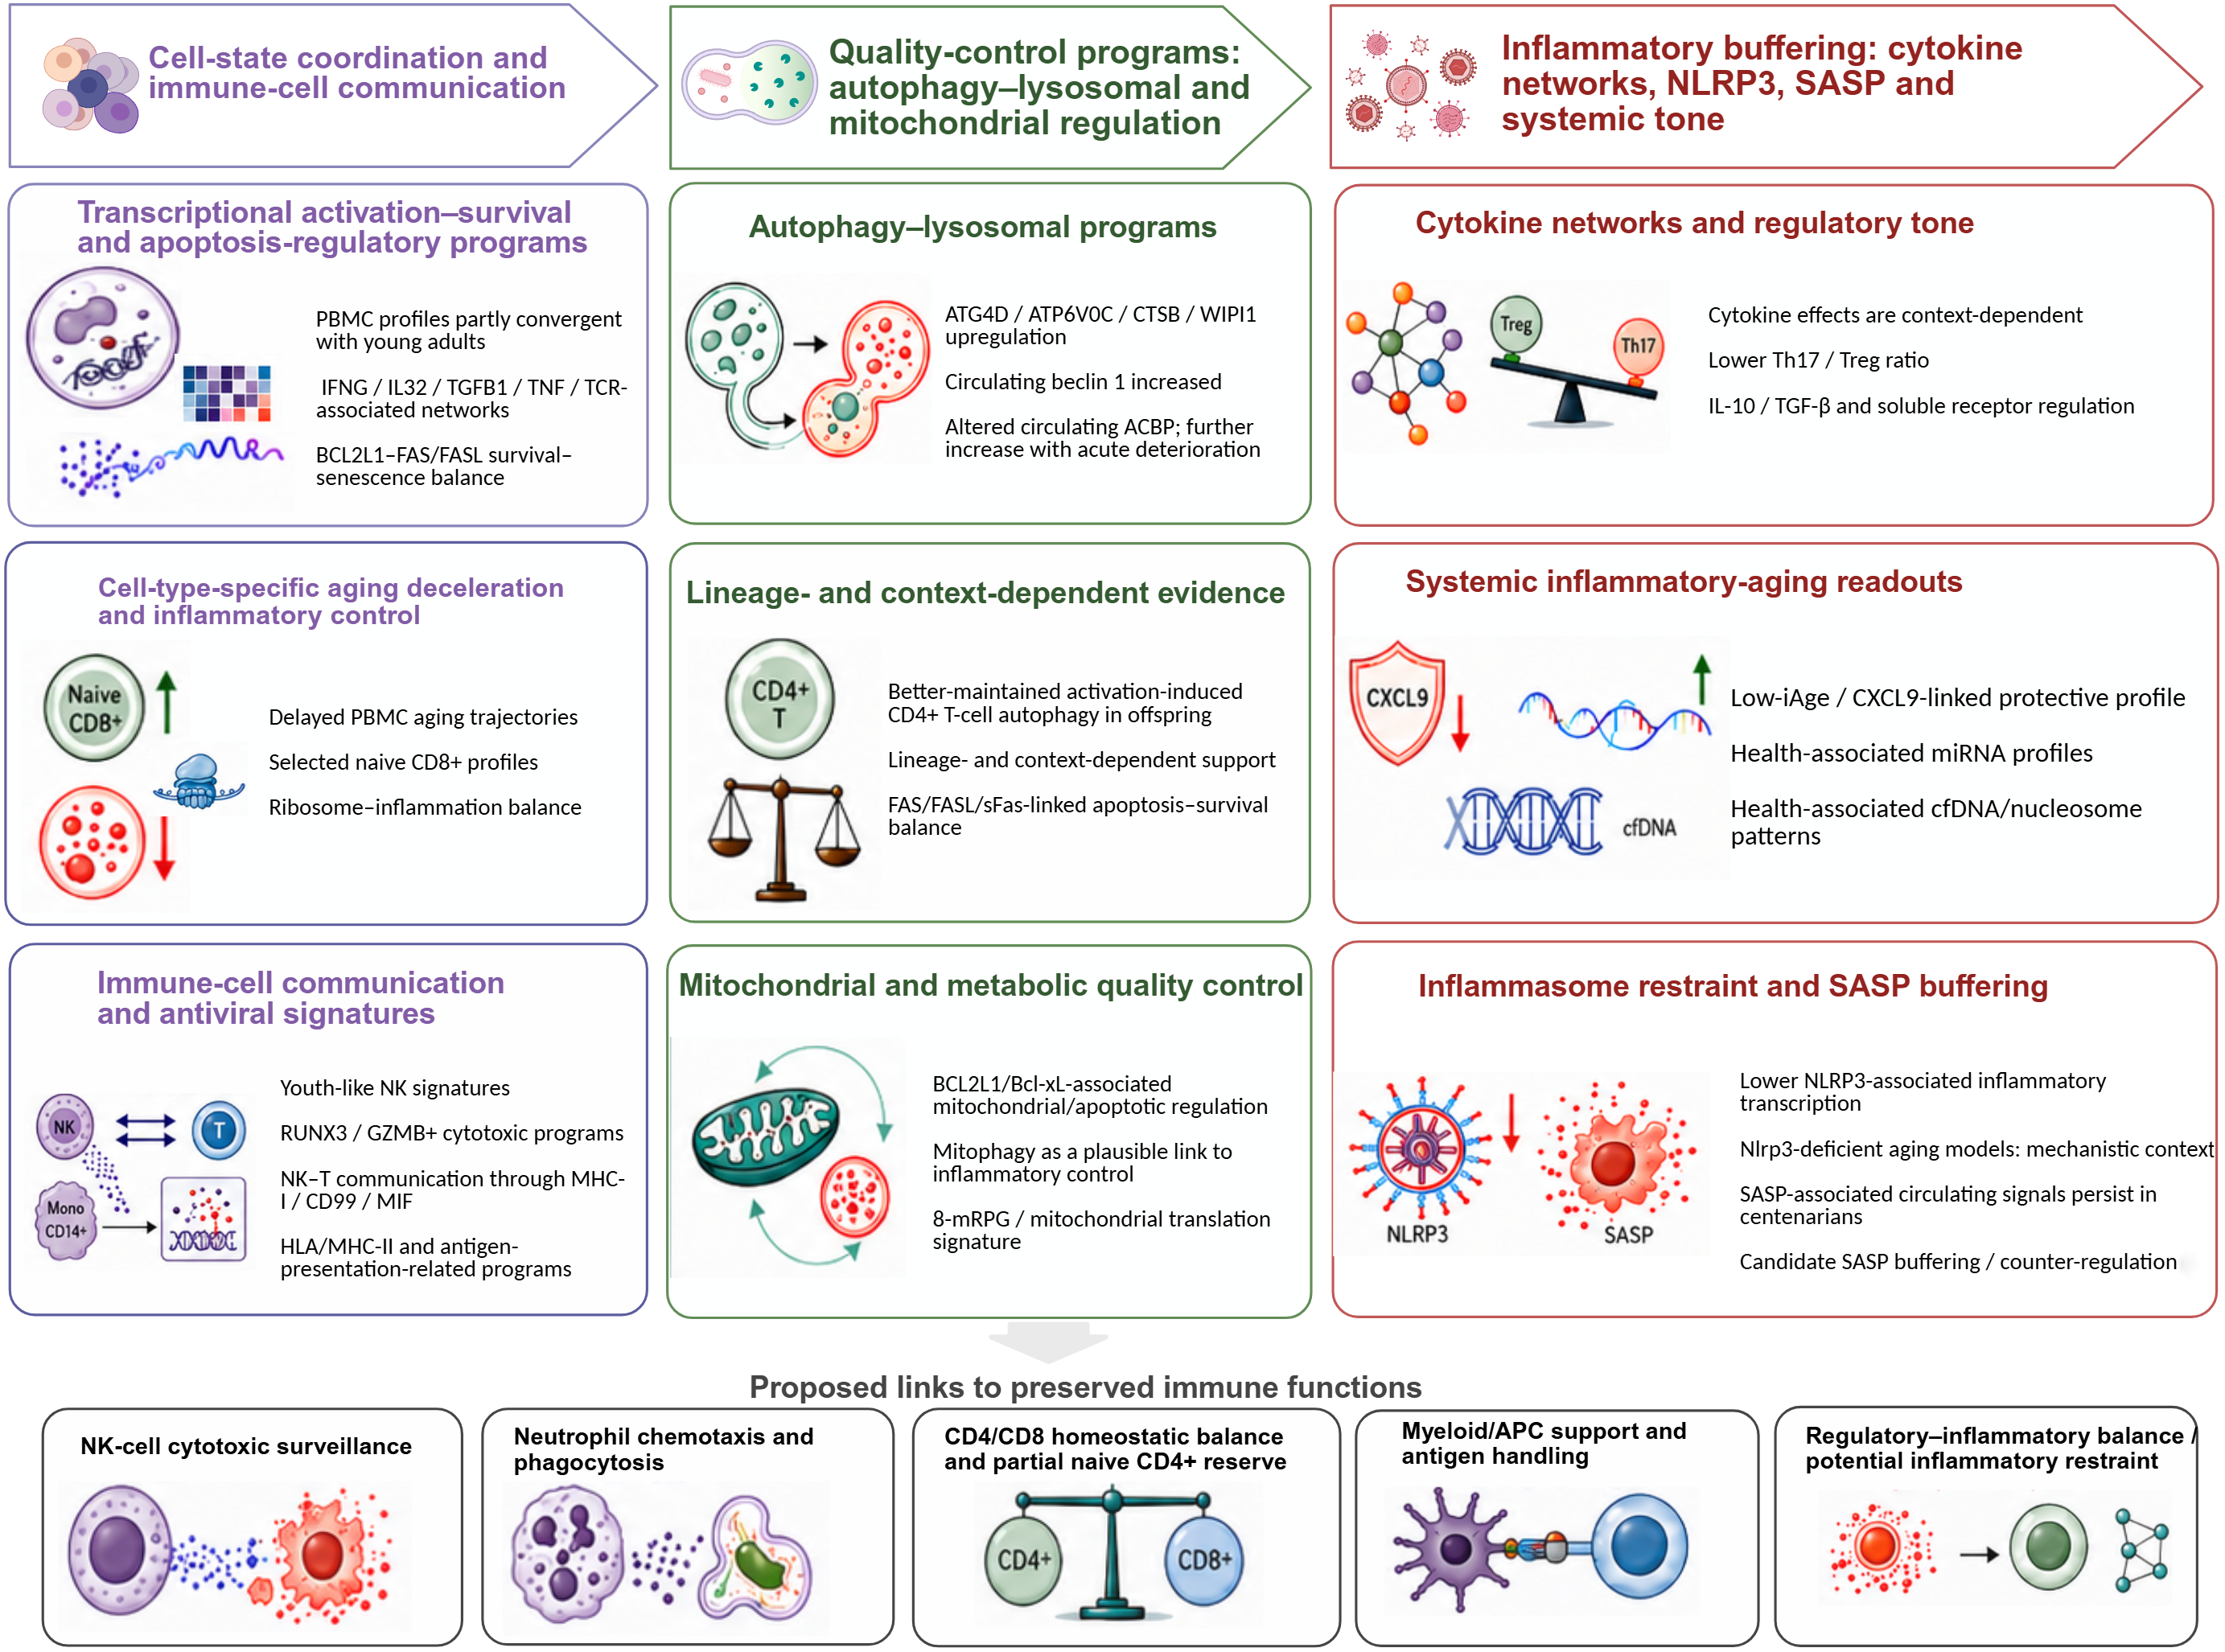
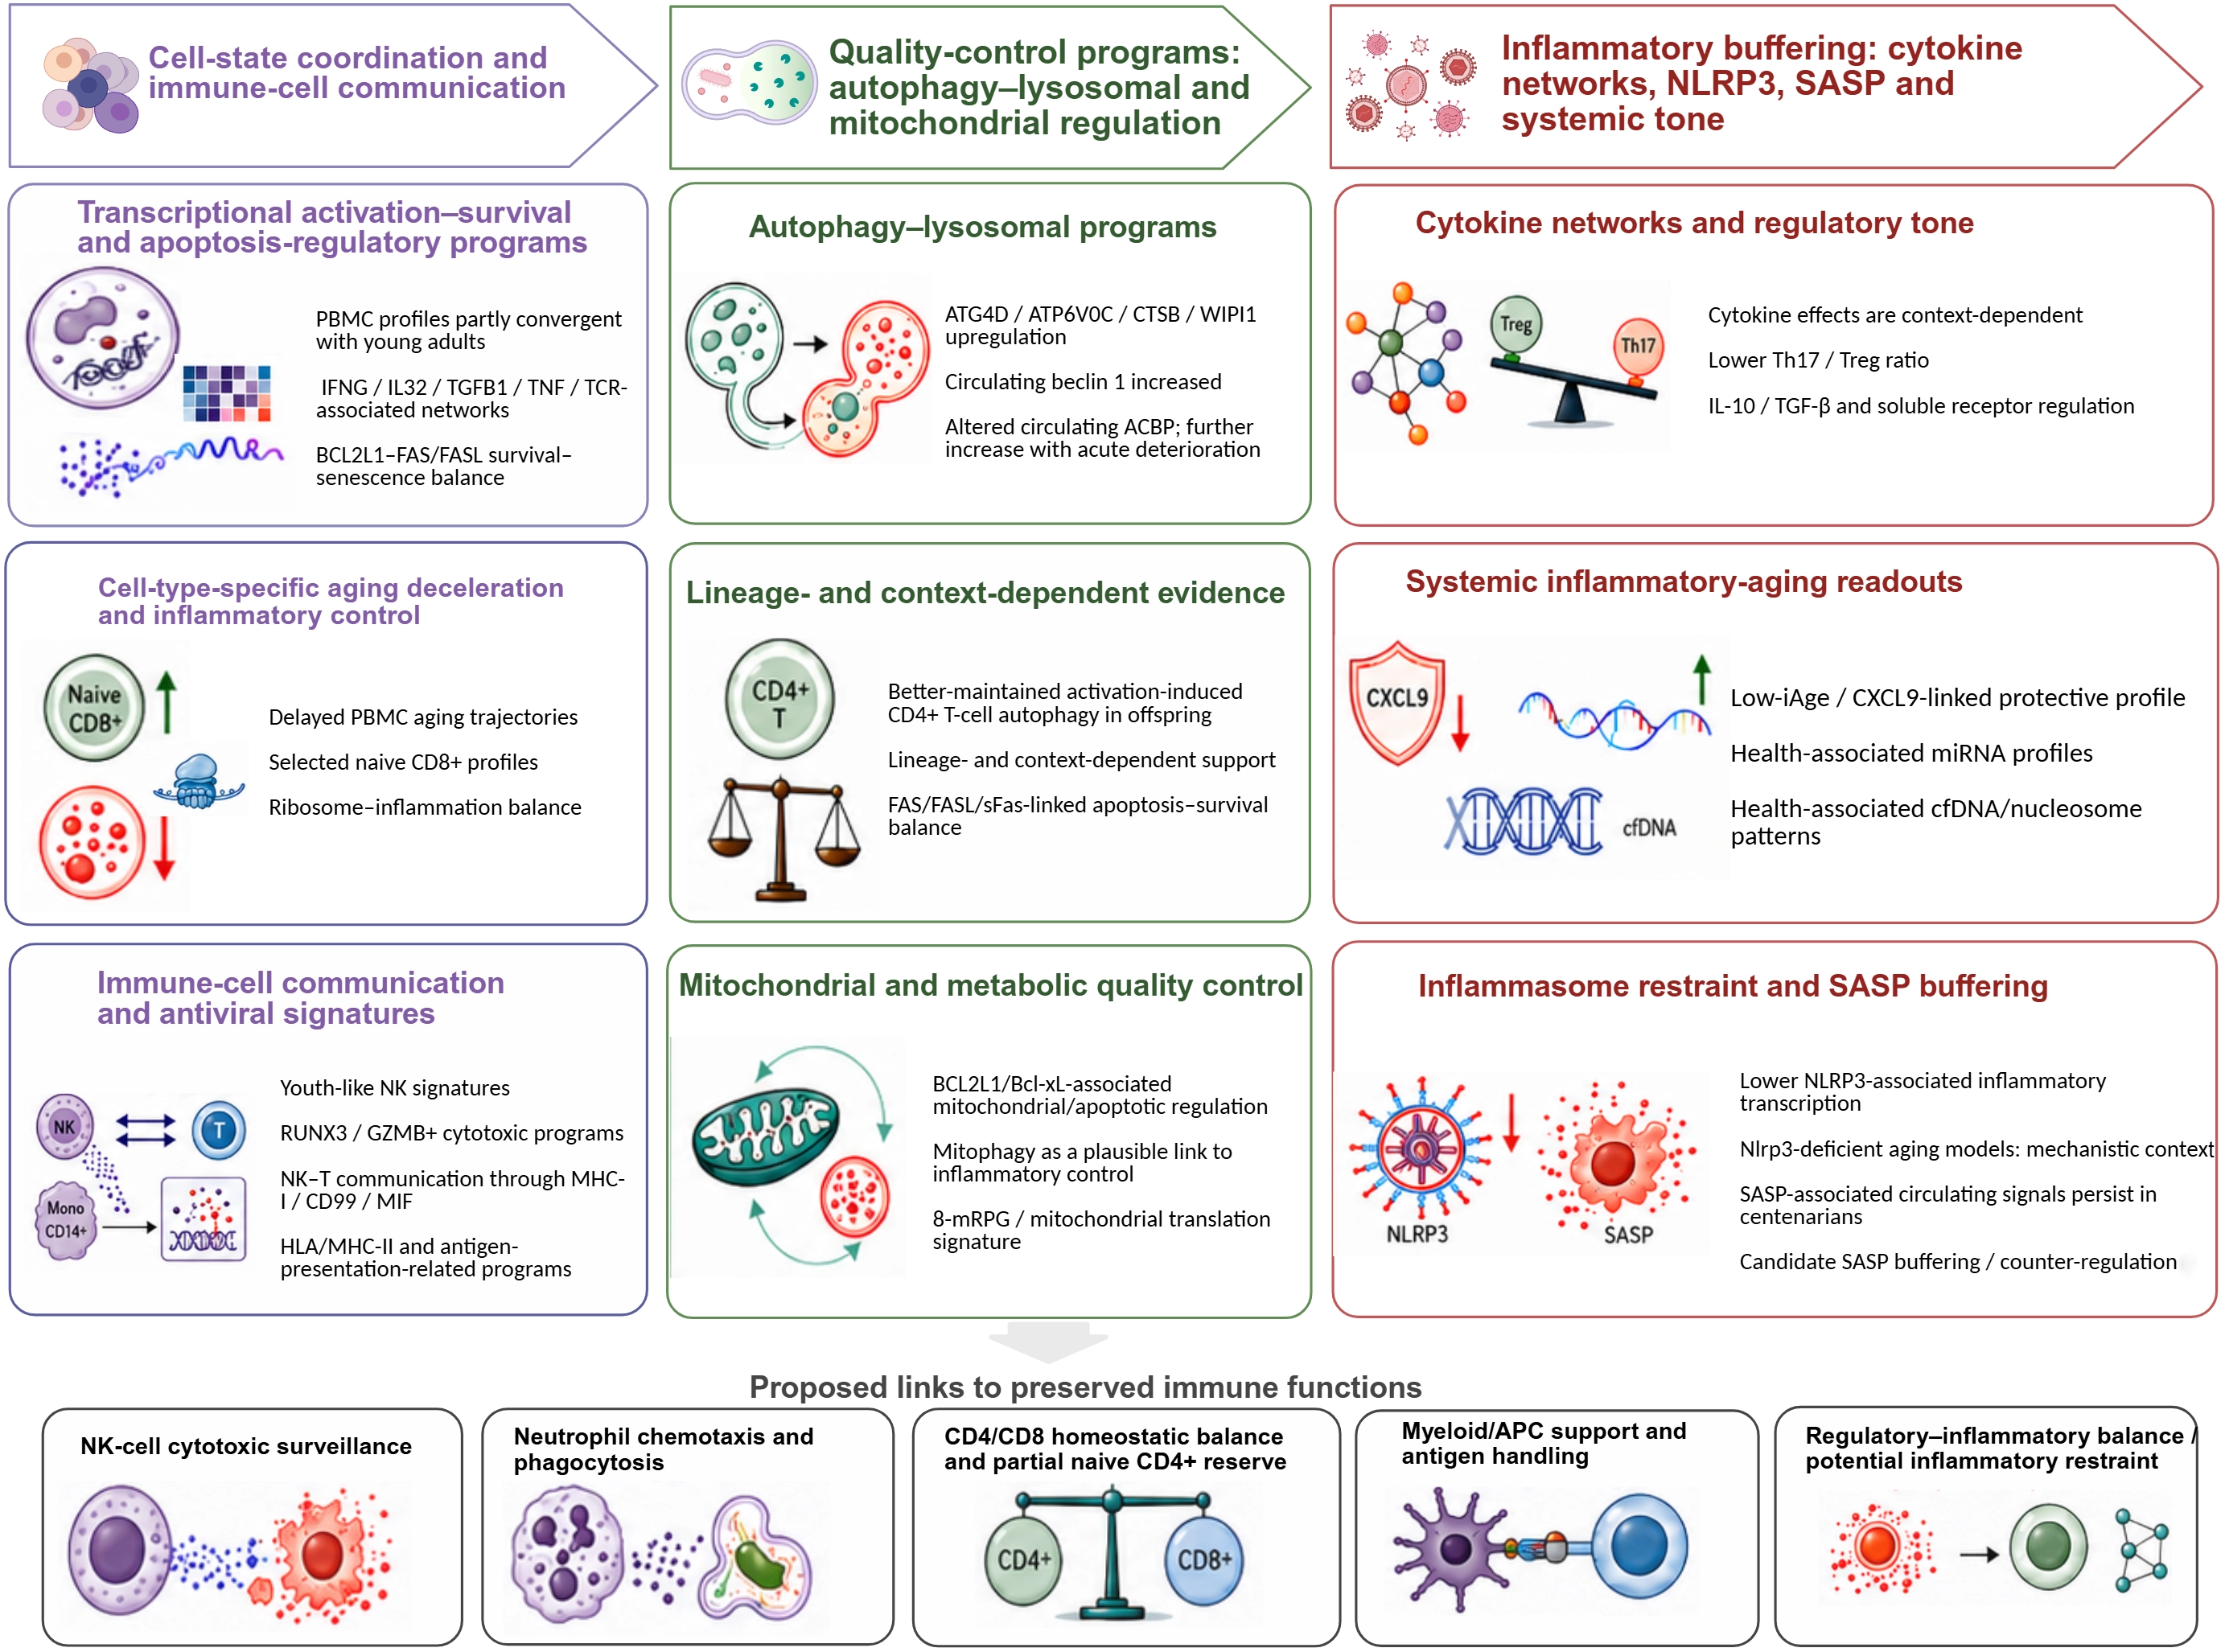
Figure 3. Candidate cellular and molecular programs supporting selectively preserved immune competence in human longevity. Three candidate support layers are summarized: cell-state coordination and immune-cell communication, quality-control programs involving autophagy-lysosomal and mitochondrial regulation, and inflammatory buffering. Human LLI-associated findings are integrated with complementary experimental and aging-model evidence to illustrate proposed links to preserved NK-cell cytotoxic surveillance, neutrophil chemotaxis and phagocytosis, CD4/CD8 homeostatic balance and partial naive CD4+ T-cell reserve, myeloid/APC support and antigen handling, and regulatory-inflammatory restraint. The molecular features shown should be interpreted primarily as associative or candidate support programs rather than as established causal mechanisms in primary immune cells from LLIs. LLI: long-lived individual; NLRP3: NLR family pyrin domain containing 3; PBMC: peripheral blood mononuclear cell; IFN: interferon; IL: interleukin; TGF-β: transforming growth factor beta; TCR: T-cell receptor; CD4: cluster of differentiation 4; CD8: cluster of differentiation 8; NK: natural killer; MHC-I: major histocompatibility complex class I; MHC-II, major histocompatibility complex class II; HLA: human leukocyte antigen; ACBP: acyl-CoA-binding protein; Bcl-xL: B-cell lymphoma-extra large; 8-mRPG: eight mitochondrial ribosomal protein gene signature; Th17: T helper 17 cell; Treg: regulatory T cell; CXCL9: C-X-C motif chemokine ligand 9; cfDNA: cell-free DNA; miRNA: microRNA; SASP: senescence-associated secretory phenotype; APC: antigen-presenting cell; MIF: macrophage migration inhibitory factor.
5. Conclusion and Perspectives
The central conclusion of this Review is that human longevity is associated with selective preservation of immune competence, with youth-like features retained in specific functional compartments. The most consistent examples are preserved innate effector activity, especially NK-cell cytotoxic surveillance and neutrophil chemotaxis and phagocytosis, together with maintenance of CD4/CD8 homeostatic balance and partial preservation of naive CD4+ T-cell reserve. Evidence-limited support is also available for preserved regulatory-inflammatory balance. These findings suggest that functionally important immune activities can remain comparatively intact under the biological constraints of extreme age, even as other immune compartments undergo lifelong antigen-driven remodeling.
The next step is to determine whether these preserved immune features are descriptive correlates or functionally meaningful predictors of healthy longevity. Most LLI studies remain cross-sectional, making it difficult to distinguish mechanisms that contribute to healthy aging from survivor selection, compensatory adaptation, or biomarkers of preserved health. Repeated sampling across nonagenarian, centenarian, and supercentenarian trajectories should therefore be paired with infection history, vaccination responses, cancer history, CMV status, sex, frailty, functional outcomes, and cause-specific morbidity. Multi-omics should also be linked more directly to immune function. Transcriptomic signatures, aging clocks, autophagy markers, mitochondrial programs, and inflammatory indices are informative, but their value will depend on whether they predict cytotoxicity, phagocytosis, antigen presentation, vaccine responsiveness, and inflammatory tolerance. This is especially important for autophagy, mitophagy, NLRP3 restraint, SASP modulation, and mitochondrial protein-synthesis programs, where LLI-associated evidence is promising but causality remains unresolved.
The cancer relevance of this framework should be tested but not assumed. Several cohorts suggest delayed or attenuated cancer burden among centenarians[7,90,91], and immune surveillance is one plausible contributor. Preserved NK-cell function and controlled inflammatory tone are plausible contributors to immune surveillance, whereas the functional consequences of cytotoxic T-cell remodeling are likely context dependent and remain unresolved. However, these associations do not establish that youth-like immune maintenance is a direct anticancer mechanism. Future work should connect immune phenotypes with cancer incidence, premalignant clonal states, clonal hematopoiesis, tissue-level immune surveillance, and longitudinal outcomes. This would clarify whether selective immune maintenance contributes to cancer protection or represents one component of a broader healthy-aging state.
The translational message is not to stimulate immunity broadly. It is to preserve immune competence while reducing inflammatory cost. Autophagy-lysosomal maintenance, mitochondrial and metabolic quality control, NLRP3 restraint, and inflammatory buffering are candidate intervention axes, but each requires further validation and carries potential risk[70,71,86]. LLI biology therefore points to a therapeutic principle rather than a single target: maintain defense capacity, preserve surveillance, and prevent immune activation from becoming chronically damaging. This principle aligns with geroscience approaches to cancer prevention and late-life disease control[92,93]. Overall, distinguishing preserved youth-like features from adaptive, non-youth-like remodeling is essential for interpreting human longevity and for designing interventions that support late-life immune competence without amplifying chronic inflammation.
Acknowledgements
Figures were prepared by the authors using BioRender.com and Adobe Illustrator. During manuscript preparation, ChatGPT (OpenAI) was used to assist with language editing and proofreading, checking citation consistency and reference formatting, and preparing selected visual elements in schematic figures based on author-developed concepts. All scientific decisions, including literature selection and interpretation, were made by the authors, who reviewed and edited all AI-assisted outputs and take full responsibility for the content of this publication.
Authors contribution
Wang XY, Yin FQ: Investigation; writing-original draft; writing-review & editing.
Kong QP: Conceptualization, methodology, supervision, writing-review & editing.
All authors have read and approved the final manuscript.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical approval
Not applicable.
Consent to participate
Not applicable.
Consent for publication
Not applicable.
Availability of data and materials
Not applicable.
Funding
This work was supported by the National Key R&D Program of China (Grant No. 2023YFC3603400), National Natural Science Foundation of China (Grant Nos. 82430049, 82371580, 82401833, and 82603050), and Yunnan Fundamental Research Projects (Grant Nos. 202201AS070080, 202301AT070281, and 202401AW070011).
Copyright
© The Author(s) 2026.
References
-
20. Foley MK, Searle SD, Toloue A, Booth R, Falkenham A, Falzarano D, et al. Centenarians and extremely old people living with frailty can elicit durable SARS-CoV-2 spike specific IgG antibodies with virus neutralization functions following virus infection as determined by serological study. EClinicalMedicine. 2021;37:100975.
-
23. Sansoni P, Cossarizza A, Brianti V, Fagnoni F, Snelli G, Monti D, et al. Lymphocyte subsets and natural killer cell activity in healthy old people and centenarians. Blood. 1993;82(9):2767-2773.[PubMed]
-
35. Fagnoni FF, Vescovini R, Passeri G, Bologna G, Pedrazzoni M, Lavagetto G, et al. Shortage of circulating naive CD8(+) T cells provides new insights on immunodeficiency in aging. Blood. 2000;95(9):2860-2868.[PubMed]
-
80. Bagnara GP, Bonsi L, Strippoli P, Bonifazi F, Tonelli R, D’Addato S, et al. Hemopoiesis in healthy old people and centenarians: Well-maintained responsiveness of CD34+ cells to hemopoietic growth factors and remodeling of cytokine network. J Gerontol A Biol Sci Med Sci. 2000;55(2):B61-B66.
Copyright
© The Author(s) 2027. This is an Open Access article licensed under a Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, sharing, adaptation, distribution and reproduction in any medium or format, for any purpose, even commercially, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons license, and indicate if changes were made.
Publisher’s Note
Science Exploration remains a neutral stance on jurisdictional claims in published
maps
and institutional affiliations. The views expressed in this article are solely those
of
the author(s) and do not reflect the opinions of the Editors or the publisher.
Share And Cite


Science Exploration Style
Wang XY, Yin FQ, Kong QP. Selective preservation of immune competence in human longevity: Youth-like cellular features and molecular support programs. Ageing Cancer Res Treat. 2027;4:202632. https://doi.org/10.70401/acrt.2026.0044
Tips
Copy completed.
Submit a Manuscript
Author Instructions
Cite this Article
Article Metrics
0
View
0
Download
Cited
Article Updates

- Abstract
- Keywords
- 1. Introduction
- 2. Comparative Immune Landscape and Interpretive Framework
- 3. Youth-Like Cellular Immune Features in Long-Lived Individuals
- 4. Molecular Programs Supporting Selectively Preserved Immune Competence
- 5. Conclusion and Perspectives
- Acknowledgements
- Authors contribution
- Conflicts of interest
- Ethical approval
- Consent to participate
- Consent for publication
- Availability of data and materials
- Funding
- References
- Copyright
 Get citation
Science Exploration Style

Wang XY, Yin FQ, Kong QP. Selective preservation of immune competence in human longevity: Youth-like cellular features and molecular support programs. Ageing Cancer Res Treat. 2027;4:202632. https://doi.org/10.70401/acrt.2026.0044
copy
Share Link
copy